 filings.tools
Quest Diagnostics 10-K 2019-12-31
Filed 2020-02-20. 22 sections, 507K characters. Original on sec.gov · Markdown · JSON
Cover and table of contents
UNITED STATES SECURITIES AND EXCHANGE COMMISSION
WASHINGTON, DC 20549
FORM 10-K
☒ ANNUAL REPORT PURSUANT TO SECTION 13 OR 15(D) OF THE SECURITIES EXCHANGE ACT OF 1934
For the Fiscal Year Ended December 31, 2019
Or
☐ TRANSITION REPORT PURSUANT TO SECTION 13 OR 15(D) OF THE SECURITIES EXCHANGE ACT OF 1934
For the transition period from __________ to __________
Commission File Number 001-12215
Quest Diagnostics Inc****orporated
| Delaware | 16-1387862 | ||||
| (State of Incorporation) | (I.R.S. Employer Identification Number) | ||||
| 500 Plaza Drive | |||||
| Secaucus, | NJ | 07094 | |||
| (973) | 520-2700 |
| Securities registered pursuant to Section 12(b) of the Act: | ||
| Title of Each Class | Trading Symbol(s) | Name of Each Exchange on Which Registered |
| Common Stock, $.01 par value | DGX | New York Stock Exchange |
| Securities registered pursuant to Section 12(g) of the Act: | None |
Indicate by check mark if the registrant is a well-known seasoned issuer, as defined in Rule 405 of the Securities Act.
Yes X No
Indicate by check mark if the registrant is not required to file reports pursuant to Section 13 or Section 15(d) of the Exchange Act.
Yes No X
Indicate by check mark whether the registrant: (1) has filed all reports required to be filed by Section 13 or 15(d) of the Securities Exchange Act of 1934 during the preceding 12 months (or for such shorter period that the registrant was required to file such reports), and (2) has been subject to such filing requirements for the past 90 days.
Yes X No
Indicate by check mark whether the registrant has submitted electronically every Interactive Data File required to be submitted pursuant to Rule 405 of Regulation S-T (§232.405 of this chapter) during the preceding 12 months (or for such shorter period that the registrant was required to submit such files).
Yes X No
Indicate by check mark whether the registrant is a large accelerated filer, an accelerated filer, a non-accelerated filer, a smaller reporting company, or an emerging growth company. See the definitions of “large accelerated filer,” “accelerated filer,” “smaller reporting company,” and "emerging growth company" in Rule 12b-2 of the Exchange Act.
| Large accelerated filer | ☒ | Accelerated filer | ☐ |
| Non-accelerated filer | ☐ | Smaller reporting company | ☐ |
| Emerging growth company | ☐ |
If an emerging growth company, indicate by check mark if the registrant has elected not to use the extended transition period for complying with any new or revised financial accounting standards provided pursuant to Section 13(a) of the Exchange Act. [ ]
Indicate by check mark whether the registrant is a shell company (as defined in Rule 12b-2 of the Exchange Act). Yes No X
As of June 30, 2019, the aggregate market value of the approximately 134 million shares of voting and non-voting common equity held by non-affiliates of the registrant was approximately $13.7 billion, based on the closing price on such date of the registrant's Common Stock on the New York Stock Exchange.
As of January 31, 2020, there were outstanding 133,455,068 shares of the registrant’s common stock, $.01 par value.
| Documents Incorporated by Reference | Part of Form 10-K into which incorporated |
| Document | |
| Portions of the registrant's Proxy Statement to be filed by April 29, 2020 | Part III |
Such Proxy Statement, except for the portions thereof which have been specifically incorporated by reference, shall not be deemed “filed” as part of this report on Form 10-K.
TABLE OF CONTENTS
i
The discussion in Item 1 below includes several defined terms:
ACA - Affordable Care Act
ACO - Accountable Care Organization
CAP - The College of American Pathologists
CLIA - Clinical Laboratory Improvement Act
CMS - Centers for Medicare and Medicaid Services
FDA - U.S. Food and Drug Administration
IDN - Independent Delivery Network (including hospital health systems)
IPA - Independent Physician Association
LAB Act - Laboratory Access for Beneficiaries Act
LDT - Laboratory-Developed Test
PAMA - The Protecting Access to Medicare Act of 2014
The discussion also includes several tables, indexed in the following guide.
| Guide to Tables | ||
| Services Portfolio | Table 1 | |
| Approaches to Accelerate Growth | Table 2 | |
| Key Professional Laboratory Services Offerings | Table 3 | |
| Clinical Franchises | Table 4 | |
| Consumer-Centric Initiatives | Table 5 | |
| Major Themes to Drive Operational Excellence | Table 6 | |
| Our Strengths | Table 7 | |
| Assets and Capabilities | Table 8 | |
| 2019 Net Revenues | Table 9 | |
| Clinical Testing Industry | Table 10 | |
| Key Trends | Table 11 | |
| Reducing Healthcare Costs and Improving Care | Table 12 | |
| Customers | Table 13 | |
| Potential Factors Considered When Selecting a Diagnostics Information Services Provider | Table 14 | |
| 2019 Medicare and Medicaid Revenues as % of Consolidated Net Revenues | Table 15 | |
| Key Regulatory Schemes | Table 16 | |
| Information Available at Our Corporate Governance Webpage | Table 17 | |
| Executive Officers | Table 18 |
Item 1. Business
INTRODUCTION
Quest Diagnostics Incorporated is the world's leading provider of diagnostic information services. We play a crucial role in the healthcare ecosystem, empowering people to take action to improve health outcomes. Derived from the world's largest database of clinical lab results, our diagnostic insights reveal new avenues to identify and treat disease, inspire healthy behaviors and improve health care management. In the right hands and with the right context, our diagnostic insights can inspire actions that transform lives.
Quest Diagnostics was incorporated in Delaware in 1990; its predecessor companies date back to 1967. We conduct business through our headquarters in Secaucus, New Jersey, and our laboratories, patient service centers, offices and other facilities around the United States and in selected locations outside the United States. Unless the context otherwise requires, the terms “Quest Diagnostics,” the “Company,” “we” and “our” mean Quest Diagnostics Incorporated and its consolidated subsidiaries.
The patients we serve comprise approximately one-third of the adult population of the United States annually, and approximately one-half of the adult population in the United States over a three-year period. We estimate that annually we serve approximately half of the physicians and half of the hospitals in the United States.
During 2019, we generated net revenues of $7.7 billion. Additional financial information concerning Quest Diagnostics, including our consolidated subsidiaries and businesses, for each of the years ended December 31, 2019, 2018 and 2017 is included in the consolidated financial statements and notes thereto in “Financial Statements and Supplementary Data” in Part II, Item 8.
Our vision, aspirational goals and values are set forth below.
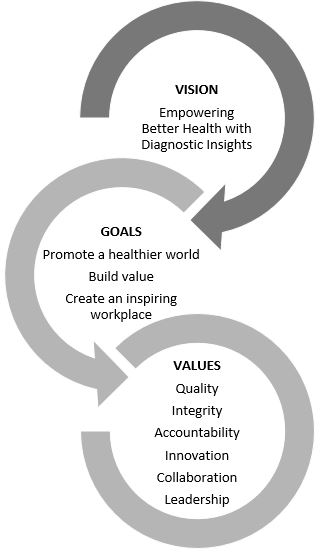
We believe that our vision, aspirational goals and strategy (discussed below) align very well with, and our strong value proposition supports, the triple aim of healthcare: improving medical quality and the patient experience while reducing the cost of care.
OUR STRATEGY
We have a two-point business strategy, reviewed by our Board of Directors, to achieve our vision and our goals.
Accelerate Growth
| Our strategy to accelerate revenue growth is based on the Company’s portfolio of services. | |||
| Services Portfolio (Table 1) | |||
| Activity | Key Characteristics | At A Glance | Quest Value Proposition |
| General Diagnostics | Testing services generating strong cash flows and steady growth | • Routine and non-routine testing services • Largest revenue stream • Essential portion of health care delivery | • Scale • Operational excellence • Access and convenience |
| Advanced Diagnostics | Testing services targeting faster growth through innovation testing model | • Genetic and advanced molecular testing services • An important part of precision medicine • Innovation-based competitors | • Rich clinical, scientific and medical innovation expertise • Quality and reliability of new assays • Ability to manage potential new regulatory requirements |
| Diagnostic Services | Laboratory and data-related healthcare opportunities targeting faster growth | • Enables partners to deliver health care more efficiently (e.g., risk assessment; Professional Laboratory Services; wellness) • Services to support population health (e.g., data analytics; extended care services) | • Extensive diagnostic capability • Large and growing database and analytics expertise • Partnerships with industry leaders across healthcare landscape |
| We have identified the following five approaches to accelerate growth. |
| Approaches to Accelerate Growth (Table 2) |
| 1. Delivering a compound annual revenue growth rate of more than 2% through accretive, strategic acquisitions |
| Plus organic growth through: |
| 2. Partnering with health plans, IDNs and other risk bearing entities |
| 3. Offering the broadest access to diagnostic innovation |
| 4. Being recognized as the consumer-friendly provider of choice of diagnostic information services |
| 5. Supporting population health with data analytics and extended care services |
1. Growing through acquisitions. We have maintained a strategy since November 2018 to grow revenue each year by more than 2% compound annual growth rate through accretive, strategic acquisitions. Our approach to acquisitions is discussed below under the heading Deliver disciplined capital deployment*.*
2. Partnering with health plans, IDNs and other risk bearing entities. To help accelerate growth, we focus on large opportunities to partner with outside entities. We strengthen our relationships with health plans and increase the volume of our services for their members by driving value with employers and providing strong value propositions for members and clinicians. This includes building an information platform to help health plans manage utilization and population health, and enhancing processes to help plans keep laboratory testing in network. Effective January 1, 2019, the Company established a long-term strategic partnership with UnitedHealthcare, including collaborating on a variety of value-based programs, became a preferred provider to Horizon Blue Cross Blue Shield of New Jersey for most products and became a participating provider to Blue Cross Blue Shield of Georgia. Effective July 1, 2019, the Company was selected to be one of only five lab companies named participants in the UnitedHealthcare Preferred Lab Network, meeting exceptional criteria for access, cost, data, quality and service.
We believe that the growing market challenges faced by IDNs, including continued price transparency, cost and utilization pressure, evolving healthcare payment models, capital needs, changing technology and limited resources, provides us with an opportunity to more effectively partner with them as they consider their laboratory testing strategy and will drive demand for our expertise. We have deployed a dedicated health systems team to strengthen our relationships with IDNs, including with respect to their reference testing. We provide reference testing for approximately 50% of hospitals in the U.S., and are the leading provider of this testing in the country. In 2019, we implemented new Professional Laboratory Services relationships with Catholic Health Services of Long Island and Regional Medical Center of Orangeburg, S.C.
| Our industry-leading Professional Laboratory Services suite of solutions help IDNs build and execute their laboratory strategy, improve quality, reduce the cost of care and focus on core competencies. | |
| Key Professional Laboratory Services Offerings (Table 3) | |
| Lab management outsourcing | Advanced data solutions |
| Joint venture | Reference testing, including advanced diagnostics |
| Outreach acquisition | Supply chain management and purchasing |
| Test menu optimization and spend consolidation | Blood utilization management |
- Offering the broadest access to diagnostic innovation. Our diagnostic solutions deliver high clinical value to the medical community nationwide. We create value through scientific and product innovation and solution delivery for major clinical opportunities. Starting with a clinical focus on a specific disease state or clinical problem, we take advantage of advanced technology for more precise, comprehensive and actionable information, and deliver the information to the medical community in a meaningful way. We make innovative diagnostic solutions available to community physicians through our connectivity solutions, operational footprint and by making
Showing the first 8K of 113K characters. Open the full section
Item 1A. Risk Factors
You should carefully consider all of the information set forth in this Report, including the following risk factors, before deciding to invest in any of our securities. The risks below are not the only ones that we face. Additional risks not presently known to us, or that we presently deem immaterial, may also negatively impact us. Our business, consolidated financial condition, revenues, results of operations, profitability, reputation or cash flows could be materially impacted by any of these factors.
| This Report also includes forward-looking statements that involve risks or uncertainties. Our results could differ materially from those anticipated in these forward-looking statements as a result of certain factors, including the risks we face described below and elsewhere. See “Cautionary Factors that May Affect Future Results” on page 37. |
The U.S. healthcare system is evolving and medical laboratory testing market fundamentals are changing, and our business could be adversely impacted if we fail to adapt.
The U.S. healthcare system is evolving, in part in response to the ACA. The ACA established the Center for Medicare and Medicaid Innovation to examine alternative payment methodologies and conduct demonstration programs. The ACA provided for extensive health insurance reforms, including the elimination of pre-existing condition exclusions and other limitations on coverage, fixed percentages on medical loss ratios, expansion in Medicaid and other programs, employer mandates, individual mandates, creation of state and regional health insurance exchanges, and tax subsidies for individuals to help cover the cost of individual insurance coverage. The ACA also permits the establishment of ACOs.
Certain aspects of the ACA have been repealed, delayed or modified. The scope and timing of any further legislation to repeal, amend, replace, or reform the rest of the ACA is uncertain, but if such legislation were to become law, it could have a significant impact on the U.S. healthcare system. In addition, uncertainty regarding the status of the ACA prior to any such repeal, amendment, replacement or reform could create uncertainty generally in the healthcare market.
Several federal courts have recently issued determinations that portions of the ACA are unconstitutional; those rulings are net yet final. Uncertainty about court rulings regarding the ACA could add to uncertainty in the healthcare market.
Significant change is taking place in the healthcare system, including as discussed above under the heading The Clinical Testing Industry, beginning on page 13. For example, value-based reimbursement is increasing (e.g., UnitedHealthcare's Preferred Lab Network); CMS has set goals for value-based reimbursement to be achieved. Patients are encouraged to take increased interest in and responsibility for, and often are bearing increased responsibility for payment for, their healthcare. Healthcare industry participants are evolving and consolidating. Healthcare services increasingly are being provided by non-traditional providers (e.g., physician assistants), in non-traditional venues (e.g., retail medical clinics, urgent care centers) and using new technologies (e.g., telemedicine, digital pathology). Utilization of the healthcare system is being influenced by several factors and may result in a decline in the demand for diagnostic information services.
In addition, we believe that clinical testing market fundamentals are changing. We believe that PAMA-driven reimbursement pressure is negatively impacting access to care and hurting the clinical testing industry, and remains a catalyst for structural change in the market. We also believe that our expanded health plan network access and increased health plan focus on driving better value in laboratory testing services will reduce variation in spending on these services. We also believe that ongoing consumerization in healthcare, with increased cost being borne by consumers, is sharpening focus on price disparities. We expect that the evolution of the healthcare industry will continue, and that industry change is likely to be extensive.
The clinical testing business is highly competitive, and if we fail to provide an appropriately priced level of service or otherwise fail to compete effectively it could have a material adverse effect on our revenues and profitability.
The clinical testing business remains a fragmented and highly competitive industry. We primarily compete with three types of clinical testing providers: other commercial clinical laboratories, hospital-affiliated laboratories and physician-office laboratories. We also compete with other providers, including anatomic pathology practices and large physician group practices. Hospitals generally maintain on-site laboratories to perform testing on their patients (inpatient or outpatient). In addition, many hospitals compete with commercial clinical laboratories for outreach (non-hospital patients) testing. Hospitals may seek to leverage their relationships with community clinicians and encourage the clinicians to send their outreach testing to the hospital's laboratory. As a result of this affiliation between hospitals and community clinicians, we compete against hospital-affiliated laboratories primarily based on quality and scope of service as well as pricing. In addition, hospitals that own physician practices may require the practices to refer testing to the hospital's laboratory. In recent years, there has been a trend of hospitals acquiring physician practices, increasing the percentage of physician practices owned by hospitals. Increased hospital ownership of physician practices may enhance clinician ties to hospital-affiliated laboratories and may strengthen their competitive position. The formation of ACOs and IDNs, and their approach to contracts with healthcare providers, in addition to the impact of informatics, also may increase competition to provide diagnostic information services.
The diagnostic information services industry also is faced with changing technology and new product introductions. Competitors may compete using advanced technology, including technology that enables more convenient or cost-effective testing. Digital pathology, still in an emerging state, is an example of this. Competitors also may compete on the basis of new service offerings. Competitors also may offer testing to be performed outside of a commercial clinical laboratory, such as (1) point-of-care testing that can be performed by physicians in their offices; (2) advanced testing that can be performed by hospitals in their own laboratories; and (3) home testing that can be carried out without requiring the services of outside providers.
Government payers, such as Medicare and Medicaid, have taken steps to reduce the utilization and reimbursement of healthcare services, including clinical testing services.
We face efforts by government payers to reduce utilization of and reimbursement for diagnostic information services. One example of this is increased use of prior authorization requirements. We expect efforts to reduce reimbursements, to impose more stringent cost controls and to reduce utilization of clinical test services will continue.
Pursuant to PAMA, CMS promulgated revised reimbursement rate schedules for 2018 - 2020 for clinical laboratory testing services provided under Medicare. Reimbursement rates for many clinical laboratory tests were reduced in 2018 and 2019 and are scheduled to be reduced again by approximately 10% in 2020 (rates, and reductions, vary by test). PAMA calls for further revision of the Medicare Clinical Laboratory Fee Schedule for years after 2020, based on future surveys of market rates; reimbursement rate reduction from 2021-23 is capped by PAMA at 15% annually. In late 2019, the LAB Act became law. The LAB Act provides an opportunity for reforms to PAMA by delaying PAMA's next data collection and reporting period until January 1, 2021 and by ordering a study to determine ways to improve future collection of more representative market rate data under PAMA.
In addition, CMS has adopted policies limiting or excluding coverage for clinical tests that we perform. We also provide physician services that are reimbursed by Medicare under a physician fee schedule, which is subject to adjustment on an annual basis. Medicaid reimbursement varies by state and is subject to administrative and billing requirements and budget pressures. The ACA includes further provisions that are designed to control utilization and payment levels.
In addition, over the last several years, the federal government has expanded its contracts with private health insurance plans for Medicare beneficiaries, called “Medicare Advantage” programs, and has encouraged such beneficiaries to switch from the traditional programs to the private programs. There has been growth of health insurance plans offering Medicare Advantage programs, and of beneficiary enrollment in these programs. States have mandated that Medicaid beneficiaries enroll in private managed care arrangements. In addition, state budget pressures have encouraged states to consider several courses of action that may impact our business, such as delaying payments, reducing reimbursement, restricting coverage eligibility, denying claims and service coverage restrictions.
From time to time, the federal government has considered whether competitive bidding could be used to provide clinical testing services for Medicare beneficiaries at attractive rates while maintaining quality and access to care. Congress periodically considers cost-saving initiatives. These initiatives have included coinsurance for clinical testing services, co-payments for clinical testing and further laboratory fee schedule reductions.
Health plans and other third parties have taken steps to reduce the utilization and reimbursement of health services, including clinical testing services.
We face efforts by non-governmental third-party payers, including health plans, to reduce utilization of and reimbursement for clinical testing services. Examples include increased use of prior authorization requirements and increased denial of coverage for services. Since the passage of ACA, there is increased market activity regarding alternative payment models, including bundled payment models. We expect continuing efforts by third-party payers, including in their rules, practices and policies, to reduce reimbursements, to impose more stringent cost controls and to reduce utilization of clinical testing services. ACOs and IDNs also may undertake efforts to reduce utilization of, or reimbursement for, diagnostic information services.
The healthcare industry has experienced a trend of consolidation among health insurance plans, resulting in fewer but larger insurance plans with significant bargaining power to negotiate fee arrangements with healthcare providers, including clinical testing providers. These health plans, and independent physician associations, may demand that clinical testing providers accept discounted fee structures or assume all or a portion of the financial risk associated with providing testing services to their members through capitated payment arrangements. Some health plans also are reviewing test coding, evaluating coverage decisions and requiring preauthorization of certain testing. There are also an increasing number of patients enrolling in consumer driven products and high deductible plans that involve greater patient cost-sharing.
The increased consolidation among health plans also has increased pricing transparency and bargaining power and the potential adverse impact of ceasing to be a contracted provider with any such insurer.
Government payers and third parties, including health plans, may not recognize the value of, or compensate or reimburse us for, new and innovative solutions.
Government payers and third parties, including health plans, are taking steps to reduce utilization of, and reimbursement for, some new and innovative healthcare solutions, including new tests and other solutions that we may offer.
In response to requests from payers to have a strategy to report a single or at most a few codes to describe procedures used to perform molecular and toxicology testing, the American Medical Association CPT® Editorial Panel has established and replaced billing codes used to report those procedures. The adoption of these revised codes has resulted in limited coverage decisions on certain occasions, new requirements for documentation to facilitate payment from certain payers and increased payment denials. While some payers have adopted the new payment methods, others have not yet modified their systems and ask that laboratories continue to report their services using the previous reporting strategies, when those codes still exist.
These steps may discourage innovation and access to innovative solutions that we may offer.
Our business operations and reputation may be materially impaired if we do not comply with privacy laws or information security policies.
In our business, we collect, generate, process or maintain sensitive information, such as patient data and other personal information. If we do use or not adequately safeguard that information in compliance with applicable requirements under federal, state and international laws, or if it were disclosed to persons or entities that should not have access to it, our business could be materially impaired, our reputation could suffer and we could be subject to fines, penalties and litigation. In the event of a data security breach, we may be subject to notification obligations, litigation and governmental investigation or sanctions, and may suffer reputational damage, which could have an adverse impact on our business.
We are subject to laws and regulations regarding protecting the security and privacy of certain healthcare and personal information, including: (a) the federal Health Insurance Portability and Accountability Act and the regulations thereunder, which establish (i) a complex regulatory framework including requirements for safeguarding protected health information and (ii) comprehensive federal standards regarding the uses and disclosures of protected health information; (b) state laws, including the California Consumer Privacy Act; and (c) the European Union's General Data Protection Regulation.
Our business could be negatively affected if we are unable to continue to improve our efficiency.
It is important that we continue to improve our efficiency to enable us to mitigate the impact on our profitability of steps taken by government payers and health insurers to reduce the utilization and reimbursement of healthcare services, including diagnostic information services.
Business development activities are inherently risky and integrating our operations with businesses we acquire may be difficult.
We plan selectively to enhance our business from time to time through business development activities, such as acquisitions, licensing arrangements, investments and alliances. However, these plans are subject to the availability of appropriate opportunities and competition from other companies seeking similar opportunities. Moreover, the success of any such effort may be affected by a number of factors, including our ability to properly assess and value the potential business opportunity, and to integrate it into our business. The success of our strategic alliances depends not only on our contributions and capabilities, but also on the property, resources, efforts and skills contributed by our strategic partners. Further, disputes may arise with strategic partners, due to conflicting priorities or conflicts of interests.
Acquisitions are not all the same (e.g., asset acquisitions differ from acquisitions of equity interests); different acquisitions offer different risks. Acquisitions may involve the integration of a separate company that has different systems, processes, policies and cultures. Integration of acquisitions involves a number of risks including the diversion of management's attention to the assimilation of the operations of assets or businesses we have acquired, difficulties in the integration of operations and systems and the realization of potential operating synergies, the assimilation and retention of the personnel of the acquired businesses, challenges in retaining the customers of the combined businesses, and potential adverse effects on operating results. The process of combining acquisitions may be disruptive to our businesses and may cause an interruption of, or a loss of momentum in, such businesses as a result of the following difficulties, among others:
| • | loss of key customers or employees; |
| • | difficulty in standardizing information and other systems; |
| • | difficulty in consolidating facilities and infrastructure; |
| • | failure to maintain the quality or timeliness of services that our Company has historically provided; |
| • | diversion of management's attention from the day-to-day business of our Company as a result of the need to deal with the foregoing disruptions and difficulties; and |
| • | the added costs of dealing with such disruptions. |
If we are unable successfully to integrate strategic acquisitions in a timely manner, our business and our growth strategies could be negatively affected. Even if we are able to successfully complete the integration of the operations of other assets or businesses we may acquire in the future, we may not be able to realize all or any of the benefits that we expect to result from such integration, either in monetary terms or in a timely manner.
We are subject to numerous legal and regulatory requirements governing our activities, and we may face substantial fines and penalties, and our business activities may be impacted, if we fail to comply.
Our business is subject to or impacted by extensive and frequently changing laws and regulations in the United States (including at both the federal and state levels) and the other jurisdictions in which we engage in business. While we seek to conduct our business in compliance with all applicable laws, many of the laws and regulations applicable to us are vague or indefinite and have not been interpreted by the courts, including many of those relating to:
| • | billing and reimbursement of clinical testing; |
| • | certification or licensure of clinical laboratories; |
| • | the anti-self-referral and anti-kickback laws and regulations; |
| • | the laws and regulations administered by the FDA; |
| • | the corporate practice of medicine; |
| • | operational, personnel and quality requirements intended to ensure that clinical testing services are accurate, reliable and timely; |
| • | physician fee splitting; |
| • | relationships with physicians and hospitals; |
| • | safety and health of laboratory employees; and |
| • | handling, transportation and disposal of medical specimens, infectious and hazardous waste and radioactive materials. |
These laws and regulations may be interpreted or applied by a prosecutorial, regulatory or judicial authority in a manner that could require us to make changes in our operations, including our pricing and/or billing practices. We may not be able to maintain, renew or secure required permits, licenses or any other regulatory approvals needed to operate our business or commercialize our services. If we fail to comply with applicable laws and regulations, or if we fail to maintain, renew or obtain necessary permits, licenses and approvals, we could suffer civil and criminal penalties, fines, exclusion from participation in governmental healthcare programs and the loss of various licenses, certificates and authorizations necessary to operate our business, as well as incur additional liabilities from third-party claims. If any of the foregoing were to occur, our reputation could be damaged and important business relationships with third parties could be adversely affected.
We regularly receive requests for information, and occasionally subpoenas, from governmental authorities. We also are subject from time to time to qui tam claims brought by former employees or other “whistleblowers.” The federal and state governments continue aggressive enforcement efforts against perceived healthcare fraud. Legislative provisions relating to healthcare fraud and abuse provide government enforcement personnel substantial funding, powers, penalties and remedies to pursue suspected cases of fraud and abuse. In addition, the government has substantial leverage in negotiating settlements since the amount of potential damages far exceeds the rates at which we are reimbursed for our services, and the government has the remedy of excluding a non-compliant provider from participation in the Medicare and Medicaid programs. Regardless of merit or eventual outcome, these types of investigations and related litigation can result in:
| • | diversion of management time and attention; |
| • | expenditure of large amounts of cash on legal fees, costs and payment of damages; |
| • | increases to our administrative, billing or other operating costs; |
| • | limitations on our ability to continue some of our operations; |
| • | enforcement actions, fines and penalties or the assertion of private litigation claims and damages; |
| • | decreases to the amount of reimbursement related to diagnostic information services performed; |
| • | adverse affects to important business relationships with third parties; |
| • | decreased demand for our services; and/or |
| • | injury to our reputation. |
Changes in applicable laws and regulations may result in existing practices becoming more restricted, or subject our existing or proposed services to additional costs, delay, modification, withdrawal or reconsideration. Such changes also could require us to modify our business objectives.
Our business could be adversely impacted by the FDA's approach to regulation.
The FDA has regulatory responsibility over, among other areas, instruments, software, test kits, reagents and other devices used by clinical laboratories to perform diagnostic testing in the U.S. A number of tests we develop internally are offered as LDTs. The FDA has claimed regulatory authority over all LDTs, but has stated that it exercised enforcement discretion with regard to most LDTs performed by high complexity CLIA-certified laboratories.
As the FDA moves to regulate more clinical laboratory testing, its approach to regulation is impacting industry practices and participants, new competitors may enter the industry, and competition may come in new forms.
Legislation introduced in Congress would enable the FDA to regulate LDTs, in vitro diagnostics, software and other items used in the diagnosis of disease. If the legislation becomes law, the FDA could regulate diagnostic tests and components and platforms used as part of these tests. If the legislation becomes law, it could have a significant impact on the clinical laboratory testing industry, including regulating LDTs in new ways, while creating avenues of opportunity and competition regarding clinical laboratory testing. New competitors may enter the industry, and competition may come in new forms.
Pursuant to the 21st Century Cures Act, the FDA issued final guidance regarding its position on the regulation of clinical decision software, which may be used in connection with LDTs. The guidance attempts to clarify whether FDA approval of certain software is required. In January 2019 the FDA issued a draft guidance on a pre-certification pilot program to help software developers have a speedier and less restrictive path to clearance or approval of their software.
Failure to accurately bill for our services, or to comply with applicable laws relating to government healthcare programs, could have a material adverse effect on our business.
Billing for diagnostic information services is complex and subject to extensive and non-uniform rules and administrative requirements. Depending on the billing arrangement and applicable law, we bill various payers, such as patients, insurance companies, Medicare, Medicaid, clinicians, hospitals and employer groups. The majority of billing and related operations for our Company are being provided by a third party under the Company's oversight. Failure to accurately bill for our services could have a material adverse effect on our business. In addition, failure to comply with applicable laws relating to billing government healthcare programs may result in various consequences, including: civil and criminal fines and penalties, exclusion from participation in governmental healthcare programs and the loss of various licenses, certificates and authorizations necessary to operate our business, as well as incur additional liabilities from third-party claims, all of which could have a material adverse effect on our business. Certain violations of these laws may also provide the basis for a civil remedy under the federal False Claims Act, including fines and damages of up to three times the amount claimed. The qui tam provisions of the federal False Claims Act and similar provision in certain state false claims acts allow private individuals to bring lawsuits against healthcare companies on behalf of government payers, private payers and/or patients alleging inappropriate billing practices.
Although we believe that we are in compliance, in all material respects, with applicable laws and regulations, there can be no assurance that a regulatory agency or tribunal would not reach a different conclusion. The federal or state government may bring claims based on our current practices, which we believe are lawful. The federal and state governments have substantial leverage in negotiating settlements since the amount of potential damages and fines far exceeds the rates at which we are reimbursed, and the government has the remedy of excluding a non-compliant provider from participation in the Medicare and Medicaid programs. We believe that federal and state governments continue aggressive enforcement efforts against perceived healthcare fraud. Legislative provisions relating to healthcare fraud and abuse provide government enforcement personnel with substantial funding, powers, penalties and remedies to pursue suspected cases of fraud and abuse.
Hardware and software failures or delays in our information technology systems, including failures resulting from our systems conversions or otherwise, could disrupt our operations and cause the loss of confidential information, customers and business opportunities or otherwise adversely impact our business.
IT systems are used extensively in virtually all aspects of our business, including clinical testing, test reporting, billing, customer service, logistics and management of medical data. Our success depends, in part, on the continued and uninterrupted performance of our IT systems. A failure or delay in our IT systems could impede our ability to serve our customers and patients and protect their confidential personal data. Despite redundancy and backup measures and precautions that we have implemented, our IT systems may be vulnerable to damage, disruptions and shutdown from a variety of sources, including telecommunications or network failures, system conversion or standardization initiatives, human acts and natural disasters. These issues can also arise as a result from failures by third parties with whom we do business and for which we have limited control. Any disruption or failure of our IT systems could have a material impact on our ability to serve our customers and patients, including negatively affecting our reputation in the marketplace.
The IT systems that we rely on may be subject to unauthorized tampering, cyberattack or other security breach.
Our IT systems are subject to potential cyberattacks, tampering or other security breaches. These attacks, if successful, could result in shutdowns or significant disruptions of our IT systems and/or in unauthorized persons misappropriating intellectual property and other confidential information, including patient data that we obtain, transmit and store on and through our IT systems.
External actors may develop and deploy viruses and other malicious software programs, including those that target our employees, designed to attack our IT systems or otherwise exploit security vulnerabilities, such as electronic spamming, phishing, spear phishing or similar tactics. As a result of the difficulty in detecting many of these attacks, intrusions and breaches, failures or losses may be repeated or compounded before they are discovered or rectified, which could further increase these costs and consequences. In December 2016, we reported that an internet application on our IT network had been the target of an external cyberattack, resulting in the theft of certain patient data. The accessed data did not include Social Security numbers, credit card information, or insurance and other financial information, and there is no indication that patient data has been misused in any way. When the intrusion was discovered, we immediately took steps to stop any further unauthorized activity.
From time to time, our IT systems have experienced other attacks, viruses, attempted intrusions or similar problems, but each was mitigated. None materially disrupted, interrupted, damaged or shutdown the company's IT systems, materially disrupted the Company's performance of its business or, to the Company's knowledge, resulted in material unauthorized access to data.
In addition, certain third parties to whom we outsource certain of our services or functions, or with whom we interface, store our confidential patient data or other confidential information, as well as those third parties’ providers, are also subject to the risks outlined above. A breach or attack affecting these third parties could also harm our business, results of operations and reputation and subject us to liability.
On June 3, 2019, the Company reported that Retrieval-Masters Creditors Bureau, Inc./American Medical Collection Agency (“AMCA”), informed the Company and Optum360 LLC, which provides revenue management services to the Company, about a data security incident involving AMCA (the “AMCA Data Security Incident”). AMCA (which provided debt collection services for Optum360) informed the Company and Optum360 that AMCA had learned that an unauthorized user had access to AMCA’s system between August 1, 2018 and March 30, 2019. AMCA first informed the Company of the AMCA Data Security Incident on May 14, 2019. AMCA’s affected system included financial information (e.g., credit card numbers and bank account information), medical information and other personal information (e.g., social security numbers). Test results were not included. Neither Optum360’s nor the Company’s systems or databases were involved in the incident. AMCA has also informed us that information pertaining to other laboratories’ customers was also affected.
Although the Company has robust security measures implemented, which are monitored and routinely tested both by internal resources and external parties, cyber threats against us or our third party providers continue to evolve and are often not recognized until such attacks are launched against a potential target. There can be no assurance that the Company or its third party providers can anticipate all such evolving future attacks, viruses or intrusions, implement adequate preventative measures, nor remediate any security vulnerabilities. Such breaches could expose our or our third party providers' IT systems to attack, which could result in major disruption of our business, and compromise our customer’s confidential information, result in litigation and potential liability for the Company, government investigation, significant damage to our reputation or otherwise adversely affect our business. Any mitigation or remediation efforts that we undertake may require expenditures of significant resources and the diversion of the attention of management.
We have taken, and continue to take, precautionary measures to reduce the risk of, and detect and respond to, future cyber threats, and prevent or minimize vulnerabilities in our IT systems, including the loss or theft of intellectual property, patient data or other confidential information that we obtain and store on our systems. We also have taken, and will continue to take, measures to assess the cybersecurity protections used by our third-party providers. In addition, we collaborate with government agencies regarding potential cyber threats and have worked with a leading cyber security firm to evaluate and strengthen our systems. There can be no assurances that our precautionary measures or measures used by our third-party providers will prevent, contain or successfully defend against cyber or information security threats that could have a significant impact on our business, results of operations and reputation and subject us to liability.
Failure to develop, or acquire licenses for, new tests, technology and services could negatively impact our testing volume and revenues.
The diagnostic information services industry is faced with changing technology and new product introductions. Other companies or individuals, including our competitors, may obtain patents or other property rights that would prevent, limit or interfere with our ability to develop, perform or sell our solutions or operate our business or increase our costs. In addition, they could introduce new tests, technologies or services that may result in a decrease in the demand for our services or cause us to reduce the prices of our services. Our success in continuing to introduce new solutions, technology and services will depend, in part, on our ability to license new and improved technologies on favorable terms. We may be unable to develop or introduce new solutions or services. Other companies or individuals, including our competitors, may obtain patents or other property rights on tests or processes that we may be performing, that could prevent, limit or interfere with our ability to develop, perform or sell our tests or operate our business. We also may be unable to continue to negotiate acceptable licensing arrangements, and arrangements that we do conclude may not yield commercially successful clinical tests. If we are unable to license these testing methods at competitive rates, our research and development costs may increase as a result. In addition, if we are unable to develop and introduce, or license, new solutions, technology and services to expand our advanced testing capabilities, our services may become outdated when compared with our competition.
We may be unable to obtain, maintain or enforce our intellectual property rights and may be subject to intellectual property litigation that could adversely impact our business.
We may be unable to obtain or maintain adequate patent or other proprietary rights for our solutions or services or to successfully enforce our proprietary rights. In addition, we may be subject to intellectual property litigation and we may be found to infringe on the proprietary rights of others, which could force us to do one or more of the following:
| • | cease developing, performing or selling solutions or services that incorporate the challenged intellectual property; |
| • | obtain and pay for licenses from the holder of the infringed intellectual property right; |
| • | redesign or re-engineer our tests; |
| • | change our business processes; or |
| • | pay substantial damages, court costs and attorneys' fees, including potentially increased damages for any infringement held to be willful. |
The development of new technologies (including artificial intelligence technologies) may impact the healthcare industry, and the development of new, more cost-effective solutions that can be performed by our customers or by patients, and the continued internalization of testing by hospitals or clinicians, could negatively impact our testing volume and revenues.
The diagnostic information services industry is faced with changing technology and new product introductions, including technology that enables more convenient or cost-effective testing. For example, digital pathology is an emerging technology that may change the practice of pathology. Information technology that includes self-learning or "artificial intelligence" features is growing and may impact the healthcare industry.
Competitors also may offer testing to be performed outside of a commercial clinical laboratory, such as (1) point-of-care testing that can be performed by clinicians in their offices; (2) complex testing that can be performed by hospitals in their own laboratories; and (3) home testing that can be carried out without requiring the services of outside providers. Advances in technology also may lead to the need for less frequent testing. Further, diagnostic tests approved or cleared by the FDA for home use are automatically deemed to be “waived” tests under CLIA and may be performed by patients in their homes; test kit manufacturers could seek to increase sales to patients of such test kits.
Some traditional customers for anatomic pathology services, including specialty physicians that generate biopsies through surgical procedures, such as dermatologists, gastroenterologists, urologists and oncologists, are consolidating, have added in-office histology labs or have retained pathologists to read cases on site. Hospitals also are internalizing clinical laboratory testing, including some non-routine and advanced testing. Internalization of testing may reduce demand for services previously referred to outside service providers, such as the Company.
Our outstanding debt may impair our financial and operating flexibility.
As of December 31, 2019, we had approximately $4.8 billion of debt outstanding. We do not have any off-balance sheet financing arrangements in place or available. Our debt agreements contain various restrictive covenants. These restrictions could limit our ability to use operating cash flow in other areas of our business because we must use a portion of these funds to make principal and interest payments on our debt. We have obtained ratings on our public debt from Standard and Poor's, Moody's Investor Services and Fitch Ratings. There can be no assurance that any rating so assigned will remain for any given period of time or that a rating will not be lowered or withdrawn entirely by a rating agency if in that rating agency's judgment future circumstances relating to the basis of the rating, such as adverse changes in our Company or our industry, so warrant. If such ratings are lowered, our borrowing costs could increase. Changes in our credit ratings, however, do not require repayment or acceleration of any of our debt.
We or our subsidiaries may incur additional indebtedness in the future. Our ability to make principal and interest payments will depend on our ability to generate cash in the future. If we incur additional debt, a greater portion of our cash flows may be needed to satisfy our debt service obligations and if we do not generate sufficient cash to meet our debt service requirements, we may need to seek additional financing. In that case, it may be more difficult, or we may be unable, to obtain financing on terms that are acceptable to us. As a result, we would be more vulnerable to general adverse economic, industry and capital markets conditions as well as the other risks associated with indebtedness.
Our ability to attract and retain qualified employees is critical to the success of our business and the failure to do so may materially adversely affect our performance.
Our people are a critical resource. The supply of qualified personnel may be limited and competition for qualified employees is strong. We may lose, or fail to attract and retain, key management personnel, or qualified skilled technical or professional employees (e.g., pathologists).
Failure to establish, and perform to, appropriate quality standards to assure that the appropriate standard of quality is observed in the performance of our diagnostic information services could adversely affect the results of our operations and adversely impact our reputation.
The provision of diagnostic information services involves certain inherent risks. The services that we provide are intended to provide information for healthcare providers in providing patient care. Therefore, users of our services may have a greater sensitivity to errors than the users of services or products that are intended for other purposes.
Negligence in performing our services can lead to injury or other adverse events. We may be sued under physician liability or other liability law for acts or omissions by our pathologists, laboratory personnel and hospital employees who are under the supervision of our hospital-based pathologists. We are subject to the attendant risk of substantial damages awards and risk to our reputation.
We are subject to numerous political, legal, operational and other risks as a result of our international operations which could impact our business in many ways.
Our international operations increase our exposure to risks inherent in doing business in non-U.S. markets, which may vary by market and include: intellectual property legal protections and remedies; weak legal systems which may affect our ability to enforce contractual rights; trade regulations and procedures and actions affecting approval, production, pricing,
reimbursement and marketing of services; and challenges based on differing languages and cultures. International operations also require us to devote significant management resources to implement our controls and systems in new markets, and to comply with the U.S. Foreign Corrupt Practices Act and similar anti-corruption laws in non-U.S. jurisdictions.
Our operations may be adversely impacted by the effects of natural disasters such as hurricanes and earthquakes, public health emergencies and health pandemics, hostilities or acts of terrorism and other criminal activities.
Our operations may be adversely impacted by the effects of natural disasters such as hurricanes and earthquakes, public health emergencies and health pandemics, hostilities or acts of terrorism or other criminal activities. Such events may result in a decline in the number of patients who seek clinical testing services or in our employees' ability to perform their job duties. In addition, such events may interrupt our ability to transport specimens, to receive materials from our suppliers or otherwise to provide our services.
Adverse results in material litigation could have an adverse financial impact and an adverse impact on our client base and reputation.
We are involved in various legal proceedings arising in the ordinary course of business including, among other things, disputes as to intellectual property, professional liability and employee-related matters, as well as inquiries from governmental agencies and Medicare or Medicaid carriers. Some proceedings against us involve claims that are substantial in amount and could divert management's attention from operations. These proceedings also may result in substantial monetary damages.
CAUTIONARY FACTORS THAT MAY AFFECT FUTURE RESULTS
Some statements and disclosures in this document are forward-looking statements. Forward-looking statements include all statements that do not relate solely to historical or current facts and can be identified by the use of words such as “may,” “believe,” “will,” “expect,” “project,” “estimate,” “anticipate,” “plan” or “continue.” These forward-looking statements are based on our current plans and expectations and are subject to a number of risks and uncertainties that could cause our plans and expectations, including actual results, to differ materially from the forward-looking statements. Investors are cautioned not to unduly rely on such forward-looking statements when evaluating the information presented in this document. The following important factors could cause our actual financial results to differ materially from those projected, forecasted or estimated by us in forward-looking statements:
| (a) | Heightened competition from commercial clinical testing companies, hospitals, physicians and others. |
| (b) | Increased pricing pressure from customers, including payers and patients. |
| (c) | A decline in economic conditions. |
| (d) | Impact of changes in payment mix, including increased patient financial responsibility and any shift from fee-for-service to discounted, capitated or bundled fee arrangements. |
| (e) | Adverse actions by government or other third-party payers, including healthcare reform that focuses on reducing healthcare costs but does not recognize the value and importance to healthcare of clinical testing or innovative solutions, unilateral reduction of fee schedules payable to us, unilateral recoupment of amounts allegedly owed and competitive bidding. |
| (f) | The impact upon our testing volume and collected revenue or general or administrative expenses resulting from compliance with policies and requirements imposed by Medicare, Medicaid and other third-party payers. These include: |
| (1) | the requirements of government and other payers to provide diagnosis codes and other information for many tests; |
| (2) | inability to obtain from patients a valid advance consent form for tests that cannot be billed without prior receipt of the form; |
| (3) | the impact of additional or expanded limited coverage policies and limits on the allowable number of test units or ordering frequency of same; and |
| (4) | the impact of increased prior authorization programs. |
| (g) | Adverse results from pending or future government investigations, lawsuits or private actions. These include, in particular, monetary damages, loss or suspension of licenses, and/or suspension or exclusion from the Medicare and Medicaid programs and/or criminal penalties. |
| (h) | Failure to efficiently integrate acquired businesses and to manage the costs related to any such integration, or to retain key technical, professional or management personnel. |
| (i) | Denial, suspension or revocation of CLIA certification or other licenses for any of our clinical laboratories under the CLIA standards, revocation or suspension of the right to bill the Medicare and Medicaid programs or other adverse regulatory actions by federal, state and local agencies. |
| (j) | Changes in and complexity of federal, state or local laws or regulations, including changes that result in new or increased federal or state regulation of commercial clinical laboratories, tests developed by commercial clinical laboratories or other products or services that we offer or activities in which we are engaged, including regulation by the FDA. |
| (k) | Inability to achieve expected benefits from our acquisitions of other businesses. |
| (l) | Inability to achieve additional benefits from our business performance tools and efficiency initiatives. |
| (m) | Adverse publicity and news coverage about the diagnostic information services industry or us. |
| (n) | Failure of the Company to maintain, defend and secure its financial, accounting, technology, customer data and other operational systems from cyberattacks, IT system outages, telecommunications failures, malicious human acts and failure of the systems of third parties upon which the Company relies. |
| (o) | Development of technologies that substantially alter the practice of clinical testing, including technology changes that lead to the development of more convenient or cost-effective testing, or testing to be performed outside of a commercial clinical laboratory, such as (1) point-of-care testing that can be performed by physicians in their offices, (2) advanced testing that can be performed by hospitals in their own laboratories or (3) home testing that can be carried out without requiring the services of clinical laboratories. |
| (p) | Negative developments regarding intellectual property and other property rights that could prevent, limit or interfere with our ability to develop, perform or sell our tests or operate our business. These include: |
| (1) | Issuance of patents or other property rights to our competitors or others; and |
| (2) | Inability to obtain or maintain adequate patent or other proprietary rights for our products and services or to successfully enforce our proprietary rights. |
| (q) | Development of tests by our competitors or others which we may not be able to license, or usage (or theft) of our technology or similar technologies or our trade secrets or other intellectual property by competitors, any of which could negatively affect our competitive position. |
| (r) | Regulatory delay or inability to commercialize newly developed or licensed tests or technologies or to obtain appropriate reimbursements for such tests. |
| (s) | The complexity of billing and revenue recognition for clinical laboratory testing. |
| (t) | Changes in interest rates and changes in our credit ratings from Standard & Poor's, Moody's Investor Services or Fitch Ratings causing an unfavorable impact on our cost of and access to capital. |
| (u) | Inability to hire or retain qualified or key senior management personnel. |
| (v) | Terrorist and other criminal activities, hurricanes, earthquakes or other natural disasters, and public health emergencies and health pandemics, which could affect our customers or suppliers, transportation or systems, or our facilities, and for which insurance may not adequately reimburse us. |
| (w) | Difficulties and uncertainties in the discovery, development, regulatory environment and/or marketing of new services or solutions or new uses of existing tests. |
| (x) | Failure to adapt to changes in the healthcare system (including the medical laboratory testing market) and healthcare delivery, including those stemming from the ACA (or its repeal, amendment or replacement), PAMA, trends in utilization of the healthcare system and increased patient financial responsibility for services. |
| (y) | Results and consequences of governmental inquiries. |
(z) Difficulty in implementing, or lack of success with, our strategic plan.
(aa) The impact of informatics on our industry and the ability of our Company to adapt to that impact.
(bb) Failure to adequately operationalize appropriate controls around use of our data, including risk of non-compliance with privacy law requirements.
Item 1B. Unresolved Staff Comments
There are no unresolved SEC comments that require disclosure.
Item 2. Properties
Our executive offices are located in Secaucus, New Jersey. We maintain clinical testing laboratories throughout the continental United States; in several instances a joint venture of which we are a partner maintains the laboratory. We also maintain offices, data centers, call centers, distribution centers and patient service centers at locations throughout the United States. In addition, we maintain offices, patient service centers and clinical laboratories in locations outside the United States, including in Puerto Rico and Mexico. Our properties that are not owned are leased on terms and for durations that are reflective of commercial standards in the communities where these properties are located. We believe that, in general, our facilities are suitable and adequate for our current and anticipated future levels of operation and are adequately maintained. We believe that if we were unable to renew a lease on any of our facilities, we could find alternative space at competitive market
rates and relocate our operations to such new location without material disruption to our business. Several of our principal facilities are highlighted below.
| Location | Leased or Owned | |
| Sacramento, California (laboratory) | Leased | |
| West Hills, California (laboratory) | Leased | |
| San Juan Capistrano, California (laboratory) | Owned | |
| Tampa, Florida (laboratory) | Owned | |
| Atlanta, Georgia (laboratory) | Owned | |
| Chicago, Illinois (2) (laboratories) | One owned, one leased | |
| Marlborough, Massachusetts (laboratories) | Leased | |
| Baltimore, Maryland (laboratory) | Owned | |
| Teterboro, New Jersey (laboratory) | Leased | |
| Philadelphia, Pennsylvania (laboratory) | Leased | |
| Dallas, Texas (laboratory) | Leased | |
| Chantilly, Virginia (laboratory) | Leased | |
| Lenexa, Kansas (laboratory) | Owned | |
| Greensboro, North Carolina (laboratory) | Leased | |
| Lewisville, Texas (laboratory) | Leased | |
| Cleveland, Ohio (laboratory) | Leased |
Item 3. Legal Proceedings
See Note 18 to the Consolidated Financial Statements (Part II, Item 8 of this Report) for information regarding legal proceedings in which we are involved.
Item 4. Mine Safety Disclosures
Not applicable.
PART II
Item 5. Market for Registrant's Common Equity, Related Stockholder Matters and Issuer Purchases of Equity Securities
Our common stock is listed and traded on the New York Stock Exchange under the symbol “DGX.” As of February 1, 2020, we had approximately 2,500 record holders of our common stock; we believe that the number of beneficial holders of our common stock exceeds the number of record holders.
The table below sets forth the information with respect to purchases made by or on behalf of the Company of its common stock during the fourth quarter of 2019.
| ISSUER PURCHASES OF EQUITY SECURITIES | ||||||||||||||
| Period | Total Number of Shares Purchased | Average Price Paid per Share | Total Number of Shares Purchased as Part of Publicly Announced Plans or Programs | Approximate Dollar Value of Shares that May Yet Be Purchased Under the Plans or Programs (in thousands) | ||||||||||
| October 1, 2019 – October 31, 2019 | ||||||||||||||
| Share Repurchase Program (A) | 361,966 | $ | 101.22 | 361,966 | $ | 405,493 | ||||||||
| Employee Transactions (B) | 536 | $ | 104.19 | N/A | N/A | |||||||||
| November 1, 2019 – November 30, 2019 | ||||||||||||||
| Share Repurchase Program (A) | 947,325 | $ | 103.32 | 947,325 | $ | 1,307,613 | ||||||||
| Employee Transactions (B) | 164 | $ | 102.48 | N/A | N/A | |||||||||
| December 1, 2019 – December 31, 2019 | ||||||||||||||
| Share Repurchase Program (A) | 617,067 | $ | 106.11 | 617,067 | $ | 1,242,138 | ||||||||
| Employee Transactions (B) | 769 | $ | 107.25 | N/A | N/A | |||||||||
| Total | ||||||||||||||
| Share Repurchase Program (A) | 1,926,358 | $ | 103.82 | 1,926,358 | $ | 1,242,138 | ||||||||
| Employee Transactions (B) | 1,469 | $ | 105.60 | N/A | N/A |
| (A) | Since the share repurchase program's inception in May 2003, our Board of Directors has authorized $9 billion of share repurchases of our common stock through December 31, 2019. The share repurchase authority has no set expiration or termination date. |
| (B) | Includes: (1) shares delivered or attested to in satisfaction of the exercise price and/or tax withholding obligations by holders of stock options (granted under the Company's Amended and Restated Employee Long-Term Incentive Plan) who exercised options; and (2) shares withheld (under the terms of grants under the Long-Term Incentive Plan) to offset tax withholding obligations that occur upon the delivery of outstanding common shares underlying restricted share units and performance share units. |
Performance Graph
Set forth below is a line graph comparing the cumulative total shareholder return on Quest Diagnostics' common stock since December 31, 2014 based on the market price of the Company's common stock and assuming reinvestment of dividends, with the cumulative total shareholder return of companies on the Standard & Poor's 500 Stock Index and the S&P 500 Healthcare Equipment & Services Index.
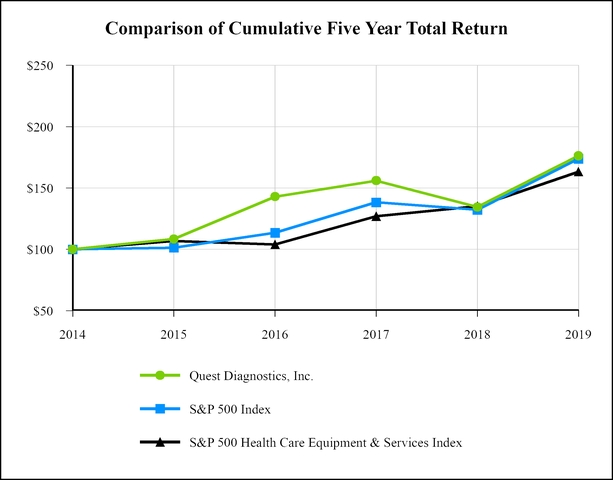
| Closing DGX Price | Total Shareholder Return | Performance Graph Values | |||||||||||||||||||||||
| Date | DGX | S&P 500 | S&P 500 H.C. | DGX | S&P 500 | S&P 500 H.C. | |||||||||||||||||||
| 12/31/2015 | $ | 71.14 | 8.35 | % | 1.38 | % | 6.89 | % | $ | 108.35 | $ | 101.38 | $ | 106.89 | |||||||||||
| 12/31/2016 | $ | 91.90 | 31.89 | % | 11.96 | % | (2.69 | )% | $ | 142.91 | $ | 113.51 | $ | 104.01 | |||||||||||
| 12/30/2017 | $ | 98.49 | 9.16 | % | 21.83 | % | 22.08 | % | $ | 156.00 | $ | 138.29 | $ | 126.98 | |||||||||||
| 12/29/2018 | $ | 83.27 | (13.84 | )% | (4.38 | )% | 6.47 | % | $ | 134.41 | $ | 132.23 | $ | 135.19 | |||||||||||
| 12/31/2019 | $ | 106.79 | 31.15 | % | 31.49 | % | 20.82 | % | $ | 176.27 | $ | 173.86 | $ | 163.34 |
Item 6. Selected Financial Data
| See page 52. |
Item 7. Management's Discussion and Analysis of Financial Condition and Results of Operations
| See page 57. |
Item 7A. Quantitative and Qualitative Disclosures About Market Risk
See Management's Discussion and Analysis of Financial Condition and Results of Operations.
Item 8. Financial Statements and Supplementary Data
See Item 15(a)1 and Item 15(a)2.
Item 9. Changes in and Disagreements with Accountants on Accounting and Financial Disclosure
None.
Item 9A. Controls and Procedures
Conclusion Regarding Effectiveness of Disclosure Controls and Procedures
Under the supervision and with the participation of our management, including our Chief Executive Officer and our Chief Financial Officer, we have evaluated the effectiveness of our disclosure controls and procedures (as defined under Rules 13a-15(e) and 15d-15(e) of the Securities Exchange Act of 1934, as amended). Based upon that evaluation, our Chief Executive Officer and our Chief Financial Officer concluded that our disclosure controls and procedures were effective as of the end of the period covered by this annual report.
Report of Management on Internal Control Over Financial Reporting
| See page 74. |
Changes in Internal Control
During the fourth quarter of 2019, there were no changes in our internal control over financial reporting (as defined in Rule 13a-15(f) under the Securities Exchange Act of 1934, as amended) that materially affected, or are reasonably likely to materially affect, our internal control over financial reporting.
Item 9B. Other Information
None.
PART III
Item 10. Directors, Executive Officers and Corporate Governance
Our Code of Ethics applies to all employees, executive officers and directors, including our Chief Executive Officer, Chief Financial Officer and Corporate Controller. You can find our Code of Ethics on our corporate governance website, www.QuestDiagnostics.com/investor. We will post any amendments to the Code of Ethics, and any waivers that are required to be disclosed by the rules of either the SEC or the New York Stock Exchange, on our website.
Information regarding the Company's executive officers is contained in Part I, Item 1 of this Report under “Information about our Executive Officers.” Information regarding the directors and executive officers of the Company appearing in our Proxy Statement to be filed by April 29, 2020 (“Proxy Statement”) under the captions “Proposal No. 1 - Election of Directors,” “Director Independence,” “Board Committees” and "Delinquent Section 16(a) Reports" is incorporated by reference herein.
Item 11. Executive Compensation
Information appearing in our Proxy Statement under the captions “2019 Director Compensation Table,” “Compensation Discussion and Analysis,” “Information Regarding Executive Compensation” and “Compensation Committee Report” is incorporated by reference herein.
Item 12. Security Ownership of Certain Beneficial Owners and Management and Related Stockholders' Matters
Information regarding security ownership of certain beneficial owners and management appearing in our Proxy Statement under the captions “Stock Ownership Information” and "Equity Compensation Plan Information" is incorporated by reference herein.
Item 13. Certain Relationships and Related Transactions, and Director Independence
Information regarding certain relationships and related transactions appearing in our Proxy Statement under the captions “Related Person Transactions” and “Director Independence” is incorporated by reference herein.
Item 14. Principal Accounting Fees and Services
Information regarding principal accountant fees and services appearing in our Proxy Statement under the caption “Audit" (excluding the information under the subheading “Audit and Finance Committee Report”) is incorporated by reference herein.
PART IV
Item 15. Exhibits, Financial Statement Schedules
| (a) | Documents filed as part of this Report. |
| 1. | Index to financial statements and supplementary data filed as part of this Report. |
| 2. | Financial Statement Schedule. |
| Item | Page |
| Schedule II - Valuation Accounts and Reserves | F- 51 |
| 3. | Exhibits |
| (b) | Exhibits filed as part of this Report. |
The exhibit index in (a) above is incorporated herein by reference.
| (c) | None. |
Item 16. Form 10-K Summary
None.
Signatures
Pursuant to the requirements of Sections 13 or 15(d) of the Securities Exchange Act of 1934, the Registrant has duly caused this report to be signed on its behalf by the undersigned, thereunto duly authorized, on February 20, 2020.
| QUEST DIAGNOSTICS INCORPORATED | ||
| (Registrant) | ||
| By: | /s/Stephen H. Rusckowski | |
| Stephen H. Rusckowski | ||
| Chairman of the Board, Chief Executive Officer and President |
Each individual whose signature appears below constitutes and appoints Michael E. Prevoznik and William J. O'Shaughnessy, Jr., and each of them singly, his or her true and lawful attorneys-in-fact and agents with full power of substitution, for him or her and in his or her name, place and stead, in any and all capacities, to sign any and all amendments to this Annual Report on Form 10-K filed with the Securities and Exchange Commission, granting unto said attorneys-in-fact and agents, and each of them, full power and authority to do and perform each and every act and thing requisite and necessary to be done in and about the premises, as fully to all intents and purposes as he or she might or could do in person, hereby ratifying and confirming all the said attorneys-in-fact and agents or any of them or their or his or her substitute or substitutes, may lawfully do or cause to be done by virtue hereof.
Pursuant to the requirements of the Securities Exchange Act of 1934, this report has been signed below by the following persons on behalf of the Registrant and in the capacities indicated on February 20, 2020.
| Signature | Capacity | |
| /s/Stephen H. Rusckowski Stephen H. Rusckowski | Chairman of the Board, Chief Executive Officer and President (Principal Executive Officer) | |
| /s/Mark J. Guinan Mark J. Guinan | Executive Vice President and Chief Financial Officer (Principal Financial Officer) | |
| /s/Michael J. Deppe Michael J. Deppe | Vice President, Corporate Controller and Chief Accounting Officer (Principal Accounting Officer) | |
| /s/Vicky B. Gregg Vicky B. Gregg | Director | |
| /s/Timothy L. Main Timothy L. Main | Director | |
| /s/Denise M. Morrison Denise M. Morrison | Director | |
| /s/Gary M. Pfeiffer Gary M. Pfeiffer | Director | |
| /s/Timothy M. Ring Timothy M. Ring | Director | |
| /s/Daniel C. Stanzione Daniel C. Stanzione | Director | |
| /s/Helen I. Torley Helen I. Torley | Director | |
| /s/Gail R. Wilensky Gail R. Wilensky | Director |
SELECTED HISTORICAL FINANCIAL DATA OF OUR COMPANY
The following table summarizes selected historical financial data of our Company and our subsidiaries at the dates and for each of the periods presented. The selected historical financial data is only a summary and should be read together with the audited consolidated financial statements and related notes of our Company and management's discussion and analysis of financial condition and results of operations included elsewhere in this Annual Report on Form 10-K.
| Year Ended December 31, | |||||||||||||||||||
| 2019 | 2018 | 2017 | 2016 | 2015 | |||||||||||||||
| (dollars in millions, except per share data) | |||||||||||||||||||
| Operations Data: | (a) (b) (c) | (a) (d) (e) | (a) (f) (g) | (a) (h) (i) | (a) (j) (k) | ||||||||||||||
| Net revenues | $ | 7,726 | $ | 7,531 | $ | 7,402 | $ | 7,214 | $ | 7,493 | |||||||||
| Operating income | 1,231 | 1,101 | 1,165 | 1,277 | 1,399 | ||||||||||||||
| Income from continuing operations | 886 | 788 | 824 | 696 | 753 | ||||||||||||||
| Income from discontinued operations, net of taxes | 20 | — | — | — | — | ||||||||||||||
| Net income | 906 | 788 | 824 | 696 | 753 | ||||||||||||||
| Less: Net income attributable to noncontrolling interests | 48 | 52 | 52 | 51 | 44 | ||||||||||||||
| Net income attributable to Quest Diagnostics | $ | 858 | $ | 736 | $ | 772 | $ | 645 | $ | 709 | |||||||||
| Amounts attributable to Quest Diagnostics' common stockholders: | |||||||||||||||||||
| Income from continuing operations | $ | 838 | $ | 736 | $ | 772 | $ | 645 | $ | 709 | |||||||||
| Income from discontinued operations, net of taxes | 20 | — | — | — | — | ||||||||||||||
| Net income | $ | 858 | $ | 736 | $ | 772 | $ | 645 | $ | 709 |
| Earnings per share attributable to Quest Diagnostics' common stockholders - basic: | |||||||||||||||||||
| Income from continuing operations | $ | 6.21 | $ | 5.39 | $ | 5.63 | $ | 4.58 | $ | 4.92 | |||||||||
| Income from discontinued operations | 0.15 | — | — | — | — | ||||||||||||||
| Net income | $ | 6.36 | $ | 5.39 | $ | 5.63 | $ | 4.58 | $ | 4.92 | |||||||||
| Earnings per share attributable to Quest Diagnostics' common stockholders - diluted: | |||||||||||||||||||
| Income from continuing operations | $ | 6.13 | $ | 5.29 | $ | 5.50 | $ | 4.51 | $ | 4.87 | |||||||||
| Income from discontinued operations | 0.15 | — | — | — | — | ||||||||||||||
| Net income | $ | 6.28 | $ | 5.29 | $ | 5.50 | $ | 4.51 | $ | 4.87 | |||||||||
| Dividends per common share | $ | 2.12 | $ | 2.03 | $ | 1.80 | $ | 1.65 | $ | 1.52 |
| Year Ended December 31, | |||||||||||||||||||
| 2019 | 2018 | 2017 | 2016 | 2015 | |||||||||||||||
| (dollars in millions) | |||||||||||||||||||
| Balance Sheet Data (at end of year): | (a) (b) (c) | (a) (d) (e) | (a) (f) (g) | (a) (h) (i) | (a) (j) (k) | ||||||||||||||
| Cash and cash equivalents | $ | 1,192 | $ | 135 | $ | 137 | $ | 359 | $ | 133 | |||||||||
| Total assets | 12,843 | 11,003 | 10,503 | 10,100 | 9,962 | ||||||||||||||
| Long-term debt | 3,966 | 3,429 | 3,748 | 3,728 | 3,492 | ||||||||||||||
| Total debt | 4,770 | 3,893 | 3,784 | 3,734 | 3,651 | ||||||||||||||
| Redeemable noncontrolling interest | 76 | 77 | 80 | 77 | 70 | ||||||||||||||
| Other Data: |
Showing the first 8K of 297K characters. Open the full section