 filings.tools
HCA Healthcare 10-K 2019-12-31
Filed 2020-02-20. 22 sections, 558K characters. Original on sec.gov · Markdown · JSON
Cover and table of contents
UNITED STATES
SECURITIES AND EXCHANGE COMMISSION
Washington, D.C. 20549
Form
10-K
(Mark One)
| ☒ | ANNUAL REPORT PURSUANT TO SECTION 13 OR 15(d) OF THE SECURITIES EXCHANGE ACT OF 1934 |
|---|
For the fiscal year ended
December 31, 2019
Or
| ☐ | TRANSITION REPORT PURSUANT TO SECTION 13 OR 15(d) OF THE SECURITIES EXCHANGE ACT OF 1934 |
|---|
For the transition period from
to
Commission File Number
1-11239
HCA Healthcare, Inc.
(Exact Name of Registrant as Specified in its Charter)
| Delaware | 27-3865930 | |
| (State or Other Jurisdiction of Incorporation or Organization) | (I.R.S. Employer Identification No.) | |
| One Park Plaza Nashville , Tennessee | 37203 | |
| (Address of Principal Executive Offices) | (Zip Code) |
Registrant’s telephone number, including area code: (
)
344-9551
Securities Registered Pursuant to Section 12(b) of the Act:
| Title of Each Class | Trading Symbol(s) | Name of Each Exchange on Which Registered | ||
| Common Stock , $0.01 Par Value | HCA | New York Stock Exchange |
Securities Registered Pursuant to Section 12(g) of the Act: None
Indicate by check mark if the Registrant is a well-known seasoned issuer, as defined in Rule 405 of the Securities Act. Yes
☒
No
☐
Indicate by check mark if the Registrant is not required to file reports pursuant to Section 13 or Section 15(d) of the Act. Yes
☐
No
☒
Indicate by check mark whether the Registrant (1) has filed all reports required to be filed by Section 13 or 15(d) of the Securities Exchange Act of 1934 during the preceding 12 months (or for such shorter period that the Registrant was required to file such reports), and (2) has been subject to such filing requirements for the past 90 days.
Yes
☒
No
☐
Indicate by check mark whether the Registrant has submitted electronically every Interactive Data File required to be submitted pursuant to Rule 405 of Regulation
S-T
(§ 232.405 of this chapter) during the preceding 12 months (or for such shorter period that the Registrant was required to submit such
files).
Yes
☒
No
☐
Indicate by check mark whether the Registrant is a large accelerated filer, an accelerated filer, a
non-accelerated
filer, a smaller reporting company, or an emerging growth company. See the definitions of “large accelerated filer,” “accelerated filer,” “smaller reporting company” and “emerging growth company” in Rule
12b-2
of the Exchange Act.
| Large accelerated filer | ☒ | Accelerated filer | ☐ | |||
| Non-accelerated filer | ☐ | Smaller reporting company | ☐ | |||
| Emerging growth company | ☐ |
If an emerging growth company, indicate by check mark if the registrant has elected not to use the extended transition period for complying with any new or revised financial accounting standards provided pursuant to Section 13(a) of the Exchange Act.
☐
Indicate by check mark whether the Registrant is a shell company (as defined in Rule
12b-2
of the Act). Yes
☐
No
☒
As of January 31, 2020, there were
338,427,300
outstanding shares of the Registrant’s common stock. As of June 30, 2019, the aggregate market value of the common stock held by nonaffiliates was approximately $36.403 billion. For purposes of the foregoing calculation only, Hercules Holding II and the Registrant’s directors and executive officers have been deemed to be affiliates.
DOCUMENTS INCORPORATED BY REFERENCE
Portions of the Registrant’s definitive proxy materials for its 2020 Annual Meeting of Stockholders are incorporated by reference into Part III hereof.
INDEX
PART I
Item 1. Business
| --- | --- |
General
HCA Healthcare, Inc. is one of the leading health care services companies in the United States. At December 31, 2019, we operated 184 hospitals, comprised of 179 general, acute care hospitals; three psychiatric hospitals; and two rehabilitation hospitals. In addition, we operated 123 freestanding surgery centers. Our facilities are located in 21 states and England.
The terms “Company,” “HCA,” “we,” “our” or “us,” as used herein and unless otherwise stated or indicated by context, refer to HCA Healthcare, Inc. and its affiliates. The term “affiliates” means direct and indirect subsidiaries of HCA Healthcare, Inc. and partnerships and joint ventures in which such subsidiaries are partners. The terms “facilities” or “hospitals” refer to entities owned and operated by affiliates of HCA, and the term “employees” refers to employees of affiliates of HCA.
Our primary objective is to provide a comprehensive array of quality health care services in the most cost-effective manner possible. Our general, acute care hospitals typically provide a full range of services to accommodate such medical specialties as internal medicine, general surgery, cardiology, oncology, neurosurgery, orthopedics and obstetrics, as well as diagnostic and emergency services. Outpatient and ancillary health care services are provided by our general, acute care hospitals, freestanding surgery centers, freestanding emergency care facilities, urgent care facilities,
walk-in
clinics, diagnostic centers and rehabilitation facilities. Our psychiatric hospitals provide a full range of mental health care services through inpatient, partial hospitalization and outpatient settings.
Our common stock is traded on the New York Stock Exchange (symbol “HCA”). Through our predecessors, we commenced operations in 1968. The Company was incorporated in Delaware in October 2010. Our principal executive offices are located at One Park Plaza, Nashville, Tennessee 37203, and our telephone number is (615)
344-9551.
Available Information
We file certain reports with the Securities and Exchange Commission (the “SEC”), including annual reports on Form
10-K,
quarterly reports on Form
10-Q
and current reports on Form
8-K.
The SEC maintains an Internet site at http://www.sec.gov that contains the reports, proxy and information statements and other information we file. Our website address is www.hcahealthcare.com. Please note that our website address is provided as an inactive textual reference only. We make available free of charge, through our website, our annual report on Form
10-K,
quarterly reports on Form
10-Q,
current reports on Form
8-K
and all amendments to those reports filed or furnished pursuant to Section 13 or 15(d) of the Exchange Act, as soon as reasonably practicable after such material is electronically filed with or furnished to the SEC. The information provided on our website is not part of this report, and is therefore not incorporated by reference unless such information is specifically referenced elsewhere in this report.
Our Code of Conduct is available free of charge upon request to our Corporate Secretary, HCA Healthcare, Inc., One Park Plaza, Nashville, Tennessee 37203, and is also available on the Ethics and Compliance and Corporate Governance portion of our website at www.hcahealthcare.com.
Business Strategy
We are committed to providing the communities we serve with high quality, cost-effective health care while growing our business and creating long-term value for our stockholders. To achieve these objectives, we align our efforts around the following growth agenda:
| • | grow our presence in existing markets; |
|---|
| • | achieve industry-leading performance in clinical and satisfaction measures; |
|---|
| • | recruit and employ physicians to meet the need for high quality health services; |
|---|
| • | continue to leverage our scale and market positions to grow the Company; and |
|---|
| • | pursue a disciplined development strategy. |
|---|
Health Care Facilities
We currently own, manage or operate hospitals, freestanding surgery centers, freestanding emergency care facilities, urgent care facilities,
walk-in
clinics, diagnostic and imaging centers, radiation and oncology therapy centers, comprehensive rehabilitation and physical therapy centers, physician practices and various other facilities.
At December 31, 2019, we owned and operated 179 general, acute care hospitals with 48,443 licensed beds. Most of our general, acute care hospitals provide medical and surgical services, including inpatient care, intensive care, cardiac care, diagnostic services and emergency services. The general, acute care hospitals also provide outpatient services such as outpatient surgery, laboratory, radiology, respiratory therapy, cardiology and physical therapy. Each hospital has an organized medical staff and a local board of trustees or governing board, made up of members of the local community.
At December 31, 2019, we operated three psychiatric hospitals with 412 licensed beds. Our psychiatric hospitals provide therapeutic programs, including child, adolescent and adult psychiatric care and adolescent and adult alcohol and drug abuse treatment and counseling.
We also operate outpatient health care facilities, which include freestanding ambulatory surgery centers (“ASCs”), freestanding emergency care facilities, urgent care facilities,
walk-in
clinics, diagnostic and imaging centers, comprehensive rehabilitation and physical therapy centers, radiation and oncology therapy centers, physician practices and various other facilities. These outpatient services are an integral component of our strategy to develop comprehensive health care networks in select communities. Most of our ASCs are operated through partnerships or limited liability companies, with majority ownership of each partnership or limited liability company typically held by a general partner or member that is an affiliate of HCA.
Certain of our affiliates provide a variety of management services to our health care facilities, including patient safety programs, ethics and compliance programs, national supply contracts, equipment purchasing and leasing contracts, accounting, financial and clinical systems, governmental reimbursement assistance, construction planning and coordination, information technology systems and solutions, legal counsel, human resources services and internal audit services.
Sources of Revenue
Hospital revenues depend upon inpatient occupancy levels, the medical and ancillary services ordered by physicians and provided to patients, the volume of outpatient procedures and the charges or payment rates for such services. Reimbursement rates for inpatient and outpatient services vary significantly depending on the type of third-party payer, the type of service (e.g., medical/surgical, intensive care or psychiatric) and the geographic location of the hospital. Inpatient occupancy levels fluctuate for various reasons, many of which are beyond our control.
We receive payments for patient services from the federal government under the Medicare program, state governments under their respective Medicaid or similar programs, managed care plans (including plans offered through the American Health Benefit Exchanges (“Exchanges”)), private insurers and directly from patients. Our revenues by primary third-party payer classification and other (including uninsured patients) for the years ended December 31, 2019, 2018 and 2017 are summarized in the following table (dollars in millions):
| Years Ended December 31, |
Showing the first 8K of 123K characters. Open the full section
Item 1A. Risk Factors
| --- | --- |
If any of the events discussed in the following risk factors were to occur, our business, financial position, results of operations, cash flows or prospects could be materially, adversely affected. Additional risks and uncertainties not presently known, or currently deemed immaterial, may also constrain our business and operations.
Our substantial leverage could adversely affect our ability to raise additional capital to fund our operations, limit our ability to react to changes in the economy or our industry, expose us to interest rate risk to the extent of our variable rate debt and prevent us from meeting our obligations.
We are highly leveraged. As of December 31, 2019, our total indebtedness was $33.722 billion. As of December 31, 2019, we had availability of $1.967 billion under our senior secured revolving credit facility and $1.270 million under our asset-based revolving credit facility, after giving effect to letters of credit and borrowing base limitations. Our high degree of leverage could have important consequences, including:
| • | increasing our vulnerability to downturns or adverse changes in general economic, industry or competitive conditions and adverse changes in government regulations; |
|---|
| • | requiring a substantial portion of cash flows from operations to be dedicated to the payment of principal and interest on our indebtedness, therefore reducing our ability to use our cash flows to fund our operations, capital expenditures and future business opportunities; |
|---|
| • | exposing us to the risk of increased interest rates to the extent that our existing unhedged borrowings are at variable rates of interest or we seek to refinance our debt in a rising rate environment; |
|---|
| • | limiting our ability to make strategic acquisitions or causing us to make nonstrategic divestitures; |
|---|
| • | limiting our ability to obtain additional financing for working capital, capital expenditures, share repurchases, dividends, product or service line development, debt service requirements, acquisitions and general corporate or other purposes; and |
|---|
| • | limiting our ability to adjust to changing market conditions and placing us at a competitive disadvantage compared to our competitors who are less highly leveraged. |
|---|
We and our subsidiaries have the ability to incur additional indebtedness in the future, subject to the restrictions contained in our senior secured credit facilities and the indentures governing our outstanding notes. If new indebtedness is added to our current debt levels, interest rates and the related risks that we now face could intensify.
We may not be able to generate sufficient cash to service all of our indebtedness and may not be able to refinance our indebtedness on favorable terms. If we are unable to do so, we may be forced to take other actions to satisfy our obligations under our indebtedness, which may not be successful.
Our ability to make scheduled payments on or to refinance our debt obligations depends on our financial condition and operating performance, which are subject to prevailing economic and competitive conditions and to certain financial, business and other factors beyond our control. We cannot assure you we will maintain a level of cash flows from operating activities sufficient to permit us to pay the principal, premium, if any, and interest on our indebtedness.
In addition, we conduct our operations through our subsidiaries. Accordingly, repayment of our indebtedness is dependent on the generation of cash flows by our subsidiaries and their ability to make such cash available to us by dividend, debt repayment or otherwise. Our subsidiaries may not be able to, or may not be permitted to, make distributions to enable us to make payments in respect of our indebtedness. Each subsidiary is a distinct legal entity, and, under certain circumstances, legal and contractual restrictions may limit our ability to obtain cash from our subsidiaries.
We may find it necessary or prudent to refinance our outstanding indebtedness, the terms of which may not be favorable to us. Our ability to refinance our indebtedness on favorable terms, or at all, is directly affected by the then current global economic and financial conditions which affect the availability of debt financing and the rates at which such financing is available. In addition, our ability to incur secured indebtedness (which would generally enable us to achieve better pricing than the incurrence of unsecured indebtedness) depends in part on the value of our assets, which depends, in turn, on the strength of our cash flows and results of operations, and on economic and market conditions and other factors.
If our cash flows and capital resources are insufficient to fund our debt service obligations or we are unable to refinance our indebtedness, we may be forced to reduce or delay investments and capital expenditures, or to sell assets, seek additional capital or restructure our indebtedness. These alternative measures may not be successful and may not permit us to meet our scheduled debt service obligations. If our operating results and available cash are insufficient to meet our debt service obligations, we could face substantial liquidity problems and might be required to dispose of material assets or operations to meet our debt service and other obligations. We may not be able to consummate those dispositions, or the proceeds from the dispositions may not be adequate to meet any debt service obligations then due.
Our debt agreements contain restrictions that limit our flexibility in operating our business.
Our senior secured credit facilities and, to a lesser extent, the indentures governing our outstanding notes contain various covenants that limit our ability to engage in specified types of transactions. These covenants limit our and certain of our subsidiaries’ ability to, among other things:
| • | incur additional indebtedness or issue certain preferred shares; |
|---|
| • | pay dividends on, repurchase or make distributions in respect of our capital stock or make other restricted payments; |
|---|
| • | make certain investments; |
|---|
| • | sell or transfer assets; |
|---|
| • | create liens; |
|---|
| • | consolidate, merge, sell or otherwise dispose of all or substantially all of our assets; and |
|---|
| • | enter into certain transactions with our affiliates. |
|---|
Under our asset-based revolving credit facility, borrowing availability is subject to a borrowing base of 85% of eligible accounts receivable less customary reserves, with any reduction in the borrowing base commensurately reducing our ability to access this facility as a source of liquidity. In addition, under the asset-based revolving credit facility, when (and for as long as) the combined availability under our asset-based revolving credit facility and our senior secured revolving credit facility is less than a specified amount for a certain period of time or, if a payment or bankruptcy event of default has occurred and is continuing, funds deposited into any of our depository accounts will be transferred on a daily basis into a blocked account with the administrative agent and applied to prepay loans under the asset-based revolving credit facility and to collateralize letters of credit issued thereunder.
Under our senior secured credit facilities, we are required to satisfy and maintain specified financial ratios. Our ability to meet those financial ratios may be affected by events beyond our control, and there can be no assurance we will continue to meet those ratios. A breach of any of these covenants could result in a default under both the cash flow credit facility and the asset-based r
Showing the first 8K of 77K characters. Open the full section
Item 1B. Unresolved Staff Comments
| --- | --- |
None.
Item 2. Properties
| --- | --- |
The following table lists, by state, the number of hospitals (general, acute care, psychiatric and rehabilitation) directly or indirectly owned and operated by us as of December 31, 2019:
| State | Hospitals | Beds | ||||||
| Alaska | 1 | 250 | ||||||
| California | 5 | 1,858 | ||||||
| Colorado | 7 | 2,411 | ||||||
| Florida | 45 | 12,410 | ||||||
| Georgia | 9 | 2,469 | ||||||
| Idaho | 2 | 468 | ||||||
| Indiana | 1 | 278 | ||||||
| Kansas | 4 | 1,374 | ||||||
| Kentucky | 2 | 384 | ||||||
| Louisiana | 3 | 914 | ||||||
| Mississippi | 1 | 130 | ||||||
| Missouri | 5 | 1,058 | ||||||
| Nevada | 3 | 1,421 | ||||||
| New Hampshire | 2 | 306 | ||||||
| North Carolina | 7 | 1,181 | ||||||
| South Carolina | 3 | 949 | ||||||
| Tennessee | 13 | 2,576 | ||||||
| Texas | 46 | 13,395 | ||||||
| Utah | 8 | 1,011 | ||||||
| Virginia | 11 | 3,300 | ||||||
| International | ||||||||
| England | 6 | 892 | ||||||
| 184 | 49,035 | |||||||
In addition to the hospitals listed in the above table, we directly or indirectly operate 123 freestanding surgery centers. We also operate medical office buildings in conjunction with some of our hospitals. These office buildings are primarily occupied by physicians who practice at our hospitals. Fourteen of our general, acute care hospitals and two of our other properties have been mortgaged to support our obligations under our senior secured cash flow credit facility and first lien secured notes.
We maintain our headquarters in approximately 2,127,000 square feet of space in the Nashville, Tennessee area. In addition to the headquarters in Nashville, we maintain regional service centers related to our shared services initiatives. These service centers are located in markets in which we operate hospitals.
We believe our headquarters, hospitals and other facilities are suitable for their respective uses and are, in general, adequate for our present needs. Our properties are subject to various federal, state and local statutes and ordinances regulating their operation. Management does not believe that compliance with such statutes and ordinances will materially affect our financial position or results of operations.
Item 3. Legal Proceedings
| --- | --- |
We operate in a highly regulated and litigious industry. As a result, various lawsuits, claims and legal and regulatory proceedings have been and can be expected to be instituted or asserted against us. We are also subject to claims and suits arising in the ordinary course of business, including claims for personal injuries or wrongful restriction of, or interference with, physicians’ staff privileges. In certain of these actions the claimants may seek punitive damages against us which may not be covered by insurance. We are also subject to claims by various taxing authorities for additional taxes and related interest and penalties. The resolution of any such lawsuits, claims or legal and regulatory proceedings could have a material, adverse effect on our results of operations, financial position or liquidity.
Government Investigations, Claims and Litigation
Health care companies are subject to numerous investigations by various governmental agencies. Under the federal False Claims Act (“FCA”), private parties have the right to bring
qui tam
, or “whistleblower,” suits against companies that submit false claims for payments to, or improperly retain overpayments from, the government. Some states have adopted similar state whistleblower and false claims provisions. Certain of our individual facilities have received, and from time to time, other facilities may receive, government inquiries from, and may be subject to investigation by, federal and state agencies. Depending on whether the underlying conduct in these or future inquiries or investigations could be considered systemic, their resolution could have a material, adverse effect on our results of operations, financial position or liquidity.
Texas operates a state Medicaid program pursuant to a waiver from CMS under Section 1115 of the Social Security Act (“Program”). The Program includes uncompensated-care pools; payments from these pools are intended to defray the uncompensated costs of services provided by our and other hospitals to Medicaid eligible or uninsured individuals. Separately, we and other hospitals provide charity care services in several communities in the state. In 2018, the Civil Division of the U.S. Department of Justice and the U.S. Attorney’s Office for the Southern District of Texas requested information about whether the Program, as operated in Harris County, complied with the laws and regulations applicable to provider related donations, and the Company cooperated with that request. On May 21, 2019, a
qui tam
lawsuit asserting violations of the FCA and the Texas Medicaid Fraud Prevention Act related to the Program, as operated in Harris County, was unsealed by the U.S. District Court for the Southern District of Texas. Both the federal and state governments declined to intervene in the
qui tam
lawsuit. The Company believes that our participation is and has been consistent with the requirements of the Program and is vigorously defending against the lawsuit being pursued by the relator. We cannot predict what effect, if any, the
qui tam
lawsuit could have on the Company.
Item 4. Mine Safety Disclosures
| --- | --- |
None.
PART II
Item 5. Market for Registrant’s Common Equity, Related Stockholder Matters and Issuer Purchases of Equity Securities
| --- | --- |
During January 2020 and 2019, our Board of Directors authorized share repurchase programs for up to $4 billion ($2 billion for each authorization) of our outstanding common stock. Repurchases made during the fourth quarter of 2019, as detailed below, were made pursuant to the January 2019 share repurchase authorization and were made in the open market.
The following table provides certain information with respect to our repurchases of common stock from October 1, 2019 through December 31, 2019 (dollars in millions, except per share amounts).
| Period | Total Number of Shares Purchased | Average Price Paid per Share | Total Number of Shares Purchased as Part of Publicly Announced Plans or Programs | Approximate Dollar Value of Shares That May Yet Be Purchased Under Publicly Announced Plans or Programs | ||||||||||||
| October 1, 2019 through October 31, 2019 | 898,323 | $ | 120.23 | 898,323 | $ | 1,405 | ||||||||||
| November 1, 2019 through November 30, 2019 | 585,739 | $ | 136.44 | 585,739 | $ | 1,325 | ||||||||||
| December 1, 2019 through December 31, 2019 | 585,429 | $ | 143.49 | 585,429 | $ | 1,241 | ||||||||||
| Total for Fourth Quarter 2019 | 2,069,491 | $ | 131.40 | 2,069,491 | $ | 1,241 | ||||||||||
Our common stock is traded on the New York Stock Exchange (“NYSE”) (symbol “HCA”). On January 27, 2020, our Board of Directors declared a quarterly dividend of $0.43 per share on our common stock payable on March 31, 2020 to stockholders of record at the close of business on March 2, 2020. Future declarations of quarterly dividends and the establishment of future record and payment dates are subject to the final determination of our Board of Directors. Our ability to declare future dividends may also from time to time be limited by the terms of our debt agreements. During 2019, our Board of Directors declared four quarterly dividends of $0.40 per share, or $1.60 per share in the aggregate, on our common stock. At the close of business on February 7, 2020, there were approximately 390 holders of record of our common stock.
STOCK PERFORMANCE GRAPH
COMPARISON OF 5 YEAR CUMULATIVE TOTAL RETURN
Among HCA Healthcare, Inc., the S&P 500 Index and the S&P Health Care Index
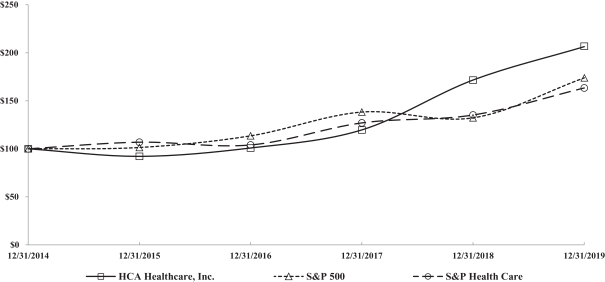
| 12/31/2014 | 12/31/2015 | 12/31/2016 | 12/31/2017 | 12/31/2018 | 12/31/2019 | |||||||||||||||||||
| HCA Healthcare, Inc. | $ | 100.00 | $ | 92.15 | $ | 100.86 | $ | 119.69 | $ | 171.61 | $ | 206.36 | ||||||||||||
| S&P 500 | 100.00 | 101.38 | 113.51 | 138.29 | 132.23 | 173.86 | ||||||||||||||||||
| S&P Health Care | 100.00 | 106.89 | 104.01 | 126.98 | 135.19 | 163.34 |
The graph shows the cumulative total return to our stockholders beginning as of December 31, 2014 through December 31, 2019, in comparison to the cumulative returns of the S&P 500 Index and the S&P Health Care Index. The graph assumes $100 invested on December 31, 2014 in our common stock and in each index with the subsequent reinvestment of dividends. The stock performance shown on the graph represents historical stock performance and is not necessarily indicative of future stock price performance.
Item 6. Selected Financial Data
| --- | --- |
HCA HEALTHCARE, INC.
SELECTED FINANCIAL DATA
AS OF AND FOR THE YEARS ENDED DECEMBER 31
(Dollars in millions, except per share amounts)
| 2019 | 2018 | 2017 | 2016 | 2015 | ||||||||||||||||
| Summary of Operations: | ||||||||||||||||||||
| Revenues | $ | 51,336 | $ | 46,677 | $ | 43,614 | $ | 41,490 | $ | 39,678 | ||||||||||
| Salaries and benefits | 23,560 | 21,425 | 20,059 | 18,897 | 18,115 | |||||||||||||||
| Supplies | 8,481 | 7,724 | 7,316 | 6,933 | 6,638 | |||||||||||||||
| Other operating expenses | 9,481 | 8,608 | 8,051 | 7,496 | 7,056 | |||||||||||||||
| Equity in earnings of affiliates | (43 | ) | (29 | ) | (45 | ) | (54 | ) | (46 | ) | ||||||||||
| Depreciation and amortization | 2,596 | 2,278 | 2,131 | 1,966 | 1,904 | |||||||||||||||
| Interest expense | 1,824 | 1,755 | 1,690 | 1,707 | 1,665 | |||||||||||||||
| Losses (gains) on sales of facilities | (18 | ) | (428 | ) | (8 | ) | (23 | ) | 5 | |||||||||||
| Losses on retirement of debt | 211 | 9 | 39 | 4 | 135 | |||||||||||||||
| Legal claim (benefits) costs | — | — | — | (246 | ) | 249 | ||||||||||||||
| 46,092 | 41,342 | 39,233 | 36,680 | 35,721 | ||||||||||||||||
| Income before income taxes | 5,244 | 5,335 | 4,381 | 4,810 | 3,957 | |||||||||||||||
| Provision for income taxes | 1,099 | 946 | 1,638 | 1,378 | 1,261 | |||||||||||||||
| Net income | 4,145 | 4,389 | 2,743 | 3,432 | 2,696 | |||||||||||||||
| Net income attributable to noncontrolling interests | 640 | 602 | 527 | 542 | 567 | |||||||||||||||
| Net income attributable to HCA Healthcare, Inc. | $ | 3,505 | $ | 3,787 | $ | 2,216 | $ | 2,890 | $ | 2,129 | ||||||||||
| Per common share data: | ||||||||||||||||||||
| Basic earnings per share | $ | 10.27 | $ | 10.90 | $ | 6.12 | $ | 7.53 | $ | 5.14 | ||||||||||
| Diluted earnings per share | $ | 10.07 | $ | 10.66 | $ | 5.95 | $ | 7.30 | $ | 4.99 | ||||||||||
| Cash dividends declared per share | $ | 1.60 | $ | 1.40 | — | — | — | |||||||||||||
| Financial Position: | ||||||||||||||||||||
| Assets | $ | 45,058 | $ | 39,207 | $ | 36,593 | $ | 33,758 | $ | 32,744 | ||||||||||
| Working capital | 3,439 | 2,644 | 3,819 | 3,252 | 3,716 | |||||||||||||||
| Long-term debt, net, including amounts due within one year | 33,722 | 32,821 | 33,058 | 31,376 | 30,488 | |||||||||||||||
| Noncontrolling interests | 2,243 | 2,032 | 1,811 | 1,669 | 1,553 | |||||||||||||||
| Stockholders’ deficit | (565 | ) | (2,918 | ) | (4,995 | ) | (5,633 | ) | (6,046 | ) | ||||||||||
| Cash Flow Data: | ||||||||||||||||||||
| Cash provided by operating activities | $ | 7,602 | $ | 6,761 | $ | 5,426 | $ | 5,653 | $ | 4,734 | ||||||||||
| Cash used in investing activities | (5,720 | ) | (3,901 | ) | (4,279 | ) | (3,240 | ) | (2,583 | ) | ||||||||||
| Purchase of property and equipment | (4,158 | ) | (3,573 | ) | (3,015 | ) | (2,760 | ) | (2,375 | ) | ||||||||||
| Cash used in financing activities | (1,771 | ) | (3,075 | ) | (1,061 | ) | (2,508 | ) | (1,976 | ) |
| 2019 | 2018 | 2017 | 2016 | 2015 | ||||||||||||||||
| Operating Data: | ||||||||||||||||||||
| Number of hospitals at end of period | 184 | 179 | 179 | 170 | 168 | |||||||||||||||
| Number of freestanding outpatient surgical centers at end of period | 123 | 123 | 120 | 118 | 116 | |||||||||||||||
| Number of licensed beds at end of period(a) | 49,035 | 47,199 | 46,738 | 44,290 | 43,771 | |||||||||||||||
| Weighted average licensed beds(b) | 48,480 | 46,857 | 45,380 | 44,077 | 43,620 | |||||||||||||||
| Admissions(c) | 2,108,927 | 2,003,753 | 1,936,613 | 1,891,831 | 1,868,789 | |||||||||||||||
| Equivalent admissions(d) | 3,646,335 | 3,420,406 | 3,286,432 | 3,191,519 | 3,122,746 | |||||||||||||||
| Average length of stay (days)(e) | 4.9 | 4.9 | 4.9 | 4.9 | 4.9 | |||||||||||||||
| Average daily census(f) | 28,134 | 26,663 | 26,000 | 25,340 | 25,084 | |||||||||||||||
| Occupancy(g) | 58 | % | 57 | % | 57 | % | 58 | % | 58 | % | ||||||||||
| Emergency room visits(h) | 9,161,129 | 8,764,431 | 8,624,137 | 8,378,340 | 8,050,159 | |||||||||||||||
| Outpatient surgeries(i) | 1,009,947 | 971,537 | 941,231 | 932,213 | 909,386 | |||||||||||||||
| Inpatient surgeries(j) | 566,635 | 548,220 | 540,304 | 537,306 | 529,900 | |||||||||||||||
| Days revenues in accounts receivable(k) | 50 | 51 | 52 | 50 | 53 | |||||||||||||||
| Outpatient revenues as a % of patient revenues(l) | 39 | % | 38 | % | 38 | % | 38 | % | 40 | % |
| (a) | Licensed beds are those beds for which a facility has been granted approval to operate from the applicable state licensing agency. |
|---|
| (b) | Represents the average number of licensed beds, weighted based on periods owned. |
|---|
| (c) | Represents the total number of patients admitted to our hospitals and is used by management and certain investors as a general measure of inpatient volume. |
|---|
| (d) | Equivalent admissions are used by management and certain investors as a general measure of combined inpatient and outpatient volume. Equivalent admissions are computed by multiplying admissions (inpatient volume) by the sum of gross inpatient revenue and gross outpatient revenue and then dividing the resulting amount by gross inpatient revenue. The equivalent admissions computation “equates” outpatient revenue to the volume measure (admissions) used to measure inpatient volume, resulting in a general measure of combined inpatient and outpatient volume. |
|---|
| (e) | Represents the average number of days admitted patients stay in our hospitals. |
|---|
| (f) | Represents the average number of patients in our hospital beds each day. |
|---|
| (g) | Represents the percentage of hospital licensed beds occupied by patients. Both average daily census and occupancy rate provide measures of the utilization of inpatient rooms. |
|---|
| (h) | Represents the number of patients treated in our emergency rooms. |
|---|
| (i) | Represents the number of surgeries performed on patients who were not admitted to our hospitals. Pain management and endoscopy procedures are not included in outpatient surgeries. |
|---|
| (j) | Represents the number of surgeries performed on patients who have been admitted to our hospitals. Pain management and endoscopy procedures are not included in inpatient surgeries. |
|---|
| (k) | Revenues per day is calculated by dividing the revenues for the fourth quarter of each year by the days in the quarter. Days revenues in accounts receivable is then calculated as accounts receivable at the end of the period divided by revenues per day. |
|---|
| (l) | Represents the percentage of patient revenues related to patients who are not admitted to our hospitals. |
|---|
HCA HEALTHCARE, INC.
MANAGEMENT’S DISCUSSION AND ANALYSIS OF FINANCIAL CONDITION
AND RESULTS OF OPERATIONS
Item 7. Management’s Discussion and Analysis of Financial Condition and Results of Operations
| --- | --- |
The selected financial data and the accompanying consolidated financial statements present certain information with respect to the financial position, results of operations and cash flows of HCA Healthcare, Inc. which should be read in conjunction with the following discussion and analysis. The terms “HCA,” “Company,” “we,” “our,” or “us,” as used herein, refer to HCA Healthcare, Inc. and its affiliates. The term “affiliates” means direct and indirect subsidiaries of HCA Healthcare, Inc. and partnerships and joint ventures in which such subsidiaries are partners.
Forward-Looking Statements
This annual report on Form
10-K
includes certain disclosures which contain “forward-looking statements” within the meaning of the federal securities laws, which involve risks and uncertainties. Forward-looking statements include statements regarding expected share-based compensation expense, expected capital expenditures, expected dividends, expected net claim payments and all other statements that do not relate solely to historical or current facts, and can be identified by the use of words like “may,” “believe,” “will,” “expect,” “project,” “estimate,” “anticipate,” “plan,” “initiative” or “continue.” These forward-looking statements are based on our current plans and expectations and are subject to a number of known and unknown uncertainties and risks, many of which are beyond our control, which could significantly affect current plans and expectations and our future financial position and results of operations. These factors include, but are not limited to, (1) the impact of our substantial indebtedness and the ability to refinance such indebtedness on acceptable terms, (2) the impact of the Patient Protection and Affordable Care Act, as amended by the Health Care and Education Reconciliation Act of 2010 (collectively, the “Affordable Care Act”), including the effects of court challenges to, any repeal of, or changes to, the Affordable Care Act or additional changes to its implementation, the possible enactment of additional federal or state health care reforms and possible changes to other federal, state or local laws or regulations affecting the health care industry, including single-payer proposals (often referred to as “Medicare for All”), (3) the effects related to the continued implementation of the sequestration spending reductions required under the Budget Control Act of 2011, and related legislation extending these reductions, and the potential for future deficit reduction legislation that may alter these spending reductions, which include cuts to Medicare payments, or create additional spending reductions, (4) increases in the amount and risk of collectability of uninsured accounts and deductibles and copayment amounts for insured accounts, (5) the ability to achieve operating and financial targets, and attain expected levels of patient volumes and control the costs of providing services, (6) possible changes in Medicare, Medicaid and other state programs, including Medicaid supplemental payment programs or Medicaid waiver programs, that may impact reimbursements to health care providers and insurers and the size of the uninsured or underinsured population, (7) the highly competitive nature of the health care business, (8) changes in service mix, revenue mix and surgical volumes, including potential declines in the population covered under third-party payer agreements, the ability to enter into and renew third-party payer provider agreements on acceptable terms and the impact of consumer-driven health plans and physician utilization trends and practices, (9) the efforts of health insurers, health care providers, large employer groups and others to contain health care costs, (10) the outcome of our continuing efforts to monitor, maintain and comply with appropriate laws, regulations, policies and procedures, (11) increases in wages and the ability to attract and retain qualified management and personnel, including affiliated physicians, nurses and medical and technical support personnel, (12) the availability and terms of capital to fund the expansion of our business and improvements to our existing facilities, (13) changes in accounting practices, (14) changes in general economic conditions nationally and regionally in our markets, (15) the emergence of and effects related to pandemics, epidemics and infectious diseases, (16) future divestitures which may result in charges and possible impairments of long-lived assets, (17) changes in business strategy or development plans, (18) delays in receiving payments for services provided, (19) the outcome of pending and any future tax audits, disputes and litigation associated
HCA HEALTHCARE, INC.
MANAGEMENT’S DISCUSSION AND ANALYSIS OF FINANCIAL CONDITION
AND RESULTS OF OPERATIONS (Continued)
Forward-Looking Statements (continued)
with our tax positions, (20) potential adverse impact of known and unknown government investigations, litigation and other claims that may be made against us, (21) the impact of potential cybersecurity incidents or security breaches, (22) our ongoing ability to demonstrate meaningful use of certified electronic health record (“EHR”) technology and the impact of interoperability requirements, (23) the impact of natural disasters, such as hurricanes and floods, or similar events beyond our control, (24) changes in U.S. federal, state, or foreign tax laws including interpretive guidance that may be issued by taxing authorities or other standard setting bodies, and (25) other risk factors described in this annual report on Form
10-K.
As a consequence, current plans, anticipated actions and future financial position and results of operations may differ from those expressed in any forward-looking statements made by or on behalf of HCA. You are cautioned not to unduly rely on such forward-looking statements when evaluating the information presented in this report.
2019 Operations Summary
Net income attributable to HCA Healthcare, Inc. totaled $3.505 billion, or $10.07 per diluted share, for 2019, compared to $3.787 billion, or $10.66 per diluted share, for 2018. The 2019 results include gains on sales of facilities of $18 million, or $0.04 per diluted share, and losses on retirement of debt of $211 million, or $0.47 per diluted share. The 2018 results include gains on sales of facilities of $428 million, or $0.91 per diluted share, and losses on retirement of debt of $9 million, or $0.02 per diluted share. The 2019 results also include revenues of $86 million, or $0.19 per diluted share, related to the resolution of transaction price differences regarding certain
out-of-network
services performed in prior periods. The 2018 results also include a reduction in our provision for income taxes of $67 million, or $0.19 per share, for the remeasurement of certain of our deferred tax assets and liabilities for which we were unable to record reasonable estimates in 2017. During 2019 and 2018, we recorded reductions to the provision for professional liability risks of $50 million, or $0.11 per diluted share, and $70 million, or $0.15 per diluted share, respectively. During 2018, we recorded additional expenses and losses of revenues estimated at approximately $31 million, or $0.07 per diluted share, associated with the impact of hurricane Michael on our Florida facilities. This amount is prior to any insurance recoveries. During 2018, we recorded a benefit of $49 million, or $0.11 per diluted share, from an insurance recovery related to hurricane Harvey business interruption losses incurred during 2017, and we recorded a reduction to the provision for income taxes of $28 million, or $0.08 per diluted share, for tax credits related to certain 2017 hurricane-related expenses. Our provisions for income taxes for 2019 and 2018 included tax benefits of $65 million, or $0.19 per diluted share, and $124 million, or $0.35 per diluted share, respectively, related to employee e
Showing the first 8K of 77K characters. Open the full section
Item 7A. Quantitative and Qualitative Disclosures about Market Risk
| --- | --- |
Information with respect to this Item is provided under the caption “Market Risk” under Item 7, “Management’s Discussion and Analysis of Financial Condition and Results of Operations.”
Item 8. Financial Statements and Supplementary Data
| --- | --- |
Information with respect to this Item is contained in our consolidated financial statements indicated in the Index to Consolidated Financial Statements on Page
F-1
of this annual report on Form
10-K.
Item 9. Changes in and Disagreements with Accountants on Accounting and Financial Disclosure
| --- | --- |
None.
Item 9A. Controls and Procedures
| --- | --- |
- Conclusion Regarding the Effectiveness of Disclosure Controls and Procedures
Under the supervision and with the participation of our management, including our principal executive officer and principal financial officer, we conducted an evaluation of our disclosure controls and procedures, as such term is defined under Rule
13a-15(e)
promulgated under the Securities Exchange Act of 1934, as amended (the “Exchange Act”). Based on this evaluation, our principal executive officer and our principal financial officer concluded that our disclosure controls and procedures were effective as of the end of the period covered by this annual report.
- Internal Control Over Financial Reporting
(a) Management’s Report on Internal Control Over Financial Reporting
Our management is responsible for establishing and maintaining effective internal control over financial reporting, as such term is defined in Exchange Act Rule
13a-15(f).
Because of its inherent limitations, internal control over financial reporting may not prevent or detect misstatements. Therefore, even those systems determined to be effective, can provide only reasonable assurance with respect to financial statement preparation and presentation.
Under the supervision and with the participation of our management, including our principal executive officer and principal financial officer, we conducted an assessment of the effectiveness of our internal control over financial reporting based on the framework in Internal Control — Integrated Framework issued by the Committee of Sponsoring Organizations of the Treadway Commission (2013 framework). Based on our assessment under the framework in Internal Control — Integrated Framework, our management concluded that our internal control over financial reporting was effective as of December 31, 2019.
Ernst & Young LLP, the independent registered public accounting firm that audited our consolidated financial statements included in this Form
10-K,
has issued a report on our internal control over financial reporting, which is included herein.
(b) Attestation Report of the Independent Registered Public Accounting Firm
Report of Independent Registered Public Accounting Firm
The Board of Directors and Stockholders
HCA Healthcare, Inc.
Opinion on Internal Control over Financial Reporting
We have audited HCA Healthcare, Inc.’s internal control over financial reporting as of December 31, 2019, based on criteria established in Internal Control — Integrated Framework issued by the Committee of Sponsoring Organizations of the Treadway Commission (2013 framework) (the COSO criteria). In our opinion, HCA Healthcare, Inc. (the Company) maintained, in all material respects, effective internal control over financial reporting as of December 31, 2019, based on the COSO criteria.
We also have audited, in accordance with the standards of the Public Company Accounting Oversight Board (United States) (PCAOB), the consolidated balance sheets of HCA Healthcare, Inc. as of December 31, 2019 and 2018, and the related consolidated statements of income, comprehensive income, stockholders’ deficit, and cash flows for each of the three years in the period ended December 31, 2019, and the related notes and our report dated February 20, 2020 expressed an unqualified opinion thereon.
Basis for Opinion
The Company’s management is responsible for maintaining effective internal control over financial reporting and for its assessment of the effectiveness of internal control over financial reporting included in the accompanying Management’s Report on Internal Control Over Financial Reporting. Our responsibility is to express an opinion on the Company’s internal control over financial reporting based on our audit. We are a public accounting firm registered with the PCAOB and are required to be independent with respect to the Company in accordance with the U.S. federal securities laws and the applicable rules and regulations of the Securities and Exchange Commission and the PCAOB.
We conducted our audit in accordance with the standards of the PCAOB. Those standards require that we plan and perform the audit to obtain reasonable assurance about whether effective internal control over financial reporting was maintained in all material respects.
Our audit included obtaining an understanding of internal control over financial reporting, assessing the risk that a material weakness exists, testing and evaluating the design and operating effectiveness of internal control based on the assessed risk, and performing such other procedures as we considered necessary in the circumstances. We believe that our audit provides a reasonable basis for our opinion.
Definition and Limitations of Internal Control Over Financial Reporting
A company’s internal control over financial reporting is a process designed to provide reasonable assurance regarding the reliability of financial reporting and the preparation of financial statements for external purposes in accordance with generally accepted accounting principles. A company’s internal control over financial reporting includes those policies and procedures that (1) pertain to the maintenance of records that, in reasonable detail, accurately and fairly reflect the transactions and dispositions of the assets of the company; (2) provide reasonable assurance that transactions are recorded as necessary to permit preparation of financial statements in accordance with generally accepted accounting principles, and that receipts and expenditures of the company are being made only in accordance with authorizations of management and directors of the company; and (3) provide reasonable assurance regarding prevention or timely detection of unauthorized acquisition, use, or disposition of the company’s assets that could have a material effect on the financial statements.
Because of its inherent limitations, internal control over financial reporting may not prevent or detect misstatements. Also, projections of any evaluation of effectiveness to future periods are subject to the risk that controls may become inadequate because of changes in conditions, or that the degree of compliance with the policies or procedures may deteriorate.
/s/ Ernst & Young LLP
Nashville, Tennessee
February 20, 2020
(c) Changes in Internal Control Over Financial Reporting
During the fourth quarter of 2019, there have been no changes in our internal control over financial reporting that have materially affected or are reasonably likely to materially affect our internal control over financial reporting.
Item 9B. Other Information
| --- | --- |
None.
PART III
Item 10. Directors, Executive Officers and Corporate Governance
| --- | --- |
The information required by this Item regarding the identity and business experience of our directors and executive officers is set forth under the heading “Nominees for Election” and “Election of Directors” in the definitive proxy materials of HCA to be filed in connection with our 2020 Annual Meeting of Stockholders with respect to our directors and is set forth in Item 1 of Part I of this annual report on Form
10-K
with respect to our executive officers. The information required by this Item contained in such definitive proxy materials is incorporated herein by reference.
Information on the beneficial ownership reporting for our directors and executive officers required by this Item is contained under the caption “Delinquent Section 16(a) Reports” in the definitive proxy materials to be filed in connection with our 2020 Annual Meeting of Stockholders and is incorporated herein by reference.
Information on our Audit and Compliance Committee and Audit Committee Financial Experts required by this Item is contained under the caption “Corporate Governance” in the definitive proxy materials to be filed in connection with our 2020 Annual Meeting of Stockholders and is incorporated herein by reference.
We have a Code of Conduct which is applicable to all our directors, officers and employees (the “Code of Conduct”). The Code of Conduct is available on the Ethics and Compliance and Corporate Governance pages of our website at www.hcahealthcare.com. To the extent required pursuant to applicable SEC regulations, we intend to post amendments to or waivers from our Code of Conduct (to the extent applicable to our chief executive officer, principal financial officer or principal accounting officer) at this location on our website or report the same on a Current Report on Form
8-K.
Our Code of Conduct is available free of charge upon request to our Corporate Secretary, HCA Healthcare, Inc., One Park Plaza, Nashville, TN 37203.
Item 11. Executive Compensation
| --- | --- |
The information required by this Item is set forth under the headings “Executive Compensation” and “Compensation Committee Interlocks and Insider Participation” in the definitive proxy materials to be filed in connection with our 2020 Annual Meeting of Stockholders, which information is incorporated herein by reference.
Item 12. Security Ownership of Certain Beneficial Owners and Management and Related Stockholder Matters
| --- | --- |
Information about security ownership of certain beneficial owners required by this Item is set forth under the heading “Security Ownership of Certain Beneficial Owners and Management and Related Stockholder Matters” in the definitive proxy materials to be filed in connection with our 2020 Annual Meeting of Stockholders, which information is incorporated herein by reference.
This table provides certain information as of December 31, 2019 with respect to our equity compensation plans:
EQUITY COMPENSATION PLAN INFORMATION
(Share and share unit amounts in millions)
| (a) | (b) | (c) | ||||||||||
| Number of securities to be issued upon exercise of outstanding options, warrants and rights | Weighted-average exercise price of outstanding options, warrants and rights | Number of securities remaining available for future issuance under equity compensation plans (excluding securities reflected in column(a)) | ||||||||||
| Equity compensation plans approved by security holders | 16.849 | (1) | $ | 71.79 | (1) | 27.211 | (2) | |||||
| Equity compensation plans not approved by security holders | — | — | — | |||||||||
| Total | 16.849 | $ | 71.79 | 27.211 | ||||||||
| (1) | Includes 2.620 million restricted share units which vest solely based upon continued employment over a specific period of time and 3.035 million performance share units which vest based upon continued employment over a specific period of time and the achievement of predetermined financial targets over time. The performance share units reported reflect the number of performance share units that would vest upon achievement of target performance; the number of performance share units that vest can vary from zero (for actual performance less than 90% of target for 2019 grants and 80% of target for 2018 and prior grants) to two times the units granted (for actual performance of 110% or more of target for 2019 grants and 120% or more of target for 2018 and prior grants). The weighted average exercise price does not take these restricted share units and performance share units into account. |
|---|
| (2) | Includes 20.328 million shares available for future grants under the 2006 Stock Incentive Plan for Key Employees of HCA Holdings, Inc. and its Affiliates, as Amended and Restated, and 6.883 million shares of common stock reserved for future issuance under the HCA Holdings, Inc. Employee Stock Purchase Plan. |
|---|
| * | For additional information concerning our equity compensation plans, see the discussion in Note 2 — Share-Based Compensation in the notes to the consolidated financial statements. |
|---|
Item 13. Certain Relationships and Related Transactions, and Director Independence
| --- | --- |
The information required by this Item is set forth under the headings “Certain Relationships and Related Party Transactions” and “Corporate Governance” in the definitive proxy materials to be filed in connection with our 2020 Annual Meeting of Stockholders, which information is incorporated herein by reference.
Item 14. Principal Accountant Fees and Services
| --- | --- |
The information required by this Item is set forth under the heading “Ratification of Appointment of Independent Registered Public Accounting Firm” in the definitive proxy materials to be filed in connection with our 2020 Annual Meeting of Stockholders, which information is incorporated herein by reference.
PART IV
Item 15. Exhibits and Financial Statement Schedules
| --- | --- |
(a) Documents filed as part of the report:
Financial Statements.
The accompanying Index to Consolidated Financial Statements on page
F-1
of this annual report on Form
10-K
is provided in response to this item.
List of Financial Statement Schedules.
All schedules are omitted because the required information is either not present, not present in material amounts or presented within the consolidated financial statements.
- List of Exhibits
Showing the first 8K of 72K characters. Open the full section
Item 16. Form 10-K Summary
| --- | --- |
None.
SIGNATURES
Pursuant to the requirements of Section 13 or 15(d) of the Securities Exchange Act of 1934, the Registrant has duly caused this report to be signed on its behalf by the undersigned, thereunto duly authorized.
| HCA HEALTHCARE, INC. | ||
| By: | /s/ Samuel N. Hazen | |
| Samuel N. Hazen Chief Executive Officer | ||
Dated: February 20, 2020
Pursuant to the requirements of the Securities Exchange Act of 1934, this report has been signed below by the following persons on behalf of the registrant and in the capacities and on the dates indicated.
| Signature | Title | Date | ||
| /s/ Samuel N. Hazen Samuel N. Hazen | Chief Executive Officer and Director (Principal Executive Officer) | February 20, 2020 | ||
| /s/ William B. Rutherford William B. Rutherford | Executive Vice President and Chief Financial Officer (Principal Financial Officer and Principal Accounting Officer) | February 20, 2020 | ||
| /s/ Thomas F. Frist III Thomas F. Frist III | Chairman and Director | February 20, 2020 | ||
| /s/ Meg G. Crofton Meg G. Crofton | Director | February 20, 2020 | ||
| /s/ Robert J. Dennis Robert J. Dennis | Director | February 20, 2020 | ||
| /s/ Nancy-Ann DeParle Nancy-Ann DeParle | Director | February 20, 2020 | ||
| /s/ William R. Frist William R. Frist | Director | February 20, 2020 | ||
| /s/ Charles O. Holliday, Jr. Charles O. Holliday, Jr. | Director | February 20, 2020 | ||
| /s/ Geoffrey G. Meyers Geoffrey G. Meyers | Director | February 20, 2020 | ||
| /s/ Michael W. Michelson Michael W. Michelson | Director | February 20, 2020 | ||
| /s/ Wayne J. Riley Wayne J. Riley | Director | February 20, 2020 | ||
| /s/ John W. Rowe John W. Rowe | Director | February 20, 2020 |
HCA HEALTHCARE, INC.
INDEX TO CONSOLIDATED FINANCIAL STATEMENTS
F-1
Report of Independent Registered Public Accounting Firm
The Board of Directors and Stockholders
HCA Healthcare, Inc.
Opinion on the Financial Statements
We have audited the accompanying consolidated balance sheets of HCA Healthcare, Inc. (the Company) as of December 31, 2019 and 2018, the related consolidated statements of income, comprehensive income, stockholders’ deficit and cash flows for each of the three years in the period ended December 31, 2019, and the related notes (collectively referred to as the “consolidated financial statements”). In our opinion, the consolidated financial statements present fairly, in all material respects, the financial position of the Company at December 31, 2019 and 2018, and the results of its operations and its cash flows for each of the three years in the period ended December 31, 2019, in conformity with U.S. generally accepted accounting principles.
We also have audited, in accordance with the standards of the Public Company Accounting Oversight Board (United States) (PCAOB), the Company’s internal control over financial reporting as of December 31, 2019, based on criteria established in Internal Control-Integrated Framework issued by the Committee of Sponsoring Organizations of the Treadway Commission (2013 framework), and our report dated February 20, 2020 expressed an unqualified opinion thereon.
Adoption of New Accounting Standard
As discussed in Note 1 to the consolidated financial statements, effective January 1, 2019, the Company adopted ASU No.
2016-02,
Leases (Topic 842), on a modified retrospective basis.
Basis for Opinion
These financial statements are the responsibility of the Company’s management. Our responsibility is to express an opinion on the Company’s financial statements based on our audits. We are a public accounting firm registered with the PCAOB and are required to be independent with respect to the Company in accordance with the U.S. federal securities laws and the applicable rules and regulations of the Securities and Exchange Commission and the PCAOB.
We conducted our audits in accordance with the standards of the PCAOB. Those standards require that we plan and perform the audit to obtain reasonable assurance about whether the financial statements are free of material misstatement, whether due to error or fraud. Our audits included performing procedures to assess the risks of material misstatement of the financial statements, whether due to error or fraud, and performing procedures that respond to those risks. Such procedures included examining, on a test basis, evidence regarding the amounts and disclosures in the financial statements. Our audits also included evaluating the accounting principles used and significant estimates made by management, as well as evaluating the overall presentation of the financial statements. We believe that our audits provide a reasonable basis for our opinion.
Critical Audit Matters
The critical audit matters communicated below are matters arising from the current period audit of the financial statements that were communicated or required to be communicated to the audit committee and that: (1) relate to accounts or disclosures that are material to the financial statements and (2) involved our especially challenging, subjective or complex judgments. The communication of critical audit matters does not alter in any way our opinion on the consolidated financial statements, taken as a whole, and we are not, by communicating the critical audit matters below, providing separate opinions on the critical audit matters or on the accounts or disclosures to which they relate.
F-2
| Revenue Recognition | ||
| Description of the Matter | For the year ended December 31, 2019, the Company’s revenues were $51.336 billion. As discussed in Note 1 to the consolidated financial statements, revenues are based upon the estimated amounts the Company expects to be entitled to receive from patients and third-party payers. Estimates of contractual allowances under managed care, commercial, and governmental insurance plans are based upon the payment terms specified in the related contractual agreements or as mandated under government payer programs. Management continually reviews the contractual allowances estimation process to consider and incorporate updates to laws and regulations and the frequent changes in managed care contractual terms resulting from contract renegotiations and renewals. Revenues related to uninsured patients and uninsured copayment and deductible amounts for patients who have health care insurance coverage may have discounts applied (uninsured discounts and contractual dis |
Showing the first 8K of 171K characters. Open the full section