 filings.tools
HCA Healthcare 10-K 2022-12-31
Filed 2023-02-17. 23 sections, 566K characters. Original on sec.gov · Markdown · JSON
Cover and table of contents
UNITED STATES
SECURITIES AND EXCHANGE COMMISSION
Washington, D.C. 20549
Form 10-K
(Mark One)
☒ ANNUAL REPORT PURSUANT TO SECTION 13 OR 15(d) OF THE SECURITIES EXCHANGE ACT OF 1934
For the fiscal year ended December 31**,** 2022
Or
☐ TRANSITION REPORT PURSUANT TO SECTION 13 OR 15(d) OF THE SECURITIES EXCHANGE ACT OF 1934
For the transition period from to
Commission File Number 1-11239
HCA Healthcare, Inc.
(Exact Name of Registrant as Specified in its Charter)
| Delaware | 27-3865930 |
| (State or Other Jurisdiction of Incorporation or Organization) | (I.R.S. Employer Identification No.) |
| One Park Plaza Nashville**,** Tennessee | 37203 |
| (Address of Principal Executive Offices) | (Zip Code) |
Registrant’s telephone number, including area code: (615) 344-9551
Securities Registered Pursuant to Section 12(b) of the Act:
| Title of Each Class | Trading Symbol(s) | Name of Each Exchange on Which Registered |
| Common Stock, $0.01 Par Value | HCA | New York Stock Exchange |
Securities Registered Pursuant to Section 12(g) of the Act: None
Indicate by check mark if the Registrant is a well-known seasoned issuer, as defined in Rule 405 of the Securities Act. Yes ☒ No ☐
Indicate by check mark if the Registrant is not required to file reports pursuant to Section 13 or Section 15(d) of the Act. Yes ☐ No ☒
Indicate by check mark whether the Registrant (1) has filed all reports required to be filed by Section 13 or 15(d) of the Securities Exchange Act of 1934 during the preceding 12 months (or for such shorter period that the Registrant was required to file such reports), and (2) has been subject to such filing requirements for the past 90 days. Yes ☒ No ☐
Indicate by check mark whether the Registrant has submitted electronically every Interactive Data File required to be submitted pursuant to Rule 405 of Regulation S-T (§ 232.405 of this chapter) during the preceding 12 months (or for such shorter period that the Registrant was required to submit such files). Yes ☒ No ☐
Indicate by check mark whether the Registrant is a large accelerated filer, an accelerated filer, a non-accelerated filer, a smaller reporting company, or an emerging growth company. See the definitions of “large accelerated filer,” “accelerated filer,” “smaller reporting company” and “emerging growth company” in Rule 12b-2 of the Exchange Act.
| Large accelerated filer | ☒ | Accelerated filer | ☐ |
| Non-accelerated filer | ☐ | Smaller reporting company | ☐ |
| Emerging growth company | ☐ |
If an emerging growth company, indicate by check mark if the Registrant has elected not to use the extended transition period for complying with any new or revised financial accounting standards provided pursuant to Section 13(a) of the Exchange Act. ☐
Indicate by check mark whether the Registrant has filed a report on and attestation to its management’s assessment of the effectiveness of its internal control over financial reporting under Section 404(b) of the Sarbanes-Oxley Act (15 U.S.C. 7262(b)) by the registered public accounting firm that prepared or issued its audit report. ☒
If securities are registered pursuant to Section 12(b) of the Act, indicate by check mark whether the financial statements of the registrant included in the filing reflect the correction of an error to previously issued financial statements. ☐
Indicate by check mark whether any of those error corrections are restatements that required a recovery analysis of incentive-based compensation received by any of the registrant’s executive officers during the relevant recovery period pursuant to §240.10D-1(b). ☐
Indicate by check mark whether the Registrant is a shell company (as defined in Rule 12b-2 of the Act). Yes ☐ No ☒
| Auditor PCAOB ID Number: 42 | Auditor Name: Ernst & Young LLP | Auditor Location: Nashville, Tennessee, United States of America |
As of January 31, 2023, there were 276,966,400 outstanding shares of the Registrant’s common stock. As of June 30, 2022, the aggregate market value of the common stock held by nonaffiliates was approximately $36.171 billion. For purposes of the foregoing calculation only, Hercules Holding II and the Registrant’s directors and executive officers have been deemed to be affiliates.
DOCUMENTS INCORPORATED BY REFERENCE
Portions of the Registrant’s definitive proxy materials for its 2023 Annual Meeting of Stockholders are incorporated by reference into Part III hereof.
INDEX
PART I
Item 1. Business
General
HCA Healthcare, Inc. is one of the leading health care services companies in the United States. At December 31, 2022, we operated 182 hospitals, comprised of 175 general, acute care hospitals; five psychiatric hospitals; and two rehabilitation hospitals. In addition, we operated 126 freestanding surgery centers and 21 freestanding endoscopy centers. Our facilities are located in 20 states and England.
The terms “Company,” “HCA,” “HCA Healthcare,” “we,” “our” or “us,” as used herein and unless otherwise stated or indicated by context, refer to HCA Healthcare, Inc. and its affiliates. The term “affiliates” means direct and indirect subsidiaries of HCA Healthcare, Inc. and partnerships and joint ventures in which such subsidiaries are partners. The terms “facilities” or “hospitals” refer to entities owned and operated by affiliates of HCA, and the term “employees” refers to employees of affiliates of HCA.
Our primary objective is to provide a comprehensive array of quality health care services in the most cost-effective manner possible. Our general, acute care hospitals typically provide a full range of services to accommodate such medical specialties as internal medicine, general surgery, cardiology, oncology, neurosurgery, orthopedics and obstetrics, as well as diagnostic and emergency services. Outpatient and ancillary health care services are provided by our general, acute care hospitals, freestanding surgery centers, freestanding emergency care facilities, urgent care facilities, walk-in clinics, diagnostic centers and rehabilitation facilities. Our psychiatric hospitals provide a full range of mental health care services through inpatient, partial hospitalization and outpatient settings.
Our common stock is traded on the New York Stock Exchange (symbol “HCA”). Through our predecessors, we commenced operations in 1968. HCA Healthcare, Inc. was incorporated in Delaware in October 2010. Our principal executive offices are located at One Park Plaza, Nashville, Tennessee 37203, and our telephone number is (615) 344-9551.
Available Information
We file certain reports with the Securities and Exchange Commission (the “SEC”), including annual reports on Form 10-K, quarterly reports on Form 10-Q and current reports on Form 8-K. The SEC maintains an Internet site at http://www.sec.gov that contains the reports, proxy and information statements and other information we file. Our website address is www.hcahealthcare.com. Please note that our website address is provided throughout this report as an inactive textual reference only. We make available free of charge, through our website, our annual report on Form 10-K, quarterly reports on Form 10-Q, current reports on Form 8-K and all amendments to those reports filed or furnished pursuant to Section 13 or 15(d) of the Exchange Act, as soon as reasonably practicable after such material is electronically filed with or furnished to the SEC. The information provided on our website is not part of this report, and is therefore not incorporated by reference unless such information is specifically referenced elsewhere in this report.
Our Code of Conduct is available free of charge upon request to our Investor Relations Department, HCA Healthcare, Inc., One Park Plaza, Nashville, Tennessee 37203, and is also available on the Ethics and Compliance and Corporate Governance portion of our website at www.hcahealthcare.com.
Business Strategy
We are committed to providing the communities we serve with high quality, convenient and cost-effective health care while growing our business and creating long-term value for our stockholders. We strive to be the health care system of choice in the communities we serve by developing comprehensive networks locally and supporting these networks with enterprise expertise and economies of scale. Our strategy is organized around a framework that seeks to drive sustained growth by delivering operational excellence, attracting exceptional physicians and other health care professionals, developing comprehensive services; creating greater access, and coordinating higher quality care for patients.
To achieve these objectives, we align our efforts around the following growth agenda:
grow our presence in existing markets;
achieve industry-leading performance in clinical, operational and satisfaction measures;
recruit and retain physicians and other health care professionals to meet the need for high quality health services;
continue to utilize economies of scale to grow the Company; and
pursue a disciplined development strategy.
Our strategy also emphasizes investments that advance our clinical systems and digital capabilities, transform care models with innovative care solutions, expand our workforce development programs and enhance our health care networks and partnerships.
Health Care Facilities
We currently own, manage or operate hospitals, freestanding surgery centers, freestanding emergency care facilities, urgent care facilities, walk-in clinics, diagnostic and imaging centers, radiation and oncology therapy centers, comprehensive rehabilitation and physical therapy centers, physician practices, home health, hospice, outpatient physical therapy home and community-based services providers, and various other facilities.
At December 31, 2022, we owned and operated 175 general, acute care hospitals with 48,508 licensed beds. Most of our general, acute care hospitals provide medical and surgical services, including inpatient care, intensive care, cardiac care, diagnostic services and emergency services. The general, acute care hospitals also provide outpatient services such as outpatient surgery, laboratory, radiology, respiratory therapy, cardiology and physical therapy. Each hospital has an organized medical staff and a local board of trustees or governing board comprised of members of the local community.
At December 31, 2022, we operated five psychiatric hospitals with 593 licensed beds. Our psychiatric hospitals provide therapeutic programs, including child, adolescent and adult psychiatric care and adolescent and adult alcohol and drug abuse treatment and counseling.
We also operate outpatient health care facilities, which include freestanding ambulatory surgery centers (“ASCs”), freestanding emergency care facilities, urgent care facilities, walk-in clinics, diagnostic and imaging centers, comprehensive rehabilitation and physical therapy centers, radiation and oncology therapy centers, physician practices and various other facilities. These outpatient services are an integral component of our strategy to develop comprehensive health care networks in select communities. Most of our ASCs are operated through partnerships or limited liability companies, with majority ownership of each partnership or limited liability company typically held by a general partner or member that is an affiliate of HCA.
Certain of our affiliates provide a variety of management services to our health care facilities, including patient safety programs, ethics and compliance programs, national supply contracts, equipment purchasing and leasing contracts, accounting, financial and clinical systems, governmental reimbursement assistance, construction planning and coordination, information technology systems and solutions, legal counsel, human resources services and internal audit services.
COVID-19
We believe the extent of COVID-19’s impact on our operating results and financial condition has been and could continue to be driven by many factors, most of which are beyond our control and ability to forecast. Because of these uncertainties, we cannot estimate how long or to what extent COVID-19 will impact our operations.
Summary Risk Factors
You should carefully read and consider the risk factors set forth under Item 1A, “Risk Factors,” as well as all other information contained in this annual report on Form 10-K. Additional risks and uncerta
Showing the first 8K of 161K characters. Open the full section
Item 1A. Risk Factors
If any of the events discussed in the following risk factors were to occur, our business, financial position, results of operations, cash flows or prospects could be materially, adversely affected. Additional risks and uncertainties not presently known to us or that we currently deem immaterial may also affect us. COVID-19 amplifies and exacerbates many of the risks we face in our business operations, including those discussed below. Our business is subject to the following material risks and uncertainties.
Risks related to COVID-19 and other potential pandemics:
COVID-19 has affected, and may continue to affect, our operations. Further, COVID-19 could negatively impact our business, financial condition, and cash flows, particularly if it causes public health conditions and/or economic conditions to deteriorate.
As a front-line provider of health care services, we have been and continue to be affected by the health and economic effects of COVID-19. Although vaccines and booster shots for the virus causing COVID-19 are widely available in the United States, COVID-19 has continued to result in a significant number of hospitalizations. COVID-19 continues to evolve, including as a result of mutations of the virus. Due to the concentration of our hospitals in Florida and Texas, we may be particularly sensitive to increases in COVID-19 cases in those states, where COVID-19 could have a disproportionate effect on our business. The extent to which COVID-19 will continue to impact our business, results of operations, financial condition and liquidity will depend on future developments that are uncertain and cannot be accurately predicted. We are unable to predict the severity or duration of impacts related to COVID-19, including direct or indirect impacts on macroeconomic conditions.
We continue to work with federal, state and local health authorities to respond to COVID-19 cases in the markets we serve and continue to take and support measures to try to limit the spread of the virus and to mitigate the burden on the health care system. We expect to continue to incur additional costs, which may be significant, as a result of operational changes in response to COVID-19. Further, our response to COVID-19 has required and may continue to require a substantial investment of management’s time and resources across our enterprise, which may affect our ability to properly prioritize and successfully execute on the Company’s strategic initiatives.
We have implemented considerable safety measures within our hospitals and other facilities in response to COVID-19. Nonetheless, treatment of COVID-19 patients has associated risks, which may include the manner in which patients and our physicians and clinical staff perceive and respond to such risks. These risks may result in reduced operating capacity, impaired employee morale and increased exposure to workforce disruptions. Furthermore, we have experienced and may continue to experience supply chain disruptions, including delays and price increases in equipment, pharmaceuticals and medical supplies and supply shortages. Continued constraints on staffing and equipment, laboratory resources and pharmaceutical and medical supplies shortages may impact our ability to schedule, admit and treat patients. In addition, we may be subject to claims from patients, employees and others exposed to COVID-19 at our facilities. Such actions may involve large demands, as well as substantial defense costs. Our insurance, a portion of which is provided through our insurance subsidiaries, may not cover all claims against us.
Our operations and financial performance have been, and may continue to be, affected by actions taken by governmental authorities in response to COVID-19. Some of these measures, such as restrictions on elective procedures, reduced, and may in the future reduce, the volume of procedures performed at our facilities, as well as the volume of emergency room and physician office visits unrelated to COVID-19. Moreover, we believe that some individuals have elected to postpone medical care for an undetermined period of time as a result of COVID-19, impacting patient volumes in comparison to pre-pandemic levels. While patient volumes began rebounding in the second quarter of 2021 as the effects of COVID-19 moderated and pandemic-related restrictions and policies were eased, we experienced a resurgence in COVID-19 cases in the latter half of 2021 and early 2022, further impacting the return to pre-pandemic levels. We cannot provide assurances as to the continued recovery and stability of pre-pandemic patient volumes or the ultimate impact on demand. Further, our patient volumes may be adversely impacted by the expanded use of telehealth services from other providers as a result of reduced regulatory barriers on the use and reimbursement of telehealth services and individuals becoming more comfortable with receiving remote care. The Company may not be able to timely innovate its strategies and technologies to meet changing consumer demands as a result of COVID-19. It is possible that COVID-19 could continue to impact patient behavior in future periods.
Beginning in 2020 and continuing through 2022, we experienced increased patient acuity as a result of COVID-19 cases at our hospitals, which led to increased reimbursements. However, the impacts of COVID-19, including patient acuity levels, in future periods may vary, and could exert unpredictable and potentially negative effects on clinical performance metrics that impact reimbursement levels and could adversely affect our results of operations.
Developments related to COVID-19, including broad economic factors related to COVID-19 and public health conditions, may have a material, adverse effect on our business, results of operations, financial position and cash flows. The ongoing impact of COVID-19 on our business will depend on, among other factors, the duration and severity of any severe or widespread outbreaks of COVID-19; the impact of COVID-19 on economic conditions; the volume of canceled or rescheduled procedures at our facilities; the volume of COVID-19 patients cared for across our health systems; the availability, acceptance of, and need for effective vaccines and medical treatments; the spread of potentially more contagious and/or virulent forms of the virus; and the impact of government actions on the health care industry and broader economy. COVID-19 continues to evolve, and we may not be able to predict or effectively respond to future developments.
The foregoing and other continued disruptions to our business as a result of COVID-19 could heighten the risks in certain of the other risk factors described in this annual report on Form 10-K, any of which could have a material, adverse effect on our results of operations and financial position.
We are unable to predict the ultimate impact of the CARES Act and other stimulus and relief legislation or the effect that such legislation and other governmental responses intended to assist providers in responding to COVID-19 may have on our business, financial condition, results of operations or cash flows.
In response to COVID-19, federal and state governments have passed legislation, promulgated regulations and taken other administrative actions intended to assist health care providers in providing care to COVID-19 and other patients and to provide financial relief to health care providers. Together, the CARES Act, the Paycheck Protection Program and Health Care Enhancement (“PPPHCE”) Act, the Consolidated Appropriations Act, 2021 (“CAA”) and the ARPA authorized over $186 billion in funding to be distributed to hospitals and other health care providers through the Public Health and Social Services Emergency Fund (“PHSSEF”), also known as the Provider Relief Fund, and expanded the Medicare Accelerated and Advance Payment Program. Funds from the Provider Relief Fund are intended to reimburse eligible prov
Showing the first 8K of 112K characters. Open the full section
Item 1B. Unresolved Staff Comments
None.
Item 2. Properties
The following table lists, by state, the number of hospitals (general, acute care, psychiatric and rehabilitation) directly or indirectly owned and operated by us as of December 31, 2022:
| State | Hospitals | Beds | ||||||
| Alaska | 1 | 250 | ||||||
| California | 5 | 1,883 | ||||||
| Colorado | 7 | 2,471 | ||||||
| Florida | 46 | 12,988 | ||||||
| Georgia | 5 | 1,487 | ||||||
| Idaho | 2 | 442 | ||||||
| Indiana | 1 | 278 | ||||||
| Kansas | 4 | 1,400 | ||||||
| Kentucky | 2 | 384 | ||||||
| Louisiana | 3 | 923 | ||||||
| Missouri | 5 | 1,072 | ||||||
| Nevada | 3 | 1,524 | ||||||
| New Hampshire | 3 | 432 | ||||||
| North Carolina | 7 | 1,181 | ||||||
| South Carolina | 3 | 989 | ||||||
| Tennessee | 14 | 2,742 | ||||||
| Texas | 45 | 13,609 | ||||||
| Utah | 8 | 1,038 | ||||||
| Virginia | 11 | 3,300 | ||||||
| International | ||||||||
| England | 7 | 888 | ||||||
| 182 | 49,281 |
In addition to the hospitals listed in the above table, we directly or indirectly operate 126 freestanding surgery centers and 21 freestanding endoscopy centers. We also operate medical office buildings in conjunction with some of our hospitals. These office buildings are primarily occupied by physicians who practice at our hospitals. Twelve of our general, acute care hospitals and five of our other properties have been mortgaged to support our obligations under our senior secured cash flow credit facility.
We maintain our headquarters in approximately 2,031,000 square feet of space in the Nashville, Tennessee area. In addition to the headquarters in Nashville, we maintain regional service centers related to our shared services initiatives. These service centers are located in markets in which we operate hospitals.
We believe our headquarters, hospitals and other facilities are suitable for their respective uses and are, in general, adequate for our present needs. Our properties are subject to various federal, state and local statutes and ordinances regulating their operation. Management does not believe that compliance with such statutes and ordinances will materially affect our financial position or results of operations.
Item 3. Legal Proceedings
The information set forth in Note 10 – Contingencies in the notes to the consolidated financial statements is incorporated herein by reference.
Item 4. Mine Safety Disclosures
None.
PART II
Item 5. . Market for Registrant’s Common Equity, Related Stockholder Matters and Issuer Purchases of Equity Securities
During February 2021, January 2022 and January 2023, our Board of Directors authorized $6 billion, $8 billion and $3 billion, respectively, for share repurchases of the Company’s outstanding common stock. The February 2021 authorization was completed during 2022, and at December 31, 2022, there was $1.586 billion of share repurchase authorization that remained available under the January 2022 authorization. All repurchases made during the fourth quarter of 2022, as detailed below, were made pursuant to the January 2022 share repurchase authorization and were made in the open market.
The following table provides certain information with respect to our repurchases of common stock from October 1, 2022 through December 31, 2022 (dollars in billions, except per share amounts).
| Period | Total Number of Shares Purchased | Average Price Paid per Share | Total Number of Shares Purchased as Part of Publicly Announced Plans or Programs | Approximate Dollar Value of Shares That May Yet Be Purchased Under Publicly Announced Plans or Programs | ||||||||||||
| October 2022 | 1,753,666 | $ | 205.58 | 1,753,666 | $ | 2.745 | ||||||||||
| November 2022 | 2,733,018 | $ | 222.84 | 2,733,018 | $ | 2.136 | ||||||||||
| December 2022 | 2,294,497 | $ | 239.71 | 2,294,497 | $ | 1.586 | ||||||||||
| Total for Fourth Quarter 2022 | 6,781,181 | $ | 224.09 | 6,781,181 | $ | 1.586 |
Our common stock is traded on the New York Stock Exchange (“NYSE”) (symbol “HCA”). During 2022, our Board of Directors declared four quarterly dividends of $0.56 per share, or $2.24 per share in the aggregate, on our common stock. On January 26, 2023, our Board of Directors declared a quarterly dividend of $0.60 per share on our common stock payable on March 31, 2023 to stockholders of record at the close of business on March 17, 2023. Future declarations of quarterly dividends and the establishment of future record and payment dates are subject to the final determination of our Board of Directors. Our ability to declare future dividends may also from time to time be limited by the terms of our debt agreements. At the close of business on February 1, 2023, there were approximately 400 holders of record of our common stock.
STOCK PERFORMANCE GRAPH
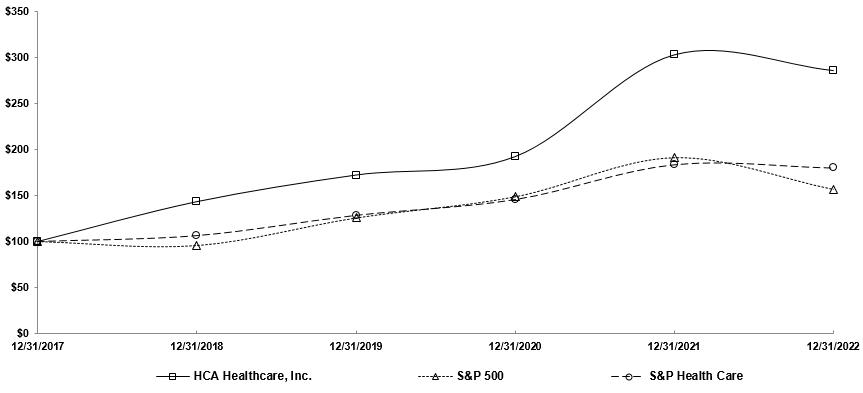
COMPARISON OF 5 YEAR CUMULATIVE TOTAL RETURN
Among HCA Healthcare, Inc., the S&P 500 Index and the S&P Health Care Index
| 12/31/2017 | 12/31/2018 | 12/31/2019 | 12/31/2020 | 12/31/2021 | 12/31/2022 | |||||||||||||||||||
| HCA Healthcare, Inc. | $ | 100.00 | $ | 143.38 | $ | 172.41 | $ | 192.49 | $ | 303.33 | $ | 286.20 | ||||||||||||
| S&P 500 | 100.00 | 95.62 | 125.72 | 148.85 | 191.58 | 156.89 | ||||||||||||||||||
| S&P Health Care | 100.00 | 106.47 | 128.64 | 145.93 | 184.07 | 180.47 |
The graph shows the cumulative total return to our stockholders for the five-year period ended December 31, 2022, in comparison to the cumulative returns of the S&P 500 Index and the S&P Health Care Index. The graph assumes $100 invested on December 31, 2017 in our common stock and in each index with the subsequent reinvestment of dividends. The stock performance shown on the graph represents historical stock performance and is not necessarily indicative of future stock price performance.
Item 6. . [Reserved]
HCA HEALTHCARE, INC.
MANAGEMENT'S DISCUSSION AND ANALYSIS OF FINANCIAL CONDITION
AND RESULTS OF OPERATIONS
Item 7. . Management’s Discussion and Analysis of Financial Condition and Results of Operations
The accompanying consolidated financial statements present certain information with respect to the financial position, results of operations and cash flows of HCA Healthcare, Inc. which should be read in conjunction with the following discussion and analysis. The terms “HCA,” “Company,” “we,” “our,” or “us,” as used herein, refer to HCA Healthcare, Inc. and its affiliates. The term “affiliates” means direct and indirect subsidiaries of HCA Healthcare, Inc. and partnerships and joint ventures in which such subsidiaries are partners.
Forward-Looking Statements
This annual report on Form 10-K includes certain disclosures that contain “forward-looking statements,” within the meaning of the federal securities laws, which involve risks and uncertainties. Forward-looking statements include statements regarding expected share-based compensation expense, expected capital expenditures, expected dividends, expected share repurchases, expected net claim payments, expected inflationary pressures and all other statements that do not relate solely to historical or current facts, and can be identified by the use of words like “may,” “believe,” “will,” “expect,” “project,” “estimate,” “anticipate,” “plan,” “initiative” or “continue.” These forward-looking statements are based on our current plans and expectations and are subject to a number of known and unknown uncertainties and risks, many of which are beyond our control, which could significantly affect current plans and expectations and our future financial position and results of operations. These factors include, but are not limited to, (1) developments related to COVID-19, including, without limitation, the length and severity of its impact and the spread of virus strains with new epidemiological characteristics; the volume of canceled or rescheduled procedures and the volume and acuity of COVID-19 patients cared for across our health systems; measures we are taking to respond to COVID-19; the impact and terms (including the termination or expiration) of government and administrative regulation and stimulus and relief measures (including the Families First Coronavirus Response Act, the Coronavirus Aid, Relief, and Economic Security (“CARES”) Act, the Paycheck Protection Program and Health Care Enhancement Act, the Consolidated Appropriations Act, 2021, the American Rescue Plan Act of 2021 (“ARPA”) and other enacted and potential future legislation) and whether various stimulus and relief programs continue or new similar programs are enacted in the future; changes in revenues due to declining patient volumes, changes in payer mix, deteriorating macroeconomic conditions (including increases in uninsured and underinsured patients) and capacity constraints; potential increased expenses related to inflation or labor, supply chain or other expenditures; supply shortages and disruptions; and the timing, availability and adoption of effective medical treatments and vaccines (including boosters), (2) the impact of our substantial indebtedness and the ability to refinance such indebtedness on acceptable terms, (3) the impact of current and future federal and state health reform initiatives and possible changes to other federal, state or local laws and regulations affecting the health care industry, including but not limited to, the Patient Protection and Affordable Care Act, as amended by the Health Care and Education Reconciliation Act of 2010 (collectively, the “Affordable Care Act”), additional changes to the Affordable Care Act, its implementation, or interpretation (including through executive orders and court challenges), and proposals to expand coverage of federally-funded insurance programs as an alternative to private insurance or establish a single-payer system (such reforms often referred to as “Medicare for All”), (4) the effects related to the implementation of sequestration spending reductions required under the Budget Control Act of 2011, related legislation extending these reductions and those required under the Pay-As-You-Go Act of 2010 (“PAYGO Act”) as a result of the federal budget deficit impact of the ARPA, and the potential for future deficit reduction legislation that may alter these spending reductions, which include cuts to Medicare payments, or create additional spending reductions, (5) increases in the amount and risk of collectability of uninsured accounts and deductibles and copayment amounts for insured accounts, (6) the ability to achieve operating and financial targets, and attain expected levels of patient volumes and control the costs of providing services, (7) possible changes in Medicare, Medicaid and other state programs, including Medicaid supplemental payment programs or Medicaid waiver programs, that may impact reimbursements to health care providers and insurers and the size of the uninsured or underinsured population, (8) personnel related capacity constraints; increases in wages and the ability to attract, utilize and retain qualified management and other personnel, including affiliated physicians, nurses and medical and technical support personnel; and workforce disruptions, (9) the highly competitive nature of the health care business, (10) changes in service mix, revenue mix and surgical volumes, including potential declines in the population covered under third-party payer agreements, the ability to enter into and renew third-party payer provider agreements on acceptable terms and the impact of consumer-driven health plans and physician utilization trends and practices, (11) the efforts of health insurers, health care providers, large employer groups and others to contain health care costs, (12) the outcome of our continuing efforts to monitor, maintain and comply with appropriate laws, regulations, policies and procedures, (13) the availability and terms of capital to fund the expansion of our business and improvements to our existing facilities, (14) changes in accounting practices, (15) changes in general economic conditions nationally and regionally in our markets, including inflation and economic and business conditions (and the impact thereof on the economy and financial markets), (16) the emergence of and effects related to pandemics, epidemics and infectious diseases, (17) future divestitures which may result in charges and possible impairments of long-lived assets, (18) changes in business strategy or development plans, (19) delays in receiving payments for
HCA HEALTHCARE, INC.
MANAGEMENT'S DISCUSSION AND ANALYSIS OF FINANCIAL CONDITION
AND RESULTS OF OPERATIONS (Continued)
Forward-Looking Statements (continued)
services provided, (20) the outcome of pending and any future tax audits, disputes and litigation associated with our tax positions, (21) potential adverse impact of known and unknown government investigations, litigation and other claims that may be made against us, (22) the impact of potential cybersecurity incidents or security breaches, (23) our ongoing ability to demonstrate meaningful use of certified electronic health record (“EHR”) technology and the impact of interoperability requirements, (24) the impact of natural disasters, such as hurricanes and floods, physical risks from climate change or similar events beyond our control, (25) changes in U.S. federal, state, or foreign tax laws including interpretive guidance that may be issued by taxing authorities or other standard setting bodies, and (26) other risk factors described in this annual report on Form 10-K. As a consequence, current plans, anticipated actions and future financial position and results of operations may differ from those expressed in any forward-looking statements made by or on behalf of HCA. You are cautioned not to unduly rely on such forward-looking statements when evaluating the information presented in this report, which forward-looking statements reflect management’s views only as of the date of this report. We undertake no obligation to revise
Showing the first 8K of 75K characters. Open the full section
Item 7A. . Quantitative and Qualitative Disclosures about Market Risk
Information with respect to this Item is provided under the caption “Market Risk” under Item 7, “Management’s Discussion and Analysis of Financial Condition and Results of Operations.”
Item 8. . Financial Statements and Supplementary Data
Information with respect to this Item is contained in our consolidated financial statements indicated in the Index to Consolidated Financial Statements on Page F-1 of this annual report on Form 10-K.
Item 9. . Changes in and Disagreements with Accountants on Accounting and Financial Disclosure
None.
Item 9A. . Controls and Procedures
1. Conclusion Regarding the Effectiveness of Disclosure Controls and Procedures
Under the supervision and with the participation of our management, including our principal executive officer and principal financial officer, we conducted an evaluation of our disclosure controls and procedures, as such term is defined under Rule 13a-15(e) promulgated under the Securities Exchange Act of 1934, as amended (the “Exchange Act”). Based on this evaluation, our principal executive officer and our principal financial officer concluded that our disclosure controls and procedures were effective as of the end of the period covered by this annual report.
2. Internal Control Over Financial Reporting
(a) Management’s Report on Internal Control Over Financial Reporting
Our management is responsible for establishing and maintaining effective internal control over financial reporting, as such term is defined in Exchange Act Rule 13a-15(f). Because of its inherent limitations, internal control over financial reporting may not prevent or detect misstatements. Therefore, even those systems determined to be effective, can provide only reasonable assurance with respect to financial statement preparation and presentation.
Under the supervision and with the participation of our management, including our principal executive officer and principal financial officer, we conducted an assessment of the effectiveness of our internal control over financial reporting based on the framework in Internal Control — Integrated Framework issued by the Committee of Sponsoring Organizations of the Treadway Commission (2013 framework). Based on our assessment under the framework in Internal Control — Integrated Framework, our management concluded that our internal control over financial reporting was effective as of December 31, 2022.
Ernst & Young LLP, the independent registered public accounting firm that audited our consolidated financial statements included in this Form 10-K, has issued a report on our internal control over financial reporting, which is included herein.
(b) Attestation Report of the Independent Registered Public Accounting Firm
Report of Independent Registered Public Accounting Firm
The Board of Directors and Stockholders
HCA Healthcare, Inc.
Opinion on Internal Control over Financial Reporting
We have audited HCA Healthcare, Inc.’s internal control over financial reporting as of December 31, 2022, based on criteria established in Internal Control — Integrated Framework issued by the Committee of Sponsoring Organizations of the Treadway Commission (2013 framework) (the COSO criteria). In our opinion, HCA Healthcare, Inc. (the Company) maintained, in all material respects, effective internal control over financial reporting as of December 31, 2022, based on the COSO criteria.
We also have audited, in accordance with the standards of the Public Company Accounting Oversight Board (United States) (PCAOB), the consolidated balance sheets of HCA Healthcare, Inc. as of December 31, 2022 and 2021, and the related consolidated statements of income, comprehensive income, stockholders’ equity (deficit), and cash flows for each of the three years in the period ended December 31, 2022, and the related notes and our report dated February 17, 2023 expressed an unqualified opinion thereon.
Basis for Opinion
The Company’s management is responsible for maintaining effective internal control over financial reporting and for its assessment of the effectiveness of internal control over financial reporting included in the accompanying Management’s Report on Internal Control Over Financial Reporting. Our responsibility is to express an opinion on the Company’s internal control over financial reporting based on our audit. We are a public accounting firm registered with the PCAOB and are required to be independent with respect to the Company in accordance with the U.S. federal securities laws and the applicable rules and regulations of the Securities and Exchange Commission and the PCAOB.
We conducted our audit in accordance with the standards of the PCAOB. Those standards require that we plan and perform the audit to obtain reasonable assurance about whether effective internal control over financial reporting was maintained in all material respects.
Our audit included obtaining an understanding of internal control over financial reporting, assessing the risk that a material weakness exists, testing and evaluating the design and operating effectiveness of internal control based on the assessed risk, and performing such other procedures as we considered necessary in the circumstances. We believe that our audit provides a reasonable basis for our opinion.
Definition and Limitations of Internal Control Over Financial Reporting
A company’s internal control over financial reporting is a process designed to provide reasonable assurance regarding the reliability of financial reporting and the preparation of financial statements for external purposes in accordance with generally accepted accounting principles. A company’s internal control over financial reporting includes those policies and procedures that (1) pertain to the maintenance of records that, in reasonable detail, accurately and fairly reflect the transactions and dispositions of the assets of the company; (2) provide reasonable assurance that transactions are recorded as necessary to permit preparation of financial statements in accordance with generally accepted accounting principles, and that receipts and expenditures of the company are being made only in accordance with authorizations of management and directors of the company; and (3) provide reasonable assurance regarding prevention or timely detection of unauthorized acquisition, use, or disposition of the company’s assets that could have a material effect on the financial statements.
Because of its inherent limitations, internal control over financial reporting may not prevent or detect misstatements. Also, projections of any evaluation of effectiveness to future periods are subject to the risk that controls may become inadequate because of changes in conditions, or that the degree of compliance with the policies or procedures may deteriorate.
/s/ Ernst & Young LLP
Nashville, Tennessee
February 17, 2023
(c) Changes in Internal Control Over Financial Reporting
During the fourth quarter of 2022, there were no changes in our internal control over financial reporting that materially affected or are reasonably likely to materially affect our internal control over financial reporting.
Item 9B. . Other Information
None.
Item 9C. . Disclosure Regarding Foreign Jurisdictions that Prevent Inspections
None.
PART III
Item 10. . Directors, Executive Officers and Corporate Governance
The information required by this Item regarding the identity and business experience of our directors and executive officers is set forth under the heading “Nominees for Election” and “Election of Directors” in the definitive proxy materials of HCA to be filed in connection with our 2023 Annual Meeting of Stockholders with respect to our directors and is set forth in Item 1 of Part I of this annual report on Form 10-K with respect to our executive officers. The information required by this Item contained in such definitive proxy materials is incorporated herein by reference.
Information on the beneficial ownership reporting for our directors and executive officers required by this Item is contained under the caption “Delinquent Section 16(a) Reports” in the definitive proxy materials to be filed in connection with our 2023 Annual Meeting of Stockholders and is incorporated herein by reference.
Information on our Audit and Compliance Committee and Audit Committee Financial Experts required by this Item is contained under the caption “Corporate Governance” in the definitive proxy materials to be filed in connection with our 2023 Annual Meeting of Stockholders and is incorporated herein by reference.
We have a Code of Conduct which is applicable to all our directors, officers and employees (the “Code of Conduct”). The Code of Conduct is available on the Ethics and Compliance and Corporate Governance pages of our website at www.hcahealthcare.com. To the extent required pursuant to applicable SEC regulations, we intend to post amendments to or waivers from our Code of Conduct (to the extent applicable to our chief executive officer, principal financial officer or principal accounting officer) at this location on our website or report the same on a Current Report on Form 8-K. Our Code of Conduct is available free of charge upon request to our Investor Relations Department, HCA Healthcare, Inc., One Park Plaza, Nashville, TN 37203.
Item 11. . Executive Compensation
The information required by this Item is set forth under the headings “Executive Compensation” and “Compensation Committee Interlocks and Insider Participation” in the definitive proxy materials to be filed in connection with our 2023 Annual Meeting of Stockholders, which information is incorporated herein by reference, except as to information required pursuant to Item 402(v) of SEC Regulation S-K, relating to pay versus performance.
Item 12. . Security Ownership of Certain Beneficial Owners and Management and Related Stockholder Matters
Information about security ownership of certain beneficial owners required by this Item is set forth under the heading “Security Ownership of Certain Beneficial Owners and Management and Related Stockholder Matters” in the definitive proxy materials to be filed in connection with our 2023 Annual Meeting of Stockholders, which information is incorporated herein by reference.
This table provides certain information as of December 31, 2022 with respect to our equity compensation plans:
EQUITY COMPENSATION PLAN INFORMATION
(Share and share unit amounts in millions)
| (a) | (b) | (c) | |||||
| Number of securities to be issued upon exercise of outstanding options, warrants and rights | Weighted-average exercise price of outstanding options, warrants and rights | Number of securities remaining available for future issuance under equity compensation plans (excluding securities reflected in column(a)) | |||||
| Equity compensation plans approved by security holders | 9.586 | (1) | $126.38 | (1) | 18.262 | (2) | |
| Equity compensation plans not approved by security holders | — | — | — | ||||
| Total | 9.586 | $126.38 | 18.262 |
(1)
Includes 1.784 million restricted share units which vest solely based upon continued employment over a specific period of time and 1.715 million performance share units which vest based upon continued employment over a specific period of time and the achievement of predetermined financial targets over time. The performance share units reported reflect the number of performance share units that would vest upon achievement of target performance; the number of performance share units that vest can vary from zero (for actual performance less than 90% of target) to two times the units granted (for actual performance of 110% or more of target). The weighted average exercise price does not take these restricted share units and performance share units into account.
(2)
Includes 13.826 million shares available for future grants under the 2020 Stock Incentive Plan for Key Employees of HCA Healthcare, Inc. and its Affiliates and 4.436 million shares of common stock reserved for future issuance under the HCA Holdings, Inc. Employee Stock Purchase Plan.
- For additional information concerning our equity compensation plans, see the discussion in Note 2 — Share-Based Compensation in the notes to the consolidated financial statements.
Item 13. . Certain Relationships and Related Transactions, and Director Independence
The information required by this Item is set forth under the headings “Certain Relationships and Related Party Transactions” and “Corporate Governance” in the definitive proxy materials to be filed in connection with our 2023 Annual Meeting of Stockholders, which information is incorporated herein by reference.
Item 14. . Principal Accountant Fees and Services
The information required by this Item is set forth under the heading “Ratification of Appointment of Independent Registered Public Accounting Firm” in the definitive proxy materials to be filed in connection with our 2023 Annual Meeting of Stockholders, which information is incorporated herein by reference.
PART IV
Item 15. . Exhibits and Financial Statement Schedules
(a) Documents filed as part of the report:
-
Financial Statements. The accompanying Index to Consolidated Financial Statements on page F-1 of this annual report on Form 10-K is provided in response to this item.
-
List of Financial Statement Schedules. All schedules are omitted because the required information is either not present, not present in material amounts or presented within the consolidated financial statements.
3. List of Exhibits
Showing the first 8K of 76K characters. Open the full section
Item 16. . Form 10-K Summary
None.
SIGNATURES
Pursuant to the requirements of Section 13 or 15(d) of the Securities Exchange Act of 1934, the Registrant has duly caused this report to be signed on its behalf by the undersigned, thereunto duly authorized.
| HCA HEALTHCARE, INC. | |
| By: | /S/ SAMUEL N. HAZEN |
| Samuel N. Hazen Chief Executive Officer |
Dated: February 17, 2023
Pursuant to the requirements of the Securities Exchange Act of 1934, this report has been signed below by the following persons on behalf of the Registrant and in the capacities and on the dates indicated.
| Signature | Title | Date |
| /S/ SAMUEL N. HAZEN | Chief Executive Officer and Director (Principal Executive Officer) | February 17, 2023 |
| Samuel N. Hazen | ||
| /S/ WILLIAM B. RUTHERFORD | Executive Vice President and Chief Financial Officer (Principal Financial Officer and Principal Accounting Officer) | February 17, 2023 |
| William B. Rutherford | ||
| /S/ THOMAS F. FRIST III | Chairman and Director | February 17, 2023 |
| Thomas F. Frist III | ||
| /S/ MEG G. CROFTON | Director | February 17, 2023 |
| Meg G. Crofton | ||
| /S/ ROBERT J. DENNIS | Director | February 17, 2023 |
| Robert J. Dennis | ||
| /S/ NANCY-ANN DEPARLE | Director | February 17, 2023 |
| Nancy-Ann DeParle | ||
| /S/ WILLIAM R. FRIST | Director | February 17, 2023 |
| William R. Frist | ||
| /S/ CHARLES O. HOLLIDAY, JR. | Director | February 17, 2023 |
| Charles O. Holliday, Jr. | ||
| /S/ HUGH F. JOHNSTON | Director | February 17, 2023 |
| Hugh F. Johnston | ||
| /S/ MICHAEL W. MICHELSON | Director | February 17, 2023 |
| Michael W. Michelson | ||
| /S/ WAYNE J. RILEY | Director | February 17, 2023 |
| Wayne J. Riley | ||
| /S/ ANDREA B. SMITH | Director | February 17, 2023 |
| Andrea B. Smith |
HCA HEALTHCARE, INC.
INDEX TO CONSOLIDATED FINANCIAL STATEMENTS
F-1
Report of Independent Registered Public Accounting Firm
The Board of Directors and Stockholders
HCA Healthcare, Inc.
Opinion on the Financial Statements
We have audited the accompanying consolidated balance sheets of HCA Healthcare, Inc. (the Company) as of December 31, 2022 and 2021, the related consolidated statements of income, comprehensive income, stockholders’ equity (deficit) and cash flows for each of the three years in the period ended December 31, 2022, and the related notes (collectively referred to as the “consolidated financial statements”). In our opinion, the consolidated financial statements present fairly, in all material respects, the financial position of the Company at December 31, 2022 and 2021, and the results of its operations and its cash flows for each of the three years in the period ended December 31, 2022, in conformity with U.S. generally accepted accounting principles.
We also have audited, in accordance with the standards of the Public Company Accounting Oversight Board (United States) (PCAOB), the Company’s internal control over financial reporting as of December 31, 2022, based on criteria established in Internal Control-Integrated Framework issued by the Committee of Sponsoring Organizations of the Treadway Commission (2013 framework), and our report dated February 17, 2023 expressed an unqualified opinion thereon.
Basis for Opinion
These financial statements are the responsibility of the Company's management. Our responsibility is to express an opinion on the Company’s financial statements based on our audits. We are a public accounting firm registered with the PCAOB and are required to be independent with respect to the Company in accordance with the U.S. federal securities laws and the applicable rules and regulations of the Securities and Exchange Commission and the PCAOB.
We conducted our audits in accordance with the standards of the PCAOB. Those standards require that we plan and perform the audit to obtain reasonable assurance about whether the financial statements are free of material misstatement, whether due to error or fraud. Our audits included performing procedures to assess the risks of material misstatement of the financial statements, whether due to error or fraud, and performing procedures that respond to those risks. Such procedures included examining, on a test basis, evidence regarding the amounts and disclosures in the financial statements. Our audits also included evaluating the accounting principles used and significant estimates made by management, as well as evaluating the overall presentation of the financial statements. We believe that our audits provide a reasonable basis for our opinion.
Critical Audit Matters
The critical audit matters communicated below are matters arising from the current period audit of the financial statements that were communicated or required to be communicated to the audit committee and that: (1) relate to accounts or disclosures that are material to the financial statements and (2) involved our especially challenging, subjective or complex judgments. The communication of critical audit matters does not alter in any way our opinion on the consolidated financial statements, taken as a whole, and we are not, by communicating the critical audit matters below, providing separate opinions on the critical audit matters or on the accounts or disclosures to which they relate.
F-2
| Revenue Recognition | |
| Description of the Matter | For the year ended December 31, 2022, the Company’s revenues were $60.233 billion. As discussed in Note 1 to the consolidated financial statements, revenues are based upon the estimated amounts the Company expects to be entitled to receive from patients and third-party payers. Estimates of contractual allowances under managed care and commercial insurance plans are based upon the payment terms specified in the related contractual agreements. Management continually reviews the contractual allowances estimation process to consider and incorporate updates to laws and regulations and the frequent changes in managed care contractual terms resulting from contract renegotiations and renewals. Revenues related to uninsured patients and uninsured copayment and deductible amounts for patients who have health care coverage may have discounts applied (uninsured discounts and contractual discounts). The Company also records estimated implicit price concessions (based primarily on historical collection experience) related to uninsured accounts to record these revenues and accounts receivable at the estimated amounts the Company expects to collect. The primary collection risks relate to uninsured patient accounts, including amounts owed from patients after insurance has paid the amounts covered by the applicable agreement. Implicit price concessions relate primarily to amounts due d |
Showing the first 8K of 117K characters. Open the full section