 filings.tools
Item 1. Business
250K characters. Original on sec.gov · Markdown
Item 1. Business
Moderna is pioneering a new class of medicines made of messenger RNA, or mRNA. The potential implications of using mRNA as a drug are significant and far-reaching and could meaningfully improve how medicines are discovered, developed, manufactured and administered.
Since our founding in 2010, we have transformed from a research-stage company advancing programs in the field of mRNA to a commercial enterprise with a diverse clinical portfolio of vaccines and therapeutics across seven modalities, a broad intellectual property portfolio in areas including mRNA and lipid nanoparticle (LNP) formulation, and an integrated manufacturing plant that allows for rapid clinical and commercial production at scale. Moderna has established relationships with a broad range of domestic and overseas government and commercial collaborators, which has allowed for the pursuit of both groundbreaking science and rapid scaling of our manufacturing capabilities. Most recently, Moderna’s capabilities have come together to allow the authorization and approval of one of the earliest and most-effective vaccines against the COVID-19 pandemic.
In 2020, mRNA technology emerged as a new class of medicine. In under a year, we designed our vaccine against COVID-19 (mRNA-1273) using mRNA-based technology, conducted clinical trials, which demonstrated that the vaccine was highly effective at preventing COVID-19, and obtained an Emergency Use Authorization (EUA) from the U.S. Food and Drug Administration (FDA) and authorizations from other regulators around the world. During 2021, we shipped more than 800 million doses of our COVID-19 vaccine to countries around the globe to help fight the pandemic, with approximately 25% of those doses going to low- and middle-income countries. In January 2022, the FDA approved the Biologics License Application (BLA) for our COVID-19 vaccine, Spikevax*®*, for individuals 18 years of age and older in the United States.
THE mRNA OPPORTUNITY
mRNA, the software of life
mRNA transfers the information stored in our genes to the cellular machinery that makes all the proteins required for life. Our genes are stored as sequences of DNA which contain the instructions to make specific proteins. DNA serves as a hard drive, safely storing these instructions in the nucleus until they are needed by the cell.
When a cell needs to produce a protein, the instructions to make that protein are copied from the DNA to mRNA, which serves as the template for protein production. Each mRNA molecule contains the instructions to produce a specific protein with a distinct function in the body. mRNA transmits those instructions to cellular machinery, called ribosomes, that make copies of the required protein.
We see mRNA functioning as the “software of life.” Every cell uses mRNA to provide real time instructions to make the proteins necessary to drive all aspects of biology, including in human health and disease. This was codified as the central dogma of molecular biology over 50 years ago, and is exemplified in the schematic below.

The structure of mRNA
Messenger RNA is a linear polymer comprising four monomers called nucleotides: adenosine (A), guanosine (G), cytosine (C), and uridine (U). Within the region of the molecule that codes for a protein, or the coding region, the sequence of these four nucleotides forms a language made up of three-letter words called codons. The first codon, or start codon (AUG), signals where the ribosome should start protein synthesis. To know what protein to make, the ribosome then progresses along the mRNA one codon at a time, appending the appropriate amino acid to the growing protein. To end protein synthesis, three different codons (UAA, UAG, and UGA)
Table of Content
serve as stop signals, telling the ribosome where to terminate protein synthesis. In total, there are 64 potential codons, but only 20 amino acids that are used to build proteins; therefore, multiple codons can encode for the same amino acid.
The process of protein production is called translation because the ribosome is reading in one language (a sequence of codons) and outputting in another language (a sequence of amino acids). The coding region is analogous to a sentence in English. Much like a start codon, a capitalized word can indicate the start of a sentence. Codons within the coding region resemble groups of letters representing words. The end of the sentence is signaled by a period in English, or a stop codon for mRNA.
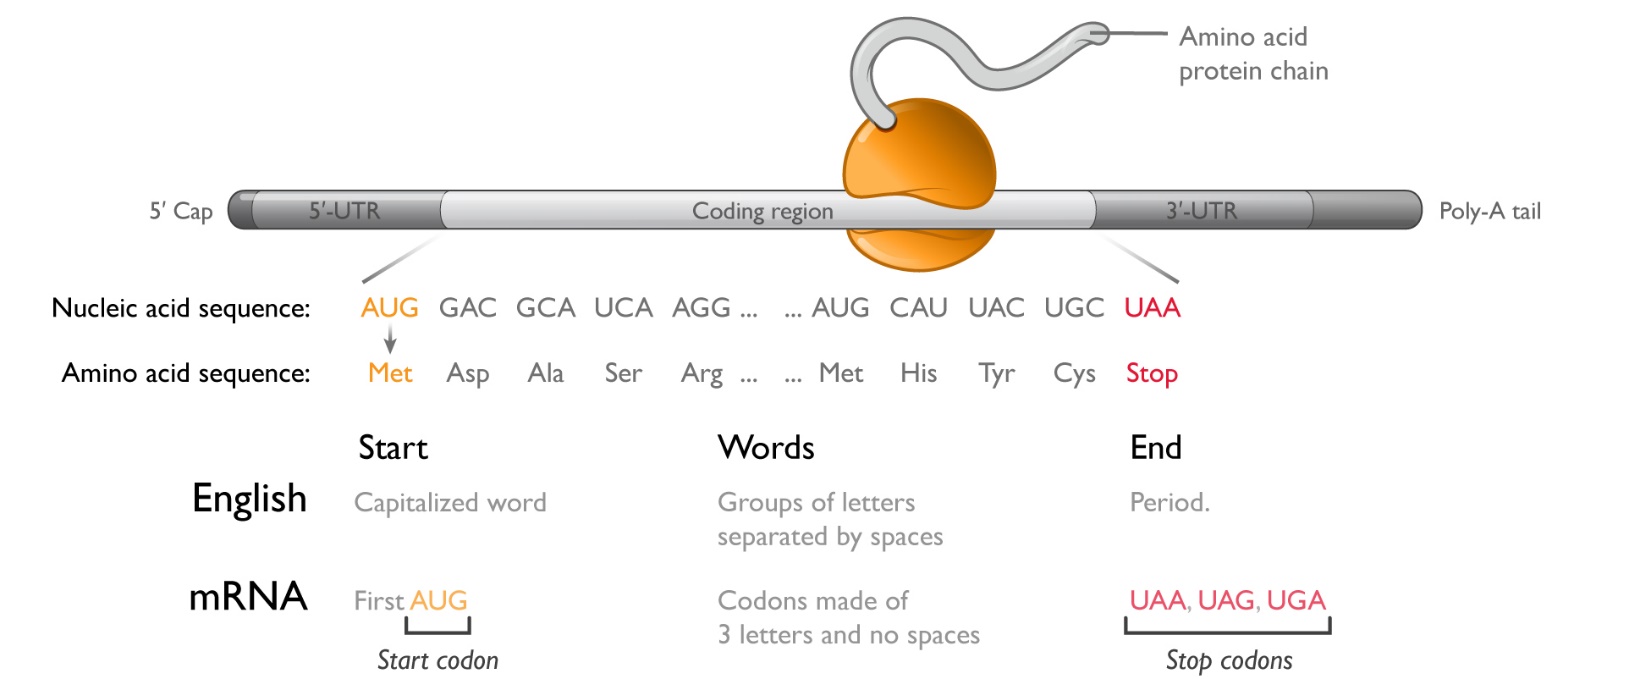
In every cell, hundreds of thousands of mRNAs make hundreds of millions of proteins every day. A typical protein contains 200-600 amino acids; therefore, a typical mRNA coding region ranges from 600-1,800 nucleotides. In addition to the coding region, mRNAs contain four other key features: (1) the 5’ untranslated region or 5’-UTR; (2) the 3’ untranslated region or 3’-UTR; (3) the 5’ cap; and (4) a 3’ polyadenosine, or poly-A, tail. The sequence of nucleotides in the 5’-UTR influences how efficiently the ribosome initiates protein synthesis, whereas the sequence of nucleotides in the 3’-UTR contains information about which cell types should translate that mRNA and how long the mRNA should last. The 5’ cap and 3’ poly-A tail enhance ribosome engagement and protect the mRNA from attack by intracellular enzymes that digest mRNA from its ends.
The intrinsic advantages of using mRNA as a medicine
mRNA possesses inherent characteristics that we believe provide it with a strong foundation as a new class of medicines. These characteristics include:
-
mRNA is used by every cell to produce all proteins:** mRNA is used to make every type of protein, including secreted, membrane, and intracellular proteins, in varying quantities over time, in different locations, and in various combinations. Given the universal role of mRNA in protein production, we believe that mRNA medicines could have broad applicability across human disease.
-
Making proteins inside one’s own cells mimics human biology:** Using a person’s own cells to produce protein therapeutics or vaccine antigens provides certain advantages over existing technologies such as recombinant proteins, which are manufactured using processes that are foreign to the human body.
-
mRNA has a simple and flexible chemical structure:** Each mRNA molecule comprises four chemically similar nucleotides to encode proteins made from up to 20 chemically different amino acids. To make the full diversity of possible proteins, only simple sequence changes are required in mRNA.
-
mRNA has classic pharmacologic features:** mRNA possesses many of the attractive pharmacologic features of most modern medicines, including reproducible activity, predictable potency, and well-behaved dose dependency; mRNA also provides the ability to adjust dosing based on an individual patient’s needs, including stopping or lowering the dose, to seek to ensure safety and tolerability.
mRNA as a new class of medicines
Unlike traditional approaches to medicine, where a protein or chemical is introduced to the body, we send tailored mRNA into cells to instruct them to produce specific proteins. Instead of starting from scratch for each new vaccine or therapy, our mRNA approach
Table of Content
leverages the technology and fundamental components that we have been researching and developing since our founding. Our success in developing, manufacturing and commercializing the Moderna COVID-19 vaccine further supports our belief that mRNA-based medicines as a class have the potential to help patients in far-reaching ways that could exceed the impact of traditional approaches to medicine.
We have developed four core beliefs about the value drivers of mRNA as a new class of medicines:
1.mRNA has the potential to create an unprecedented abundance and diversity of medicines. mRNA’s breadth of applicability has the potential to create an extraordinary number of new mRNA-based medicines that are currently beyond the reach of recombinant protein technology.
2.Advances in the development of our mRNA medicines reduce risks across our portfolio. mRNA medicines share fundamental features that can be used to learn quickly across a portfolio. We believe that once safety and proof of protein production has been established in one program, the technology and biology risks of related programs that use similar mRNA technologies, delivery technologies, and manufacturing processes will decrease significantly.
3.mRNA technology can accelerate discovery and development. The software-like features of mRNA enable rapid in silico design and the use of automated high-throughput synthesis processes that permit discovery to proceed in parallel rather than sequentially. We believe these mRNA features can also accelerate drug development by allowing the use of shared manufacturing processes and infrastructure.
4.The ability to leverage shared processes and infrastructure can drive significant capital efficiency over time. We believe the manufacturing requirements of different mRNA medicines are similar and that at commercial scale, a portfolio of mRNA medicines will benefit from shared capital expenditures.
OUR STRATEGY
We believe that the development of mRNA as a new class of medicines, as evidenced by the development of mRNA-based vaccines during 2020, represents a significant breakthrough for patients and our industry. Our success in developing a highly effective vaccine against COVID-19, going from sequence selection, conducting clinical trials and to receipt of regulatory authorization for emergency use, all in less than a year, provides a visible example of the promise of mRNA-based medicine. The Moderna COVID-19 Vaccine/Spikevax has been authorized for use or approved in over 70 countries. In January 2022, the FDA approved the BLA for Spikevax for individuals 18 years of age and older in the United States. From the beginning of the pandemic through December 31, 2021, we delivered 824 million doses of our vaccine, helping to vaccinate millions of people worldwide and combat the pandemic. We believe our success in developing this vaccine has positive implications beyond infectious disease vaccines and across our entire pipeline. We currently have 44 programs in development, and our pipeline spans five therapeutic areas: infectious diseases, immuno-oncology, rare diseases, cardiovascular diseases and autoimmune diseases.
In order to deliver on the full scope of the mRNA opportunity and maximize long-term value for patients and investors, we have developed four pillars underlying our product strategy that guide our near-term and long-term goals:
1.Continue to advance our COVID-19 program and bring to market a pan-respiratory annual booster vaccine. Our long-term vision is to develop, and seek regulatory approval for, a convenient, annual, single-dose booster against as many respiratory viruses as possible. mRNA vaccines have the ability to combine multiple different antigens into one vaccine. We believe a single-dose booster would provide significant value to patients and healthcare systems, as compliance and convenience would increase and there would be a reduction in vaccine administration costs.
This vision includes a single-dose booster vaccine against COVID-19, seasonal flu and respiratory syncytial virus (RSV). We are developing vaccines against each of these diseases individually, while also pursuing parallel development of combination vaccines. We are committed to bringing COVID-19 booster shots (variant-specific, if needed) to the market until the pandemic is under control. We have announced positive Phase 1 data for both our flu vaccine (mRNA-1010) and RSV vaccine (mRNA-1345). mRNA-1010 is preparing for a Phase 3 trial to start in 2022 and mRNA-1345 has started the Phase 3 portion of a pivotal Phase 2/3 study. We are also exploring agreements with governments around the world to establish local manufacturing capabilities in their countries, which would provide those governments with access to these annual vaccines, as well as future pandemic preparedness capabilities.
2.Bring to market first-in-class vaccines against latent viruses. Latent viruses, such as cytomegalovirus (CMV), Epstein-Barr virus (EBV) and human immunodeficiency virus (HIV), cause acute infections and significant long-term effects, or sequelae. CMV infection is the leading infectious cause of birth defects in children in the U.S. and is a major driver of immune dysfunction with aging, including cardiovascular diseases, cancer and cognitive impairment. EBV infection is a
Table of Content
major cause of infectious mononucleosis (IM), has been tied to increased risk of developing multiple sclerosis, and is associated with certain lymphoproliferative disorders, higher risk of developing cancer/autoimmune diseases and long-COVID. Untreated HIV infection causes impairment of the immune system, leading to acquired immunodeficiency syndrome (AIDS).
Our CMV vaccine (mRNA-1647) is in an ongoing pivotal Phase 3 study to evaluate the safety and efficacy of mRNA-1647 against primary CMV infection in women ages 16-40 years. Our prophylactic EBV vaccine (mRNA-1189) is in an ongoing Phase 1 study. We have two partnered HIV programs, one that is in an ongoing Phase 1 study (mRNA-1644) and another that is preparing to enter the clinic (mRNA-1547). In February 2022, we announced two new development candidates against herpes simplex virus (HSV) and varicella-zoster virus (VZV). Both of these candidates are in preclinical development.
3.Bring to market therapeutics based on mRNA-encoded proteins. We believe that mRNA medicines have the potential to provide patients with any therapeutic protein, including those targeting intracellular or membrane proteins. Across our therapeutics pipeline, we have 15 development programs across four therapeutic areas: oncology, cardiovascular, rare disease and autoimmune diseases.
We have had positive, early signals in clinical studies in oncology, cardiovascular and rare diseases, demonstrating early proof-of-concept. However, we are still waiting to advance these programs through full clinical development and regulatory review, as we have done with our COVID-19 vaccine.
4.Expand our portfolio through strategic investments that leverage or enhance our platform. As we advance our existing technologies in mRNA and LNP delivery as well as our biology expertise, we believe we can expand our portfolio through collaborations. This strategy includes bringing forward novel nucleic acid editing capabilities through Moderna Genomics (MGX), which is our effort to expand the use of our platform to create more innovative drugs to help patients through complex gene editing. We are committed to advancing this research responsibly and are working toward identifying the right combinations of technologies that can leverage our platform and lead to further breakthroughs in this area.
In December 2021, we announced a collaboration with Metagenomi, Inc., a genetic medicines company with a versatile portfolio of next-generation gene editing tools, focused on advancing new gene editing systems for in vivo human therapeutic applications. In January 2022, we announced a collaboration with Carisma Therapeutics, Inc. to discover, develop and commercialize in vivo engineered chimeric antigen receptor monocyte (CAR-M) therapeutics for the treatment of cancer.
The strategic principles that guide our approach are:
-
We seek to discover and develop a large pipeline in parallel.** Our goal is to address or prevent as many human diseases as our technology, talent, capital, and other resources permit. We do so as rapidly as we can, understanding both the urgency for patients and the need to be disciplined in our approach.
-
We undertake sustained, long-term investment in technology creation.** We aim to improve the performance of mRNA medicines in our current modalities, and to unlock new modalities, through investments within basic and applied science.
-
We focus on the pace and scale of our learning.** We seek to accelerate our progress by solving numerous technical problems in parallel rather than in sequence. We make significant investments in digital assets and research infrastructure to accelerate the pace and scale of our learning.
-
We integrate across the most critical parts of our value chain.** mRNA is a complex multicomponent system and we believe it demands integration. We believe that we must be directly engaged in research, drug discovery, drug development, process and analytical development, and manufacturing to accelerate our learning, reduce our risk, and protect our critical know-how.
-
We forward invest in core enabling capabilities and infrastructure.** To execute across a broad pipeline, we need to invest at risk before we have all the answers. Our forward investments focus on areas where lead times are long and where early investments can reduce execution risk and accelerate future progress. We proactively invested in a dedicated manufacturing facility, the Moderna Technology Center (MTC), in Norwood, Massachusetts, to support the anticipated growth of our pipeline, and this early investment greatly facilitated our ability to respond to the COVID-19 pandemic by allowing us to begin production of our vaccine even before we received regulatory authorization for its distribution.
Table of Content
OUR PLATFORM
Overview of our platform
Our mRNA “platform” refers to our accumulated knowledge and capabilities in basic and applied sciences. There are three key components to our platform: mRNA, delivery, and the manufacturing process. Our platform incorporates advances across all three of these areas as we advance our medicines. It is the integration of these components that allows us to make our medicines and we combine different versions of mRNA delivery and process into each of our medicines.
There are common features between groups of medicines, which we call “modalities.” These modalities are the application of our platform – the groupings have common features in mRNA or delivery technology or in the process by which they are made. This strategy allows us to manage risk across development programs as well as to understand, in cases of success, where we can rapidly expand and build on success with similar programs.
The primary goal of our platform is to identify new modalities and to expand the utility of our existing modalities. Programs within a modality often have correlated technology risk, but because they pursue diverse diseases, they often have uncorrelated biology risk. Each time we add a modality and a new medicine to our portfolio, we create a network effect because each incremental program can help us gain additional insight into the other the programs in our pipeline.
We have created seven modalities to date:
-
Prophylactic vaccines
-
Systemic secreted and cell surface therapeutics
-
Cancer vaccines
-
Intratumoral immuno-oncology
-
Localized regenerative therapeutics
-
Systemic intracellular therapeutics
-
Inhaled pulmonary therapeutics
Our platform: mRNA science advancements
We continue to invest in both basic and applied research, seeking to advance both the state of our technology and the state of the scientific community’s understanding of mRNA. Examples of advances in mRNA science that combine nucleotide chemistry, sequence engineering, and targeting elements are described below.
mRNA chemistry: Modified nucleotides to mitigate immune system activation: The innate immune system has evolved to protect cells from foreign RNA, such as viral RNA, by inducing inflammation and suppressing mRNA translation once detected. Many cells surveil their environment through sensors called toll-like-receptors (TLRs). These include types that are activated by the presence of double-stranded RNA (TLR3) or uridine containing RNA fragments (TLR7, TLR8). Additionally, all cells have cytosolic double-stranded RNA, sensors, including retinoic acid inducible gene-I (RIG-I) that are sensitive to foreign RNA inside the cell.
The immune and cellular response to mRNA is complex, context specific, and often linked to the sensing of uridine. To minimize undesired immune responses to our potential mRNA medicines, our platform employs chemically-modified uridine nucleotides to minimize recognition by both immune cell sensors such as TLR3/7/8, and broadly-distributed cytosolic receptors such as RIG-I.
mRNA sequence engineering: Maximizing protein expression: mRNA exists transiently in the cytoplasm, during which time it can be translated into thousands of proteins before eventually being degraded. Our platform applies bioinformatic, biochemical, and biological screening capabilities, most of which have been invented internally that aim to optimize the amount of protein produced per mRNA. We have identified proprietary sequences for the 5’-UTR that have been observed to increase the likelihood that a ribosome bound to the 5’-end of the mRNA transcript will find the desired start codon and reliably initiate translation of the coding region. We additionally design the nucleotide sequence of the coding region to maximize its successful translation into protein.
Targeting elements: Enabling tissue-targeted translation: All nucleated cells in the body are capable of translating mRNA, resulting in pharmacologic activity in any cell in which mRNA is delivered and translated. To minimize or prevent potential off-target effects, our platform employs technologies that regulate mRNA translation in select cell types. Cells often contain short RNA sequences, called microRNAs or miRNAs, that bind to mRNA to regulate protein translation at the mRNA level. Different cell types have different concentrations of specific microRNAs, in effect giving cells a microRNA signature. microRNA binding directly to mRNA effectively silences or reduces mRNA translation and promotes mRNA degradation. We design microRNA binding sites into the 3’-UTR of our potential mRNA medicines so that if our mRNA is delivered to cells with such microRNAs, it will be minimally translated and rapidly degraded.
Table of Content
Our platform: Delivery science
Our mRNA can, in specific instances, such as our VEGF therapeutic, be delivered by direct injection to a tissue in a simple saline formulation without LNPs to locally produce small amounts of pharmacologically active protein. However, the blood and interstitial fluids in humans contain significant RNA degrading enzymes that rapidly degrade any extracellular mRNA and prevent broader distribution without LNPs. Additionally, cell membranes tend to act as a significant barrier to entry of large, negatively-charged molecules such as mRNA. We have therefore invested heavily in delivery science and have developed LNP technologies to enable delivery of larger quantities of mRNA to target tissues.
LNPs are generally composed of four components: an amino lipid, a phospholipid, cholesterol, and a pegylated-lipid (PEG-lipid). Each component, as well as the overall composition, or mix of components, contributes to the properties of each LNP system. LNPs containing mRNA injected into the body rapidly bind proteins that can drive uptake of LNPs into cells. Once internalized in endosomes within cells, the LNPs are designed to escape the endosome and release their mRNA cargo into the cell cytoplasm, where the mRNA can be translated to make a protein and have the desired therapeutic effect. Any mRNA and LNP components that do not escape the endosome are typically delivered to lysosomes where they are degraded by the natural process of cellular digestion. Examples of tools we developed by using our platform include proprietary LNP formulations that address the steps of mRNA delivery, including cell uptake, endosomal escape, and subsequent lipid metabolism, and for avoidance of counterproductive interactions with the immune system.
Chemistry: Novel lipid chemistry to potentially improve safety and tolerability: We initially used LNP formulations that were based on known lipid systems, which we refer to as “legacy LNPs.” A recognized limitation of these legacy LNPs is the potential for inflammatory reactions upon single and repeat administration that can impact tolerability and therapeutic index. Our later-developed, proprietary LNP systems are therefore designed to be highly tolerated and minimize any LNP vehicle-related toxicities with repeat administration in vivo. The changes we made have included engineering amino lipids to avoid the immune system and to be rapidly biodegradable relative to prior lipids.
Composition: Proprietary LNPs enhance delivery efficiency: Our platform includes extensive in-house expertise in medicinal chemistry, which we have applied to design large libraries of novel lipids. Using these libraries in combination with our discovery biology capabilities, we have conducted high throughput screens for desired LNP properties and believe that we have made fundamental discoveries in preclinical studies about the relationships between structural motifs of lipids and LNP performance for protein expression.
Surface properties: Novel LNP design to avoid immune recognition: We have designed our proprietary LNP systems for sustained pharmacology upon repeat dosing by eliminating or altering features that activate the immune system. These are based on insights into the surface properties of LNPs. Upon repeated dosing, surface features on traditional LNPs such as amino lipids, phospholipids, and PEG-lipids, can be recognized by the immune system, leading to rapid clearance from the bloodstream, a decrease in potency upon repeat dosing, and an increase in inflammation. Based on our insights into these mechanisms, we have engineered our LNP systems to reduce or eliminate undesirable surface features. In preclinical studies in non-human primates for our systemic therapeutic development candidates that use our novel LNP systems, we have been able to repeat dose with negligible or undetectable loss in potency, liver damage, and immune system activation.
Our platform: Manufacturing process science
We invest significantly in manufacturing process science to impart more potent features to our mRNA and LNPs, and to invent the technological capabilities necessary to manufacture our mRNA medicines at scales ranging from micrograms to kilograms, as well as achieve pharmaceutical properties such as solubility and shelf life. We view developing these goals of manufacturing and pharmaceutical properties as appropriate for each program, based on its stage of development.
mRNA manufacturing process: Improving pharmacology: Our platform creates mRNA using a cell-free approach called in vitro transcription in which an RNA polymerase enzyme binds to and transcribes a DNA template, adding the nucleotides encoded by the DNA to the growing RNA strand. Following transcription, we employ proprietary purification techniques to ensure that our mRNA is free from undesired synthesis components and impurities that could activate the immune system in an indiscriminate manner. Applying our understanding of the basic science underlying each step in the manufacturing process, we have designed proprietary manufacturing processes to impart desirable pharmacologic features, for example increasing potency in a vaccine.
Table of Content
LNP manufacturing process: Improving pharmacology: Our platform technology includes synthetic processes to produce LNPs. Traditionally LNPs are assembled by dissolving the four molecular components, amino lipid, phospholipid, cholesterol, and PEG-lipid, in ethanol and then mixing this with mRNA in an aqueous buffer. The resulting mixture is then purified to isolate LNPs from impurities. Such impurities include molecular components that have not been incorporated into particles, un-encapsulated mRNA that could activate the immune system, and particles outside of the desired size range. Going beyond optimization of traditional manufacturing processes, we have invested in understanding and measuring the various biochemical and physical interactions during LNP assembly and purification. We have additionally developed state-of-the-art analytical techniques necessary to characterize our LNPs and biological systems to analyze their in vitro and in vivo performance. With these insights, we have identified manufacturing process parameters that drive LNP performance, for example, the potency in a secreted therapeutic setting. These insights have allowed us to make significant improvements in the efficiency of our processing and the potency of our LNPs.
Manufacturing facilities and scale: One of the key aspects of our mRNA platform is that a single manufacturing facility can be used to manufacture any of our mRNA medicines. In 2016, following positive Phase 1 data, we decided to build our clinical manufacturing site in Norwood, Massachusetts. This facility produces not only mRNA medicines for all of our preclinical experiments and clinical trials, but has also produced millions of doses of our COVID-19 vaccine for commercial use. We have also partnered with Lonza and additional contract manufacturing organizations (CMOs) to scale up our manufacturing capabilities globally in an effort to combat the COVID-19 pandemic. We are currently working with governments in different geographies to build additional manufacturing facilities, with a view toward being able to combat future pandemics.
Demonstrations of our platform
Since our founding in 2010, we have made considerable advancements across our platform. Several examples are described below.
Dose-dependent protein expression in the clinic: We have demonstrated in the clinic the ability to generate consistent dose dependent levels of protein (antibodies) as well as the ability to safely repeat dose. For example, we demonstrated the ability to safely repeat dosing in the Phase 1 study of our Chikungunya Antibody program (mRNA-1944), which demonstrated dose-dependent increases in levels of antibodies against chikungunya.
Reproducible pharmacology, including upon repeated dosing: By combining advances in mRNA, delivery, and manufacturing process science, we have demonstrated in preclinical studies sustained and reproducible pharmacology. An example is seen in a mouse model that recapitulates metabolic defects in propionic acidemia (PA). In this rare disease, a defect in one or both of two different subunits (PCCA and PCCB) of the mitochondrial enzyme propionyl-CoA carboxylase results in accumulation of toxic metabolites such as 2-methylcitrate (2MC). In mice hypomorphic for the PCCA subunit, monthly intravenous (IV) administration of mRNAs encoding PCCA and PCCB formulated in our proprietary LNP (mRNA-3927) resulted in a significant and sustained lowering of 2MC throughout the duration of the 6-month study compared to control (luciferase) mRNA (1 mg/kg, n=6/group).
Decreased immune activation upon repeat dosing in non-human primates: We have observed decreased immune activation which enables repeat dosing in non-human primates. Published data indicates serum concentration of human erythropoietin (hEPO) with repeat dosing of mRNA encoding hEPO in our proprietary LNPs with weekly IV administration at 0.2 mg/kg in non-human primates.
Pharmacologic activity in the target tissue and cell: While some of our modalities, such as systemic secreted therapeutics, can leverage many different cell types to make therapeutic proteins, others such as systemic intracellular therapeutics, may require delivery of our mRNA into specific tissues and cell types, for instance hepatocytes in certain liver metabolic diseases. Combining our proprietary mRNA, delivery, and manufacturing process technologies we have observed on-target pharmacologic activity in hepatocytes in non-human primates. The on-target potency of this approach contrasts with traditional delivery technologies. In published data, we have shown one of our proprietary LNPs with increased hepatocyte transfecting properties result in protein expression in liver hepatocytes in non-human primates (demonstrated with a reporter protein detected by immunohistochemistry at 6 hours after IV infusion at 2 mg/kg). Additionally, this LNP results in extended expression of a secreted reporter protein in non-human primates as compared to one of our other proprietary LNPs after IV delivery at 0.1mg/kg.
Our platform’s future: Improving and expanding our modalities
We are committed to sustaining investment in our platform, both in basic science to elucidate new mechanistic insights, and in applied science to discover new technologies that harness these insights. Our platform investments have enabled seven modalities to date, most of which have already led to multiple development candidates and investigational medicines in our pipeline. We believe that sustaining our investment in platform research and development will enable further improvements in the current modalities and will lead to the creation of new modalities, both of which will benefit our clinical pipeline in the years ahead.
Table of Content
OUR MODALITIES
Our approach to developing modalities
Within our platform, we develop technologies that enable the development of mRNA medicines for diverse applications. When we identify technologies that we believe could enable a new group of potential mRNA medicines with shared product features, we call that group a “modality.” While the programs within a modality may target diverse diseases, they share similar mRNA technologies, delivery technologies, and manufacturing processes to achieve shared product features. The programs within a modality will also generally share similar pharmacology profiles, including the desired dose response, the expected dosing regimen, the target tissue for protein expression, safety and tolerability goals, as well as pharmaceutical properties.
Illustrating our approach: From our first modality to today
We started with prophylactic vaccines as our first modality because we believed this modality faced lower technical hurdles, relative to other areas. Our early formulations of mRNA tended to stimulate the immune system, which would present a challenge to therapeutics but was a desired feature for vaccines. In addition, many potential prophylactic vaccine antigens are well-characterized, allowing us to reduce biology risk. Lastly, the dosing regimens for vaccines require as few as one or two administrations, and generally involve relatively low doses.
For our first programs in this modality we chose our H10N8 and H7N9 pandemic influenza vaccines, each requiring expression of a single membrane protein. We chose to pursue two programs in separate, but parallel, clinical trials to establish the flexibility of our platform. When both programs met our goals for safety, tolerability, and pharmacology, we accelerated and expanded our vaccine pipeline to include multiple commercially meaningful and increasingly complex vaccines.
These included a combination vaccine, designed to protect against two unrelated respiratory viruses, human metapneumovirus (hMPV) and human parainfluenza 3 (PIV3), and a vaccine that combines six different mRNAs, our CMV vaccine, to express a complex pentameric antigen. We also sought strategic alliances with the Defense Advanced Research Projects Agency (DARPA), the Biomedical Advanced Research Development Authority (BARDA) and Merck & Co. (Merck), to allow us to rapidly expand our pipeline and complement our capabilities with their expertise. This early work in the prophylactic vaccines modality led to the ability to introduce our COVID-19 vaccine during 2020 in response to the ongoing pandemic.
Over time, we have taken on more challenging applications and technological hurdles with each successive modality, but we have also tried to build upon our prior experiences to manage risk. For example, in our cancer vaccines modality, we are now applying our technology to elicit T cell responses to potentially recognize and eradicate cancer as a logical extension of our prophylactic vaccines modality. Having demonstrated local expression of protein in our vaccines, we expanded into local therapeutic applications. For example, in our intra-tumoral immuno-oncology modality, we are seeking to use local expression to drive anti-cancer T cell responses by transforming tumor microenvironments. We can also use local expression to drive regenerative processes as in our Vascular Endothelial Growth Factor A (VEGF-A) program. We expanded into two new modalities that use systemic delivery of mRNA to encode secreted and cell surface or intracellular proteins. Most recently, following a breakthrough in pulmonary delivery stemming from our partnership with Vertex Pharmaceuticals (Vertex), we expanded into the inhaled pulmonary therapeutics modality with our cystic fibrosis (CF) program.
Expanding within our designated core modalities
In 2020, we designated the prophylactic vaccines and systemic secreted and cell surface therapeutics modalities as “core modalities” following positive Phase 1 data from our CMV vaccine and chikungunya antibody program, respectively. We believed that this data reduced the risk of these modalities, and our strategy is to invest in additional development candidates within these modalities.
We believe our portfolio of modalities—each with distinct technological and biological risk profiles—allows us to maximize long-term value for patients and investors. We see our seven current modalities as seven distinct product pipelines that represent different risk profiles and benefit from common infrastructure and a shared platform technology. We believe the high technology correlation within a modality allows us to rapidly accelerate the expansion of the pipeline in that modality based on learnings from the initial programs. We believe the lower technology correlation between modalities allows us to compartmentalize the technology risks. We believe our ongoing investments in our platform will lead to the identification of additional new modalities in the future, and will expand the diversity of our pipeline.
Table of Content
Modality descriptions
We currently have seven modalities, described in more detail below:
- Prophylactic vaccines**: The goal of any vaccine is to safely pre-expose the immune system to a small quantity of a protein from a pathogen, called an antigen, so that the immune system is prepared to fight the pathogen if exposed in the future, and prevent infection or disease.
We believe mRNA vaccines have several advantages: (1) ability to mimic many aspects of natural viral infections, (2) multiplexing of mRNA for more compelling product profiles, (3) rapid discovery and advancement of mRNA programs into the clinic, and (4) capital efficiency and speed from shared manufacturing processes and infrastructure.
- Cancer vaccines:** The goal of a cancer vaccine is to safely expose the patient’s immune system to tumor related antigens, known as neoantigens, to enable the immune system to elicit a more effective antitumor response. Our cancer vaccines modality is focused on the use of mRNA to express neoantigens found in a particular tumor in order to elicit an immune response via T cells that recognize those neoantigens, and therefore the tumor. These neoantigens can either be unique to a patient or can be related to a driver oncogene found across subsets of patients. Recent breakthroughs in cancer immunotherapy, such as checkpoint inhibitors and chimeric antigen receptor T cell therapies, have demonstrated that powerful antitumor responses can be achieved by activating antigen specific T cells. We believe one approach to improve the efficacy of checkpoint inhibitors is to develop vaccines that increase both the number and antitumor activity of a patient’s T cells that recognize tumor neoantigens.
We believe that mRNA technology is an attractive approach for cancer vaccines: (1) mRNA vaccines can deliver multiple neoantigens concatenated in a single mRNA molecule, (2) mRNA encoding for neoantigens is translated and processed by patients’ endogenous cellular mechanisms for presentation to the immune system, and (3) mRNA vaccines can be efficiently personalized.
- Intratumoral immuno-oncology:** The goal of this modality is to treat or cure cancer by transforming the tumor microenvironment to drive anti-cancer T cell responses against tumors. The outlook for any patients with advanced cancer remains poor, especially in tumors that have little immune system engagement (sometimes termed immunologically “cold”). In conjunction with a checkpoint inhibitor, we aim to activate the immune system against these otherwise immunologically cold tumors. Intratumoral administration allows for localized effect of these therapeutics that could be toxic if administered systemically.
We believe our approach to immuno-oncology using mRNA medicines could complement checkpoint inhibitors and has several advantages over recombinant protein-based drugs: (1) mRNA focuses and limits exposure of immune stimulatory proteins, (2) mRNA can produce membrane associated immune stimulatory proteins, (3) multiplexing of mRNA allows access to multiple immune stimulatory pathways, (4) mRNA sequences can be engineered to reduce off-target effects, and (5) local administration of mRNA can create a concentration gradient for encoded proteins.
- Localized regenerative therapeutics:** The goal of this modality is to develop mRNA medicines to address injured or diseased tissues by locally producing proteins that provide a therapeutic benefit in the targeted tissue. There are multiple applications for tissue regeneration and our initial focus is on cardiovascular diseases.
We believe our approach to localized regenerative therapeutics using mRNA has several advantages over alternative approaches: (1) mRNA can be administered locally to produce the desired protein for an extended duration, (2) local administration of mRNA allows for focused activity, and (3) mRNA allows for dose-dependent and repeated production of the encoded protein.
- Systemic secreted and cell surface therapeutics:** The goal of this modality is to provide secreted proteins, such as antibodies or enzyme replacement therapies across a wide range of diseases, such as heart failure, infectious diseases, and rare genetic diseases. Our mRNA medicines instruct various cells of the human body to secrete proteins for therapeutic effect. Systemically delivered, secreted and cell surface therapeutics, we believe, would allow us to target areas of biology that cannot be addressed using recombinant proteins.
Our potential advantages in this area include: (1) mRNA can produce hard-to-make or complex secreted proteins, (2) mRNA can produce membrane associated proteins, (3) native post-translational modifications are possible through intracellular protein production using mRNA, (4) mRNA can sustain production of proteins, which can increase exposure to proteins with short half-lives, and (5) mRNA allows for desirable pharmacology in rare genetic diseases currently addressed by enzyme replacement therapies.
Table of Content
- Systemic intracellular therapeutics:** The goal of this modality is to provide intracellular proteins, such as intracellular enzymes and organelle-specific proteins, as safe, tolerable, and efficacious therapies. Our mRNA medicines aim to increase levels of intracellular proteins to achieve a therapeutic effect in one or more tissues or cell types and our initial focus is on rare genetic diseases. Intracellular therapeutics are not currently addressable with recombinant proteins, which are typically administered systematically and cannot reach inside of the cell.
Our potential advantages in these areas include: (1) using mRNA to encode for intracellular and organelle-specific proteins; mRNA can produce hard-to-make or complex proteins, (2) native post-translational modifications are possible through intracellular protein production using mRNA, (3) mRNA can sustain production of proteins, which can increase exposure to proteins with short half-lives, and (4) mRNA allows for desirable pharmacology in complex metabolic diseases.
- Inhaled pulmonary therapeutics:** The goal of this modality is to develop mRNA medicines that can be delivered to the lung as safe, tolerable and efficacious therapies. We are developing nebulized NLP formulations that can transfect airway epithelial cells to deliver mRNA into the lungs of patients in order to express proteins coded in the mRNA. We aim to leverage our technology for pulmonary diseases in patients for whom there are no existing effective therapies.
Our potential advantages in these areas include: (1) mRNA can produce hard-to-make or complex proteins, (2) mRNA can replace defective genes, and (3) LNP delivery allows for repeat dosing.
OUR PIPELINE
Since we nominated our first program in late 2014, we and our strategic collaborators have advanced in parallel a diverse development pipeline which currently consists of 44 development program across our 41 development candidates, with 25 having entered the clinic and one development candidate subject to an open investigational new drug application (IND). In the third quarter of 2021, we refined the way we track our development programs and now separately track each indication of our COVID-19 and RSV vaccine candidates, which resulted in an increase in the number of our development programs. We have entered seven other development candidates into the clinic that are no longer being pursued for further clinical development. Aspects of our pipeline have been supported through strategic alliances, including with AstraZeneca, Merck, and Vertex, and government-sponsored organizations and private foundations focused on global health initiatives, including BARDA, DARPA, the National Institutes of Health (NIH), and the Bill & Melinda Gates Foundation.
Our selection process for advancing new development candidates reflects both program-specific considerations as well as portfolio-wide considerations. Program-specific criteria include, among other relevant factors, the severity of the unmet medical need, the biology risk of our chosen target or disease, the feasibility of clinical development, the costs of development, and the commercial opportunity. Portfolio-wide considerations include the ability to demonstrate technical success for our platform components within a modality, thereby increasing the probability of success and learnings for subsequent programs in the modality and in some cases in other modalities.
The breadth of biology addressable using mRNA technology is reflected in our current development pipeline of 44 programs. The diversity of proteins made from mRNA within our development pipeline is shown in the figure below.
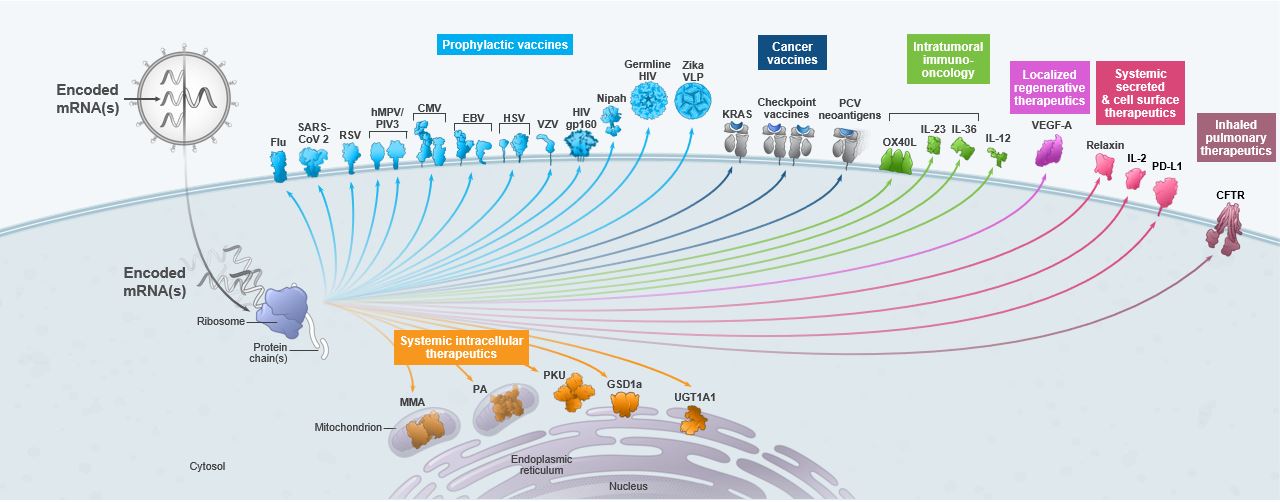
Table of Content
Our full pipeline, grouped by modalities, is shown in the figure below:
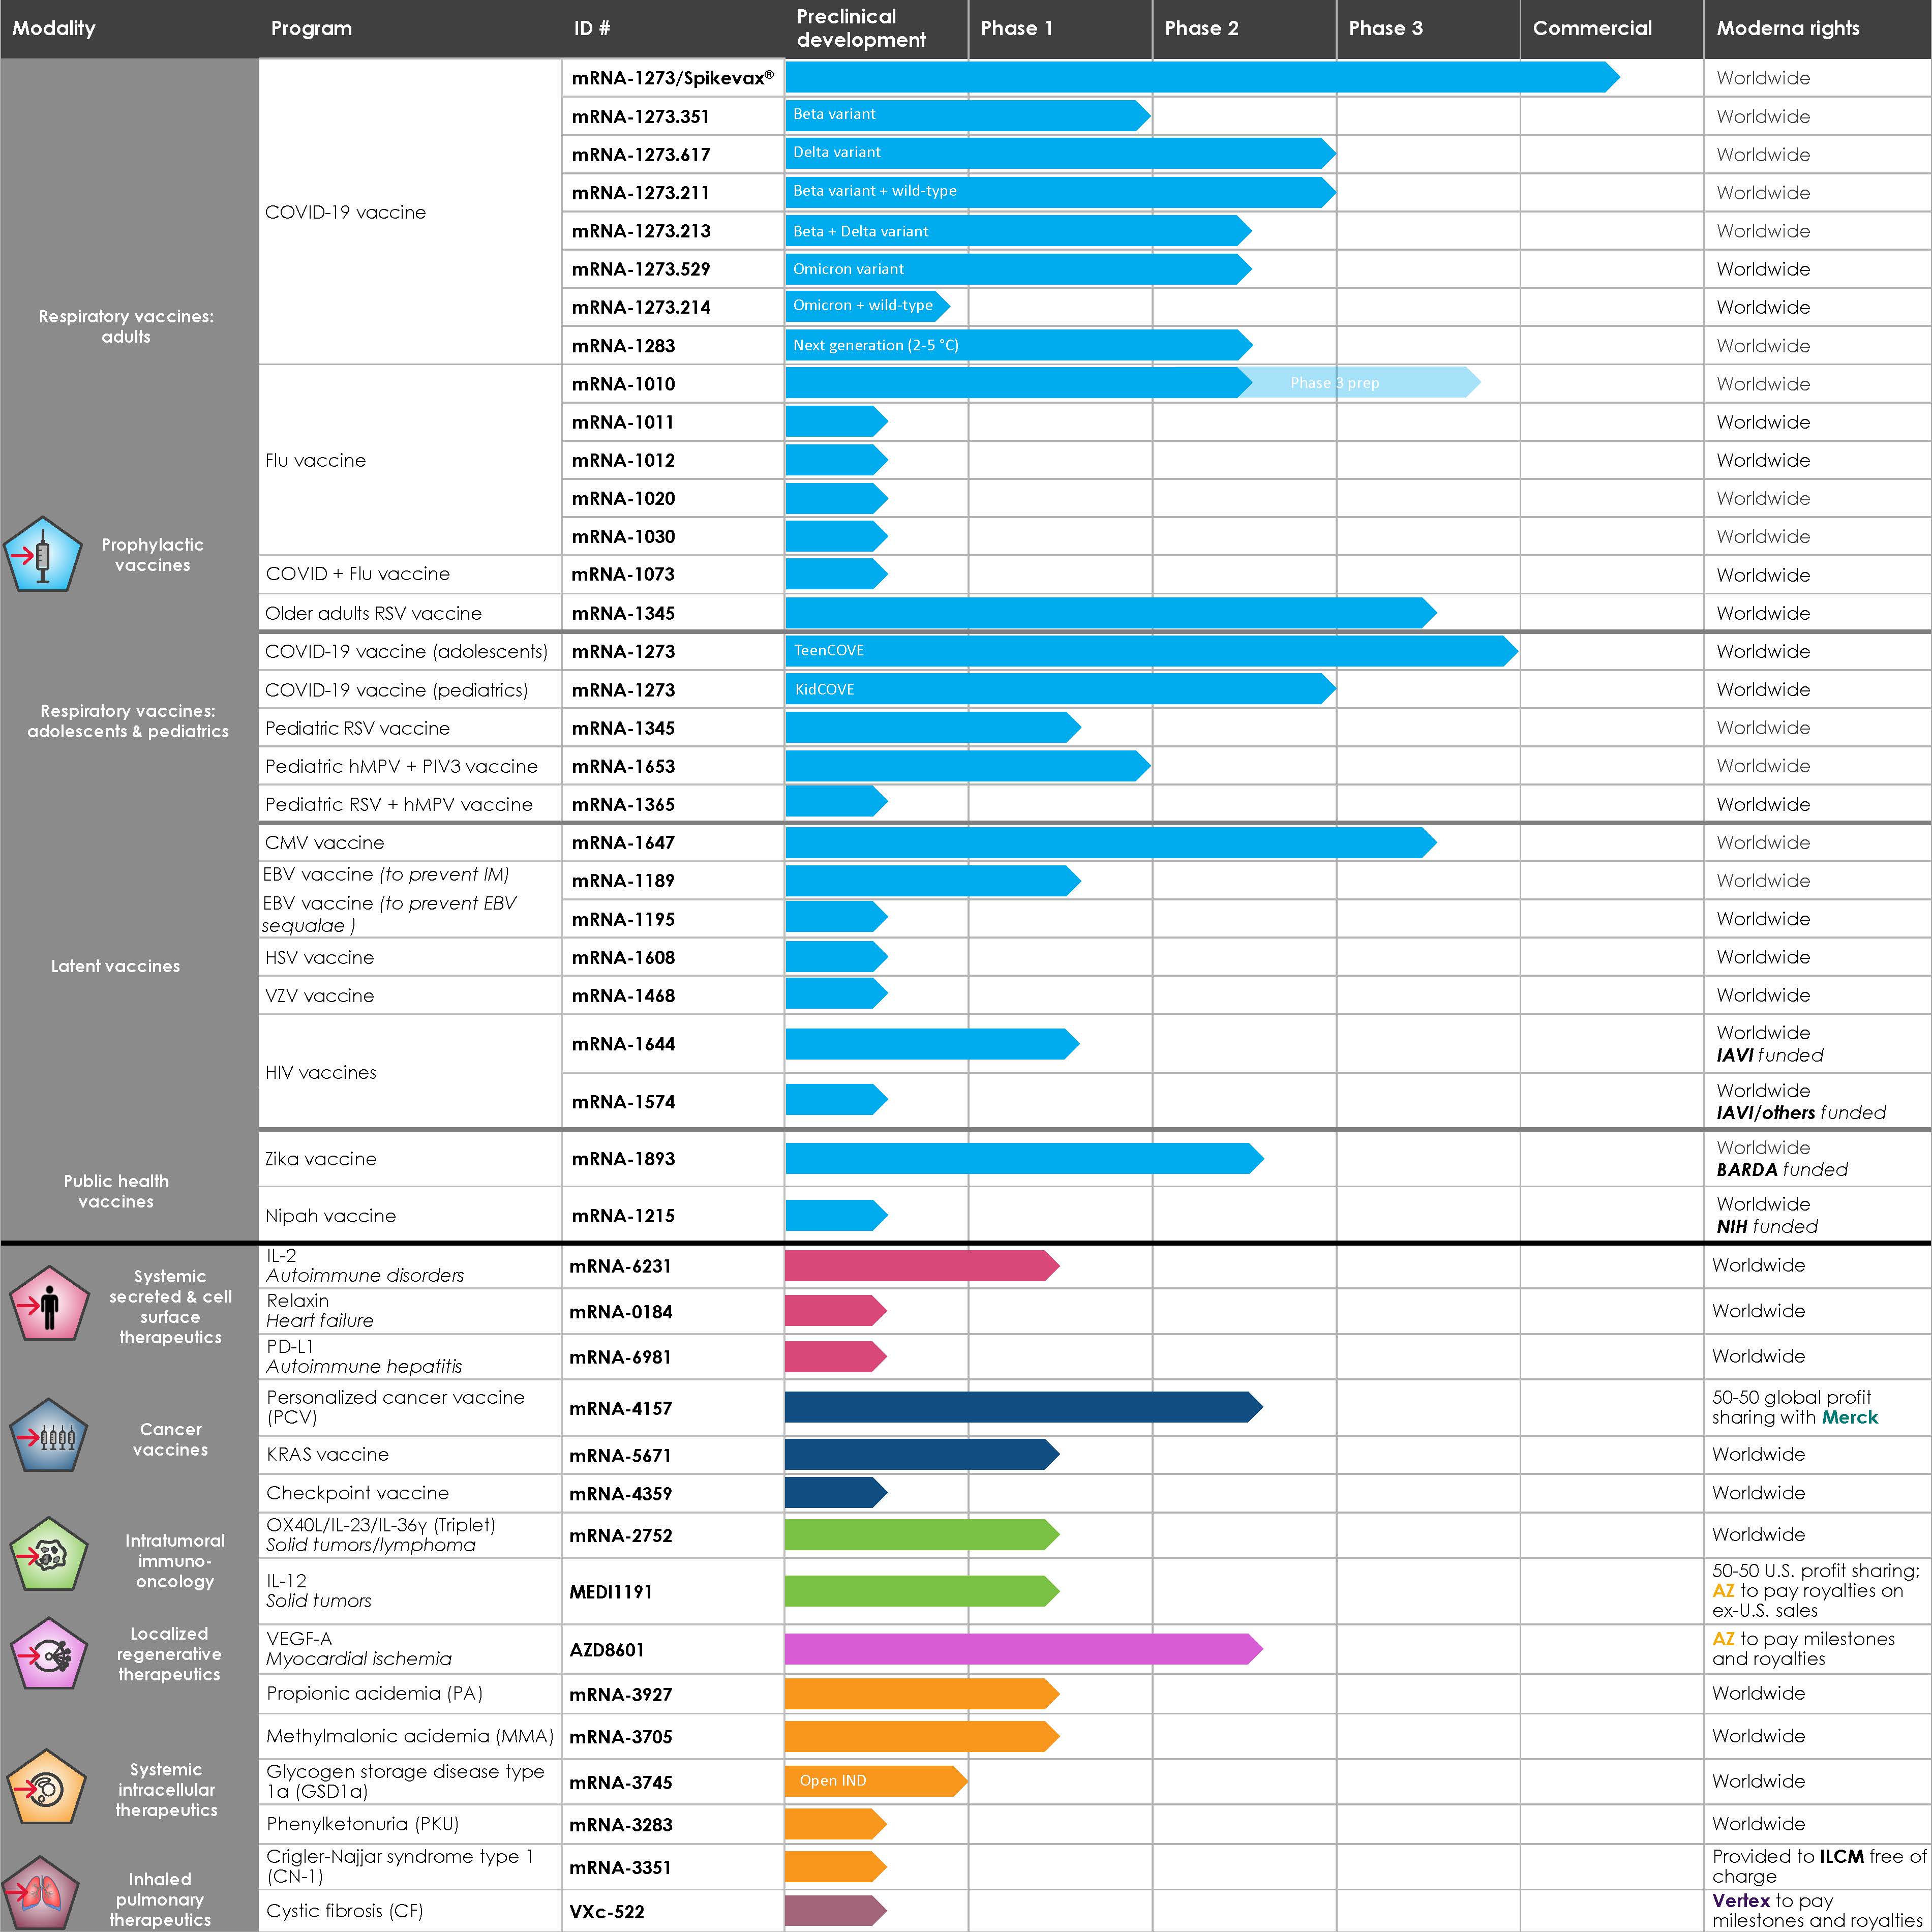
Table of Content
PROPHYLACTIC VACCINES MODALITY
We have 29 different prophylactic vaccine programs, of which 17 have entered the clinic. We separate our prophylactic vaccines modality into three categories: (1) vaccines against respiratory viruses, (2) vaccines against latent viruses, and (3) other vaccines (such as public health programs).
Prophylactic vaccines: Vaccines against respiratory viruses
COVID-19 vaccine (mRNA-1273)
Moderna’s COVID-19 Vaccine/Spikevax is approved or authorized for use in more than 70 countries
The Moderna COVID-19 Vaccine, which is also marketed under the brand name Spikevax, is our first commercial product. From the beginning of the COVID-19 pandemic through December 31, 2021, we delivered approximately 824 million doses of our vaccine globally, with approximately 807 million of those doses shipped in 2021.
Coronaviruses are a large family of viruses that can cause illness in animals or humans. In humans there are several known coronaviruses that cause respiratory infections. These coronaviruses range from the common cold to more severe diseases such as severe acute respiratory syndrome (SARS), Middle East respiratory syndrome (MERS), and COVID-19. SARS-CoV-2 is the novel coronavirus first identified in humans in December 2019 and is the cause of COVID-19. COVID-19 is the most severe global pandemic since the influenza pandemic of 1918. According to the Johns Hopkins Coronavirus Resource Center, since the identification of SARS-CoV-2 in 2020, there have been over 430 million confirmed cases and over 5.9 million global deaths from COVID-19. The risk of mortality increases with age and the risk of severe disease and mortality increase for persons with pre-existing diseases or comorbid conditions (e.g. cardiovascular disease, diabetes, chronic lung disease, obesity).
Our vaccine against COVID-19, mRNA-1273, was designed, subject to Phase 1, Phase 2 and Phase 3 clinical trials, delivered clinical trial results, and received emergency use and other conditional authorizations in less than a year, and has been and continues to be a key tool in fighting the global COVID-19 pandemic. The SARS-CoV-2 virus continues to evolve, and certain variants of the virus have proven to be more transmissible and to cause more severe cases of COVID-19 than the ancestral strain that first emerged in Wuhan, China. As part of our strategy to combat the COVID-19 pandemic, we have continued to develop and assess variant-specific versions of our COVID-19 vaccine, including versions aimed at targeting the Beta, Delta and Omicron variants of the virus. Forward-looking references to our COVID-19 vaccine in this Annual Report on Form 10-K may include future modifications to mRNA-1273 or other development candidates that are designed to provide protection against variants of the SARS-CoV-2 virus.
We continue to study the use of our COVID-19 vaccine (mRNA-1273) in adolescent and pediatric populations, and for boosting and other indications. In addition to our original COVID-19 vaccine, we have advanced multiple other variant-specific vaccines into the clinic as part of effort to fight the global COVID-19 pandemic. As of the date of this Annual Report on Form 10-K, these programs include:
Spikevax/mRNA-1273 Programs
- Moderna COVID-19 vaccine/Spikevax: Approved/authorized in individuals 18 years and older in more than 70 countries (100 µg dose).
◦In January 2022, the U.S. FDA approved the Biologics License Application (BLA) for Spikevax (COVID-19 Vaccine, mRNA) to prevent COVID-19 in individuals 18 years of age and older.
- Adolescent COVID-19 vaccine/Spikevax: Authorized in individuals 12-17 years in the European Union, UK, Australia, Canada, Switzerland and other countries (100 µg dose); authorization by the U.S. FDA is pending.
◦The U.S. FDA notified us that it will require additional time to complete its assessment of our EUA request for the use of mRNA-1273 at the 100 µg dose level in adolescents 12 to 17 years of age. In early December 2021, we also decided to evaluate the potential of a lower 50 µg dose for primary vaccination.
- Pediatric COVID-19 vaccine/Spikevax: In clinical trials in children from 6 months to 11 years old; authorized in individuals 6-11 years in Australia, and subject to a positive recommendation from the European Medicines Agency’s Committee for Medicinal Products for Human Use in individuals from 6-11 years (50 µg dose).
◦The Phase 2 study of mRNA-1273 in pediatric populations is ongoing. We selected the 50 µg dose for expanded enrollment in the 6 to 11 years old cohort, which is now fully enrolled (N=4,000). Dose selection studies are underway for 2 years to 5 years old and 6 months to <2 years old groups. In early December 2021, we also decided to evaluate the potential of a lower dose of 25 µg to meet regulatory guidance for immunogenicity in children 6-11 years of age. We expect to report data in children 2-5 years of age in March 2022.
- Booster dose of COVID-19 vaccine/Spikevax: Authorized in individuals 18 years and older in the United States, the European Union, Switzerland and other countries (50 µg dose).
◦For immunocompromised individuals, a booster dose of 100 µg is authorized.
Table of Content
Other COVID-19 Vaccine Programs
- Next-generation COVID-19 vaccine (mRNA-1283) is in an ongoing Phase 2 trial.
◦mRNA-1283 is a next-generation COVID-19 vaccine candidate that encodes for the portions of the SARS-CoV-2 spike protein critical for neutralization, specifically the Receptor Binding Domain (RBD) and Nterminal Domain (NTD). The encoded mRNA-1283 antigen is shorter than mRNA-1273 and is being developed as a potential refrigerator-stable mRNA vaccine that will facilitate easier distribution and administration by healthcare providers.
- Variant-specific or multi-valent COVID-19 vaccines: As SARS-CoV-2 has continued to evolve, we have proactively made new mRNA candidates in the case they are needed for an escape variant. In the event that mRNA-1273 proves ineffective at protecting against these variants, we have developed the variant vaccines listed below, which may be utilized to the extent necessary as the virus continues to evolve:
◦mRNA-1273.351: Vaccine against the Beta variant. Phase 2 clinical trial ongoing.
◦mRNA-1273.617: Vaccine against the Delta variant. Phase 2 clinical trial ongoing.
◦mRNA-1273.529: Vaccine against the Omicron variant. Phase 2 clinical trial ongoing.
◦mRNA-1273.211: Vaccine against the Beta variant and wild-type. Phase 2 clinical trial ongoing.
◦mRNA-1273.213: Vaccine against the Beta variant and Delta variant. Phase 2 clinical trial ongoing.
◦mRNA-1273.214: Vaccine against the Omicron variant and wild-type.
Moderna COVID-19 Vaccine Clinical Trials
The final analysis of adjudicated cases from the Phase 3 clinical trial for mRNA-1273, which we refer to as the COVE Study, demonstrated efficacy of 93% through six months after the second dose of the vaccine. The final analysis also demonstrated greater than 98% efficacy against severe cases of COVID-19 and 100% efficacy against death caused by COVID-19 in the per protocol cohort. The final analysis also demonstrated consistency in our subgroup analysis, including analyses by gender, by race and by preexisting medical conditions. The safety profile for mRNA-1273 continues to be consistent with the Phase 3 data over the longer period of safety follow up and across population subgroups.
Variant-specific and multivalent vaccines and Omicron update
We are continuously advancing booster candidates to address emerging variants of concern (VOCs). The strategy involves evaluating the prototype vaccine (mRNA-1273) at the authorized booster dose (50 µg), an Omicron-specific booster candidate (mRNA-1273.529), and a bivalent booster candidate (mRNA-1273.214) combining mRNA-1273.529 and mRNA-1273. Booster candidates are being evaluated in ongoing Phase 2/3 studies of approximately 300-600 participants per arm. In December 2021, we announced that at day 29 post-boost, the authorized 50 µg booster of mRNA-1273 increased neutralizing geometric mean titers (GMT) against Omicron approximately 37-fold higher than pre-boost levels. At day 29 post-boost, the 100 µg dose booster of mRNA-1273 increased neutralizing GMTs approximately 83-fold higher than pre-boost levels. Multivalent candidates (mRNA-1273.211 and mRNA-1273.213) boosted Omicron specific neutralizing antibody levels to similarly high levels at both the 50 µg and 100 µg levels. Based on the strength of neutralizing titers generated by mRNA-1273, the rapid pace of Omicron expansion, and the increased complexity of deploying a new vaccine, we are focusing our near-term efforts to address Omicron on the mRNA-1273 booster.
However, given the long-term threat demonstrated by Omicron’s immune escape, we are also developing an Omicron containing variant vaccine (mRNA-1273.529) and a bivalent vaccine that is tailored to Omicron and the wild-type virus (mRNA-1273.214). The first participant was dosed in the mRNA-1273.529 trial in January 2022 and this trial is ongoing.
COVID-19 Commercial, Manufacturing and Supply Updates
Commercial sales of our COVID-19 vaccine accounted for $17.7 billion in revenues for the year ended December 31, 2021, based upon the delivery of approximately 807 million doses of the vaccine, accounting for all of our commercial revenues. We anticipate that sales of our COVID-19 vaccine in 2022 will similarly provide all of our commercial revenues for the coming year. These sales, both for 2021 and 2022, have been and will primarily be made to governments and international organizations engaged in the purchase of vaccines to combat the COVID-19 pandemic. We are preparing for the fall 2022 booster season and, if marketing approval is received for boosters of our COVID-19 vaccine, we expect to initiate sales in the U.S. private market. As the COVID-19 pandemic evolves into an endemic phase, we anticipate greater seasonality for sales, with greater demand in the fall/winter season in each hemisphere as countries seek to boost their populations. For further information on the sales and manufacturing of our COVID-19 vaccine, see “Manufacturing” and “Management’s Discussion and Analysis of Financial Condition and Results of Operations” below.
Seasonal influenza vaccine (mRNA-1010, mRNA-1011, mRNA-1012, mRNA-1020 and mRNA-1030)
We are developing five influenza vaccines. mRNA-1010 has reported positive Phase 1 data and is ongoing in a Phase 2 study and a Phase 3 study is planned to start soon.
Table of Content
Seasonal influenza viruses are estimated by the World Health Organization (WHO) to cause 3 to 5 million cases of severe illness and up to 650,000 deaths each year, resulting in a severe challenge to public health. Currently licensed seasonal influenza virus vaccines rarely exceed 60% overall effectiveness and can provide low effectiveness during years when the circulating viruses do not match the strains selected for the vaccine antigens. Our mRNA seasonal influenza vaccine program has three different approaches. Our first approach – Quadrivalent Vaccine – is developing a quadrivalent seasonal flu vaccine (mRNA-1010) targeting WHO recommendations, including A H1N1, H3N2 and influenza B Yamagata and Victoria lineages. Our second approach – Expanded Coverage – is to provide an enhanced antigen selection opportunity to public health authorities with the potential for regional variation. Our third approach – Immunologic Breadth – is to provide immunity by targeting more conserved antigens to provide the broadest coverage. We also aim to work with the WHO and other regulators to make vaccines closer to the flu season and potentially choose strains closer to the ones circulating in the hemisphere.
mRNA-1010 is a single investigational vaccine consisting of four distinct mRNA sequences that encode the A H1N1, H3N2 and influenza B Yamagata and Victoria lineages in our proprietary LNP. mRNA-1011 and mRNA-1012 are investigational vaccines that will include the four WHO recommended strains and aim to add additional Hemagglutinin (HA) antigens (e.g. H3N2, H1N1). mRNA-1020 and mRNA-1030 are investigational vaccines that will aim to add Neuraminidase (NA) antigens.
Latest data and next steps
mRNA-1010 is ongoing in a Phase 2 study and a Phase 3 efficacy study is planned to start in 2022. In December 2021, we announced positive Phase 1 data, and that mRNA-1010 successfully boosted hemagglutination inhibition (HAI) assay geometric mean titers against all strains 29 days after vaccination at all doses tested in both younger and older adults. In the Phase 1 study, mRNA-1010 was evaluated at 50 µg, 100 µg and 200 µg dose levels in younger adult (age 18-49) and older adult (age 50+) cohorts. No significant safety findings were observed through day 29. Adverse reactions (ARs) were generally reported more frequently in younger adults compared to older adults, and at higher dose levels. Minimal differences in dose response was observed between the 50 µg, 100 µg and 200 µg dose levels, suggesting the potential to explore even lower doses.
Our expanded coverage influenza vaccines (mRNA-1011 & mRNA-1012) and immunologic breadth influenza vaccines (mRNA-1020 & mRNA-1030) are in preclinical studies.
RSV vaccine (mRNA-1345)
We are developing an RSV vaccine for children and older adults. In older adults, mRNA-1345 is ongoing in a pivotal Phase 3 study; in pediatrics, mRNA-1345 is ongoing in a Phase 1 study.
Respiratory syncytial virus (RSV) is one of the most common causes of respiratory disease in children under the age of five and also in older adults. Most children are infected at least once by two years of age. In the United States, it is estimated that over two million children younger than five years of age receive medical attention and more than 86,000 are hospitalized due to RSV infection annually. RSV also causes a substantial burden of respiratory illness in older adults. RSV infection causes an estimated 177,00 hospitalizations and 14,000 deaths per year in adults aged >65 years in the United States.
mRNA-1345 encodes an engineered form of the RSV F protein stabilized in the prefusion conformation and is formulated in our proprietary LNP. We believe that neutralizing antibodies elicited by mRNA-1345 may lead to an efficacious RSV vaccine.
Latest data and next steps
The Phase 1 study of mRNA-1345 to evaluate the tolerability, reactogenicity and immunogenicity of mRNA-1345 in younger adults, older adults, older adults of Japanese descent, women of child-bearing age and children with serologic evidence of prior RSV exposure is ongoing. The age range of children in this de-escalation Phase 1 study is 12-59 months. Enrollment in the pediatric and older adult Japanese descent cohorts are ongoing, whereas the other cohorts are fully enrolled. Phase 1 interim data from the older adult cohort showed that a single mRNA-1345 vaccination at 50 µg, 100 µg or 200 µg boosted neutralizing antibody titers against RSV-A by approximately 14-fold and against RSV-B by approximately 10-fold.
The Phase 3 portion of the pivotal global Phase 2/3 study of mRNA-1345 with approximately 34,000 participants and testing the 50 µg is currently enrolling. The FDA has granted Fast Track designation for mRNA-1345 in adults older than 60 years of age.
hMPV/PIV3 vaccine (mRNA-1653)
We are developing a combination vaccine to address two viruses that are leading causes of respiratory infection
Table of Content
Human metapneumovirus (hMPV) and human parainfluenza virus 3 (PIV3) are significant causes of respiratory tract infections in children. hMPV has been detected in 4% to 15% of patients with acute respiratory infections. hMPV causes disease primarily in young children but can also infect adults, the elderly, and immunocompromised individuals. Infections from parainfluenza virus (PIV) account for up to 7% of acute respiratory infections among children younger than 5 years. Of the four PIV types identified, PIV3 most frequently results in infections and leads to the more serious lower respiratory tract infections compared to the other three PIV types.
mRNA-1653 is a single investigational vaccine consisting of two distinct mRNA sequences that encode the membrane F proteins of hMPV and PIV3, co-formulated in our proprietary LNP.
Latest data and next steps
A first-in-human dose-ranging study, mRNA-1653-P101, in healthy adults (N=124) was completed in January 2020. This study evaluated the safety, reactogenicity, and immunogenicity of a range of dose levels (25, 75, 150 or 300 µg) administered on a 1-dose or 2-dose vaccination schedule (approximately 28 days apart) compared with a placebo control in healthy adult subjects (18 through 49 years of age) with a 13 month follow-up period. The mRNA-1653 vaccine was generally well-tolerated at all dose levels. A single dose of mRNA-1653 boosted serum neutralization titers against hMPV and PIV3, and the magnitude of the boost was similar at all dose levels. The Month 1 to baseline geometric mean ratio (GMR) for the pooled mRNA-1653 treatment groups was approximately 6 for hMPV and 3 for PIV3. A second vaccination did not impact the magnitude of hMPV or PIV3 neutralization titers measured at Month 2. The hMPV neutralizing antibody titers remained above baseline at all dose levels through Month 13, and the PIV3 neutralizing antibody titers remained above baseline at all dose levels through Month 7.
We are conducting a Phase 1b trial to evaluate mRNA-1653 in healthy adults and children aged 12-59 months. The Phase 1b trial is a randomized, observer-blinded, placebo-controlled, dose-ranging trial to evaluate the safety and immunogenicity of two dose levels of mRNA-1653 in healthy adults (18-49 years of age) and two dose levels in children (12-59 months of age) with serologic evidence of prior hMPV and PIV3 exposure. The study is fully enrolled.
Combination vaccines (mRNA-1073 & mRNA-1365)
Our vision is to develop a pan-respiratory annual booster vaccine (mRNA-1073) and a pediatric combination vaccine (mRNA-1365)
In September 2021, we announced two development candidates that build upon our combination strategy. mRNA-1073 is our COVID-19 and seasonal flu combination vaccine. mRNA-1073 encodes for the COVID-19 spike protein and the flu HA glycoproteins. mRNA-1365 is our pediatric RSV and hMPV combination vaccine. mRNA-1365 encodes for the RSV prefusion F glycoprotein and the hMPV F protein.
Prophylactic vaccines: Vaccines against latent viruses
CMV vaccine (mRNA-1647)
Our CMV program targets prevention of CMV infections, which could reduce the risk of birth defects
Human CMV is a common human pathogen and member of the herpes virus family. Congenital CMV results from infected mothers transmitting the virus to their unborn child and it is the leading infectious cause of birth defects in the United States, with approximately 25,000 newborns in the U.S. infected annually. There is currently no available vaccine for CMV and a vaccine that leads to durable immunity in women of child-bearing age would address a critical unmet need in the prevention of congenital CMV infection.
Our CMV vaccine, mRNA-1647, combines six mRNAs in one vaccine, which encode for two proteins located on the surface of CMV: five mRNAs encoding the subunits that form the membrane-bound pentamer complex and one mRNA encoding the full-length membrane-bound glycoprotein B (gB). Both the pentamer and gB are essential for CMV to infect barrier epithelial surfaces and gain access to the body, which is the first step in CMV infection. mRNA-1647 is designed to produce an immune response against both the pentamer and gB for the prevention of CMV infection.
Latest data and next steps
Phase 1 and 2 studies of mRNA-1647 demonstrated functional antigen-specific responses that support the vaccine candidate’s potential to prevent CMV infection. Interim, seven-month data from the Phase 2 study of mRNA-1647 at the 50 μg, 100 μg and 150 μg dose levels showed that mRNA-1647 was generally well tolerated. In CMV-seronegative participants in mRNA-1647 treatment groups after the third vaccination, neutralizing antibody GMTs against epithelial cell infection were at least 20-fold higher than the baseline GMT of the CMV seropositive group, and neutralizing antibody GMTs against fibroblast infection approximated the baseline
Table of Content
GMT of the CMV-seropositive group. In CMV positive participants in mRNA-1647 treatment groups after the third vaccination, neutralizing antibody GMTs against epithelial cell infection increased to at least 6.8-fold over baseline, and neutralizing antibody GMTs against fibroblast infection increased to approximately 2-fold over baseline.
Based on the interim analysis of the Phase 2 study, the 100 μg dose was chosen for the Phase 3 study. The first participant in the Phase 3 study, known as CMVictory, was dosed in October 2021. The study is evaluating the safety and efficacy of mRNA-1647 against primary CMV infection in women ages 16-40 years and seeks to enroll 6,900 women of child-bearing age.
EBV vaccine (mRNA-1189 & mRNA-1195)
We are developing two EBV vaccines – a vaccine to prevent infectious mononucleosis and another vaccine to prevent the longer term sequelae of EBV infection
Epstein-Barr virus (EBV) a member of the herpesvirus family that includes CMV, infects approximately 90% of people by adulthood, with primary infection typically occurring during childhood or late adolescence (approximately 50% and 89% seropositivity, respectively) in the U.S. EBV is the major cause of infectious mononucleosis in the U.S., accounting for over 90% of the approximately 1-2 million cases of infectious mononucleosis in the U.S. each year. Infectious mononucleosis can debilitate patients for weeks to months and, in some cases, can lead to hospitalization and splenic rupture. EBV infection is associated with the development and progression of certain lymphoproliferative disorders, cancers, and autoimmune diseases. In particular, EBV infection and infectious mononucleosis are associated with increased risk of developing multiple sclerosis, an autoimmune disease of the central nervous system.
Similar to our CMV vaccine (mRNA-1647) product concept, we believe that an effective EBV vaccine must generate an immune response to antigens that are required for viral entry in most of the susceptible cell types. We have thus designed our EBV vaccine, mRNA-1189, to elicit an immune response to EBV envelope glycoproteins gp220 as well as gp42, and the gH/gL complex, which are required for infection of both epithelial and B cells. mRNA-1189 contains four mRNAs encoding for these proteins encapsulated in our proprietary LNPs. mRNA-1195 encodes for additional antigens and the first indication it will focus on is post-transplant lymphoproliferative diseases (80% of PTLD can be attributed to EBV).
Latest data and next steps
We are conducting a Phase 1, randomized, observer-blind, placebo-controlled study of mRNA-1189. The primary purpose of the Phase 1 study is to assess safety, tolerability and immunogenicity of mRNA-1189 in healthy adults ages 18 to 30. We announced the dosing of the first participant in January 2022 and we expect to enroll approximately 270 participants. Our EBV therapeutic vaccine, mRNA-1195, is in preclinical studies.
HSV vaccine (mRNA-1608)
We are developing a herpes simplex virus (HSV) vaccine candidate against HSV-2 disease
Herpes simplex viruses (commonly known as herpes) are categorized into two types: HSV-1 infects the mouth, face and genitals, and HSV-2 primarily infects the genitals. Both viruses establish life-long latent infections within nearby sensory neurons from which they can reactivate and re-infect the skin. There is a significant burden of disease from HSV genital infections. Diagnosed, symptomatic genital herpes causes a reduction in quality of life, which antivirals (current standard of care) only partially restore. In the United States, approximately 18.6 million adults ages 18 to 49 years are living with HSV-2. Globally, approximately 5% of the population in the 18-to-49-year age range is HSV-2 seropositive.
We believe that an HSV vaccine could deliver similar efficacy as suppressive antiviral treatments and could improve compliance and quality of life. We aim to induce a strong antibody response with neutralizing and effector functionality combined with cell-mediated immunity.
Latest data and next steps
Our HSV vaccine (mRNA-1608) is currently in preclinical studies. In a preclinical study in mice, we demonstrated robust neutralizing response induced by an mRNA vaccine containing HSV-2 antigens against both HSV-2 infection, and cross-neutralization against HSV-1 infection. In addition, the sera also demonstrated high antibody-dependent cellular cytotoxicity (ADCC) activity. The immune responses induced by the HSV-2 mRNA vaccine are higher than the average observed in 80 randomly selected seropositive human sera.
VZV vaccine (mRNA-1468)
We are developing a varicella-zoster virus (VZV) vaccine candidate to reduce the rate of herpes zoster (shingles)
Table of Content
Herpes zoster occurs in one of three adults in their lifetime and incidence dramatically increases at approximately 50 years of age. Declining immunity in older adults decreases cell-mediated immunity against VZV, allowing reactivation of the virus from latently infected neurons, causing painful and itchy lesions. Serious herpes zoster complications include postherpetic neuralgia (10-13% of herpes zoster cases), bacterial coinfections, and cranial and peripheral palsies; 1-4% of individuals with herpes zoster cases are hospitalized for complications. Severity of disease and likelihood of complications, including postherpetic neuralgia (PHN) also increases with age. Immunocompromised patients, autoimmune disease patients using immunosuppressive therapies, HIV-infected patients, hematopoietic stem cell (HSCT) and organ transplant recipients have an increased risk of developing herpes zoster. The incidence of herpes zoster has been increasing throughout the world, from 0.76 per 1,000 person years from 1945 to 1949, to 7.2 per 1,000 person years in 2016. The current standard of care is ShingrixTM, an FDA-approved vaccine for the prevention of shingles (herpes zoster) in adults 50 years and older. It is more than 90% effective against herpes zoster in adults aged 50-70 with only a slight reduction in efficacy for adults over age 70.
Our VZV vaccine (mRNA-1468) is designed to express VZV glycoprotein E (gE) to reduce the rate of herpes zoster.
Latest data and next steps
In partnership with Merck, we previously published preclinical data in Vaccine showing that an LNP formulated (Merck’s proprietary LNP) mRNA encoding VZV gE antigen is highly immunogenic in non-human primates. Our VZV vaccine (mRNA-1468) using our proprietary LNP is currently in preclinical studies.
HIV vaccine (mRNA-1644 & mRNA-1574)
We are developing two HIV vaccines – one approach is to test a novel HIV vaccine strategy in humans for eliciting broadly neutralizing HIV-1 antibodies (bnAbs) and the second approach is to test novel HIV trimer designs in humans.
HIV is the virus responsible for acquired immunodeficiency syndrome (AIDS), a lifelong, progressive illness with no effective cure. Approximately 38 million people worldwide are currently living with HIV, with 1.2 million in the U.S. Approximately 1.5 million new infections of HIV are acquired worldwide every year and approximately 680,000 people die annually due to complications from HIV/AIDS. The primary routes of transmission are sexual intercourse and IV drug use, putting young adults at the highest risk of infection. From 2000 to 2015, a total of $562.6 billion globally was spent on care, treatment and prevention of HIV, representing a significant economic burden.
In collaboration with the International AIDS Vaccine Initiative (IAVI) and the Bill & Melinda Gates Foundation, mRNA-1644 is testing a novel HIV vaccine strategy in humans as delivered by mRNA to elicit broadly neutralizing HIV-1 antibodies (bnAbs) through sequential vaccination of novel prime and boost antigens that induce specific B-cell responses. In collaboration with IAVI and the HIV Vaccine Trials Network, mRNA-1574 is testing multiple native-like HIV trimer mRNAs in humans to improve our understanding of how to make stable and immunogenic native-HIV trimers.
Latest data and next steps
mRNA-1644 is in an ongoing Phase 1 clinical trial and mRNA-1574 is in preclinical studies.
Prophylactic vaccines: Public health vaccines
Zika vaccine (mRNA-1893)
In partnership with BARDA, we are in a Phase 2 clinical trial for our Zika vaccine
The Zika virus is a single stranded RNA virus of the flaviviridae family. Seroepidemiology data suggest that it is endemic to regions of Africa and Asia where the Aedes mosquito vectors are found. Zika virus is predominantly spread by mosquitos from the Aedes genus, but it can also be transmitted congenitally, sexually, and through blood donation. Zika infection is usually asymptomatic or mild in adults, leading to fever, rash, and conjunctivitis. However, infection of women during pregnancy can result in devastating microcephaly in newborns. Microcephaly is a birth defect characterized by an abnormally small head and brain, associated with lifelong neurodevelopmental delay, seizures, intellectual disability, balance problems, and dwarfism / short stature, resulting in significant disability and requiring lifelong support. In 2007, a Zika infection outbreak progressed across the Pacific islands. An outbreak observed in Brazil in 2015 soon spread across the Americas. This led to the WHO declaring it a public health emergency of international concern in 2016. During the period, there were tens of thousands of cases of microcephaly and congenital Zika syndrome reported in infants and of resulting neurological sequelae such as Guillain-Barré syndrome reported in adults.
Our Zika vaccine, mRNA-1893, encodes for the prME structural protein encapsulated in our proprietary LNP.
Table of Content
Latest data and next steps
In 2020, we announced positive data from our Phase 1 clinical trial, which enrolled four cohorts (10, 30, 100 and 250 µg). mRNA-1893 was safe and well tolerated at the 10 and 30 µg dose level. In the flavivirus-seronegative group, seroconversion rates after the second vaccination reached 94.4% at the 10 µg dose level and 100% in the 30 µg dose level (PRNT50). In the flavivirus-seropositive group, the percentage of participants achieving a 4-fold boost in pre-existing PRNT50 titers after the second vaccination reached 50% in the 10 µg dose level and 75% in the 30 µg dose level (PRNT50). We are currently enrolling mRNA-1893 in a Phase 2 clinical study in the United States and Puerto Rico with approximately 800 participants. The randomized, placebo-controlled study aims to evaluate the safety, tolerability and reactogenicity of mRNA-1893 compared to placebo.
Nipah vaccine (mRNA-1215)
In collaboration with the NIH-VRC, we are preparing to start a Phase 1 study for our Nipah vaccine
Nipah virus (NiV) is a zoonotic virus transmitted to humans from animals, contaminated food, or through direct human-to-human transmission and causes a range of illnesses including fatal encephalitis. Severe respiratory and neurologic complications from NiV have no treatment other than intensive supportive care. The case fatality rate among those infected is estimated at 40-75%. NiV outbreaks cause significant economic burden to impacted regions due to loss of human life and interventions to prevent further spread, such as the slaughter of infected animals. NiV has been identified as the cause of isolated outbreaks in India, Bangladesh, Malaysia, and Singapore since 2000 and is included on the WHO R&D Blueprint list of epidemic threats needing urgent R&D action.
Latest data and next steps
mRNA-1215, our vaccine candidate against the Nipah virus (NiV), was co-developed along with the NIH’s Vaccine Research Center. The Phase 1 clinical testing will be focused on pandemic preparedness.
SYSTEMIC SECRETED AND CELL SURFACE THERAPEUTICS MODALITY
Our systemic secreted and cell surface therapeutics modality currently has three active development programs, of which one has entered the clinic. We previously announced positive data from our Chikungunya Antibody program (mRNA-1944) within this modality. However, we do not expect to advance our Chikungunya Antibody program without outside funding, and we are not currently pursuing further development of it at this time.
IL-2 Mutein (mRNA-6231)
IL-2 is a critical cytokine for Treg activation and expansion and our product utilizes subcutaneous mRNA administration to produce a modified version of IL-2 in order to treat autoimmune diseases
IL-2-based therapeutics are being clinically evaluated for a wide range of immune-mediated disorders, including rheumatoid arthritis, systemic lupus erythematosus, graft versus host disease, inflammatory bowel diseases, and autoimmune hepatitis. IL-2 is a cytokine, which are potent modulators of the immune system, directing function and homeostasis. IL-2 is critically important to T cell survival and function. IL-2 acts through a receptor complex that can be dimeric, IL-2Rß (CD122) plus the common γ chain (CD132), or trimeric, which is formed through the addition of IL-2Rα (CD25) to the dimeric form. The trimeric form has 10-fold to 100-fold greater affinity for IL-2. Under low or homeostatic IL-2 conditions, those cells which preferentially express the trimeric receptor, or IL-2R, such as Tregs and very recently activated effector T cells, are activated.
We believe that our platform can be exploited to produce a modified IL-2 for the treatment of autoimmune conditions. Our modified IL-2 is engineered with mutations that selectively decrease binding to the dimeric IL-2 receptor present on CD4+ and CD8+ T effector cells and NK cells, and increase reliance upon CD25 of the trimeric IL-2 receptor complex to trigger the signaling cascade in regulatory T cells. Our modified IL-2 is also expressed as a fusion protein to extend its half-life in the serum. It is also the first demonstration of subcutaneous administration of the delivery technology that was also used our chikungunya antibody therapeutic, mRNA-1944.
Latest data and next steps
mRNA-6231 is ongoing in a Phase 1 clinical study. The trial is a Phase 1, first-in-human, dose-escalation study to evaluate the safety, tolerability, pharmacokinetics, and pharmacodynamics of mRNA-6231 in healthy adult participants (between 18-50 years of age), following subcutaneous administration of mRNA-6231.
Table of Content
PD-L1 (mRNA-6981)
PD-L1 is a co-inhibitory receptor that can induce anergy in programmed cell death protein 1 (PD-1)-expressing T cells and we intend to induce expression of PD-L1 on myeloid cells to send a tolerizing signal to immune cells in their environment in order to treat autoimmune diseases
The PD-L1/PD-1 pathway has a critical function in immune regulation and promotes development and function of Tregs. PD-L1 is a transmembrane protein expressed on antigen presenting cells, such as dendritic cells and macrophages, activated T cells, B cells, and monocytes as well as peripheral tissues. Its cognate receptor, PD-1, is a co-inhibitory transmembrane protein expressed on T cells, B cells, natural killer cells and thymocytes. Preclinical mouse models deficient in PD-1 spontaneously develop a variety of autoimmune diseases such as arthritis, myocarditis, lupus-like glomerulonephritis and type 1 diabetes, demonstrating the critical role of the PD-L1/PD-1 interaction in maintaining tolerance to self-antigens. Additionally, treatment of cancer patients with PD-1 or PD-L1 inhibitors sometimes results in immune-related adverse events, including the development of hepatitis, dermatitis and colitis, demonstrating the role of PD-1/PD-L1 in human autoimmune reactions.
We believe our PD-L1 therapy may augment PD-L1 expression on cell types similar to those that endogenously express it, and by reducing immune activation, potentially reduce the clinical manifestations of a variety of autoimmune diseases. Our intent is to use our platform to influence myeloid cells, including dendritic cells, to provide additional co-inhibitory signals by augmenting endogenous expression of PD-L1. We believe that this tolerizing signal to lymphocytes may limit autoreactivity in the context of ongoing autoimmune pathology without severe and global suppression of the immune system. Given that our platform allows us to modify myeloid cells in situ, our approach to the creation of a tolerogenic environment may provide unique benefits in treating autoimmune diseases by seeking to restore immune homeostasis.
Latest data and next steps
We have investigated mRNA-6981 in a range of preclinical models of autoimmune and related diseases, including arthritis, type 1 diabetes, colitis and graft-versus-host disease, and observed disease-modifying activity. We are currently in preclinical studies for mRNA-6981.
Relaxin (mRNA-0184)
Relaxin is a vasoactive peptide associated with cardiovascular remodeling and we intend to encode for a relaxin fusion protein to treat decompensated heart failure
Relaxin is a naturally occurring hormone, present in both men and women, that has been shown to promote vasodilation and angiogenesis, regulate extracellular matrix turnover, and suppress arrhythmias post myocardial infarction. Subsequent studies have implicated relaxin’s role beyond pregnancy, through vasodilatory, antifibrotic, anti-inflammatory and protective effects on multiple organs. Relaxin activates a variety of pathways, contributing to the reduction of oxidative stress, fibrosis, and inflammation. There is a large body of evidence to support relaxin’s clinical potential in several therapeutic areas, with its impact on cardiovascular diseases having been studied in both preclinical and clinical settings. Though prior studies have failed to demonstrate long-term benefit in clinical studies, we believe a novel approach can overcome potential flaws of previous approaches.
mRNA-0184 is being developed to treat decompensated heart failure. Acute heart failure (AHF) is defined as the new onset or worsening of symptoms and signs of heart failure (HF). In developed countries, HF has become a substantial public health problem, affecting 2% of the adult population and AHF is the most frequent cause of unplanned hospital admission in patients of >65 years of age. mRNA-0184 encodes for the relaxin fusion protein. The mRNA sequence of mRNA-0184 is engineered to increase protein expression and prolong half-life.
Latest data and next steps
In preclinical studies, we have shown preliminary protein expression data in nonhuman primates that supports the hypothesis of extended pharmacology relative to historical efforts with recombinant protein. We are planning for a Phase 1 study in participants with chronic heart failure. We expect that mRNA-0814 will be administered after heart failure decompensation to bridge patients through the vulnerable period.
CANCER VACCINES MODALITY
Our cancer vaccines modality currently has three development programs, two of which have entered the clinic. We have regained all rights to our KRAS vaccine (mRNA-5671) from Merck and we are evaluating next steps for the program.
Table of Content
Personalized Cancer Vaccine (PCV) (mRNA-4157)
PCV encodes for up to 34 neoantigens designed against an individual’s patient tumor mutations and is ongoing in a Phase 1 and Phase 2 trial across a variety of indications
As tumors grow, they acquire mutations, some of which create new protein sequences, or neoantigens, that can be presented on human leukocyte antigen (HLA) molecules in the tumor and recognized as non-self by T cells. These neoantigens can be shared or are completely unique to an individual patient’s tumor. In addition to the neoantigens being unique and patient specific, the presentation of those neoantigens is also dependent on a patient’s specific HLA type. Identification of patient-specific HLA type and tumor neoantigens through next generation sequencing paired with our proprietary, in silico design of each patient’s mRNA vaccine and rapid manufacturing for a specific patient allows us to rapidly deliver a completely unique and personalized medicine to patients.
Our personalized cancer vaccine program, mRNA-4157, consists of an mRNA that encodes up to 34 neoantigens, predicted to elicit both class I (CD8) and class II (CD4) responses, designed against each individual patient’s tumor mutations and specific to their HLA type. The neoantigens are encoded in a single mRNA sequence and formulated in our proprietary LNPs designed for intramuscular injection. The mRNA sequence is then manufactured using an automated workflow to enable a rapid turnaround time.
Latest data and next steps
The Phase 1 trial is an open-label, multicenter study to assess the safety, tolerability, and immunogenicity of mRNA-4157 alone in subjects with resected solid tumors and in combination with the checkpoint inhibitor, pembrolizumab (marketed in the United States as KEYTRUDA®), in subjects with resected and unresected solid tumors. mRNA-4157 is administered on the first day of each 21-day cycle for a maximum of nine doses. mRNA-4157 is administered as monotherapy (Part A) or in combination with pembrolizumab (Parts, B, C, and D) in the United States. Studies have shown mRNA-4157 to be well tolerated at all dose levels. The majority of adverse events from mRNA-4157 have been low grade and reversible. Encouraging data emerging from an expansion arm in patients with head and neck cancer has recently caused us to increase the size of that cohort, which continues to recruit trial participants.
The randomized, placebo-controlled Phase 2 study is investigating a 1 mg dose of mRNA-4157 in combination with Merck’s pembrolizumab (KEYTRUDA®), compared to pembrolizumab alone, for the adjuvant treatment of high-risk resected melanoma. This study was fully enrolled (N=150) in September 2021 and the primary endpoint of the Phase 2 study is recurrence-free survival at 12 months.
KRAS Vaccine (mRNA-5671)
The Phase 1 study, led by Merck, is ongoing; we have retained all rights to our KRAS vaccine (mRNA-5671) from Merck and we are evaluating next steps for the program.
Oncogenic driver mutations that encode targetable T cell neoantigens have considerable potential therapeutic implications: (1) driver mutations are subject to positive selection, as they confer survival advantages for the tumor, and (2) such neoantigens could be shared between patients, enabling an easier approach to developing and manufacturing such therapeutic or curative interventions.
KRAS is a frequently mutated oncogene in epithelial cancers, primarily lung, colorectal cancer (CRC) and pancreatic cancers. The four most prevalent KRAS mutations associated with these malignancies are G12D, G12V, G13D, and G12C, which constitute 80% to 90% of KRAS mutations.
Latest data and next steps
The Phase 1 open-label, multi-center study to evaluate the safety and tolerability of mRNA-5671 both as a monotherapy and in combination with pembrolizumab, led by Merck, is ongoing. We have retained all rights to our KRAS vaccine (mRNA-5671) from Merck and we are evaluating next steps for the program.
Checkpoint cancer vaccine (mRNA-4359)
We are developing a checkpoint cancer vaccine that encodes antigens for Indoleamine 2,3*-dioxygenase (IDO) and programmed death-ligand 1 (PD-L1) antigens*
Our checkpoint vaccine aims to stimulate effector T cells that target and kill suppressive immune and tumor cells that express IDO and PD-L1 antigens. Following vaccine-mediated activation, IDO- and PD-L1-specific T cells kill immunosuppressive (regulatory) immune cells and cancer cells. Cancer cell killing and the reduction of regulatory immune cells tip the balance towards productively
Table of Content
inflammatory immune cells with signaling molecules “heating up” the tumor microenvironment, which leads to additional tumor killing by vaccine-activated T cells. T cell priming leads to recognition of additional tumor-associated antigens and to more tumor killing by tumor-specific cytotoxic T cells. Systemic PD-1/PD-L1 blockade may further amplify the effect, leading to further immune activation and superior disease control.
Our initial indications for our checkpoint vaccine are advanced or metastatic cutaneous melanoma and non-small cell lung carcinoma (NSCLC). Melanoma is the fifth most common cancer diagnosis in the U.S. It accounts for approximately 5% of all new cancer diagnoses and 1.5% of all cancer-related deaths. Cutaneous melanoma is a cancer that starts in the melanocytes (pigment-producing cells) of the skin. If diagnosed at the local stage, the 5-year survival rate is approximately 95%. However, for regional or metastatic disease (stage IIIB+), 5-year survival rates decline to approximately 30 to 60%. Approximately 18,000 new patients are diagnosed with stage IIIB+ cutaneous melanoma in the U.S. Advanced melanoma, a rare and serious type of skin cancer, is responsible for most skin cancer-related deaths, despite representing only 1% of skin cancer cases. Current standard of care pembrolizumab, nivolumab or the combination of nivolumab + ipilimumab.
NSCLC frequently goes undetected, remaining asymptomatic until it has progressed to later stages. Approximately 115,000 people are diagnosed with metastatic NSCLC or progress to metastatic disease annually in the United States. The current approach to treatment of metastatic NSCLC treatment is dependent on the presence of PD-L1 expression. If tumor PD-L1 expression is greater than 50% pembrolizumab or atezolizumab monotherapy are preferred, while a combination of chemotherapy and pembrolizumab is preferred for patients with PD-L1 expression less than 50%.
Latest data and next steps
Our checkpoint vaccine is currently in preclinical studies.
INTRATUMORAL IMMUNO-ONCOLOGY MODALITY
Our intratumoral immuno-oncology modality currently has two development programs, both of which are in the clinic.
OX40L/IL-23/IL-36γ (Triplet) (mRNA-2752)
Triplet includes three mRNAs encoding human OX40L, interleukin 23 (IL-23) and interleukin 36 gamma (IL-36γ), that are encapsulated in our proprietary LNP and administered intratumorally
Despite recent advances in immune-mediated therapies for cancer, the outlook for many patients with advanced cancer is poor. We are developing Triplet (mRNA-2752) and other programs to drive anti-cancer T cell responses by transforming cold tumor microenvironments into productive, “hotter” immune landscapes with local intratumoral therapies. Triplet (mRNA-2752) utilizes the intrinsic advantage of mRNA to multiplex and to produce membrane and secreted proteins with mRNA in a single investigational medicine. Triplet (mRNA-2752) includes three mRNAs encoding human OX40L, IL-23 and IL-36γ that are encapsulated in our proprietary LNP and administered intratumorally. OX40L is a membrane protein, whereas IL-23 and IL-36γ are secreted cytokines. We believe our approach has the advantage of localized high concentration gradients of IL-23 and IL-36γ compared to recombinant proteins administered systemically or intratumorally. Additionally, the mRNA for OX40L encodes for the wild type membrane protein, which we believe recombinant protein technologies cannot enable.
We are developing Triplet (mRNA-2752) for the treatment of advanced or metastatic solid tumor malignancies or lymphoma as a single agent or in combination with checkpoint inhibitors.
Latest data and next steps
mRNA-2752 is ongoing in a Phase 1 open-label, multicenter, dose-escalation study. This study is evaluating the safety and tolerability of escalating intratumoral injections of mRNA-2752 alone and in combination with PD-L1 inhibitor (durvalumab) to define the maximum tolerated dose (MTD) or a recommended dose for expansion (RDE). The study consists of dose escalation and dose confirmation parts, which will occur in Arm A and Arm B, followed by a dose expansion part, which will occur in Arm B, and a Dose Exploration in Arm C as a neoadjuvant therapy for cutaneous melanoma. Enrollment in the dose expansion part of Arm B and Arm C is currently ongoing.
We previously announced the interim results of Part A in 2020. In 2021, we announced that the Phase 1 study demonstrates that Triplet given in combination with AstraZeneca’s durvalumab (IMFINZI®) was tolerated at all dose levels tested and elicited evidence of anti-tumor activity. The recommended dose for expansion (RDE) is up to of 4mg mRNA-2752 + durvalumab. The study also demonstrated evidence of immunomodulation and expected pharmacodynamics in the tumor immune microenvironment (TME) of both injected and un-injected lesions, in both monotherapy and combination cases, as indicated by increases in proliferating (activated)
Table of Content
T cells, PD-L1 levels (marker of interferon signaling), and T cell-inflamed (GEP) and DC transcriptional signature score, with greatest changes observed in patients with clinical benefit.
IL-12 (MEDI1191)
In collaboration with AstraZeneca, we are developing a mRNA that encodes for IL-12 encapsulated in our proprietary LNP delivered intratumorally
Another strategy for cancer patients with immunologically cold tumors is to transform the tumor microenvironment by introducing pro-inflammatory cytokines directly into tumors or draining lymph nodes. In collaboration with AstraZeneca, we are developing MEDI1191, which is an mRNA for IL-12 encapsulated in our proprietary LNP to be delivered intratumorally. Systemic administration of recombinant IL-12 protein was poorly tolerated in early clinical trials and exhibited generally low response rates. MEDI1191 can enhance the immune response by positively impacting both antigen presenting cells and T cells, and local, intratumoral expression of IL-12 can potentially improve tolerability compared to systemic protein treatments.
MEDI1191 is being developed for the treatment of advanced or metastatic solid tumors in combination with a checkpoint inhibitor. MEDI1191 consists of our proprietary LNP encapsulating an mRNA for human IL-12B (p40) and IL-12A (p35) subunits. The mRNA produces a single-chain fusion protein of the IL-12B and IL-12A subunits, with a linker between the subunits. The mRNA sequence has been engineered to enhance protein production and is designed to decrease the amount of protein that might be made in hepatocytes for better tolerability.
Latest data and next steps
In preclinical studies, treatment with IL-12 transformed the tumor microenvironment, with notable activation of natural killer and dendritic cells, and an increase in cytotoxic lymphocytes. AstraZeneca is leading the early clinical development and an open-label multicenter Phase 1 clinical trial of intratumoral injections of MEDI1191 alone and in combination with the checkpoint inhibitor, durvalumab, is ongoing. In 2021, we presented IL-12 data that show evidence of antitumor activity in injected and non-injected lesions as well as pharmacodynamic effects such as increased IL-12, Interferon gamma (IFNγ) and 12, and inflammatory transcriptome.
REGENERATIVE THERAPEUTICS MODALITY
Our regenerative therapeutics modality currently has one development program, which is in the clinic.
VEGF-A (AZD8601)
In collaboration with AstraZeneca, VEGF-A is a localized therapeutic encoding for the VEGF-A protein and addressing ischemic heart failure
Heart disease is the leading cause of death in the United States, accounting for one in every four deaths, and is often due to the inability of adults to regenerate heart tissue. Current approved therapies do not specifically address heart regeneration. Previous attempts at cardiac regeneration have included stem cell grafting and gene therapy, but have faced challenges with safety or efficacy. Several treatments are available for patients with ischemic heart failure. Current treatments include revascularization of the coronary arteries to relieve symptoms and improve cardiac function and therapies that reduce blood pressure or potentially help eliminate excess fluids in congested tissues, including: beta-blockers, angiotensin-converting enzyme inhibitors, angiotensin II inhibitors, and aldosterone receptor blockers as diuretics. However, adult humans are unable to regenerate myocardium tissue following injury and the treatment options described above cannot compensate for this.
Vascular Endothelial Growth Factor A (VEGF-A) is a potent angiogenic factor that promotes growth of blood vessels and acts as a powerful promoter of blood vessel growth. Systemic injection of VEGF-A protein increases VEGF-A exposure throughout the body, which can lead to side effects, but is very short-lived in circulation. Therefore, any therapy involving VEGF-A needs to be localized to elevate local protein concentration and drive revascularization while minimizing systemic side effects. AstraZeneca has opted to pursue the localized application of VEGF-A mRNA in a simple saline formulation in the heart muscle to elevate local protein concentration for longer periods due to increased local protein production. This potentially allows for an extended pharmacodynamic effect at the specific site of injection compared to systemic or local administration of a recombinant protein version of VEGF-A.
Latest data and next steps
Table of Content
Preclinical studies have been conducted at AstraZeneca in models of ischemic heart failure. In mouse, rat, and pig models of myocardial infarction, direct injection in the heart muscle (myocardium) of VEGF-A mRNA led to elevated cardiac VEGF-A protein levels and improved cardiac function. The Phase 1a/b study was a randomized, double-blind, placebo-controlled study in men with type 2 diabetes mellitus conducted in Europe. VEGF-A mRNA was administered by intradermal injection into the forearm skin in single ascending doses. Administration of AZD8601 demonstrated protein production and changes in local blood flow in diabetic patients. Tolerability of our mRNA injected intradermally was demonstrated for all dose levels. The only causally treatment-related adverse events were mild injection-site reactions, occurring in 32 of 33 participants receiving VEGF-A mRNA across both parts of the study design. All adverse events of injection-site reaction were of mild intensity. No deaths, serious adverse events, or adverse events leading to discontinuation occurred.
AstraZeneca has also progressed VEGF-A (AZD8601) to a randomized, placebo-controlled, double-blind, multicenter, 6-month, Phase 2a clinical trial of the safety, tolerability, and exploratory efficacy of epicardial injections of AZD8601 in patients with stable coronary artery disease and moderately decreased left ventricular ejection fraction (LVEF) who are undergoing coronary artery bypass graft surgery. Exploratory efficacy endpoints included LVEF, NT-proBNP (a biomarker which measures the level of a hormone which is elevated in patients with heart failure), and functional patient reported outcomes. In 2021, the Phase 2 study met the primary endpoint of safety and tolerability of AZD8601 for the 3 mg dose. In the study of 11 patients, seven were treated with AZD8601 VEGF-A mRNA and four received placebo injections. Numerical trends were observed in endpoints in the heart failure efficacy domains compared with placebo, including increase in LVEF and patient reported outcomes. In addition, all seven patients treated with AZD8601 had NT-proBNP levels below heart failure (HF) limit at 6 months follow-up compared to one of four patients treated with placebo. AstraZeneca has announced that they intend to move AZD8601 into further studies.
SYSTEMIC INTRACELLULAR THERAPEUTICS
Our systemic intracellular therapeutics modality currently has five development programs, two of which are in the clinic.
Propionic acidemia (PA) (mRNA-3927)
PA is an inherited metabolism disorder with significant morbidity and mortality and our mRNA therapy is ongoing in a Phase 1 trial, aiming to produce an intracellular, mitochondrial enzyme complex to treat the disorder
PA is a serious inborn error of metabolism disorder with significant morbidity and mortality. There are approximately 325-2,000 PA patients in the United States based on estimated birth prevalence (0.2-1.2:100,000 newborns) and mortality rates. The vast majority of patients present with life-threatening metabolic crises during the first few days or weeks of life, with mortality rates ranging from 13-53% during the neonatal period. The cardinal feature of the disorder is the occurrence of life-threatening acute metabolic decompensations that are more frequent in the first few years of life. Longer term sequelae include cardiac complications (cardiomyopathy, arrhythmias) and severe neurologic complications. The disorder is caused by a defect or deficiency in PCC, an enzyme that is one step upstream in the same metabolic pathway as the MUT enzyme that is deficient in MMA, as further described below. PCC is a complex hetero-dodecamer enzyme composed of six alpha subunits (PCCA) and six beta subunits (PCCB). The disorder is autosomal recessive, with PA patients generally having loss-of-function mutations in either PCCA or PCCB (and in rare instances, mutations in both PCCA and PCCB). The disorder is biochemically characterized by the accumulation of toxic metabolites such as 3-hydroxypropionic acid and 2-methylcitrate, among others, and these metabolites may be used as biomarkers of disease. There is no approved therapy for PA to treat the underlying defect, including no enzyme replacement therapy, due to the complexity of PCC and mitochondrial localization.
We are developing an IV-administered combination mRNA approach, which contains two mRNAs, one for each of the subunits of PCC (PCCA and PCCB) encapsulated in our proprietary LNP (the same LNP formulation as mRNA-1944). The intent is to potentially treat the entire PA population, regardless of whether an individual has a defect or deficiency in the PCC alpha or beta subunit. The mRNA sequences have been engineered to improve protein translation and encode enzymatically-active PCC with the proper subcellular localization in the mitochondria.
Table of Content
Latest data and next steps
We have demonstrated activity in a PA mouse model in a long-term repeat dose study. In the 6-month repeat dose study in PA mice, a significant and sustained lowering of additional disease biomarkers (e.g., 2-methylcitrate, or 2MC) was observed throughout the duration of the 6-month study. mRNA-3927 is ongoing in a Phase 1/2 study, the Paramount Study, and the first cohort is fully enrolled, and cohort 2 enrollment is ongoing. The study’s objective is to evaluate the safety and pharmacology of mRNA-3927 in patients 1 year of age and older with PA. The primary endpoints are safety and pharmacokinetics and pharmacodynamics. Secondary endpoints include incidence and severity of adverse events (AEs) and change in plasma biomarkers: methylcitric acid (2-MC) and 3-Hydroxypropionic acid (3-HP). We have received Rare Pediatric Disease Designation, Orphan Drug Designation and Fast Track Designation from the FDA and Orphan Drug Designation from the European Commission for the PA program.
Methylmalonic acidemia (MMA) (mRNA-3705)
MMA is an inherited metabolism disorder with significant morbidity and mortality and our mRNA therapy is ongoing in a Phase 1 trial, aiming to produce an intracellular, mitochondrial enzyme complex to treat the disorder
There are an estimated 500-2,000 MMA MUT deficiency patients in the United States based on estimated birth prevalence (0.3-1.2:100,000 newborns) and mortality rates. Mortality is significant, with mortality rates of 50% for MMA patients with complete MUT deficiency (mut 0) (median age of death 2 years) and 40% for MMA patients with partial MUT deficiency (mut -) (median age of death 4.5 years) reported in a large European study. MMA mainly affects the pediatric population and usually presents in the first few days or weeks of life. The occurrence of acute metabolic decompensations is the hallmark of the disorder and decompensations are typically more frequent in the first few years of life. Each decompensation is life-threatening and often requires hospitalization and management at an intensive care unit. Surviving patients often suffer from numerous complications including chronic renal failure and neurologic complications such as movement disorders, developmental delays, and seizures. Consequently, the health-related quality of life for MMA patients and their families is significantly impaired.
The disorder is autosomal recessive and primarily caused by loss-of-function mutations in the gene encoding MUT, a mitochondrial enzyme that metabolizes certain proteins and fats, resulting in complete (mut 0) or partial (mut -) enzyme deficiency. There are currently no approved therapies that address the underlying defect for MMA.
We are developing an mRNA encoding human MUT encapsulated in our proprietary LNPs for IV administration for the treatment of isolated MMA associated with MUT deficiency. The sequence has been engineered to improve protein translation. To function, the mRNA-encoded MUT protein is translocated to its site of action in the mitochondria. mRNA-3705 is our second generation MMA development candidate.
Latest data and next steps
We previously demonstrated, in a series of in vitro and in vivo pharmacology studies, that human MUT mRNA effectively directs the biosynthesis of active MUT protein with physiologically correct mitochondrial localization in vitro, and improves survival and corrects biochemical abnormalities in two different mouse models of MMA representing the spectrum of MUT deficiency (mut0 and mut-). Technology and process improvements enabled the development of an updated drug product, mRNA-3705, which shows greater potency and better pharmacology compared to our prior candidate, mRNA-3704. mRNA-3705 is currently ongoing in a Phase 1/2 study, the Landmark Study. The study is an adaptive, open-label study is designed to evaluate the safety and tolerability of up to five different dosing regimens of mRNA-3705 administered via intravenous infusion in patients one year and older with isolated methylmalonic acidemia due to methylmalonyl-CoA mutase (hMUT). Upon establishment of an optimized dose based on safety and pharmacological data, additional patients may be enrolled in an optional expansion cohort.
Table of Content
Glycogen storage disease type 1a (GSD1a) (mRNA-3745)
GSD1a is an inherited metabolism disease and our approach is to use an mRNA encoding for intracellular human glucose 6-phosphatase
GSD1a is an inherited metabolic disorder caused by a deficiency in the catalytic activity of G6Pase. G6Pase catalyzes the hydrolysis of glucose-6-phosphate to glucose and inorganic phosphate, the final step of glycogenolysis and gluconeogenesis that mainly takes place in the liver and kidneys. GSD1a patients suffer from severe fasting hypoglycemia, hepatomegaly, nephromegaly, lactic acidemia, hypertriglyceridemia, hyperuricemia, hypercholesterolemia, hepatic steatosis, and growth retardation. In addition, hepatocellular adenomas occur in 70% to 80% of GSD1a patients by their third decade of life and carries risk of transformation into hepatocellular carcinomas. Proteinuria has been observed in over half of patients above 25 years of age. GSD1a occurs in approximately 1:100,000 live births in the United States and European Union but is more common in Ashkenazi Jews where the incidence is reported to be 1:20,000 live births. There are an estimated 2,500 people in the United States and over 4,000 people in the European Union with GSD1a. Although strict diet therapy, including frequent feeding with uncooked cornstarch, allows GSD1a patients to live into adulthood by preventing hypoglycemia, the underlying pathological processes remain uncorrected resulting in the development of many long-term complications including liver adenomas and hepatocellular carcinoma.
Our program, mRNA-3745, consists of an mRNA encoding for modified human G6Pase encapsulated in our proprietary LNPs. The human G6Pase sequence is modified for improved protein production and G6Pase activity. mRNA-3745 is designed to be administered intravenously and encodes G6Pase protein to restore this deficient or defective enzyme.
Latest data and next steps
We have conducted several in vitro and in vivo pharmacology studies to demonstrate preclinical proof-of-concept for GSD1a therapy. mRNA encoding for G6Pase introduced in human cells resulted in robust production of active G6Pase with subcellular localization into endoplasmic reticulum. mRNA-3745 has been granted Orphan Drug Designation by the U.S. FDA as well as the European Medicines Agency (EMA) and has an open IND. The Phase 1 study will evaluate the safety and pharmacology of mRNA-3745 in patients 18 years of age and older with GSD1a. The Phase 1 study, the Balance Study, is a single dose escalation study in adult participants diagnosed with GSD1a. The primary objective is to determine the safety and tolerability following a single dose of mRNA-3745. Secondary objectives are to evaluate pharmacokinetics and pharmacodynamics of mRNA-3745 in adult GSD1a patients.
Phenylketonuria (PKU) (mRNA-3283)
PKU is a rare inherited metabolic disease is and our approach is to use an mRNA encoding for intracellular phenylalanine hydroxylase (PAH)
Phenylketonuria (PKU) is a rare inherited metabolic disease resulting from a deficiency in the metabolism of phenylalanine (PHE) due to mutations within the enzyme phenylalanine hydroxylase (PAH). The most effective treatment is a restrictive diet of low protein, which controls PHE intake. Approximately 20-56% of PKU patients respond to sapropterin dihydrochloride (marketed as Kuvan in the United States), a synthetic BH4 cofactor for PAH which improves PHE metabolism, but does not fully cure patients. In addition, in May 2018, Biomarin received approval for pegylated phenylalanine lyase (PAL), marketed as Palynziq. Palynziq is a pegylated recombinant bacterial enzyme which metabolizes PHE in the blood. We believe the immune risk is, at least in part, driven by bacterial PAL. PKU occurs in approximately 1:10,000-15,000 live births in the United States*.* Based on current population estimates that would translate into approximately 21,000-32,000 PKU patients in the United States. Affected individuals have a deficiency in the enzyme PAH, resulting in a reduced or complete inability to metabolize the essential amino acid phenylalanine into tyrosine. Thus, PKU patients suffer from a phenylalanine intoxication and a subsequent deprivation of tyrosine, leading to severe mental disability if left untreated.
Our program mRNA-3283 consists of an mRNA encoding human PAH encapsulated in our proprietary LNPs. The mRNA sequence is optimized for protein synthesis and contains a microRNA binding site to reduce or potentially eliminate synthesis of protein outside of the target tissues. mRNA-3283 is designed to be administered intravenously to encode enzymatically-active PAH protein in liver to restore this deficient or defective enzyme.
Latest data and next steps
We have conducted several in vitro and in vivo pharmacology studies to demonstrate preclinical proof-of-concept for PAH therapy. A PKU mouse model demonstrated a significant reduction of blood PHE levels post dose. mRNA-3283 is ongoing in preclinical studies.
Table of Content
Crigler-Najjar Syndrome Type 1 (CN-1) (mRNA-3351)
CN-1 is a severe condition caused by the mutations in the UGT1A1 gene and our approach, in collaboration with the Institute of Life Changing Medicines (ILCM), is to encode for the human UGTA1A1 protein
Crigler-Najjar syndrome is a severe condition characterized by high levels of a toxic substance called bilirubin in the blood (hyperbilirubinemia). It is caused by the mutations in the UGT1A1 gene in which bilirubin, a substance made by the liver, cannot be broken down. Without this enzyme, bilirubin can build up in the body and lead to jaundice and damage to the brain, muscles and nerves. The symptoms become apparent shortly after birth and can be life-threatening. It is estimated that there are only approximately 70-100 known cases of CN-1 in the world. Affected individuals rely on current standard of care, phototherapy treatments of up to 12 hours a day, throughout life. The only definitive treatment is liver transplant that is associated with its own set of side effects and risk of death.
Our program, mRNA-3351, consists of an mRNA encoding human UGTA1 encapsulated in our proprietary LNPs. It is designed to restore the missing or dysfunctional proteins that causes CN-1.
Latest data and next steps
We have licensed mRNA-3351 to ILCM with no upfront fees and without any downstream payments. The goal of the collaboration is to make an mRNA therapy for the treatment of CN-1 available at no cost to patients. ILCM will be responsible for the clinical development of mRNA-3351.
INHALED PULMONARY THERAPEUTICS
Our inhaled pulmonary therapeutics modality currently has one development candidate.
Cystic Fibrosis (CF) (VXc-522)
CF is a multi-system disease caused by the mutations in the CFTR gene and our approach, in collaboration with Vertex, is to deliver mRNA to the lungs to provide functional CFTR protein expression that translates to transformative clinical benefit
CF is a rare genetic disease, which is progressive from birth and leads to multi-organ damage and early death due to lung dysfunction. It is caused by the mutations in the cystic fibrosis transmembrane conductance regulator (CFTR) gene which results in the loss of CFTR chloride ion channel function. This decreased function of CFTR at the cell surface leads to thick, sticky mucus in multiple organ systems but most pathologically the lungs. It is estimated that there are ~75,000 patients with cystic fibrosis in the world, with ~10% of these patients not addressable with the approved CFTR modulators.
Our program is designed to treat the underlying cause of CF by enabling cells in the lungs to produce functional CFTR protein for the treatment of the 10% of patients who do not produce any modulator-responsive CFTR protein.
Latest data and next steps
We are collaborating with Vertex on our CF candidate, VXc-522. Pre-clinical studies are ongoing and Vertex expects to submit an IND in 2022.
Table of Content
MANUFACTURING
Manufacturing plays a critical role in our value chain and our ability to develop a new class of medicines. Our manufacturing capabilities support every stage of the development of our products, from new product ideas to commercialization. During the research stage of product development, manufacturing provides mRNA drug substance and drug product for platform research and therapeutic area drug discovery. During early development of our investigational medicines, we manufacture mRNA and drug product for IND-enabling GLP toxicology studies and initial human clinical studies. For late clinical development, we produce mRNA and drug product for phase 3 studies. At the commercial stage of development, we manufacture drug substance and drug product in collaboration with our contract manufacturing organizations (CMOs), both in the U.S. and internationally.
Our approach to date has been to proactively invest and build manufacturing capacity internally and externally with our network of strategic partners in anticipation of demand. This capacity was immediately leveraged and expanded during our COVID-19 vaccine ramp-up into a commercial product in response to the ongoing pandemic. Our ability to rapidly accelerate our manufacturing capabilities in response to COVID-19 allowed us to ship 807 million doses of our COVID-19 vaccine globally in 2021, compared to 17 million doses in December 2020. We are committed to further increase our manufacturing capacity substantially in 2022.
Overview of our manufacturing operating model
Our manufacturing activities generally focus on the following:
-
Commercial Production:** Our manufacturing expertise includes state-of-the-art technologies for mRNA and drug product manufacturing, as well as quality control testing to attain a robust and consistent supply that matches target product profiles. Our manufacturing technology is built to scale-up and support industrialization of products for commercial approval.
-
Research and Development Support:** The product supply enables platform research and drug discovery in our therapeutic and vaccine areas, in addition to activities related to clinical studies of our investigational medicines.
Given our expectations for significant ongoing pipeline expansion and the long lead time required to build manufacturing infrastructure, we built a dedicated in-house manufacturing facility in Norwood, MA, the Moderna Technology Center (MTC), which we have since expanded to a multi-building campus. The MTC provides supply for our preclinical research, IND-enabling GLP toxicology study supplies, our Phase 1 and Phase 2 pipeline activities, later-stage clinical development activities (e.g., Phase 3 CMV vaccine clinical trials), as well as COVID-19 vaccine drug substance production.
The MTC campus has been designed with a high level of automation and state-of-the-art digital integration to handle manufacturing execution, product testing and release, and regulatory filings. In addition, substantial manufacturing capabilities are realized via CMO relationships in the United States and abroad, providing drug substance and fill-finish capacity for the COVID-19 vaccine. Much of the production for our COVID-19 vaccine supply for the U.S. market is completed at the MTC campus, with additional production by Lonza Ltd. (Lonza). We have also partnered with Lonza to complete production in Switzerland of our COVID-19 vaccine for markets outside the United States, as well as with National Resilience, Inc. to manufacture drug substance at its facility in Ontario, Canada for distribution worldwide. Fill-finish services for our COVID-19 vaccine are provided by Catalent Inc., Thermo Fisher Scientific, Sanofi and Baxter BioPharma Solutions in the United States, and by ROVI (in Spain), Recipharm (in France) and Samsung Biologics (in South Korea) outside the United States. We have also partnered with other CMOs for the production of and fill-finish services of our COVID-19 vaccine, and expect that we will enter into additional collaborations as we continue to scale. In April 2021, we announced additional investments in manufacturing to increase supply at our owned and partnered manufacturing facilities, with the goal of increasing our global 2022 capacity for COVID-19 vaccine production. In May 2021, we announced the planned expansion of the MTC, which we expect to more than double the space at the MTC and allow us to continue to optimize our mRNA products as we explore new pharmaceutical delivery forms such as prefilled syringes and lyophilized products. Additionally, in February 2022, we announced new collaborations with ROVI and Thermo Fisher Scientific (Thermo Fisher) for manufacturing capabilities. With ROVI, we agreed to a ten-year collaboration to increase manufacturing capacity at ROVI’s facilities in Spain. In addition to producing our COVID-19 vaccine, we expect that ROVI's platform may be utilized to service other vaccine candidates in the future. With Thermo Fisher, we agreed to a fifteen-year collaboration to enable dedicated large-scale manufacturing in the United States of our COVID-19 vaccine and other investigational mRNA medicines in our pipeline.
In addition, during 2021 we announced agreements in principle with the governments of Canada and Australia to establish mRNA manufacturing facilities in those countries. These agreements are subject to final negotiation, but we envision entering into long-term supply agreements with these countries for the supply of mRNA vaccines. By establishing manufacturing facilities locally, we will also provide these governments with direct access to rapid pandemic response capabilities. We are in active discussions with other governments to provide similar manufacturing capabilities in other geographies.
We have further committed to building a state-of-the-art mRNA facility in Africa to provide a local source of mRNA medicines for the continent, in part to prepare for future pandemics. We expect to invest up to $500 million in this facility and anticipate that once fully operational, it will be capable of producing up to 500 million doses of vaccines annually at the 50 µg dose level.
Table of Content
Manufacturing technology development
To support our broad pipeline of products, which span multiple therapeutic areas and routes of administration (e.g., intramuscular, intratumoral, and intravenous), there is close collaboration between our platform research and technical development teams to facilitate rapid and seamless clinical translation of scientific breakthroughs. This, in turn, enables us to develop potential vaccines and therapies to serve a widening patient population.
Technical development encompasses the design and optimization of robust and consistent manufacturing processes, product characterization, fit-for-purpose formulations, and product presentations. For instance, our novel hardware platforms’ automation and robotics, coupled with the flexibility of our in-house digital development systems, allows for thousands of experiments and process parameters across our projects, thus supporting our drug product pharmaceutical readiness. Moreover, our recent technical manufacturing advances have enabled internalization of new key capabilities, including DNA plasmids and small molecules.
In parallel, we have refined existing processes, resulting in increased manufacturing scale and more robust stability of our mRNA and drug product. These improvements allow us significant control over our supply chain, resulting in larger production yields and longer shelf life of our products. Furthermore, formulation development advancements have added new drug product images, including lyophilization, giving us a path from frozen to refrigerated storage conditions.
Our substantial investments in recent years in technical development has enabled the breadth and depth of our pipeline, and laid the foundation to help meet the needs and requirements associated with late stage development and the commercialization of the COVID-19 vaccine.
Supply of mRNA for All Stages of Product Development and Commercialization
Supply for Research
High-throughput automation and custom engineered equipment allow us to produce and deliver high quality mRNA and formulated constructs in a short period of time: our proprietary platform is capable of producing up to 1,000 lots of mRNA sequences and formulations per month with a turnaround time of a few weeks from sequence to final product. The typical scale of mRNA manufactured by this team is 1–1,000 mg. This has been possible, in part, thanks to the ability of researchers in the Moderna ecosystem to order constructs through an integrated digital portal that tracks materials end-to-end in less than 45 days. In addition, multiple integrated algorithms that leverage artificial intelligence and machine learning optimize manufacturability, reduce failures, and increase quality of mRNA sequences.
Supply for Early Development
We have established manufacturing capabilities that support the early development stage of product development in three key areas: GLP Tox, Clinical Studies, and Personalized Cancer Vaccines. We supply mRNA and formulated product to conduct IND-enabling GLP toxicology studies. In addition, human clinical studies rely on supply to meet required cGMP standards. This is achieved via internal manufacturing at the MTC and external manufacturing at well-established CMOs. We select specialized CMOs to support our portfolio. We will continue to selectively partner with CMOs to complement our capacity and provide supply contingency where needed. Our MTC facility is also suited to enable rapid technology development and scale-up for future needs. Our manufacturing also produces cGMP PCVs. Due to the specialized nature of personalized medicine (i.e., where a batch is specifically designed and manufactured for a single patient), the manufacturing Personalized Vaccine Unit (PVU) has unique requirements. We digitally integrate patient-specific data from sequencing tumor samples to automatically design PCVs for patients. We have developed proprietary bioinformatics designed algorithms linked to an automated manufacturing process for rapid production of formulated mRNA, with a typical turnaround time of a few weeks. We have operationalized PCV manufacturing at the MTC campus to meet our Phase 1 and 2 pipeline supply needs by using single-use systems with fast “needle-to-needle” turnaround times. Unlike traditional process development, each PCV batch is manufactured for a single patient and thus scaled-out (in parallel) with extensive use of automation and robotics to account for the larger number of patients involved in later phases of development and commercialization. We have shown consistent quality in our production of over 160 patient batches, each with unique mRNA sequences.
These capabilities have allowed us to build our broad pipeline of 44 development programs, including the output required to supply related toxicological and human clinical studies. While the technology that underpins these programs is the same, each program typically requires customization based on target product profiles. These custom features range from varying molecular architecture to different routes of administration, often requiring multivalent products. For example, our CMV vaccine (mRNA-1647) requires six different mRNA sequences to be manufactured for inclusion in an intramuscular mRNA medicine, whereas our COVID-19 vaccine (mRNA-1273) requires a single mRNA sequence for inclusion in an intramuscular mRNA medicine. All programs, with the exception of PCV, require that we progressively scale up supply to meet clinical demand requirements across development phases, in addition to
Table of Content
the necessary preparation for regulatory approval and commercial production, which demand larger batch sizes. In contrast, the PCV program seeks to develop a cancer vaccine that is designed and manufactured for a specific patient, thus increasing the number of unique batches. As we scale manufacturing output for each program, we plan to continuously improve yield, purity, and the pharmaceutical properties of our development candidates.
Supply for Late-Stage Development and Commercialization
As we continue to manufacture our COVID-19 vaccine, our development pipeline continues to advance to later-stage development and towards commercialization. Our platform approach allows us to continue to evolve our manufacturing suites and other capabilities at our MTC campus. Building expansions and enhancements have continued throughout scale-up of our COVID-19 vaccine manufacturing capabilities. The modular nature of the MTC suites permits us to manufacture multiple products in parallel. For instance, we can produce drug substance and drug product for our phase 3 CMV clinical trial while manufacturing COVID-19 drug substance in the same facilities.
Quality Unit
Quality is core to the way we operate. We seek to ensure quality at Moderna through a combination of a robust Quality Management System (QMS), our quality culture, and our people. In accordance with applicable regulations, we have established, documented, and implemented a QMS to assure continued compliance with the requirements therein. The QMS facilitates cGMP compliance by implementing practices that identify the various required processes, their application throughout the organization, and the sequence of interaction of these processes.
The primary mode of documenting these key practices is through policies, standard operating procedures (SOPs), forms, and other quality records, which include an overarching Quality Policy and Quality Manual. We have implemented measurement tools and metrics to monitor, measure, and analyze these practices to support cGMP operations, achieve planned results, and support continuous improvement. We monitor these quality metrics through formal governance processes, including Quality Management Review (QMR), to enable continuous improvement. We have also established an independent Quality Unit that fulfills quality assurance and quality control responsibilities.
Our Quality Unit grew into an international organization with the introduction of COVID-19 vaccine manufacturing. Quality drives our quality culture and ensures it is applied consistently and thoughtfully across the globe.
While the Quality Unit is ultimately accountable and responsible for quality, this is a shared responsibility. All cGMP personnel are empowered to ensure quality systems are appropriately maintained and executed.
We have established a culture that encourages transparency, accountability, and ownership of quality at all levels in the organization. As we scale the quality organization, we have focused on hiring the best talent with the required experience, training, and education.
Supply Chain Unit
We have established an international supply chain to enable supply of the raw materials used to produce our mRNAs and the components of our formulations, securing supply for COVID-19 vaccine alongside clinical and preclinical demands. We have worked with our supply chain vendors to characterize critical raw materials and to understand their impact on the quality of mRNA drug substance and formulated drug product. We also assess the quality system and performance of our supply chain vendors and work with them to comply with regulatory requirements.
Table of Content
DIGITAL INFRASTRUCTURE
We believe that digital technologies, such as robotics, automation, artificial intelligence (AI) and cloud computing, are critical to operationalize our strategy, accelerate our pace of learning and execute at scale. We aspire to digitize our operations wherever possible, with the goal of using the power of digital technology to maximize our impact on patients. Since our inception, we have invested heavily in our digital technologies, robotics/automation, analytics, data science and AI. To facilitate our growth, we will continue to invest in our digital infrastructure. Construction has begun on our new Moderna Science Center in Cambridge, which is designed to integrate digital-first scientific research and development labs. Our approach to bring these digital technologies into our workflows and processes has involved the following:
-
utilization of a consistent set of digital building blocks;
-
application of digital technologies in multiple business processes; and
-
rapid iterations for maximum optimization.
We have seen several benefits from our investments in digitization, most importantly through the depth of our platform technology and breadth of our pipeline. Other benefits include:
-
Quality: Reduction in human errors by enabling automation, repeatability, and seamless integration;
-
Scalability: Growth in our pipeline to 44 development programs;
-
Speed: Rapid manufacture of cGMP product, as exhibited by our first COVID-19 vaccine batch, and research-grade mRNA; and
-
Cost efficiencies: Digital infrastructure utilized across our platform, drug discovery, clinical development, and manufacturing to maximize efficiencies.
Our digital building blocks
We utilize six building blocks for our digital infrastructure:
-
Cloud enablement is a critical component of our digital infrastructure. We are at the forefront of mRNA technology. We generate complex data sets, and our scientists need computational power and agility to operate without being limited by traditional computing technology. Maintaining digital infrastructure in the cloud provides the benefits of lower costs by simplifying provisioning and administration, flexibility, scalability, ease of maintenance, disaster recovery, and information security.
-
Integration of business processes enables us to streamline processes and bring data together in a consistent manner, avoiding caches of information and manual intervention. This efficient flow of data between systems enables the automation of our business processes.
-
Internet of things allows for smart interconnected devices that provide real-time synchronization of operations. The data from equipment provides real-time guidance to our scientists and engineers and helps us in supply chain and manufacturing with compliance and traceability, including tracking material, controlling inventory and optimizing instrument usage.
-
Automation allows us to scale our operations reliably and reproducibly. With the help of custom hardware solutions and state-of-the-art robotics, we can continue to increase our operating efficiency, reduce errors, and improve our quality and compliance.
-
Advanced analytics enable us to draw insights from our data. We are constantly generating large data sets that can provide important insights if mined appropriately and regularly.
-
AI is enabling key breakthroughs in predictive modeling. It will allow us to improve our mRNA design algorithms based on machine learning, and will provide us with critical insights into research, supply chain, manufacturing, and other processes.
Digital technologies to enable our drug discovery efforts
We have deployed multiple digital technologies to drive a rapid pace of learning, enable efficient workflows and business processes, and draw insights from vast amounts of data. Our aim is to provide our platform and discovery scientists with access to an environment that helps them through each step of their research cycle.
Drug Design Studio: Our proprietary in-house digital application suite contains a Sequence Designer module to tailor an entire mRNA, with ever-improving rule sets that contain our accumulated learning about mRNA design. Drug Design Studio utilizes cloud-based computational capacity to run various algorithms we have developed to design each mRNA sequence. The utility of cloud-based capacity allows us to provide flexible computational capacity on demand, allowing us to power parallel intake and design of multiple mRNA sequences. Once a sequence is designed, it can be ordered digitally using an internal order form application within Drug Design Studio.
Manufacture of research-grade mRNA: Once an order is optimized, the mRNA production process is triggered. We have developed proprietary interfaces that allow the manufacturing team to track production orders at every stage. We have automated several manufacturing steps using both off-the-shelf and custom automation. The equipment used in the manufacture of research-grade
Table of Content
mRNA is integrated with the digital interfaces to capture, extract, and interpret the data generated at each step of the manufacturing process, building digital traceability on each mRNA order. We have also embedded real-time algorithms and analytics tools to allow for automated decision-making at some stages, accelerate the quality control workflows, and provide for continuous improvement of manufacturing processes.
Dispatching and shipping mRNA: Because we produce large quantities of research-grade mRNA, we require digital tools to track their shipment to our scientists and to external contract research organizations (CROs) conducting in vivo studies. Our dispatching and shipping application automatically generates bar-coded labels, allowing for traceability of product.
Inventory and registry: Material used in research and created in production, including mRNA, cell lines, chemicals, and reagents, is tracked in our Inventory application. This application supports numerous workflow tools such as consumption, aliquoting, material transfer, and stock alerts. Critical material types are assigned unique registry identification by our Registry application.
Study design: Using our Drug Design Studio, our scientists can design their in vivo studies using our proprietary Study Design application. This application captures in vivo study protocol design parameters, including dose amount, number of doses, frequency, samples, and assays for each sample. This application serves two purposes. It allows our scientists to maintain and track their in vivo study designs and associated research grade mRNA. Our Study Design application also allows our in vivo pharmacology teams to track the various ongoing studies and leverage external CROs to manage the in vivo demand as needed.
Experiment management: We have deployed Electronic Lab Notebooks for experiment management, allowing our scientists to streamline documentation of their experiments and track it in a standardized, searchable repository. We have also integrated Electronic Lab Notebooks further with our other research tools to connect inventory, in vivo studies, and instrument data.
Advanced analytics and AI to accelerate the pace of learning: We utilize AI to enable various parts of our platform and drug discovery. Examples include:
-
Neural networks for protein engineering: One way to optimize the efficacy of the proteins encoded by our mRNA is to engineer the sequence of the protein itself. We use neural networks to analyze and model protein sequences. We train these models by inputting orthologous sequences from thousands of organisms, from which we can generate potential protein sequences optimized for specific attributes.
-
Neural networks for mRNA engineering: The redundancy in the genetic code allows for a large number of mRNA sequences that encode the same protein. mRNA sequence may impact translation, thereby impacting the amount of protein produced in circulation. We are developing AI tools to predict mRNA sequences that can enhance protein expression.
-
Automated Sanger sequencing analysis: Sanger sequencing is used repeatedly to quality check (QC) our DNA templates and final mRNA; while the data contain every nucleotide in a sequence, it is very complex to analyze. A fully automated data pipeline starts processing raw data the moment it is saved to the cloud by the sequencers. The pipeline spawns numerous AWS computer servers to run an analysis algorithm and then shuts the servers down, minimizing costs. The results are viewable in a powerful, dynamic visualization tool. We have run over three million Sanger data files through this system. We have further improved our Sanger analysis with a convolutional neural network (CNN) to better analyze the tail sections of mRNA as well.
Digital technologies to enable our clinical trials
We have deployed multiple digital technologies to drive the rapid pace of advancement, in parallel, of our development candidates into the clinic.
Digital systems for cGMP manufacture: We are committed to having integrated systems connected with robotics to drive our manufacturing in a paperless environment, and have designed and deployed automation to drive efficient manufacturing operations. We have also deployed digital tools within manufacturing process development that give us the ability to track, analyze, and rapidly deploy manufacturing process improvements. Additionally, we have implemented several digital systems across manufacturing process development, quality, supply chain, and operations, including:
-
enterprise Quality Management System (QMS) to electronically manage deviations, investigation, and correction and preventive actions;
-
Laboratory Information Management System (LIMS) to manage our analytical development data and automate our manufacturing quality control;
-
computerized maintenance management system to manage equipment maintenance and calibration; and
-
SAP/S4 Hana system for enterprise resource planning (ERP), manufacturing execution system, and manufacturing control system to manage inventories, track raw material consumption, digitally integrate equipment with manufacturing recipes in batch records, and control automated equipment.
Table of Content
Digital systems for clinical development and clinical operations: In order to track the timelines of various development candidates, we have created a set of integrated applications. Workflows include timelines for regulatory filings, planning for IND-enabling GLP toxicology studies, scheduling for cGMP manufacturing, and clinical operations management. Below is a summary of our applications:
-
Our portfolio application is a digital interface that maintains and tracks the timelines across multiple workstreams for each of our development candidates.
-
The supply application manages the manufacturing schedule of IND-enabling GLP toxicology supplies and cGMP manufacture of clinical supplies to support our programs. This application helps us see how the manufacturing schedule changes over time, identifies supply/demand mismatches, and enables resource planning with real-time alerts should we have any issues.
-
The GLP toxicology application tracks the planned and ongoing IND-enabling GLP toxicology studies and allows us to manage timelines with our external vendors.
-
The regulatory application tracks timelines related to regulatory affairs including, pre-IND meetings, IND/CTA submission dates, and other planned regulatory interactions.
-
Our clinical operations application allows us to track our ongoing trials by accessing clinical operations information in real-time from our CROs. It also has multiple tools and analytics to draw key insights, including, for example, enrollment by trial and enrollment by site to maintain our program timelines.
Digital systems for PCV: The PCV program aims to design, manufacture, and deliver a drug product that includes an mRNA sequence encoding for each patient’s specific neoantigens. The personalized nature of the PCV program adds additional steps and complexity in the overall patient treatment process. We have addressed those additional steps and complexity by digitizing and automating steps within the process, as described below.
-
Each patient is provided a unique identifier. We track the entire workflow using a single integrated tracker based on this unique identifier. This is one of many ways we ensure that each patient receives the specific drug product lot manufactured for them.
-
We use neural networks to design the mRNA sequences for the PCV program. Our proprietary vaccine design algorithm selects the top twenty neoantigens to be used and determines their amino acid sequences to trigger the desired immune response.
-
We utilize Monte Carlo simulations of PCV supply/demand to manage our capacity. Since each drug product lot is personalized to a patient, there is a need to manage supply and demand to avoid bottlenecks at any stage of the workflow.
Digital systems for commercialization: Our investment in our digital capabilities prepared us to rapidly scale our production of our COVID-19 vaccine in 2021 and 2022. We are continuing to build out our commercial capabilities to establish medical affairs engagements with doctors, support our sales and marketing capabilities and deliver a world-class patient experience. In addition to a patient- and doctor-centric view, our commercial capabilities will strengthen our supply chain demand forecasting and our compliance. We are looking at building a robust serialization process for regulatory requirements as well as anti-counterfeiting technologies to ensure safe, efficacious medicines to patients.
Digital technologies to support our business processes
We have deployed several digital systems across finance, manufacturing, and human resources to automate our business processes and drive efficiencies. We have implemented the SAP S4/Hana system for ERP. We have implemented various cloud-based solutions to improve business processes and drive efficiencies. For example, we have implemented the Workday system for human resource planning and management and integrated various applications across payroll, 401(k) services, equity plan management and expense reporting. Our class-leading integration platform, Dell Boomi, allows us to have a highly interconnected environment, moving us from simple cloud-to-cloud integrations to an evolving use of the integration platform for master data management, systems account management, and ultimately for cost savings and improved user experience.
COMMERCIAL
We have grown our U.S. and international commercial sales organization beginning in early 2020 as we prepared for the commercialization of our COVID-19 vaccine. We have active commercial subsidiaries in 11 countries, including the U.S., Canada, many European countries and the Asia Pacific region, providing us with local commercial teams in key markets around the world. This commercial presence is supported by the Moderna International Business Service center in Warsaw, Poland. Our commercial teams also work in conjunction with third-party distributors and other partners in countries where we do not have a presence. In February 2022, we announced our intention to establish a commercial presence in six additional markets in Europe and four additional markets in Asia.
To date, our COVID-19 vaccine has been sold to government customers and international purchasing organizations, such as Gavi, on behalf of the COVAX Facility, and the African Union. We anticipate that most of our COVID-19 vaccine sales in 2022 will continue
Table of Content
to be pursuant to government contracts and these international purchasing organizations. We expect future sales to private customers if and as we gain marketing approval in various jurisdictions.
In addition, during 2021, we announced agreements in principle with the Canadian and Australian governments to establish mRNA manufacturing facilities in those countries, pursuant to which we would enter into long-term supply agreements for mRNA vaccines. See “Manufacturing” above for further detail.
THIRD-PARTY STRATEGIC ALLIANCES
Strategic alliances
To accelerate the discovery and advancement of potential mRNA medicines across therapeutic areas, we have entered into, and intend to seek other opportunities to form, alliances with a diverse group of strategic collaborators. We have forged productive strategic alliances with pharmaceutical and biotechnology companies, government agencies, academic laboratories, foundations and research institutes with therapeutic area expertise and resources. Through our collaborations, we seek to advance our discovery and development programs, while leveraging our platform and our research and early development capabilities. We also seek to partner with and invest in companies developing other types of therapeutics, such as gene editing and cell-therapy, where we believe we can leverage our core mRNA and LNP capabilities to expand the reach of our technology.
Through certain of our strategic alliances, we share the rewards and risks of developing a new mRNA modality or program, where we may have early research data and desire a strategic collaborator to join us in advancing early development candidates within such modality into the clinic. Representative relationships and associated programs include those with:
-
AstraZeneca** for the VEGF-A program (AZD8601) in the localized regenerative therapeutics modality, and the IL-12 program (MEDI1191) in the intratumoral immuno-oncology modality;
-
Merck** for the personalized cancer vaccine program (mRNA-4157) in the cancer vaccines modality; and
-
Vertex** for the cystic fibrosis (CF) program (VXc-522) in the inhaled pulmonary therapeutics modality.
We view strategic alliances as important drivers for accelerating execution of our goal of rapidly developing mRNA medicines to treat patients across a wide range of medical and disease challenges. To maintain the integrity of our platform, the terms of our agreements with our strategic collaborators generally provide that either we receive rights to develop and commercialize potential mRNA medicines that we design and manufacture or our strategic collaborators receive rights to develop and commercialize potential mRNA medicines that we design and manufacture, as opposed to granting rights to our strategic collaborators to use our platform to generate new mRNA technologies, and that we generally own mRNA-related intellectual property arising from research activities performed under the strategic alliance. We plan to continue to identify potential strategic collaborators who can contribute meaningful technology and insights to our programs and allow us to more rapidly expand our impact to broader patient populations.
Below are brief descriptions of certain of our collaborations. For additional information on these relationships, including their ongoing financial and accounting impact on our business, please see Note 5, Collaboration Agreements, to our consolidated financial statements included in this Annual Report on Form 10-K.
AstraZeneca (Nasdaq: AZN)—Strategic Alliances in Cardiovascular and Oncology
We have two ongoing strategic alliances with AstraZeneca. Pursuant to the first collaboration, which was established in 2013 and amended and restated in 2018, we granted AstraZeneca certain exclusive rights and licenses to research, develop and commercialize potential mRNA medicines directed at certain targets for the treatment of cardiovascular and cardiometabolic diseases and cancer, and agreed to provide related services to AstraZeneca. Our localized VEGF-A program (AZD8601) is being developed by AstraZeneca pursuant to this alliance.
Pursuant to our second strategic alliance with AstraZeneca, which was established in 2016, we agreed to collaborate to discover, develop and commercialize potential mRNA medicines in a range of cancers. We and AstraZeneca have agreed to work together on an immune-oncology program focused on the intratumoral delivery of a potential mRNA medicine to make the IL-12 protein, and our IL-12 program (MEDI1191) is being developed in collaboration with AstraZeneca pursuant to this alliance.
Merck (NYSE: MRK)—Strategic Alliances in Infectious Diseases and Cancer Vaccines
We have established a multi-faceted relationship with Merck Sharp & Dohme Corp. (Merck) that includes distinct strategic alliances directed to the research, development, and commercialization of mRNA medicines for the prevention and treatment of viral infections and for the treatment of cancer.
Table of Content
2016 Cancer Vaccine Strategic Alliance—Personalized mRNA Cancer Vaccines with Merck
In June 2016, we entered into a personalized mRNA cancer vaccines (PCV) Collaboration and License Agreement with Merck (PCV Agreement) to develop and commercialize PCVs for individual patients using our mRNA vaccine and formulation technology. Under the strategic alliance, we identify genetic mutations present in a particular patient’s tumor cells, synthesize mRNA for these mutations, encapsulate the mRNA in one of our proprietary LNPs and administer to each patient a unique mRNA cancer vaccine designed to specifically activate the patient’s immune system against her or his own cancer cells.
Pursuant to the PCV Agreement, we are responsible for designing and researching PCVs, providing manufacturing capacity and manufacturing PCVs, and conducting Phase 1 and Phase 2 clinical trials for PCVs, alone and in combination with KEYTRUDA (pembrolizumab), Merck’s anti-PD-1 therapy, all in accordance with an agreed upon development plan and budget.
2018 Expansion of the Cancer Vaccine Strategic Alliance with Merck—Shared Neoepitope Cancer Vaccines
In April 2018, we and Merck agreed to expand our cancer vaccine strategic alliance to include the development and commercialization of our KRAS vaccine development candidate, mRNA-5671, and potentially other shared neoantigen mRNA cancer vaccines (SAVs). We preclinically developed mRNA-5671 prior to its inclusion in the cancer vaccine strategic alliance and it is comprised of a novel mRNA construct designed by us and encapsulated in one of our proprietary LNPs. The PCV Agreement was amended and restated to include the new SAV strategic alliance (PCV/SAV Agreement). We have regained all rights to our KRAS vaccine (mRNA-5671) from Merck and we are evaluating next steps for the program.
Vertex (Nasdaq: VRTX)—2016 Strategic Alliance in Cystic Fibrosis
In July 2016, we entered into a Strategic Collaboration and License Agreement (Vertex Agreement) with Vertex Pharmaceuticals Incorporated, and Vertex Pharmaceuticals (Europe) Limited (together, Vertex). The Vertex Agreement is aimed at the discovery and development of potential mRNA medicines for the treatment of cystic fibrosis (CF) by enabling cells in the lungs of people with CF to produce functional cystic fibrosis transmembrane conductance regulator (CFTR) proteins.
Vertex —2020 Strategic Alliance in Cystic Fibrosis
In September 2020, we entered into a new Strategic Collaboration and License Agreement with Vertex (Vertex 2020 Agreement). The Vertex 2020 Agreement is aimed at the discovery and development of potential medicines to treat CF by delivering gene-editing therapies to lung cells to facilitate production of functional CFTR proteins.
The three-year research period of the Vertex 2020 Agreement will initially focus on the identification and optimization of novel LNPs and mRNAs that can deliver gene-editing therapies to cells in the lungs. Following the initial three-year period, Vertex is responsible for conducting development and commercialization activities for candidates and products that arise from the strategic alliance, including the costs associated with such activities. Vertex is also obligated to pay us for research services in connection with our performance of certain activities in accordance with a jointly agreed research plan. Subject to customary “back-up” supply rights granted to Vertex, under the agreement, we are the exclusive manufacturer of related mRNA and LNPs for preclinical, clinical, and commercialization purposes.
Other Collaborations
Chiesi—2020 Collaboration and License Agreement with Chiesi
In September 2020, we entered into a Collaboration and License Agreement (Chiesi Agreement) with Chiesi Farmaceutici S.P.A. (Chiesi). The Chiesi Agreement is aimed at the discovery and development of potential mRNA medicines for the treatment of pulmonary arterial hypertension (PAH), a rare disease characterized by high blood pressure in the arteries of the lungs.
Metagenomi—2021 Collaboration for Next-Generation In Vivo Gene Editing Therapeutics
In November 2021, we entered into a strategic research and development collaboration with Metagenomi, Inc. (Metagenomi) focused on advancing new gene editing systems for in vivo human therapeutic applications. The collaboration intends to utilize Metagenomi’s novel gene editing tools and leverage our mRNA platform, as well as LNP delivery technologies, with the goal of developing curative therapies for patients with serious genetic diseases. Under the terms of the collaboration, we and Metagenomi have agreed to advance a series of in vivo gene editing therapeutics against undisclosed targets. We agreed to pay Metagenomi an up-front cash payment and make an equity investment in Metagenomi in the form of a convertible note. Metagenomi is eligible to receive certain target option exercise fees as well as certain milestone payments, plus tiered royalties on net sales of any products that are commercialized by us under the agreement.
Table of Content
Carisma Therapeutics—2022 Collaboration For In Vivo CAR-M Therapeutics
In January 2022, we entered into a new strategic collaboration agreement with Carisma Therapeutics, Inc. (Carisma) to discover, develop and commercialize in vivo engineered chimeric antigen receptor monocyte (CAR-M) therapeutics for the treatment of cancer, including solid tumors. Under the terms of the agreement, we agreed to pay Carisma an up-front cash payment and make an equity investment in Carisma in the form of a convertible note. Carisma will receive research funding and is eligible to receive certain milestone payments, plus tiered royalties on net sales of any products that are commercialized by us under the agreement. Carisma will be responsible for the discovery and optimization of development candidates while we will lead the clinical development and commercialization of therapeutics resulting from the agreement. We have the option to nominate up to twelve targets for development and commercialization.
Strategic alliances with government organizations and foundations
Defense Advanced Research Projects Agency (DARPA)
In October 2013, DARPA awarded us up to approximately $25 million under Agreement No. W911NF-13-1-0417 to research and develop potential mRNA medicines as a part of DARPA’s Autonomous Diagnostics to Enable Prevention and Therapeutics (ADEPT) program, which is focused on assisting with the development of technologies to rapidly identify and respond to threats posed by natural and engineered diseases and toxins. As of December 31, 2021, $20 million of the award amount has been funded. This award followed an initial award from DARPA given in March 2013 under Agreement No. W31P4Q-13-1-0007. The DARPA awards have been deployed primarily in support of our vaccine and antibody programs to protect against Chikungunya infection. Although our antibody against Chikungunya virus (mRNA-1944) had positive Phase 1 readouts, we do not have plans to advance to a Phase 2 study.
In September 2020, we entered into an agreement with DARPA for an award of up to $56 million to fund development of a mobile manufacturing prototype leveraging our existing manufacturing technology that is capable of rapidly producing vaccines and therapeutics. As of December 31, 2021, the committed funding, net of revenue earned was $2 million, with an additional $42 million available under Agreement No. HR0011-20-9-0118 if DARPA exercises additional contract options.
Biomedical Advanced Research and Development Authority (BARDA)
In September 2016, we received an award of up to approximately $126 million under Agreement No. HHSO100201600029C from BARDA, a component of the Office of the Assistant Secretary for Preparedness and Response (ASPR), within the U.S. Department of Health and Human Services (HHS), to help fund our Zika vaccine program. Under the terms of the agreement with BARDA, an initial base award of approximately $8 million supported toxicology studies, a Phase 1 clinical trial, and associated manufacturing activities. Additionally, four contract options were awarded under the agreement with BARDA. Three out of four of these options have been exercised, bringing the total current award to approximately $117 million to support an additional Phase 1 study of an improved Zika vaccine candidate, Phase 2 and Phase 3 clinical studies, as well as large-scale manufacturing for the Zika vaccine.
In April 2020, we entered into an agreement with BARDA for an award of up to $483 million to accelerate development of mRNA-1273, our COVID-19 vaccine. In July 2020, we amended our agreement with BARDA to provide for an additional commitment of up to $472 million to support late-stage clinical development of mRNA-1273, including the execution of a 30,000 participant Phase 3 study in the U.S. We further amended the agreement in March 2021 to provide for an additional commitment of $63 million to further support late-stage clinical development, including Phase 2/3 mRNA-1273 pediatric studies. In April 2021, we entered into a further amendment to the BARDA agreement, increasing the amount of potential reimbursements by $236 million in connection with costs associated with the Phase 3 clinical trials for mRNA-1273 and pharmacovigilance efforts. In June 2021, the agreement was further amended to award additional funding of $144 million to support pediatric clinical trials for mRNA-1273. The maximum award from BARDA, inclusive of the 2020 and 2021 amendments, is $1.4 billion. Under the terms of the agreement, BARDA will fund the advancement of mRNA-1273 to FDA licensure. All contract options have been exercised. As of December 31, 2021, the remaining available funding net of revenue earned was $189 million.
Institute for Life Changing Medicines (ILCM)
In September 2021, we entered into a collaboration agreement with the ILCM to develop a new mRNA therapeutic (mRNA-3351) for CN-1. Under the terms of the agreement, we agreed to license mRNA-3351 to ILCM with no upfront fees, and without any downstream payments. ILCM will be responsible for the clinical development of mRNA-3351.
Table of Content
The Bill & Melinda Gates Foundation
In January 2016, we entered a global health project framework agreement with the Bill & Melinda Gates Foundation to advance mRNA-based development projects for various infectious diseases. The Bill & Melinda Gates Foundation has committed up to $20 million in grant funding to support our initial project related to the evaluation of antibody combinations in a preclinical setting as well as the conduct of a first-in-human Phase 1 clinical trial of a potential mRNA medicine to help prevent HIV infections. Follow-on projects, which could bring total potential funding under the framework agreement up to $100 million (including the HIV antibody project) to support the development of additional mRNA-based projects for various infectious diseases, can be proposed and approved until the sixth anniversary of the framework agreement, subject to the terms of the framework agreement, including our obligation to grant to the Bill & Melinda Gates Foundation certain non-exclusive licenses.
INTELLECTUAL PROPERTY
We rely on a combination of intellectual property laws, including patent, trademark, copyright and trade secret, as well as confidentiality and license agreements, to protect our intellectual property and proprietary rights.
Protecting our platform, modality, and program investments: Building an expansive, multi-layered IP estate
We have built a substantial IP estate that includes numerous patents and patent applications related to the development and commercialization of mRNA vaccine and therapeutic development candidates, including related platform technologies. Our platform IP protects advances in mRNA design and engineering, proprietary LNP components, delivery systems, processes for the manufacture and purification of drug substances and products, and analytical methods. A significant portion of our platform IP estate further provides multi-layered protection for our modalities and programs.
With respect to our IP estate, our solely-owned patent portfolio consists of more than 170 issued or allowed U.S. patents or patent applications and more than 110 granted or allowed patents in jurisdictions outside of the U.S. (including granted European patents that have been validated in numerous European countries) covering certain of our proprietary platform technology, inventions, and improvements, and covering key aspects of our clinical and most advanced development candidates. We have over 430 additional pending patent applications that, in many cases, are counterparts to the foregoing U.S. and foreign patents.
Most of the patents and applications (if issued) in our portfolio will not expire until 2033 at the earliest. Any patent that may issue from our most recently filed patent applications is projected to expire between 2042 and 2043, at the earliest. We file additional U.S. and foreign patent applications as necessary to protect our evolving intellectual property position.
We also rely on trademarks, copyright, trade secrets, and know-how relating to our proprietary technology and programs, continuing innovation, and in-licensing opportunities to develop, strengthen, and maintain our proprietary position in the field of mRNA therapeutic and vaccine technologies. We take additional steps, such as entering into confidentiality and license agreements, to protect our intellectually property and proprietary rights. We additionally plan to rely on data exclusivity, market exclusivity, and patent term extensions when available, and plan to seek and rely on regulatory protection afforded through orphan drug designations. We also possess substantial proprietary know-how associated with related manufacturing processes and expertise.
IP protecting our platform
We have a broad IP estate covering key aspects of our platform. This estate provides multiple layers of protection covering the making and use of the mRNA drug substance and delivery technologies.
With respect to our platform, we have a portfolio that includes U.S. and foreign patents or patent applications covering platform innovations that are directly related to the design, formulation and manufacturing of mRNA medicines. For example, these patents and patent applications include claims directed to:
-
mRNA chemistry imparting improved properties for vaccine and therapeutic uses;
-
methods for mRNA sequence optimization to enhance the levels and fidelity of proteins expressed from our mRNA medicines;
-
methods for identifying epitopes having superior suitability in cancer vaccine contexts;
-
engineering elements tailored to enhance stability and the in vivo performance of mRNA medicines;
-
LNP delivery systems, including novel lipid components designed for optimal expression of both therapeutic and vaccine mRNAs, in particular, prophylactic infectious disease and cancer vaccine mRNAs, intratumoral immuno-oncology therapeutics, local regenerative therapeutics, systemic therapeutics, and inhaled pulmonary therapeutics; and
-
innovative processes for the manufacture and analysis of mRNA drug substance and formulated drug product.
Table of Content
IP protection for modalities
Our IP estate provides protection for the multiple programs within our modalities both at the product-specific level and at various broader levels. For example, we have patent coverage for LNP-encapsulated mRNAs having specific chemical modification suited for vaccine and therapeutic mRNA use. Our estate also includes IP covering certain LNP-encapsulated mRNAs coding for infectious disease antigens for use in prophylactic vaccination. Our mRNA chemistry, formulation and manufacturing patent applications and related know-how and trade secrets may also provide us with additional IP protection relating to our development candidates.
Prophylactic vaccines
For programs within our prophylactic vaccines modality, we typically pursue patent protection featuring composition of matter and method of use claims. Our global patent protection strategy may vary based on the unique geographic prevalence of various infectious diseases.
We have filed several patent applications covering our COVID-19 vaccine program. Claims covering mRNA-1273, which is a LNP-encapsulated mRNA encoding prefusion-stabilized Spike protein antigen, and claims to methods of vaccinating subjects against SARS-CoV-2 infection using our vaccine are featured in several patent families that includes four pending PCT applications, a pending U.S. patent application, and foreign patent applications filed in Argentina and Taiwan. Priority dates for these applications span a period from late January through late May 2020. The U.S. government has rights in certain of the foregoing patent applications. A further pending PCT application includes claims covering our variant-specific COVID-19 vaccines. Protection for mRNA-1283 can be found in a PCT application and three pending U.S. provisional patent applications. Two additional U.S. provisional patent applications include claims covering our COVID-19 and seasonal flu combination vaccine.
Issued U.S. Patent No. 10,702,600 includes claims to LNP-encapsulated mRNA encoding betacoronavirus spike protein. Issued U.S. patent 10,933,127 includes claims to methods of using such compositions to elicit an immune response in subjects. Corresponding vaccine composition and method of use claims are also featured in a pending European patent application. These patents and applications enjoy an October 2015 priority date.
Further coverage for our COVID-19 vaccine and many of our other prophylactic vaccines is found in a broad, infectious disease vaccine patent family featuring claims to LNP-encapsulated mRNAs encoding infectious disease antigens and methods using such compositions for vaccination. This patent family includes two issued U.S. patents, two pending U.S. patent applications and pending patent applications in Europe, Canada, Australia, Brazil, China, Hong Kong, India, Japan, Russia, and Singapore. Issued U.S. Patent Nos. 10,022,435 and 10,709,779 feature claims directed to methods of vaccinating subjects against infection with LNP-encapsulated mRNAs encoding infectious disease antigens.
Patent coverage for our human CMV vaccine, which includes mRNAs encoding several surface glycoproteins of the CMV virus, can be found in pending applications in Australia, Canada, Europe and in both a granted patent and pending patent application in Japan. In the United States, our CMV vaccine is covered in a pending U.S. patent application and in issued U.S. Patent Nos. 10,064,935, 10,383,937 and 10,716,846. Two pending PCT applications and a pending U.S. patent application feature claims to clinical formulations of our CMV vaccine and methods of use.
Patent applications directed to our hMPV/PIV3 vaccine are pending in the United States, Europe and Hong Kong. Five U.S. patents have issued featuring hMPV/PIV3 vaccines with U.S. Patent No. 10,064,934 having claims covering LNP-encapsulated mRNA vaccines that encode the PIV3 and hMPV fusion proteins, U.S. Patent No. 10,272,150 having claims covering administration methods for these LNP-encapsulated mRNA vaccines, U.S. Patent No. 10,543,269 having claims covering vaccines that include HMPV-encoding mRNA formulated in LNPs, U.S. Patent No. 10,702,599 having claims covering vaccines that include PIV3-encoding mRNA formulated in LNPs, and U.S. Patent 11,103,578 having claims covering specific HMPV- and PIV3-encoding mRNAs for use as vaccines. A pending provisional patent application features claims to clinical aspects of our hMPV/PIV3 vaccine. A pending U.S. patent application features claims covering our hMPV/RSV vaccine.
Our Zika mRNA vaccine is covered in a series of patent families directed to mosquito-borne viruses. These patent families include four issued U.S. Patents that cover our Zika vaccines, U.S. Patent Nos. 10,449,244, 10,653,767, 11,007,260 and 11,207,398, and several pending U.S., European and Hong Kong patent applications, one of which is recently allowed and soon to be issued as a U.S. patent, and one of which is recently allowed and soon to be granted as a European patent.
We filed patent applications in several jurisdictions covering RSV vaccines. At least two U.S. and two European patent applications are pending, as are applications in Canada, Australia and several Asian jurisdictions. Also pending are two provisional applications featuring our pediatric RSV vaccine.
A pending PCT patent application and a pending U.S. provisional patent application includes claims covering our vaccine program for the prevention of human infection with seasonal influenza virus. The program also is protected by the broad, infectious disease
Table of Content
vaccine patent family described above, in particular, issued U.S. Patent No. 9,872,900 and granted European Patent EP 3134131, having claims to HA-encoding mRNA vaccine compositions.
Pending patent applications in the United States, Australia, Canada, Europe, and Japan include claims covering our EBV vaccines and methods of use.
We have pending patent applications in the United States and Europe that include claims covering our Nipah vaccine and methods of use, and pending applications in the United States and Europe that include claims covering our HIV vaccine and methods of use.
Cancer vaccines
Composition of matter and method claims also protect programs within our cancer vaccines modality. Proprietary methods around the making and therapeutic use of our personalized cancer vaccines (PCVs) and resulting vaccine compositions are described and claimed in six pending U.S. patent applications, five pending European patent applications, four pending patent applications in each of Australia, Canada, China and Japan, and several pending patent applications in New Zealand, South Africa, as well as other European, Asian and South American countries. Of these patent applications, a U.S. patent application and a Chinese patent application are allowed and soon to be issued. These applications also relate to various vaccine design formats, in particular, polyepitopic vaccine formats, and methods of treating cancer with such personalized cancer vaccines. We also possess substantial know-how and trade secrets relating to the development and commercialization of our cancer vaccine programs, including related manufacturing process and technology.
Likewise, our KRAS antigen cancer vaccine and methods of treating cancer featuring such vaccines are covered in issued U.S. Patent No. 10,881,730, which includes claims to LNP-encapsulated mRNA encoding mutant KRAS antigens, and in a pending U.S. patent application and pending applications in Australia, Canada, Europe, and Japan, as well as in several other European, South American, Asian and Middle Eastern jurisdictions.
Intratumoral immuno-oncology
To protect programs within our intratumoral immuno-oncology modality, we have filed numerous patent applications featuring claims to mRNAs encoding immune-stimulatory proteins and methods of treating cancer using such compositions.
Two of our immuno-oncology programs are designed to be administered intratumorally to alter the tumor microenvironment in favor of mounting an immune response against tumors. Our mRNA program that includes mRNAs that encode OX40L, IL-23 and IL-36γ are covered by a granted European Patent, EP 3394093, by eleven issued U.S. patents, U.S. Patent Nos. 10,143,723, 10,172,808, 10,285,950, 10,322,090, 10,322,091, 10,379,767, 10,383,951, 10,406,113, 11,003,366, 11,071,716 and 11,185,510, by several pending U.S. and European patent applications, two of which are allowed and soon to issue, and by several pending patent applications in foreign jurisdictions including Asian, South American and other jurisdictions. These applications feature claims to the mRNA therapeutics as compositions of matter, formulations that include such mRNAs and methods of reducing tumors and treating cancer featuring these development candidates. Similar claims cover our IL-12 development candidate which can be found in issued U.S. Patent No. 10,646,549, issued U.S. Patent No. 11,000,573, and in pending patent applications in the United States and Europe, two of which are allowed and soon to be issued, and in Australia, Canada, China and Japan, as well as several other jurisdictions in Asia, South America and the Middle East.
Localized regenerative therapeutics
Our localized regenerative therapeutics modality is focused on regenerative therapeutics. Our sole program, VEGF-A, is being developed in collaboration with AstraZeneca and is covered by a granted European patent EP 3464338, granted Japanese patent JP 6859369 and granted Russian patent RU 2756313, and by pending U.S. and European patent applications and by several national phase patent applications filed in South American, Asian and Middle Eastern jurisdictions. The VEGF patent applications are solely-owned by Moderna.
Systemic intracellular therapeutics
Within our systemic intracellular therapeutics modality, we have four programs featuring expression of intracellular enzymes for the treatment of rare diseases. For our rare disease programs, we generally pursue patent protection featuring composition of matter and method of use claims, for example, pharmaceutical composition and method of treatment claims. Our most advanced rare disease development candidate, MMA, is covered by a patent family that includes issued U.S. Patent No. 10,406,112, two pending U.S. patent applications, foreign patent applications filed in Australia, Canada, Japan, Europe and the Middle East, and two pending U.S. Provisional patent applications.
Table of Content
For our PA development candidate, we have patent applications pending in the United States, Canada, Europe, and Japan which cover mRNA encoding the alpha and beta subunits of the enzyme propionyl-CoA carboxylase (PCCA and PCCB, respectively), for the treatment of PA.
For our PKU development candidate, we have a pending PCT and pending patent applications in the U.S., Europe and Japan covering mRNA encoding phenylalanine hydroxylase (PAH) for the treatment of PKU.
For our Glycogen Storage Disorder, Type 1a (GSD1a) development candidate, we have pending U.S and European patent applications, as well as applications pending in Australia, Canada, China, Japan, Israel and several Middle Eastern jurisdictions, and a pending PCT and pending provisional patent applications covering mRNA encoding glucose 6-phosphatase (G6Pase) for the treatment of this disorder.
For our Crigler-Najjar Syndrome Type 1 (CN-1) development candidate, we have patent applications pending in the U.S., Europe, Australia, Canada and Japan.
Any U.S. and foreign patents that may issue from these patent families would be expected to expire in 2036 for the earliest of the MMA patents and 2038-2042 for the remaining MMA, PA, PKU, GSD1a and CN-1 patents, excluding any patent term adjustments and any patent term extensions.
As further described below, we have filed or intend to file patent applications on these and other aspects of our technology and development candidates, and as we continue the development of our intended products, we plan to identify additional means of obtaining patent protection that would potentially enhance commercial success, including protection for additional methods of use, formulation, or manufacture.
Systemic secreted and cell-surface therapeutics
Our systemic secreted and cell-surface therapeutics modality features programs directed to expression of secreted or cell-surface proteins including antibodies, circulating modulation factors, secreted enzymes and transmembrane proteins. Our mRNA-encoded antibody against Chikungunya virus reported positive interim Phase 1 results in clinical trials and utilizes the same LNP formulation being advanced for our MMA program and other rare disease programs. Patent protection for mRNA-encoded antibody against Chikungunya virus is being sought by way of a pending U.S. and European patent applications, in which we share joint ownership rights.
Our Relaxin development candidate is covered by several pending foreign patent applications outside the United States, for example, in several Asian, European, Middle Eastern, South American and other jurisdictions, and by a pending U.S. application and by issued U.S. Patent No. 10,730,924.
Our PD-L1 and IL-2 development candidates are each covered in pending PCT patent applications.
Inhaled pulmonary therapeutics
Our inhaled pulmonary therapeutics modality currently has one development candidate directed to expression of therapeutic protein in the lungs. This Cystic Fibrosis (CF) development candidate is covered by pending U.S., European and PCT patent applications.
Trademarks
Our trademark portfolio currently contains at least 200 trademark registrations, including at least 12 registrations in the United States and the remaining in Canada, the European Union, the United Kingdom, Israel, China, Japan, Australia, and elsewhere. In addition, we have at least 375 pending trademark applications in more than 75 jurisdictions, including in the aforementioned locations and additional countries throughout Africa, Asia, and South America.
In-licensed intellectual property
While we develop and manufacture our potential mRNA medicines using our internally created mRNA technology platform, we also seek out and evaluate third party technologies and IP that may be complementary to our platform.
Patent sublicense agreements with Cellscript and mRNA RiboTherapeutics
The Trustees of the University of Pennsylvania owns several issued U.S. patents, granted European patents and pending U.S. patent applications directed, in part, to nucleoside-modified mRNAs and their uses, or the Penn Modified mRNA Patents. mRNA
Table of Content
RiboTherapeutics, Inc. (MRT) obtained an exclusive license to the Penn Modified mRNA Patents and granted its affiliate, Cellscript, LLC (Cellscript), a sublicense to the Penn Modified mRNA Patents in certain fields of use.
In June 2017, we entered into two sublicense agreements, one with Cellscript, and one with MRT, which agreements we collectively refer to as the Cellscript-MRT Agreements. Together, the Cellscript-MRT Agreements grant us a worldwide, sublicensable sublicense to the Penn Modified mRNA Patents to research, develop, make, and commercialize products covered by the Penn Modified mRNA Patents, or licensed products, for all in vivo uses in humans and animals, including therapeutic, prophylactic, and diagnostic applications. The Cellscript-MRT Agreements are non-exclusive, although Cellscript and MRT are subject to certain time restrictions on granting additional sublicenses for in vivo uses in humans under the Penn Modified mRNA Patents.
We paid Cellscript and MRT aggregate sublicense grant fees of $28 million upon entering into the Cellscript-MRT Agreements, $25 million in early 2018, and $22 million in early 2019. Cellscript and MRT are collectively eligible to receive, on a licensed product-by-licensed product basis, milestone payments totaling up to $0.5 million upon the achievement of certain regulatory-based events for diagnostic products, and milestone payments totaling up to $1.5 million upon the achievement of certain development and regulatory-based events for either therapeutic or prophylactic products, and up to $24 million upon the achievement of certain commercial-based events for either therapeutic or prophylactic products. The Cellscript-MRT Agreements require us to pay royalties based on annual net sales of licensed products at rates in the low single digits for therapeutic, prophylactic, and diagnostic uses, and royalties based on annual net sales of licensed products sold for research uses at rates in the mid-single digits, subject to certain reductions, with an aggregate minimum floor. Following the first commercial sale of licensed products under a Cellscript-MRT Agreement, we are required to pay Cellscript or MRT, as applicable, minimum annual royalties ranging from $10,000 to $400,000 depending on the use of such licensed product, with all such payments creditable against earned royalties on net sales. In 2021, we paid $641 million in royalties and milestone payments to Cellscript in connection with sales of our COVID-19 vaccine.
The Cellscript-MRT Agreements will terminate upon the expiration or abandonment of the last to expire or become abandoned of the Penn Modified mRNA Patents. Cellscript or MRT, as applicable, may terminate its respective Cellscript-MRT Agreement if we fail to make required payments or otherwise materially breach the applicable agreement, subject to specified notice and cure provisions. Cellscript or MRT, as applicable, may also terminate the applicable Cellscript-MRT Agreement upon written notice in the event of our bankruptcy or insolvency or if we challenge the validity or enforceability of the Penn Modified mRNA Patents. We have the right to terminate each Cellscript-MRT Agreement at will upon 60 days’ prior notice to Cellscript or MRT, as applicable, provided that we cease all development and commercialization of licensed products upon such termination. If rights to MRT or Cellscript under the Penn Modified mRNA Patents are terminated (e.g., due to bankruptcy of MRT or Cellscript), the terminated party will assign its interest in the respective Cellscript-MRT Agreement to the licensor from which it received rights under the Penn Modified mRNA Patents and our rights will continue under the new licensor.
Formulation technology in-licenses
Our development candidates use internally developed formulation technology that we own. We do, however, have rights to use and exploit multiple issued and pending patents covering formulation technologies under licenses from other entities. If in the future we elect to use or to grant our strategic collaborators sublicenses to use these in-licensed formulation technologies, we or our strategic collaborators may be liable for milestone and royalty payment obligations arising from such use. We consider the commercial terms of these licenses and their provisions regarding diligence, insurance, indemnification and other similar matters, to be reasonable and customary for our industry.
HUMAN CAPITAL
We had approximately 2,700 full-time employees as of December 31, 2021, representing a more than doubling of our workforce from 1,300 full-time employees as of the end of the prior year. We have undertaken significant hiring of employees to facilitate manufacturing of our COVID-19 vaccine, in addition to building out our commercial and regulatory organizations, as well as other functions, to support this continued roll-out. We also increased our hiring outside the United States during 2021, and at year-end we had employees in 12 countries around the world, with a presence in North America, Europe and the Asia-Pacific region. Much of this hiring has been of talent with experience at other pharmaceutical companies as we continue to build out our commercial and regulatory capabilities, particularly as we fill roles to facilitate our operations and commercial activities in markets around the globe. We have also continued to hire talent to support our research and clinical capabilities across the rest of our pipeline, unrelated to our COVID-19 vaccine.
We operate in a highly competitive environment for human capital, particularly as we seek to attract and retain talent with experience in the biotechnology and pharmaceutical sectors. Our workforce is highly educated, and as of December 31, 2021, 47% of our employees hold Ph.D., Doctorate, M.D., J.D., or Master’s degrees. Among our employees, as of December 31, 2021, 47% are female. Among our leadership (which we define as employees at the vice president level and above), as of December 31, 2021, approximately 39% are female, an increase from 37% in the prior year. 40% of our U.S. employees identify as racially or ethnically diverse as of
Table of Content
December 31, 2021, an increase from 35% in the prior year. In 2021, we continued to act on our commitment to belonging, inclusion & diversity by, among other things:
-
engaging all members of our Executive Committee, vice presidents and managers in our Conscious Inclusion education series;
-
conducting diversity-related events, celebrations and learning opportunities for all employees throughout the year, including Pride Month, Hispanic Heritage Month and Asian & Pacific Islander Month;
-
hosting a company-wide event on Neurodiversity in line with the CEO Action of Diversity & Inclusion’s #DayofUnderstanding;
-
increased our monitoring and reporting program regarding company-wide gender and ethnicity data;
-
doubling the number of our Employee Resource Groups; and
-
joining the Disability:IN Inclusion Works Program, an initiative that assists employers in all aspects of disability inclusion at work.
To help promote alignment between our employees and our shareholders, all employees participate in our equity programs through the receipt of equity grants, and the percentage of equity as a component of overall pay mix increases with seniority. We believe that in addition to incentivizing growth that leads to shareholder value, broad eligibility for our equity programs helps promote employee retention as these awards generally vest over a four-year period.
Throughout the COVID-19 pandemic, we have implemented various initiatives to promote the safety of our workforce and continuity of our operations. We created a Coronavirus Response Team that is responsible for implementing various safety measures at our global sites. Our protocols include regular COVID-19 testing and the provision personal protective equipment (PPE). Throughout the pandemic, much of our workforce has worked remotely, wherever possible and when local conditions recommend social distancing. We also implemented remote hiring and onboarding programs to facilitate significant hiring during 2021 in a remote work environment.
Since October 2021, we have required all of our employees in the United States to be vaccinated against COVID-19, including having received a booster dose, absent an approved medical or religious accommodation. In December 2020, following the receipt of an Emergency Use Authorization from the FDA for our COVID-19 vaccine, we made the vaccine available to our employees and adult members of their households to help ensure continuity of our operations due to the critical nature of our production of the vaccine. In December 2021 and early 2022, as the Omicron variant drove a surge in COVID-19 cases globally, we made booster doses of our vaccine available to our U.S.-based employees and adult members of their households, as well as to employees of our Swiss subsidiary.
None of our employees are represented by a labor union, and none of our employees have entered into a collective bargaining agreement with us, other than a small number of employees in France, Italy and Spain who are covered by collective bargaining agreements governing certain benefits and working conditions. We consider our employee relations to be good.
We believe that our employees are highly engaged, and we and our employees have been recognized by surveys conducted by external groups. Science magazine ranked us as a top employer for each of the last seven years. Additionally, in 2021, Biospace ranked us the number one employer in its 2022 Best Places to Work in Biopharma report and Fast Company named us the number one company on its 2021 Best Workplaces for Innovators list. We measure employee engagement through a vendor-supplied engagement software, using validated external benchmarks to track quarter-over-quarter employee engagement factors.
Our approach to attracting and retaining talent
We are committed to ensuring that our employees find that their careers at Moderna are filled with purpose, growth and fulfillment. We believe that a career at Moderna provides opportunity for:
-
Impact**: Our people will have the opportunity to do work that is unparalleled in terms of its innovation and scope of impact on people’s lives.
-
Growth**: We provide incredible opportunities for growth and we obsess over learning (as demonstrated, in part, by our Mindsets (see below)). We invest in the development of our people as scientists and as leaders.
-
Well-being**: We are committed to the health and well-being of our employees and their families by providing family-friendly benefits and opportunities to be healthy, including annual allowances for personal enrichment and monthly allowances for fitness and nutrition.
-
Inclusive environment**: We believe in the benefits of bringing together a diverse set of perspectives and backgrounds, and creating an environment where differences are celebrated and leveraged.
-
Compelling rewards**: To attract and retain the best talent, we provide competitive rewards that help to drive groundbreaking work and allow employees to share in the value we will create together, including through our equity programs.
Table of Content
Our approach to training our employees
We have established a structured training curriculum for our employees called Moderna University and have a full-time team dedicated to developing the curriculum and conducting activities for Moderna University. The objective of Moderna University is for every employee to be deeply familiar with our core technology and able to learn about technologies that might further enable our science. In addition, Moderna University is also focused on creating strong leaders through management and leadership training. There are four core areas within Moderna University including:
-
Professional development**: Includes on-site training programs for our employees including those focused on leadership and project management, as well as tools to improve interpersonal communication.
-
Digital learning library**: We have built an online library of videos of a variety of scientific material that our employees can access flexibly. This content includes:
◦Presentations by external speakers to scientific seminars conducted in-house;
◦Scientific courses at external universities; and
◦Peer-to-peer video series in which in-house experts provide an introductory view of complex topics they tackle within their teams.
-
Learning management system**: We have deployed a digital system to track and administer training programs for each of our employees. Training content is developed digitally and offered to our employees.
-
New hire orientation**: This program is designed to onboard all new employees. During this training program, new employees meet with members of the management team and senior functional leaders to learn about the Company and functional activities.
In December 2021, we announced the launch of our Artificial Intelligence (AI) Academy in partnership with Carnegie Mellon University. The AI Academy is intended to educate and empower our workforce to identify and integrate AI and machine learning solutions into our systems and processes.
Additionally, with the continued rapid growth of our company, we articulated the Moderna Mindsets in late 2021. The Moderna Mindsets are a set of leadership behaviors we use to make decisions and lead the company. We consider the Mindsets to be key as our company continues to scale, and we are working to integrate them into all of our HR processes, including performance management. Our employees participate in the Mindsets Workshops, which is an interactive, full-immersion learning experience designed to provide the opportunity to engage with, better understand and learn how to apply the Mindsets in the workplace.
To further develop and retain our workforce, we conduct periodic talent reviews that identify key talent within the organization. We use that data to inform specific development opportunities for key current and potential future leaders, and to support our periodic succession planning activities for key roles. These steps together ensure we have a robust understanding of our workforce and a talent pipeline to grow future leaders.
CORPORATE SOCIAL RESPONSIBILITY
In pursuit of our mission to deliver on the promise of mRNA science to create a new generation of transformative medicines for patients, we have scaled our operations, invested in research and building out our manufacturing and commercial capabilities, and hired top-tier talent. As we continue to mature, we believe it is important to develop long-term programs that underscore our commitment to corporate social responsibility. Please refer to the “Responsibility” section of our website, which can be found at www.modernatx.com, as well as our proxy statement related to our 2022 Annual Meeting of Stockholders that we will file with the SEC, for a description of some of the measures we have taken to support our commitment to corporate social responsibility.
COMPETITION
The biotechnology and pharmaceutical industries utilize rapidly advancing technologies and are characterized by intense competition. There is also a strong emphasis on defense of intellectual property and proprietary products.
mRNA Medicines and Our COVID-19 Vaccine
We believe that mRNA as a medicine coupled with our capabilities across mRNA technology, drug discovery, development, and manufacturing provide us with a competitive advantage. However, we face competition from others developing mRNA vaccines and therapeutics, as well as other medicines that compete or could compete with our mRNA products, development candidates and investigational medicines. We face competition from various sources, including large pharmaceutical companies, biotechnology companies, academic institutions, government agencies, and public and private research institutions. For any products that we eventually commercialize, we will not only compete with existing medicines but also compete with medicines that may become available in the future. We also face competition when entering into strategic alliances to advance and grow our pipeline.
Table of Content
We face significant competition in the market for our COVID-19 vaccine, particularly from established pharmaceutical companies with longer operating histories and significant experience in producing and marketing pharmaceutical products. In the United States, the U.S. FDA has granted a BLA to the Pfizer/BioNTech COVID-19 vaccine for the prevention of COVID-19 in individuals 16 years of age and older. The Pfizer/BioNTech COVID-19 vaccine has also been authorized under an EUA as a two-dose primary series for individuals five years of age and older, as a third primary series dose for individuals five years of age and older who have been determined to have certain kinds of immunocompromise, and as a single booster dose for individuals 12 years of age and older at least five months after completing a primary series of the vaccine. The Pfizer/BioNTech COVID-19 vaccine has also been authorized for use as a single booster dose for individuals 18 years of age and older following completion of primary vaccination with a different available COVID-19 vaccine. The CDC has recommended that individuals starting their COVID-19 vaccine series or receiving a booster dose receive either our COVID-19 vaccine or the Pfizer/BioNTech COVID-19 vaccine. The Johnson & Johnson/Janssen viral vector COVID-19 vaccine is also authorized under an EUA. Outside the United States, our COVID-19 vaccine has been authorized for use or approved in more than 70 countries, in addition to receiving authorization from the World Health Organization. In many of these jurisdictions, our vaccine is authorized for use in adolescents (ages 12-17). Internationally, our COVID-19 vaccine competes against over two dozen vaccines that have been authorized in various jurisdictions, and many other vaccine candidates remain in development, including other mRNA vaccines.
Additionally, competitors have developed treatments for COVID-19, and additional treatments may be developed in the future. For example, Pfizer and Merck have developed antiviral pills for the treatment of mild-to-moderate COVID-19 disease for certain adults who have tested positive for COVID-19. To the extent that these or other treatments are viewed as an alternative to vaccination against COVID-19, our competitive position could be harmed.
Competition for the sale of our COVID-19 vaccine can be impacted by a number of factors, including: the efficacy of our vaccine in preventing COVID-19 (particularly in the prevention of severe cases of COVID-19); the ability of our vaccine, or future iterations of the vaccine, and boosters to protect effectively against variants of the SARS-CoV-2 virus; perceptions of the efficacy of our vaccine; concerns about potential side effects from the vaccine, its safety or tolerability; the novelty of mRNA-based technology; storage and handling conditions for our vaccine and the ease or difficulty with which it can be distributed; the timing and scope of regulatory approvals; reimbursement coverage; our costs to produce and distribute our vaccine; and our ability to scale our manufacturing and distribution effectively as we continue to expand shipments internationally. The competitiveness of our COVID-19 vaccine in the future may also depend upon whether we are successful in efforts to combine the vaccine with other vaccines, like seasonal flu and RSV, and whether our competitors are successful in similar efforts. Additionally, standalone vaccines we may develop for respiratory diseases, such as seasonal flu vaccines, will face competition from existing vaccines and treatments, as well as future medicines developed by competitors. Our competitive positioning may also be affected by the fact that we do not have as long a history of producing pharmaceutical products or existing commercial relationships compared to certain of our competitors.
There are additional companies that are working on mRNA medicines, some of which have reached commercialization. Companies with mRNA programs include BioNTech and Pfizer (alone and in partnership with BioNTech and others). Other competitors include Sanofi (through the acquisition of Translate Bio), CureVac and GlaxoSmithKline, Arcturus Therapeutics, eTheRNA Immunotherapies Ethris, Genevant Sciences, Stemirna Therapeutics and Abogen Biosciences, which is developing a COVID-19 mRNA vaccine in collaboration with Walvax Biotechnology and the PLA Academy of Military Science. We also compete against other pharmaceutical companies in the market for COVID-19 vaccines that do not utilize mRNA-based technologies, including AstraZeneca and Johnson & Johnson, among others.
Beyond mRNA
We and our strategic collaborators face competition from companies developing therapies in various areas, other than the development of mRNA medicines, related to our collaborations. For example, there are a growing number of pharmaceutical, biotechnology and academic institutions researching and developing autologous and allogeneic CAR-T therapies in both the solid and liquid tumor setting. These CAR-T cell therapies are at various stages of development and approval and could compete against any CAR-T therapeutics we discover, develop and commercialize in collaboration with Carisma Therapeutics.
Similarly, there are many companies and institutions researching and developing CRISPR and other gene editing systems, which could compete against any therapies for genetic diseases we develop and commercialize in collaboration with Metagenomi or other collaborators.
GOVERNMENT REGULATION
Government authorities in the United States at the federal, state and local level and in other countries regulate, among other things, the research, development, manufacture and marketing of our products and product candidates. Generally, before a new drug or biologic can be marketed, considerable data demonstrating its quality, safety and efficacy must be obtained and submitted for review and approved by the regulatory authority.
Table of Content
U.S. drug and biological product development
In the United States, the FDA regulates drugs under the Federal Food, Drug, and Cosmetic Act (FDCA) and its implementing regulations and biologics under the FDCA, the Public Health Service Act (PHSA), and their implementing regulations. Both drugs and biologics also are subject to other federal, state and local statutes and regulations. Failure to comply with applicable U.S. requirements at any time during the product development process, approval process or following approval may subject an applicant to administrative or judicial sanctions. These sanctions could include, among other actions, the FDA’s refusal to approve pending applications, withdrawal of an approval, license revocation, a clinical hold, untitled or warning letters, voluntary or mandatory product recalls, market withdrawals, product seizures, total or partial suspension of production or distribution, injunctions, fines, refusals of government contracts, restitution, disgorgement and civil or criminal penalties. Any agency or judicial enforcement action could have a material adverse effect on us.
Any of our investigational medicines must be approved by the FDA through a BLA or new drug application, NDA, process before they may be legally marketed in the United States. The preclinical and clinical testing and approval process requires substantial time, effort and financial resources, and we cannot be certain that any approvals for our current or future investigational medicines will be granted on a timely basis, or at all.
Preclinical studies
Before any of our product candidates may be tested in humans, the product candidate must undergo rigorous preclinical testing. Preclinical studies include laboratory evaluation of product chemistry and formulation, as well as in vitro and animal studies to assess the potential for adverse events and in some cases to establish a rationale for therapeutic use. The conduct of preclinical studies is subject to federal regulations and requirements, including GLP regulations for safety/toxicology studies. An IND sponsor must submit the results of the preclinical tests, together with manufacturing information, analytical data, any available clinical data or literature and plans for clinical studies, among other things, to the FDA as part of an IND. An IND is a request for authorization from the FDA to administer an investigational product to humans and must become effective before human clinical trials may begin. Unless the FDA raises concerns, an IND automatically becomes effective 30 days after receipt by the FDA. In such a case, the IND sponsor and the FDA must resolve any outstanding concerns before the clinical trial can begin.
Clinical trials
The clinical stage of development involves the administration of the investigational product to healthy volunteers or patients under the supervision of qualified investigators and in accordance with GCP requirements. Clinical trials are conducted under protocols detailing, among other things, the objectives of the clinical trial, dosing procedures, subject selection and exclusion criteria and the parameters to be used to monitor subject safety and assess efficacy. Each protocol, and any subsequent amendments to the protocol, must be submitted to the FDA as part of the IND. Furthermore, each clinical trial must be reviewed and approved by an IRB for each institution at which the clinical trial will be conducted to ensure that the risks to individuals participating in the clinical trials are minimized and are reasonable in relation to anticipated benefits. The IRB also approves the informed consent form that must be provided to clinical trial subjects and monitors the clinical trial until completed. Further, progress reports detailing the results of the clinical trials, among other information, must be submitted at least annually to the FDA and more frequently in other situations, including the occurrence of serious adverse events. Information about certain clinical trials must be submitted within specific timeframes for publication on the www.clinicaltrials.gov website.
Under the U.S. National Institutes of Health Guidelines for Research Involving Recombinant DNA Molecules (the NIH Guidelines), supervision of human gene transfer trials includes evaluation and assessment by an institutional biosafety committee (IBC), a local institutional committee that reviews and oversees research utilizing recombinant or synthetic nucleic acid molecules at that institution. While the NIH Guidelines are only mandatory for research being conducted at or sponsored by institutions receiving NIH funding of recombinant or synthetic nucleic acid molecule research, many companies and other institutions not otherwise subject to the NIH Guidelines voluntarily follow them.
Foreign studies conducted under an IND must meet the same requirements that apply to studies being conducted in the United States. Data from a foreign study not conducted under an IND may be submitted in support of a BLA if the study was conducted in accordance with GCP requirements, and the FDA is able to validate the data.
Clinical trials generally are conducted in three sequential phases, which may overlap:
-
Phase 1 clinical trials generally involve a small number of healthy volunteers or disease-affected patients to assess the metabolism, pharmacologic action, side effect tolerability, and safety of the product candidate.
-
Phase 2 clinical trials generally involve studies in disease-affected patients to evaluate proof of concept and/or determine the dosing regimen(s) for subsequent investigations. At the same time, safety and further pharmacokinetic and pharmacodynamic information is collected, possible adverse effects and safety risks are identified, and a preliminary evaluation of efficacy is conducted.
Table of Content
- Phase 3 clinical trials generally involve a large number of patients at multiple sites and are designed to provide the data necessary to demonstrate the effectiveness of the product for its intended use, its safety in use and to establish the overall benefit/risk relationship of the product, and provide an adequate basis for product labeling.
The FDA may also require post-approval Phase 4 non-registrational studies to explore scientific questions to further characterize safety and efficacy during commercial use of a drug.
The FDA or the sponsor may suspend or terminate a clinical trial at any time on various grounds, including a finding that the patients are being exposed to an unacceptable health risk. Similarly, an IRB can suspend or terminate approval of a clinical trial at its institution if the clinical trial is not being conducted in accordance with the IRB’s requirements or if the drug or biologic has been associated with unexpected serious harm to patients. Additionally, some clinical trials are overseen by an independent group of qualified experts organized by the clinical trial sponsor, known as a data safety monitoring board or committee. This group provides authorization for whether a trial may move forward at designated check points based on access to certain data from the trial. Concurrent with clinical trials, companies usually complete additional animal studies and also must develop additional information about the chemistry and physical characteristics of the drug or biologic as well as finalize a process for manufacturing the product in commercial quantities in accordance with cGMP requirements. The manufacturing process must be capable of consistently producing quality batches of the product and, among other things, companies must develop methods for testing the identity, strength, quality, and purity of the final product.
FDA review process
Following completion of the clinical trials, data are analyzed to assess whether the investigational product is safe and effective for the proposed indicated use or uses. The results of preclinical studies and clinical trials are then submitted to the FDA as part of a BLA or NDA, along with proposed labeling, chemistry, and manufacturing information to ensure product quality and other relevant data. A BLA is a request for approval to market a biologic for one or more specified indications and must contain proof of the biologic’s safety, purity, and potency. An NDA for a new drug must contain proof of the drug’s safety and efficacy. To support marketing approval, the data submitted must be sufficient in quality and quantity to establish the safety and efficacy of the investigational product to the satisfaction of the FDA. FDA approval of a BLA or NDA must be obtained before a biologic or drug may be marketed in the United States.
Before approving a BLA or NDA, the FDA will conduct a pre-approval inspection of the manufacturing facilities for the new product to determine whether they comply with cGMP requirements and are adequate to assure consistent production of the product within required specifications. The FDA also may audit data from clinical trials to ensure compliance with GCP requirements. Additionally, the FDA may refer applications for novel products or products which present difficult questions of safety or efficacy to an advisory committee of expert advisors for review, evaluation and a recommendation as to whether the application should be approved and under what conditions, if any. The committee makes a recommendation to the FDA that is not binding but is generally followed.
After the FDA evaluates a BLA or NDA, it will grant marketing approval, request additional information or issue a complete response letter (CRL), outlining the deficiencies in the submission. The CRL may require additional testing or information, including additional preclinical or clinical data, for the FDA to reconsider the application. Even if such additional information and data are submitted, the FDA may decide that the BLA or NDA still does not meet the standards for approval. If the FDA grants approval, it issues an approval letter that authorizes commercial marketing of the product with specific prescribing information for specific indications.
Orphan drug designation
Under the Orphan Drug Act, the FDA may grant orphan designation to a drug or biologic product intended to treat a rare disease or condition, which is generally a disease or condition that affects fewer than 200,000 individuals in the United States, or more than 200,000 individuals in the United States and for which there is no reasonable expectation that the cost of developing and making the product available in the United States for this type of disease or condition will be recovered from sales of the product.
If a product that has orphan designation subsequently receives the first FDA approval for the disease or condition for which it has such designation, the product is entitled to orphan drug exclusivity, which means that the FDA may not approve any other applications to market the same drug for the same indication for seven years from the date of such approval, except in very limited circumstances, such if the latter product is shown to be clinically superior to the orphan product. Orphan drug exclusivity, however, also could block the approval of our products for seven years if a competitor first obtains approval of the same product as defined by the FDA or if our drug candidate is determined to be contained within the competitor’s product for the same indication or disease.
Expedited development and review programs
The FDA may employ one of several tools to facilitate and expedite the development and review of a drug, including fast track designation, breakthrough therapy designation, accelerated approval and priority review designation. Fast track designation is designed to facilitate the development and review of a drug that treats a serious condition and fills an unmet medical need. Breakthrough therapy designation is designed to expedite the development and review of a drug that treats a serious condition and
Table of Content
preliminary clinical evidence demonstrates substantial improvement over available therapies. Priority review designation means the FDA’s goal is to take action on an application within six months of filing. The FDA may grant priority review designation to a drug that would provide significant improvement in the safety or effectiveness of a treatment, diagnosis or prevention of a serious condition.
A product may also be eligible for accelerated approval if it treats a serious or life-threatening condition and generally provides a meaningful advantage over available therapies. In addition, it must demonstrate an effect on a surrogate endpoint that is reasonably likely to predict clinical benefit or on a clinical endpoint that can be measured earlier than irreversible morbidity or mortality (IMM) that is reasonably likely to predict an effect on IMM or other clinical benefit. As a condition of approval, the FDA may require that a sponsor of a drug or biologic receiving accelerated approval perform adequate and well-controlled post-marketing clinical trials. If the FDA concludes that a drug or biologic shown to be effective can be safely used only if distribution or use is restricted, it will require such post-marketing restrictions, as it deems necessary to assure safe use of the product. If the FDA determines that the conditions of approval are not being met, the FDA can withdraw its accelerated approval for such drug or biologic.
Even if a product qualifies for one or more of these programs, the FDA may later decide that the product no longer meets the conditions for qualification or the time period for FDA review or approval may not be shortened. Furthermore, fast track designation, priority review, accelerated approval, and breakthrough therapy designation do not change the standards for approval.
Emergency Use Authorization (EUA)
The Secretary of Health and Human Services (HHS) may authorize unapproved medical products to be marketed in the context of an actual or potential emergency that has been designated by the U.S. government. The COVID-19 pandemic has been designated as such an emergency. After an emergency has been announced, the Secretary of HHS may authorize the issuance of and the FDA Commissioner may issue EUAs for the use of specific products based on certain criteria, including that the product may be effective in diagnosing, treating, or preventing serious or life-threatening diseases when there are no adequate, approved, and available alternatives. From December 18, 2020, our COVID-19 vaccine was available under an EUA for active immunization to prevent COVID-19 in individuals 18 years of age and older. In January 2022, the FDA approved the BLA for our COVID-19 vaccine, Spikevax, to prevent COVID-19 in individuals 18 years of age and older in the United States. A booster dose of our COVID-19 vaccine at the 50 µg dose level is authorized for use under an EUA for adults 18 years and older. A third dose of our COVID-19 vaccine at the 100 µg dose level is authorized for use under an EUA in immunocompromised individuals 18 years of age or older in the United States who have undergone solid organ transplantation, or who are diagnosed with conditions that are considered to have an equivalent level of immunocompromise. An EUA terminates when the emergency determination underlying the EUA terminates. An EUA is not a long-term alternative to obtaining FDA approval, licensure, or clearance for a product. The FDA may revoke an EUA for a variety of reasons, including if the underlying health emergency no longer exists or warrants such authorization.
In the United States, the Public Readiness and Emergency Preparedness Act, the PREP Act, provides immunity for manufacturers from all claims under state or federal law for “loss” arising out of the administration or use of a “covered countermeasure.” However, injured persons may still bring a suit for “willful misconduct” against the manufacturer under some circumstances. “Covered countermeasures” include “qualified pandemic or epidemic products,” including products intended to diagnose or treat pandemic or epidemic disease, such as pandemic vaccines. For these immunities to apply, the Secretary of HHS must issue a declaration in cases of public health emergency or “credible risk” of a future public health emergency. On March 17, 2020, the Secretary of HHS issued a declaration under the PREP Act and has issued subsequent amendments thereto since then to provide liability immunity for activities related to certain countermeasures against the ongoing COVID-19 pandemic. While we believe our products would be covered under the provisions of the PREP Act, this cannot be assured.
Pediatric information
Under the Pediatric Research Equity Act of 2003, all marketing applications for new active ingredients, indications, dosage forms, dosing regimens or routes of administration must contain an assessment of the safety and effectiveness of the product for the claimed indication in pediatric patients unless this requirement is waived, deferred or inapplicable.
Under the Best Pharmaceuticals for Children Act, a product may be eligible for pediatric exclusivity, which adds six months to existing exclusivity periods and patent terms. This exclusivity may be granted based on the voluntary completion of a pediatric study in accordance with an FDA-issued written request for such a study.
Post-approval requirements
Following approval of a new product, the manufacturer and the approved product are subject to continuing regulation by the FDA, including, among other things, monitoring and record-keeping activities, reporting of adverse experiences, complying with promotion and advertising requirements, and limitations on industry-sponsored scientific and educational activities. Although physicians may prescribe legally available products for off-label uses, manufacturers may not market or promote such uses. Prescription drug and biologic promotional materials must be submitted to the FDA in conjunction with their first use. Further, if there are any modifications
Table of Content
to the drug or biologic, including changes in indications, labeling or manufacturing processes or facilities, the applicant may be required to submit and obtain FDA approval of a new BLA or NDA or BLA or NDA supplement, which may require the development of additional data or preclinical studies and clinical trials.
The FDA may also place other conditions on approvals including the requirement for a Risk Evaluation and Mitigation Strategy (REMS) to assure the benefits of the product outweigh the risks. A REMS could include medication guides, physician communication plans, or elements to assure safe use, such as restricted distribution methods, patient registries, and other risk minimization tools. Newly discovered or developed safety or effectiveness data may require changes to a drug’s approved labeling, including the addition of new warnings and contraindications, and also may require the implementation of other risk management measures, including a REMS or the conduct of post-marketing studies to assess a newly discovered safety issue. Product approvals may be withdrawn for non-compliance with regulatory standards, or if problems occur following initial marketing.
FDA regulations require that products be manufactured in specific approved facilities and in accordance with cGMP regulations. We and our third-party manufacturers must comply with cGMP regulations that require, among other things, quality control and quality assurance, the maintenance of records and documentation, and the obligation to investigate and correct any deviations from cGMP. Entities involved in the manufacture and distribution of approved drugs or biologics are required to register their establishments with the FDA and certain state agencies, and are subject to periodic unannounced inspections for compliance with cGMP requirements and other laws. The discovery of violations could result in enforcement actions, and the discovery of problems with a product after approval may result in restrictions on a product, manufacturer, or holder of an approved BLA or NDA, including recall.
U.S. patent term restoration and marketing exclusivity
In certain circumstances, some of our U.S. patents may be eligible for limited patent term extension under the Drug Price Competition and Patent Term Restoration Act of 1984, commonly referred to as the Hatch Waxman Amendments. The Hatch Waxman Amendments permit restoration of the patent term of up to five years as compensation for patent term lost during product development and FDA regulatory review process. Patent term restoration, however, cannot extend the remaining term of a patent beyond a total of 14 years from the product’s approval date. The patent term restoration period is generally one half the time between the effective date of an IND and the submission date of a BLA or NDA, plus the time between the submission date of a BLA or NDA and the approval of that application. Only one patent applicable to an approved drug is eligible for such an extension and the application for the extension must be submitted prior to the expiration of the patent. The USPTO, in consultation with the FDA, reviews and approves the application for any patent term extension or restoration.
If the FDA approves a drug product that contains an active ingredient not previously approved, the product is typically entitled to five years of non-patent regulatory exclusivity. Other products may be entitled to three years of exclusivity if approval was based on the FDA’s reliance on new clinical studies essential to approval submitted by the NDA applicant. If the NDA applicant studies the product for use by children, the FDA may grant pediatric exclusivity, which extends by 180 days each existing exclusivity (patent and regulatory) related to the product.
An abbreviated approval pathway for biological products shown to be biosimilar to, or interchangeable with, an FDA-licensed reference biological product was created by the Biologics Price Competition and Innovation Act of 2009 (the BPCI Act). Biosimilarity requires a showing that the product is “highly similar” to the reference product notwithstanding minor differences in clinically inactive components and that there are no clinically meaningful differences between the product and the reference product in terms of safety, purity, and potency. Interchangeability requires that a biological product be biosimilar to the reference product and that the product can be expected to produce the same clinical results as the reference product in any given patient and, for products administered multiple times to an individual, that the product and the reference product may be alternated or switched after one has been previously administered without increasing safety risks or risks of diminished efficacy relative to exclusive use of the reference biological product. A reference biological product is granted 12 years of data exclusivity from the time of first licensure of the product and the FDA will not accept an application for a biosimilar or interchangeable product based on the reference biological product until four years after the date of first licensure of the reference product.
European Union drug development
Medicinal products can be marketed in the EU only if a marketing authorization from the competent regulatory agencies has been obtained. Similar to the United States, the various phases of preclinical and clinical research in the EU are subject to significant regulatory controls. Effective January 2022, the European Commission adopted a new Clinical Trials Regulation to streamline and harmonize the procedures for assessment and governance of clinical trials throughout the EU and to require that information on the authorization, conduct and results of each clinical trial conducted in the EU be publicly available.
Pediatric investigation plan
An application for marketing authorization of a medicinal product for human use that is not yet authorized in the EU must include a Pediatric Investigational Plan (PIP), unless a waiver applies. A scientific committee assesses the content of any PIP, waivers, and
Table of Content
deferrals for a medicinal product submitted to it in accordance with the regulation on medicinal products for pediatric use and formulates an opinion thereon.
European drug review and approval
In the European Economic Area (EEA), which is comprised of the 27 Member States of the EU and Norway, Iceland and Liechtenstein, medicinal products can only be commercialized after obtaining a marketing authorization. A company may submit marketing authorization applications either under a centralized or decentralized procedure. The centralized procedure, which is compulsory for medicines produced by biotechnology or those medicines intended to treat AIDS, cancer, neurodegenerative disorders, or diabetes, and optional for those medicines that are highly innovative, provides for the grant of a single marketing authorization that is valid for all EU Member States. In addition to the centralized procedure, the EEA also has a nationalized procedure, which requires a separate application to and approval determination by each country; a decentralized procedure, whereby applicants submit identical applications to several countries and receive simultaneous approval; and a mutual recognition procedure, where applicants submit an application to one country for review and other countries may accept or reject the initial decision.
European exclusivity
In the EEA, new innovative products authorized for marketing (i.e., reference products) qualify for eight years of data exclusivity and an additional two years of market exclusivity upon the grant of a marketing authorization. Data exclusivity prevents regulatory authorities in the European Union from referencing the innovator’s data to assess a generic or biosimilar application. There is no guarantee that a product will be considered by the European Union’s regulatory authorities to be an innovative medicinal product, and products may not qualify for data exclusivity.
European orphan designation and exclusivity
Orphan drug designation is available in the EEA to promote the development of products that are intended for the diagnosis, prevention, or treatment of life threatening or chronically debilitating conditions affecting not more than five in 10,000 persons in the EU community, or where it is unlikely that the development of the medicine would generate sufficient return to justify the necessary investment in its development, and in each case for which no satisfactory method of diagnosis, prevention, or treatment has been authorized (or, if a method exists, the product would be a significant benefit to those affected). Medicinal products that receive and maintain orphan drug designation are entitled to 10 years of market exclusivity following approval.
European data collection
The Data Protection Directive and the General Data Protection Regulation (GDPR) governs the collection and use of personal data in the EU. The GDPR imposes several requirements relating to the consent of the individuals to whom the personal data relates, the information provided to the individuals, the security and confidentiality of the personal data, data breach notification and the use of third-party processors in connection with the processing of the personal data. The GDPR also imposes strict rules on the transfer of personal data out of the EU, provides an enforcement authority and imposes large penalties for noncompliance, including the potential for fines of up to €20.0 million or 4.0% of the annual global revenues of the infringer, whichever is greater.
The UK has incorporated the GDPR (as it existed on December 31, 2020, but subject to certain UK specific amendments) into UK law (the UK GDPR). The UK GDPR and the UK Data Protection Act 2018 set out the UK’s data protection regime, which is independent from but aligned to the EU’s data protection regime. Although the UK is regarded as a third country under the EU’s GDPR, the European Commission has issued a decision recognizing the UK as providing adequate protection under the EU GDPR and, therefore, transfers of personal data originating in the EU to the UK remain unrestricted. Like the GDPR, the UK GDPR restricts personal data transfers outside the UK to countries not regarded by the UK as providing adequate protection. The UK government has confirmed that personal data transfers from the UK to the EEA remain free flowing.
EU drug marketing
Like the Anti-Kickback Statute prohibition in the United States discussed below, the provision of benefits or advantages to physicians to induce or encourage the prescription, recommendation, endorsement, purchase, supply, order, or use of medicinal products is prohibited in the EU. Infringement of relevant EU laws could result in substantial fines and imprisonment. Payments may be made to physicians in limited circumstances, and in certain EU Member States such payments must be publicly disclosed. Moreover, agreements with physicians for the provision of services often must be the subject of prior notification and approval by the physician’s employer, his or her competent professional organization, and/or the regulatory authorities of the individual EU Member States. These requirements are provided in the national laws, industry codes, or professional codes of conduct, applicable in the EU Member States. Failure to comply with these requirements could result in reputational risk, public reprimands, administrative penalties, fines, or imprisonment.
Table of Content
Rest of the world regulation
Outside of the United States and the EU, the requirements governing the conduct of clinical trials, product licensing, pricing, and reimbursement vary from country to country. If we fail to comply with such requirements, we may be subject to, among other things, fines, suspension or withdrawal of regulatory approvals, product recalls, seizure of products, operating restrictions, or criminal prosecution.
Other healthcare laws
Healthcare providers, physicians, and third-party payors, including governmental payors such as Medicare and Medicaid will play a primary role in the recommendation and prescription of any products for which we obtain marketing approval. Any arrangements with these parties may expose us to certain fraud and abuse and other healthcare laws and regulations. In the United States, these laws include, among others:
-
The Anti-Kickback Statute, which makes it illegal for any person to knowingly and willfully solicit, receive, offer, or pay any remuneration, directly or indirectly, in cash or in kind, that is intended to induce or reward referrals, including the purchase, recommendation, order or prescription of a particular drug or any other good or service, for which payment may be made under a federal healthcare program, such as Medicare or Medicaid.
-
The federal False Claims Act, which imposes civil penalties, including through civil whistleblower or qui tam actions, against individuals or entities (including manufacturers) for, among other things, knowingly presenting, or causing to be presented, false or fraudulent claims for payment by a federal healthcare program or making a false statement or record material to payment of a false claim or avoiding, decreasing, or concealing an obligation to pay money to the federal government.
-
Health Insurance Portability and Accountability Act of 1996 (HIPAA), which imposes criminal and civil liability for, among other things, knowingly and willfully executing a scheme, or attempting to execute a scheme, to defraud any healthcare benefit program, including private payors, or falsifying, concealing, or covering up a material fact or making any materially false statements in connection with the delivery of or payment for healthcare benefits, items or services.
-
HIPAA, as amended by the Health Information Technology for Economic and Clinical Health Act of 2009 (HITECH), and their respective implementing regulations, which impose, among other things, requirements on covered entities and their business associates relating to the privacy and security of individually identifiable health information.
-
The Physician Payments Sunshine Act, enacted as part of the Patient Protection and Affordable Care Act, the ACA, which requires certain pharmaceutical manufacturers with products reimbursed under certain government programs to disclose annually to the federal government (for re-disclosure to the public) certain payments and other transfers of value provided to physicians, teaching hospitals and certain non-physician practitioners.
-
Federal government price reporting laws, which require us to calculate and report complex pricing metrics in an accurate and timely manner to government programs.
-
Federal consumer protection and unfair competition laws, which broadly regulate marketplace activities and activities that potentially harm consumers.
-
Analogous state fraud and abuse laws and regulations, such as state anti-kickback and false claims laws, which may be broader in scope and apply regardless of payor.
Additionally, certain state and foreign laws also govern the privacy and security of health information. Such data privacy and security laws may differ from each other in significant ways and often are not pre-empted by HIPAA, thus complicating compliance efforts. For example, the California Consumer Protection Act (CCPA) established a new privacy framework for covered businesses by creating an expanded definition of personal information, establishing new data privacy rights for consumers in the State of California, imposing special rules on the collection of consumer data from minors, and creating a new and potentially severe statutory damages framework for violations of the CCPA and for businesses that fail to implement reasonable security procedures and practices to prevent data breaches. Further, the California Privacy Rights Act (CPRA), which is scheduled to take effect on January 1, 2023 (with certain provisions having retroactive effect to January 1, 2022), will create additional obligations with respect to processing and storing personal information. While clinical trial data and information governed by HIPAA are currently exempt from the current versions of the CCPA and CPRA, other personal information may be applicable and possible changes to the CCPA and CPRA may broaden its scope.
The scope and enforcement of each of these laws is uncertain and subject to rapid change in the current environment of healthcare reform. Federal and state enforcement bodies have recently increased their scrutiny of interactions between healthcare companies and healthcare providers, which has led to a number of investigations, prosecutions, convictions, and settlements in the healthcare industry. If our operations are found to be in violation of any of these laws or other related governmental regulations, we may be subject to significant civil, criminal, and administrative penalties, damages, fines, imprisonment, disgorgement, exclusion of drugs from government funded healthcare programs, such as Medicare and Medicaid, reputational harm, additional oversight, and reporting obligations if we become subject to a corporate integrity agreement or similar settlement to resolve allegations of non-compliance with these laws and the curtailment or restructuring of our operations. If any of the physicians or other healthcare providers or entities with
Table of Content
whom we expect to do business is found to be not in compliance with applicable laws, they may be subject to similar actions, penalties, and sanctions. Ensuring business arrangements comply with applicable healthcare laws, as well as responding to possible investigations by government authorities, can be time- and resource-consuming and can divert a company’s attention from the business.
Current and future healthcare reform legislation
In the United States and foreign jurisdictions, there have been a number of legislative and regulatory changes and proposed changes regarding the healthcare system that could prevent or delay marketing approval of our investigational medicines, restrict or regulate post-approval activities, and affect our ability to profitably sell any approved products. The ACA, for example, contains provisions that subject biological products to potential competition by lower-cost biosimilars and may reduce the profitability of drug products through increased rebates for drugs reimbursed by Medicaid programs, extension of Medicaid rebates to Medicaid managed care plans, mandatory discounts for certain Medicare Part D beneficiaries and, annual fees based on pharmaceutical companies’ share of sales to federal health care programs. We expect that current laws, as well as other healthcare reform measures that may be adopted in the future, may result in more rigorous coverage criteria and in additional downward pressure on the price that we, or any strategic collaborators, may receive for any approved products.
In the United States, it is unclear whether the ACA will be overturned or further amended. We cannot predict what effect further changes to the ACA would have on our business. Additionally, other federal health reform measures have been proposed and adopted in the United States since the ACA was enacted, including the Budget Control Act of 2011, which includes provisions to reduce the federal deficit. The Budget Control Act, as amended, resulted in the imposition of 2% reductions in Medicare payments to providers, which began in April 2013 and will remain in effect through 2030 unless additional Congressional action is taken. Pursuant to the Coronavirus Aid, Relief, and Economic Security Act (the CARES Act), as well as subsequent legislation, these reductions have been suspended from May 1, 2020 through March 31, 2022 due to the COVID-19 pandemic. Then, a 1% payment reduction will occur beginning April 1, 2022 through June 30, 2022, and the 2% payment reduction will resume on July 1, 2022.
Further, there has been heightened governmental scrutiny over the manner in which manufacturers set prices for their marketed products, which have resulted in several Congressional inquiries and proposed bills designed to, among other things, bring more transparency to product pricing, review the relationship between pricing and manufacturer patient programs, and reform government program reimbursement methodologies for products. In addition, the federal government, state legislatures, and foreign governments have shown significant interest in implementing cost containment programs, including price-controls, restrictions on reimbursement, and requirements for substitution of generic products for branded prescription drugs to limit the growth of government paid health care costs. For example, the federal government has passed legislation requiring pharmaceutical manufacturers to provide rebates and discounts to certain entities and governmental payors to participate in federal healthcare programs.
Environment
We are subject to state and federal laws regarding environmental protection and hazardous substances, including the Occupational Safety and Health Act, the Resource Conservation and Recovery Act and the Toxic Substances Control Act. These and other laws govern the use, handling and disposal of various biologic, chemical and radioactive substances used in, and wastes generated by, operations. If our operations result in contamination of the environment or expose individuals to hazardous substances, we could be liable for damages and governmental fines. Equivalent laws have been adopted in foreign countries that impose similar obligations.
CORPORATE INFORMATION
We were incorporated under the laws of the State of Delaware on July 22, 2016. We are the successor in interest to Moderna LLC, a limited liability company formed under the laws of the State of Delaware in 2013. Moderna LLC was the successor in interest to Moderna Therapeutics, Inc., a Delaware corporation incorporated in 2009 as Newco LS18, Inc. by Flagship Pioneering. In August 2018, we changed our name from Moderna Therapeutics, Inc. to Moderna, Inc. Our principal corporate office is located at 200 Technology Square, Cambridge, MA 02139, and our telephone number is (617) 714-6500.
Our website, www.modernatx.com including the Investor Relations section, www.investors.modernatx.com; and corporate blog www.modernatx.com/moderna-blog; as well as our social media channels: Facebook, www.facebook.com/modernatx; Twitter, www.twitter.com/modernatx; and LinkedIn, www.linkedin.com/company/modernatx; contain a significant amount of information about us, including financial and other information for investors. We encourage investors to visit these websites and social media channels as information is frequently updated and new information is shared. The information on our website and that we disclose through social media channels is not incorporated by reference in this Annual Report on Form 10-K or in any other filings we make with the Securities and Exchange Commission (the SEC).
We make available on or through our website certain reports and amendments to those reports that we file with or furnish to the SEC in accordance with the Exchange Act. These include our Annual Reports on Form 10-K, our Quarterly Reports on Form 10-Q, and our
Table of Content
Current Reports on Form 8-K, and amendments to those reports filed or furnished pursuant to Section 13(a) or 15(d) of the Exchange Act. We make this information available on or through our website free of charge as soon as reasonably practicable after we electronically file the information with, or furnish it to, the SEC.
The SEC also maintains a website that contains reports, proxy and information statements, and other information regarding us and other issuers that file electronically with the SEC. The SEC’s Internet website address is http://www.sec.gov.
Table of Content
Previous: Cover and table of contents · Next: Item 1A. Risk Factors