 filings.tools
Insulet 2017 10-K Annual Report
PODD · CIK 1145197 · Form 10-K · Fiscal year ended December 31, 2017 · Filed February 22, 2018
22 sections, 402K characters. Original on sec.gov · ·
Risk FactorsBusinessMD&AFinancial StatementsWhat changed vs 2016
Cover and table of contents
10-K 1 podd-2017x12x31_10xk.htm PODD-2017-12-31_10-K
UNITED STATES SECURITIES AND EXCHANGE COMMISSION
Washington, D.C. 20549
Form 10-K
| x | ANNUAL REPORT PURSUANT TO SECTION 13 OR 15(d) OF THE SECURITIES EXCHANGE ACT OF 1934 |
| For the fiscal year ended December 31, 2017 |
| ¨ | TRANSITION REPORT PURSUANT TO SECTION 13 OR 15(d) OF THE SECURITIES EXCHANGE ACT OF 1934 |
| For the transition period from to |
Commission File Number 001-33462
INSULET CORPORATION
(Exact name of Registrant as specified in its charter)
| Delaware | 04-3523891 | |
| (State or Other Jurisdiction of Incorporation or Organization) | (I.R.S. Employer Identification No.) | |
| 600 Technology Park Drive, Suite 200 Billerica, Massachusetts | 01821 | |
| (Address of Principal Executive Offices) | (Zip Code) |
Registrant’s telephone number, including area code:
(978) 600-7000
Securities registered pursuant to Section 12(b) of the Act:
| Title of Each Class | Name of Each Exchange on Which Registered | |
| Common Stock, $0.001 Par Value Per Share | The NASDAQ Stock Market, LLC | |
| Preferred Stock Purchase Rights | The NASDAQ Stock Market, LLC |
Securities registered pursuant to Section 12(g) of the Act:
None
Indicate by check mark if the registrant is a well-known seasoned issuer, as defined in Rule 405 of the Securities Act. Yes x No ¨
Indicate by check mark if the registrant is not required to file reports pursuant to Section 13 or Section 15(d) of the Act. Yes ¨ No x
Indicate by check mark whether the registrant (1) has filed all reports required to be filed by Section 13 or 15(d) of the Securities Exchange Act of 1934 during the preceding 12 months (or for such shorter period that the Registrant was required to file such reports) and (2) has been subject to such filing requirements for the past 90 days. Yes x No ¨
Indicate by check mark whether the registrant has submitted electronically and posted on its corporate Web site, if any, every Interactive Data File required to be submitted and posted pursuant to Rule 405 of Regulation S-T (§ 232.405 of this chapter) during the preceding 12 months (or for such shorter period that the registrant was required to submit and post such files). Yes x No ¨
Indicate by check mark if disclosure of delinquent filers pursuant to Item 405 of Regulation S-K (§ 229.405) is not contained herein, and will not be contained, to the best of registrant’s knowledge, in definitive proxy or information statements incorporated by reference in Part III of this Form 10-K or any amendment to this Form 10-K. ¨
Indicate by check mark whether the registrant is a large accelerated filer, an accelerated filer, a non-accelerated filer, or a smaller reporting company. See the definitions of “large accelerated filer,” “accelerated filer” and “smaller reporting company” in Rule 12b-2 of the Exchange Act. (Check one):
| Large accelerated filer x | Accelerated filer o | Non-accelerated filer o | Smaller reporting company o | |||
| (Do not check if a smaller reporting company) |
Indicate by check mark whether the Registrant is a shell company (as defined in Rule 12b-2 of the Exchange Act). Yes ¨ No x
The aggregate market value of the common stock held by non-affiliates of the registrant computed by reference to the last reported sale price of the Common Stock as reported on The NASDAQ Global Market on June 30, 2017 was approximately $3.0 billion.
The number of shares outstanding of each of the registrant’s classes of common stock as of February 16, 2018:
| Title of Class | Shares Outstanding | |
| Common Stock, $0.001 Par Value Per Share | 58,391,036 | |
| Preferred Stock Purchase Rights | — |
DOCUMENTS INCORPORATED BY REFERENCE
The registrant intends to file a proxy statement pursuant to Regulation 14A within 120 days of the end of the fiscal year ended December 31, 2017. Portions of such proxy statement are incorporated by reference into Part III of this Annual Report on Form 10-K.
TABLE OF CONTENTS
PART I
Item 1. Business
Overview
We are primarily engaged in the development, manufacturing and sale of our proprietary Omnipod® Insulin Management System (the “Omnipod System”), an innovative, discreet and easy-to-use continuous insulin delivery system for people with insulin-dependent diabetes. The Omnipod System features a small, lightweight, self-adhesive disposable tubeless Omnipod device, which is worn on the body for approximately three days at a time, and its wireless companion: the handheld Personal Diabetes Manager (“PDM”). Conventional tubed insulin pumps require people with insulin-dependent diabetes to learn to use, manage and wear a number of cumbersome components, including up to 42 inches of tubing. In contrast, the Omnipod System features only two discreet, easy-to-use devices that eliminate the need for a bulky pump and tubing, provides for virtually pain-free automated cannula insertion, communicates wirelessly and integrates a blood glucose meter. We believe that the Omnipod System’s unique proprietary design and features allow people with insulin-dependent diabetes to manage their diabetes with unprecedented freedom, comfort, convenience, and ease.
We began commercial sale of the Omnipod System in the United States in 2005. We sell the Omnipod System in the United States through direct sales to customers or through our distribution partners. The Omnipod System is currently available in multiple countries in Europe, as well as in Canada and Israel.
In January 2018, the Centers for Medicare & Medicaid Services (“CMS”) issued guidance clarifying that Medicare Part D Plan Sponsors may provide coverage for products such as the Omnipod System under the Medicare Part D (prescription drug) program. We believe this guidance will allow many additional people with diabetes to begin accessing our product in the future. Securing Medicare Part D coverage also provides us with a direct pathway to gain Medicaid coverage at the state level, as many state-run Medicaid programs follow CMS prescription drug guidance to determine coverage. This allows access for lower-income individuals and families on Medicaid for whom Omnipod is currently not an option. The Company estimates that obtaining Medicare and Medicaid coverage extends access to Insulet's Omnipod System to approximately 450,000 additional individuals with Type 1 diabetes in the United States.
We announced in 2017 our plans to assume, on July 1, 2018, all commercial activities (including, among other things, distribution, sales, marketing, training and support) of our Omnipod System across Europe following the expiration of our distribution agreement with Ypsomed Distribution AG ("Ypsomed" or our "European distributor") on June 30, 2018.
In addition to the diabetes market space, we have partnered with pharmaceutical and biotechnology companies that utilize a customized form of the Omnipod System to deliver a drug over a specified interval of time, at a certain administered volume. The majority of our drug delivery revenue currently consists of sales of Amgen's Neulasta Onpro kit.
We are constructing a highly-automated manufacturing facility in Acton, Massachusetts, with planned production out of the facility beginning in early 2019. The facility will also serve as our global headquarters. We expect that the new facility will allow us to lower our manufacturing costs, increase supply redundancy, add capacity closer to our largest customer base and support growth.
In January 2018, we submitted a premarket notification 510(k) to the U.S. Food and Drug Administration ("FDA") requesting clearance for commercial distribution of our DASHTM System, which is our next generation of the Omnipod System, featuring a secured Bluetooth Low Energy enabled Pod and PDM with a touch screen color user interface supported by smartphone connectivity. Upon clearance, we would begin a limited commercial release of the product prior to a full market launch.
Our Market
Diabetes is a chronic, life-threatening disease for which there is no known cure. Diabetes is caused by the body’s inability to produce or effectively utilize the hormone insulin. This inability prevents the body from adequately regulating blood glucose levels. Glucose, the primary source of energy for cells, must be maintained at certain concentrations in the blood in order to permit optimal cell function and health. In people with diabetes, blood glucose levels fluctuate between very high levels, a condition known as hyperglycemia, and very low levels, a condition called hypoglycemia. Hyperglycemia can lead to serious short-term complications, such as confusion, vomiting, dehydration and loss of consciousness and long-term complications, such as blindness, kidney disease, nervous system disease, occlusive vascular diseases, stroke and cardiovascular disease, or death. Hypoglycemia can lead to confusion, loss of consciousness or death.
Diabetes is typically classified as either Type 1 or Type 2:
| • | Type 1 diabetes is characterized by the body’s nearly complete inability to produce insulin. It is frequently diagnosed during childhood or adolescence. Individuals with Type 1 diabetes require daily insulin therapy to survive, typically administered via injections or continuous infusion through pump therapy. It is estimated that approximately 1.5 million people have Type 1 diabetes in the United States. |
| • | Type 2 diabetes, the more common form of diabetes, is characterized by the body’s inability to either properly utilize insulin or produce enough insulin. Historically, Type 2 diabetes has occurred in later adulthood, but its incidence is increasing among the younger population, due primarily to increasing childhood obesity. Initially, many people with Type 2 diabetes attempt to manage their diabetes with improvements in diet, exercise and/or oral medications. As their diabetes advances, some patients progress to multiple drug therapies, which often include insulin therapy. It is estimated that approximately 1.7 million people in the United States have Type 2 diabetes requiring daily insulin administration. |
Throughout this Annual Report on Form 10-K, we refer to both Type 1 diabetes and insulin-requiring Type 2 diabetes as insulin-dependent diabetes.
Diabetes Management Challenges
Diabetes is often frustrating and difficult for patients to manage. Blood glucose levels can be affected by the carbohydrate and fat content of meals, exercise, stress, illness or impending illness, hormonal releases, variability in insulin absorption and changes in the effects of insulin on the body. For people with insulin-dependent diabetes, many corrections, consisting of the administration of additional insulin or ingestion of additional carbohydrates, are needed throughout the day in order to maintain blood glucose levels within normal ranges. Achieving this result can be very difficult without multiple daily injections of insulin or the use of continuous subcutaneous insulin infusion (“CSII”), often referred to as pump therapy. Patients attempting to control their blood glucose levels tightly to prevent the long-term complications associated with fluctuations in blood glucose levels are at greater risk for overcorrection and the resultant hypoglycemia. As a result, many patients have difficulty managing their diabetes optimally. Additionally, the time spent in managing diabetes, the swings in blood glucose levels and the fear of hypoglycemia can render diabetes management overwhelming to patients and their families.
Current Insulin Therapy
People with insulin-dependent diabetes need a continuous supply of insulin, known as basal insulin, to provide for background metabolic needs. In addition to basal insulin, people with insulin-dependent diabetes require supplemental insulin, known as bolus insulin, to compensate for carbohydrates ingested during meals or snacks or for a high blood glucose level.
There are two primary types of insulin therapy practiced today: multiple daily injection (“MDI”) therapy using syringes or insulin pens; and pump therapy using insulin pumps. Insulin pumps are used to perform continuous subcutaneous insulin infusion, or insulin pump therapy, and typically use a programmable device and an infusion set to administer insulin into the person’s body.
MDI therapy involves the administration of a rapid acting insulin before meals (bolus) to bring blood glucose levels down into the healthy range. MDI therapy may also require a separate injection of a long-acting (basal) insulin, to control glucose levels between meals; this type of insulin is typically taken once or twice per day. By comparison, insulin pump therapy uses only rapid acting insulin to fulfill both mealtime (bolus) and background (basal) requirements. Insulin pump therapy allows a person to customize their bolus and basal insulin doses to meet their insulin needs throughout the day, and is intended to more closely resemble the physiologic function of a healthy pancreas.
Insulin pump therapy has been shown to provide people with insulin-dependent diabetes with numerous advantages relative to MDI therapy. For example, insulin pump therapy eliminates individual insulin injections, delivers insulin more accurately and precisely than injections, often improves HbA1c (a common measure of blood glucose levels) over time, provides greater flexibility with meals, exercise and daily schedules, and can reduce severe low blood glucose levels.
We estimate that approximately one-third of the Type 1 diabetes population in the United States use insulin pump therapy. In addition, we believe less than 10% of the Type 2 diabetes population in the United States who are insulin-dependent use insulin pump therapy. We believe that the distinct advantages and increased awareness of insulin pump therapy as compared to other available insulin therapies will continue to generate demand for insulin pump devices.
In addition to the diabetes market space, we have partnered with pharmaceutical and biotechnology companies that utilize a customized form of the Omnipod System to deliver specific drugs over a specified interval of time, at a certain administered volume.
The Omnipod System
The Omnipod Insulin Management System is an innovative continuous insulin delivery system that provides all the proven benefits of insulin pump therapy in a way no conventional insulin pump can. The Omnipod System's innovative design and differentiated features allows people with insulin-dependent diabetes to live their lives, and manage their diabetes, with unprecedented freedom, comfort, convenience and ease.


The long-term health benefits of better blood glucose control are well known. Maintaining near-normal blood glucose levels can help people with insulin-dependent diabetes live a longer, healthier life with fewer diabetes-related complications. The Omnipod System also has many practical, everyday benefits, including convenience, freedom, flexibility and ease of use.
Continuous insulin delivery at preset rates eliminates the need for individual injections and the interruptions that come with them. In addition, with the Omnipod System, insulin delivery can be changed with the press of a button to adapt to snacks or unexpected changes in daily routine.
The Omnipod System works much like the pancreas of a person without diabetes by delivering insulin in two ways:
| • | A small, constant background supply of insulin (basal) is delivered automatically at a programmed rate, all day and night. |
| • | An extra dose of insulin (bolus) can be delivered when a patient needs it to match the carbohydrates in a meal or snacks or to correct high blood glucose. |
The Omnipod System is a discreet two part design, the Omnipod device (“Omnipod” or “Pod”) and the PDM, that eliminates the need for the external tubing required with conventional pumps.
| • | The Pod is a small, lightweight, self-adhesive device that the user fills with insulin and wears directly on the body. The Pod delivers precise, personalized doses of insulin into the body through a small flexible tube (called a cannula), based on instructions that the patient programs into the Pod's wireless companion, the PDM. |
| • | The PDM is a wireless, handheld device that programs the Pod with the user's personalized insulin-delivery instructions, wirelessly monitors the Pod's operation and includes a FreeStyle® blood glucose meter. |
We have designed the Omnipod System to fit within the normal daily routines of patients. The Omnipod System consists of just two devices, as opposed to up to seven for conventional tubed insulin pumps. As a result, the Omnipod System is easy for patients to use, which also reduces the training burden on healthcare professionals and users. We believe that the Omnipod System’s overall ease of use makes it very attractive to people with insulin-dependent diabetes. We also believe that the Omnipod System’s ease of use and substantially lower training burden helps to redefine which diabetes patients are appropriate for insulin pump therapy, allowing healthcare professionals to prescribe pump therapy to a broader pool of patients.
The Omnipod System’s unique patented design and proprietary manufacturing process allow us to provide CSII therapy at a relatively low up-front investment compared to conventional tubed insulin pumps. We believe that our pricing model reduces the risk of investing in pump therapy for third-party payors and makes this therapy much more accessible for people with insulin-dependent diabetes.
In 2017, the results of a clinical study were published in a peer-reviewed, scientific journal demonstrating that insulin infusion devices similar to the Omnipod System can effectively maintain the blood glucose levels at a basal level across a representative sample of individuals, including children and adolescents, with Type 1 diabetes. This study further demonstrates the effectiveness of the Omnipod System and builds on the catalog of clinical evidence that helps us build support for our product within the physician community.
In 2016, there were three publications in peer-reviewed, scientific journals demonstrating the clinical and quality of life benefits associated with use of the Omnipod System. Two publications reported results of a retrospective study of patients with Type 1 and Type 2 diabetes. The study demonstrated clinically meaningful and statistically significant improvements in HbA1c (an important measure of blood glucose control), reduction in total daily dose of insulin and reduction in the frequency and severity of self-reported hypoglycemic episodes after three months of Omnipod System use compared to previous treatment with either multiple daily injections or traditional tubed insulin pumps. The third publication reported results of a second study that surveyed current adult Omnipod System users of which the majority reported positive changes in quality of life including perceived control over their diabetes, reduced diabetes distress, improved overall well-being and sense of hypoglycemic safety since initiating treatment with the Omnipod System. In addition, the majority of patients also reported significant improvement in glycemic control with more than one-third reporting a decrease in severe hypoglycemic episodes.
Competition
The medical device industry is intensely competitive, subject to rapid change and significantly affected by new product introductions and other market activities of industry participants. The Omnipod System competes for patients in the insulin delivery industry. As the majority of new Omnipod System end-users have previously used MDI therapy, which is currently the most prevalent method of insulin delivery, we believe that we primarily compete with companies that provide MDI products such as insulin syringes and needles. Also, we compete with companies in the insulin pump therapy market, which consist of conventional tubed pump companies and patch-pump companies. Conventional tubed pump companies include Medtronic MiniMed, a division of Medtronic Public Limited Company ("Medtronic"), and Tandem Inc. Medtronic has historically held the majority share of the conventional tubed insulin pump market in the United States. The competitive landscape in our industry is undergoing significant change. For example, during 2017, Animas Corporation, a division of Johnson & Johnson, announced that it is exiting the insulin pump market in the United States and other countries. In addition to the established insulin pump competitors, several companies are working to develop and market new insulin patch pumps and other methods of insulin delivery, such as nasal, for the treatment of diabetes. These companies are at various stages of development and the number of such companies often changes as they enter or exit the market. Our non-insulin drug delivery product line also competes with drug delivery device companies such as West Pharmaceutical Services, Inc.
Several of our competitors are large, well-capitalized companies with significantly more market share and resources than we have. They are able to spend aggressively on product development, marketing, sales and other product initiatives. Some of these competitors have:
| • | significantly greater name recognition; |
| • | established relations with healthcare professionals, customers and third-party payors; |
| • | larger and more established sales forces and distribution networks; |
| • | greater experience in conducting research and development, manufacturing, clinical trials, marketing and obtaining regulatory approval for products; and |
| • | greater financial and human resources for product development, sales and marketing and patent litigation. |
Research and Development
Our current research and development efforts are primarily focused on the development of mobile applications for the Omnipod System, including:
| • | Omnipod DASH Insulin Management System. We are developing our next generation of the Omnipod System, which features a secure Bluetooth Low Energy enabled Pod and PDM with a touch screen color user interface supported by smartphone connectivity. We refer to this as our Omnipod DASH System, or (“DASH”). In January 2018, we submitted a premarket notification 510(k) application to the FDA requesting permission for commercial distribution of DASH. |
| • | Concentrated Insulin Delivery. In collaboration with Eli Lilly, we are developing new products that leverage the DASH mobile platform to support the use of concentrated insulins for Type 1 and Type 2 patients with higher insulin-requirements, utilizing the same form factor as our existing Pod. These new products are being specifically designed to deliver Humalog ® 200 units/mL and Humulin® R U-500 insulin, which are concentrated forms of insulin used by people with highly insulin resistant Type 2 diabetes. We believe these innovations should significantly expand our access to more of the Type 2 diabetes market. |
| • | Omnipod Horizon Automated Glucose Control. We are also developing a hybrid closed loop control system that would utilize the DASH mobile platform. Our Pod will communicate with Dexcom Inc.'s ("Dexcom") continuous glucose monitor and help control insulin delivery utilizing an algorithm located on the Pod. |
In addition to insulin delivery, we continue to work with pharmaceutical and biotechnology companies on alternative uses for our Omnipod System technology as a delivery platform for a range of different pharmaceuticals and therapies.
Manufacturing and Quality Assurance
We believe a key contributing factor to the overall attractiveness of the Omnipod System is the disposable Omnipod continuous insulin delivery device. In order to manufacture sufficient volumes and achieve a cost-effective per unit production price for the Omnipod, we have designed the Omnipod to be manufactured through our current semi-automated process.
We are currently producing our devices on varying degrees of semi-automated manufacturing lines at a facility in China, operated by a subsidiary of Flex Ltd. (“Flex”). We purchase our devices pursuant to an agreement with Flex. The current term of the agreement expires in September 2021 and is subject to an automatic renewal thereafter, unless otherwise canceled by the parties under the contract terms. The contract may be terminated by either party upon compliance with certain advance written notice provisions that are intended to provide the parties with sufficient time to make alternative arrangements.
To lower our manufacturing costs, increase supply redundancy, add capacity closer to our largest customer base, and support our growth, we continue to invest in our supply chain operations. As part of our investment strategy, in 2016 we announced our plan to establish a highly automated manufacturing operation in the United States, and we expect to begin production through this operation in early 2019. To date, we have invested approximately $70 million in property, equipment and infrastructure related to the new facility.
We utilize outside vendors for the supply of components, sub-assemblies, and various services used in the manufacture of the Omnipod System. Our outside vendors produce the components to our specifications and they are audited periodically by our Quality Assurance Department to ensure conformity with the specifications, policies and procedures for the Omnipod System. Our Quality Assurance Department also inspects and tests the Omnipod System at various steps in the manufacturing cycle to facilitate compliance with our specifications. We have received approval of our Quality Management System from the BSI Group London, U.K., an accredited Notified Body for CE Marking and the International Standards Organization (“ISO”). Processes utilized in the manufacture, test and release of the Omnipod System have been verified and validated as required by the FDA and other regulatory bodies. As a medical device manufacturer and distributor, our manufacturing facilities and the facilities of our suppliers are subject to periodic inspection by the FDA and certain corresponding state agencies.
Intellectual Property
To maintain a competitive advantage, we believe we must develop and preserve the proprietary aspect of our technologies. We rely on a combination of copyright, patent, trademark, trade secret and other intellectual property laws, non-disclosure agreements and other measures to protect our proprietary rights. Currently, we require our employees, consultants and advisers to execute non-disclosure agreements in connection with their employment, consulting or advisory relationships with us, where appropriate. We also require our employees, consultants and advisers who we expect to work on our current or future products to agree to disclose and assign to us all inventions conceived during their work with us that are developed using our property or which relate to our business. Despite any measures taken to protect our intellectual property, unauthorized parties may attempt to copy aspects of the Omnipod System or to obtain and use information that we regard as proprietary.
Patents. As of December 31, 2017, we had 16 granted and active United States patents with expiration dates ranging from 2020 through 2034, and had 53 additional pending United States patent applications. We believe it will take up to four years, and possibly longer, for the most recent of these U.S. patent applications to result in issued patents. We are also seeking patent protection for our proprietary technology in other countries and regions throughout the world. The issued patents and pending patent applications cover, among other things:
| • | the basic architecture of the Omnipod System, including the pump and the PDM; |
| • | the Omnipod shape memory alloy drive system; |
| • | the Omnipod System cannula insertion system; |
| • | communication features between system components for the Omnipod System and next generation products; |
| • | software for controlling the Omnipod System and next generation products; and |
| • | various novel aspects of the Omnipod System, potential future generations of Omnipod Systems, and other mechanisms for the delivery of pharmaceuticals. |
Trademarks. We have registered various trademarks associated with our business with the United States Patent and Trademark Office on the Principal Register and in other appropriate jurisdictions. Our trademarks include OMNIPOD(R), DASHTM, OMNIPOD U-200TM, OMNIPOD U-500TM, and HORIZONTM.
Markets and Distribution Methods
We sell our Omnipod System directly to patients or indirectly through intermediaries, such as independent distributors and the pharmacy channel, in the United States, Canada, Europe, and Israel. In 2017, direct sales to patients represented approximately 52% of our total revenue in the United States. We sell the Omnipod System in certain countries in Europe through our independent distributor. Our exclusive European distribution agreement expires on June 30, 2018, at which time we plan to assume all commercial activities (including, among other things, distribution, sales, marketing, training and support) of our Omnipod System across Europe.
Comprehensive approach across three interrelated constituencies. Our sales and marketing effort for the Omnipod System is focused on patient retention and growing patient, clinician and payor demand for the Omnipod System. We have a uniform sales and marketing approach, aligned across patients, physicians and providers, to capitalize on the unique benefits of our Omnipod System technology. We have three areas of focus:
| • | First, build patient awareness about the features and benefits that the Omnipod System provides. |
| • | Second, build physician support by increasing the clinical evidence that clearly demonstrates the benefits that the Omnipod System provides and by improving the data available to physicians to monitor their patient's diabetes care. |
| • | Third, provide payors with the clinical and economic justification of why the Omnipod System is a greater benefit for the patients whom they insure. |
Training. We believe that patient training is critical to ensure successful outcomes and patient retention on the Omnipod System. We have streamlined our new patient training by developing improved online resources, a standardized approach as well as increasing our field clinician team to directly train new Omnipod System customers.
Customer Support. We seek to provide our customers with high quality customer support, from product ordering to insurance investigation, order fulfillment and ongoing support. We have integrated our customer support systems with our sales, reimbursement and billing processes and also offer support by telephone and through our website to provide customers with seamless and reliable customer support.
Government Regulation
Domestic Regulation. The Omnipod System is a medical device subject to extensive and ongoing regulation by the FDA and other federal, state, and local regulatory bodies. FDA regulations govern, among other things, product design and development, pre-clinical and clinical testing, manufacturing, labeling, post-market adverse event reporting, post-market surveillance, complaint handling, repair or recall of products, product storage, record keeping, pre-market clearance or approval, advertising and promotion, and sales and distribution.
FDA’s Pre-Market Notification 510(k) and Pre-Market Approval Requirements. Unless an exemption applies, each medical device we seek to commercially distribute in the United States will require either prior 510(k) clearance or pre-market approval (“PMA”) from the FDA. The FDA classifies medical devices into one of three classes. Devices deemed to pose low to moderate risk are placed in either class I or II, which, absent an exemption, requires the manufacturer to submit to the FDA a premarket notification requesting clearance for commercial distribution. Some low risk devices are exempt from this requirement. Devices deemed by the FDA to pose the greatest risk, such as life-sustaining, life-supporting or implantable devices, or devices deemed not substantially equivalent to a previously cleared 510(k) device, are placed in class III, requiring approval of a PMA application. We have obtained 510(k) clearance for the Omnipod System and expect that PMA approval will be needed for some of our future products. We may be required to obtain a new 510(k) clearance or pre-market approval for significant post-market modifications to the Omnipod System. Both the 510(k) clearance and PMA processes can be expensive and lengthy and entail significant user fees, unless an exemption is available.
510(k) Clearance. To obtain 510(k) clearance for any of our potential future devices (or for certain modifications to devices that have previously received 510(k) clearance), we must submit a pre-market notification demonstrating that the proposed device is substantially equivalent to a previously cleared 510(k) device or a pre-amendment device that was in commercial distribution before May 28, 1976 for which the FDA has not yet called for the submission of a PMA application. The FDA’s 510(k) clearance pathway generally takes from three to twelve months from the date the application is completed, but can take significantly longer. After a medical device receives 510(k) clearance, any modification that could significantly affect its safety or effectiveness, or that would constitute a significant change in its intended use, requires a new 510(k) clearance or, depending on the modification, could require a PMA application. The FDA requires each manufacturer to make this determination initially, but the FDA can review any such decision and can disagree with a manufacturer’s determination.
If the FDA disagrees with a manufacturer’s determination regarding whether a new premarket submission is required for the modification of an existing device, the FDA can, at its discretion, require the manufacturer to cease marketing and/or recall the modified device until 510(k) clearance or approval of a PMA application is obtained. In addition, in these circumstances, we may be subject to significant regulatory fines or penalties for failure to submit the requisite PMA application(s).
PMA. Devices deemed by the FDA to pose the greatest risk, such as life-sustaining, life-supporting or implantable devices, devices deemed not substantially equivalent to a previously cleared 510(k) device or devices in commercial distribution before May 28, 1976 for which PMAs have not been required, generally require a PMA before they can be commercially distributed. A PMA application must be supported by extensive data, including technical information, pre-clinical and clinical trials, manufacturing and labeling to demonstrate the safety and effectiveness of the device to the FDA’s satisfaction. After a PMA application is complete, the FDA begins an in-depth review of the submitted information, which generally takes between one and three years, but may take significantly longer. During this review period, the FDA may request additional information or clarification of information already provided. Also during the review period, an advisory panel of experts from outside the FDA may be convened to review and evaluate the application and provide recommendations to the FDA as to the approvability of the device. In addition, the FDA will conduct a pre-approval inspection of the manufacturing facility to ensure compliance with Quality System Regulations, or QSRs, which impose elaborate design development, testing, control, documentation and other quality assurance procedures in the design and manufacturing process. The FDA may approve a PMA application with post-approval conditions intended to ensure the safety and effectiveness of the device including, among other things, restrictions on labeling, promotion, sale and distribution and collection of long-term follow-up data from patients in the clinical study that supported approval. Failure to comply with the conditions of approval can result in materially adverse enforcement action, including the loss or withdrawal of the approval. After any pre-market approval, a new pre-market approval application or application supplement may be required in the event of modifications to the device, its labeling, intended use or indication or its manufacturing process. PMA supplements often require submission of the same type of information as a PMA application, except that the supplement is limited to information needed to support any changes from the device covered by the original PMA application, and may not require as extensive clinical data or the convening of an advisory panel.
Clinical Trials. Clinical trials are almost always required to support a PMA application and sometimes also 510(k) submissions. If the device presents a “significant risk” to human health as defined by the FDA, the FDA requires the device sponsor to submit an investigational device exemption ("IDE") to the FDA and obtain IDE approval prior to commencing the human clinical trials. The IDE must be supported by appropriate data, such as animal and laboratory testing results, showing that it is safe to test the device in humans and that the testing protocol is scientifically sound. The IDE must be approved in advance by the FDA for a specified number of patients, unless the product is deemed a “non-significant risk” device, in which case an IDE approval from the FDA would not be required, although the clinical trial would need to meet other requirements including IRB approval. Clinical trials for a significant risk device may begin once an IDE is approved by the FDA and the appropriate Institutional Review Board ("IRB") at each clinical trial site. Future clinical trials may require that we obtain an IDE from the FDA prior to commencing any such clinical trial and that the trial be conducted with the oversight of an IRB at the clinical trial site.
Our clinical trials must be conducted in accordance with FDA regulations and federal and state regulations concerning human subject protection, including informed consent and healthcare privacy. A clinical trial may be suspended by the FDA or at a specific site by the relevant IRB at any time for various reasons, including a belief that the risks to the trial participants outweigh the benefits of participation in the clinical trial. Even if a clinical trial is completed, the results of our clinical testing may not demonstrate the safety and efficacy of the device, or may be equivocal or otherwise not be sufficient for us to obtain approval of our product.
Ongoing Regulation by FDA. Even after a device is placed on the market, regardless of its classification or premarket pathway, numerous regulatory requirements apply. These include, but are not limited to:
| • | establishment registration and device listing; |
| • | quality system regulation, or QSR, which requires manufacturers, including third party manufacturers, to follow stringent design, testing, control, documentation and other quality assurance procedures during all aspects of the manufacturing process; |
| • | labeling regulations and FDA prohibitions against the promotion of products for uncleared, unapproved or “off-label” uses, and other requirements related to promotional activities; |
| • | medical device reporting regulations, which require that manufacturers report to the FDA if their device may have caused or contributed to a death or serious injury or malfunctioned in a way that would likely cause or contribute to a death or serious injury if the malfunction were to recur; |
| • | corrections and removals reporting regulations, which require that manufacturers report to the FDA field corrections and product recalls or removals if undertaken to reduce a risk to health posed by the device or to remedy a violation of the Federal Food, Drug and Cosmetic Act that may present a risk to health. In addition, FDA may order a mandatory recall if there is a reasonable probability that the device would cause serious adverse health consequences or death; and |
| • | post-market surveillance regulations, which apply when necessary to protect the public health or to provide additional safety and effectiveness data for the device. |
Failure to comply with applicable regulatory requirements can result in enforcement actions by the FDA and other regulatory agencies, which may include any of the following sanctions: untitled letters or warning letters, fines, injunctions, consent decrees, civil or criminal penalties, recall or seizure of our current or future products, operating restrictions, partial suspension or total shutdown of production, refusal of or delay in granting 510(k) clearance or PMA approval of new products or modified products, rescinding previously granted 510(k) clearances or withdrawing previously granted PMA approvals, or refusal to grant import or export approval of our products.
We are subject to announced and unannounced inspections by the FDA, and these inspections may include the manufacturing facilities of our subcontractors. If, as a result of these inspections, the FDA determines that our equipment, facilities, laboratories or processes do not comply with applicable FDA regulations and conditions of product approval, the FDA may seek civil, criminal or administrative sanctions and/or remedies against us, including the suspension of our manufacturing operations. Since approval of the Omnipod System, we have been subject to FDA inspections of our facility on multiple occasions. We cannot assure you that our facilities or our contract manufacturer or component suppliers’ facilities would pass any future quality system inspection.
International Regulation. International sales of medical devices are subject to foreign government regulations, which may vary substantially from country to country. The time required to obtain approval by a foreign country may be longer or shorter than that required for FDA clearance or approval, and the requirements may differ. There is a trend towards harmonization of quality system standards among the European Union, United States, Canada and various other industrialized countries.
The primary regulatory body in Europe is that of the European Union, which includes most of the major countries in Europe. Other countries, such as Switzerland, have voluntarily adopted laws and regulations that mirror those of the European Union with respect to medical devices. The European Union has adopted numerous directives and standards regulating the design, manufacture, clinical trials, labeling and adverse event reporting for medical devices, including the Medical Device Directive ("MDD"). Devices that comply with the requirements of a relevant directive will be entitled to bear the CE conformity marking, indicating that the device conforms to the essential requirements of the applicable directives and, accordingly, can be commercially distributed throughout Europe. The method of assessing conformity varies depending on the class of the product, but normally involves a combination of self-assessment by the manufacturer and a third party assessment by a “Notified Body.” This third-party assessment may consist of an audit of the manufacturer’s quality system and specific testing of the manufacturer’s product. An assessment by a Notified Body of one country within the European Union is required in order for a manufacturer to commercially distribute the product throughout the European Union. Outside of the European Union, regulatory approval needs to be sought on a country-by-country basis in order for us to market our products.
In April 2009, we obtained the right to affix the CE Mark to the original Omnipod System, and in August 2011, we obtained the right to affix the CE Mark for our updated Omnipod System. The CE Mark gives us authorization to distribute the Omnipod System throughout the European Union and in other countries that recognize the CE Mark. In September 2009, we received Health Canada approval to distribute the original Omnipod System throughout Canada, and in March 2013, we received Health Canada approval for our current Omnipod System. We have been distributing the Omnipod System in certain countries in Europe through our European distributor since 2010.
Licensure. Several states require that durable medical equipment (“DME”) providers be licensed in order to sell products to patients in that state. Certain of these states require, among other things, that DME providers maintain an in-state location. Although we believe we are in compliance with all applicable state regulations regarding licensure requirements, if we were found to be noncompliant, we could lose our licensure in that state, which could prohibit us from selling our current or future products directly to patients in that state.
In addition, we are subject to certain state laws regarding professional licensure. We believe that our certified diabetes educators are in compliance with all such state laws. However, if our educators or we were to be found non-compliant in a given state, we may need to modify our approach to providing education, clinical support and customer service.
Federal Anti-Kickback and Self-Referral Laws. The Federal Anti-Kickback Statute prohibits the knowing and willful offer, payment, solicitation or receipt of any form of remuneration in return for, or to induce:
| • | the referral of an individual; |
| • | furnishing or arranging for the furnishing of items or services reimbursable under Medicare, Medicaid or other federal health care programs; or |
| • | the purchase, lease, or order of, or the arrangement or recommendation of the purchasing, leasing, or ordering of, any item or service reimbursable under Medicare, Medicaid or other federal health care programs. |
The Federal Anti-Kickback Statute has been interpreted to apply to arrangements between drug and medical device manufacturers and suppliers on one hand and prescribers, patients, purchasers and formulary managers on the other. Liability under the statute may be established without a person or entity having actual knowledge of the statute or specific intent to violate it. In addition, claims resulting from a violation of the Federal Anti-Kickback Statute constitute false or fraudulent claims for purposes of the Federal False Claims Act, which is addressed below. Although there are a number of statutory exemptions and regulatory safe harbors protecting certain common business practices from prosecution and administrative sanctions, the exemptions and safe harbors are drawn narrowly, and practices that involve remuneration that may be perceived as inducing the prescription, purchase, or recommendation of the Omnipod System may be subject to scrutiny under the law. For example, we provide the initial training to patients necessary for appropriate use of the Omnipod System either through our own diabetes educators or by contracting with outside diabetes educators that have completed a Certified Pod Trainer training course. We compensate outside diabetes educators for their services at contracted rates deemed to be consistent with the market. We have structured our arrangements with diabetes educators and other business practices to comply with statutory exemptions and regulatory safe harbors whenever possible, but our practices may be subject to scrutiny if they fail to strictly comply with the criteria in the exemption or regulatory safe harbor. Moreover, there are no safe harbors for many common practices such providing reimbursement assistance, coding and billing information or other patient assistance and product support programs. If any of our practices, arrangements or programs are found not to be in compliance with the Federal Anti-Kickback Statute, we can be subject to criminal, civil and administrative penalties, including imprisonment, fines, damages, and exclusion from Medicare, Medicaid or other governmental programs, any of which could have an adverse effect on our business and results of operations.
Federal law also includes a provision commonly known as the “Stark Law,” which prohibits a physician from referring Medicare or Medicaid patients to an entity for the furnishing of certain “designated health services,” including durable medical equipment, in which the physician has an ownership or investment interest or with which the physician has entered into a compensation arrangement. Violation of the Stark Law could result in denial of payment, disgorgement of reimbursements received for items and services referred by a physician with a noncompliant arrangement, civil damages and penalties, and exclusion from Medicare, Medicaid or other governmental programs. Although there are a number of statutory and regulatory exceptions protecting certain common business practices implicating the Stark Law, and we have structured our arrangements with physicians and other providers to comply with these exceptions, these arrangements may not expressly meet the requirements for applicable exceptions from the law.
Federal civil False Claims Act. The Federal civil False Claims Act imposes penalties against any person or entity who, among other things, knowingly presents, or causes to be presented, a false or fraudulent claim for payment of government funds or knowingly making, using or causing to be made or used a false record or statement material to a false or fraudulent claim. Actions under the False Claims Act may be brought by the Attorney General or as a qui tam action by a private individual in the name of the government. Violations of the False Claims Act are subject to the imposition of significant per claim penalties, three times the amount of damages that the federal government sustained and possible exclusion from participation in federal health care programs like Medicare and Medicaid. We believe that we are in compliance with the federal government’s laws and regulations concerning the filing of claims for reimbursement. However, many drug and medical device manufacturers have been investigated or subject to lawsuits by whistleblowers and have reached substantial financial settlements with the federal government under the False Claims Act for a variety of alleged improper marketing activities, including providing free product to customers with the expectation that the customers would bill federal programs for the product; or causing submission of false claims by providing inaccurate coding or billing information to actual or prospective purchasers, and our business practices could be subject to scrutiny and enforcement under the Federal False Claims Act. We also may be subject to other federal false claim laws, including federal criminal statutes that prohibit making a false statement to the federal government.
Civil Monetary Penalties Law. We are also subject to the Federal Civil Monetary Penalties Law, which prohibits, among other things, the offering or transferring of remuneration to a Medicare or Medicaid beneficiary that the person knows or should know is likely to influence the beneficiary’s selection of a particular supplier of Medicare or Medicaid payable items or services. Noncompliance can result in significant civil money penalties for each wrongful act, assessment of three times the amount claimed for each item or service and exclusion from the federal healthcare programs.
Federal Health Care Fraud Statutes. We are also subject to a federal health care fraud statute that, among other things, imposes criminal and civil liability for executing a scheme to defraud any health care benefit program including non-governmental programs, and prohibits knowingly and willfully falsifying, concealing or covering up a material fact or making any materially false or fraudulent statement or representation, or making or using any false writing or document with knowledge that it contains a materially false or fraudulent statement in connection with the delivery of or payment for health care benefits, items or services.
State Fraud and Abuse Laws and Marketing Restrictions. Many states have also adopted anti-kickback, anti-referral laws, and false claims laws and regulations analogous to the Federal civil Anti-Kickback Statute and Federal False Claims Act, and in some cases these state laws apply regardless of the payer, including private payors. We believe that we are in conformance with such laws. Moreover, several states have imposed requirements to disclose payments to health care providers, restrictions on marketing and other expenditures, and requirements to adopt a code of conduct or compliance program with specific elements. Nevertheless, a determination of liability under such laws could result in fines and penalties and restrictions on our ability to operate in these jurisdictions.
Administrative Simplification of the Health Insurance Portability and Accountability Act of 1996. The Health Insurance Portability and Accountability Act of 1996 (“HIPAA”) mandated the adoption of standards for the exchange of electronic health information in an effort to encourage overall administrative simplification and enhance the effectiveness and efficiency of the healthcare industry. Ensuring privacy and security of patient information is one of the key factors driving the legislation. If we are found to be in violation of HIPAA, we could be subject to civil or criminal penalties.
Patient Protection and Affordable Care Act. The Patient Protection and Affordable Care Act as amended by the Health Care and Education Reconciliation Act of 2010 (“ACA”) enacted significant changes to the provision of and payment for healthcare in the United States. Under the ACA and related laws and regulations, federal and state government initiatives are focused on limiting the growth of healthcare costs and implementing changes to healthcare delivery structures. These reforms are intended in part to put increased emphasis on the delivery to patients of more cost-effective therapies and could adversely affect our business. Certain changes to the ACA in the 115th United States Congress and under the Trump Administration have occurred and additional changes remain possible. Such changes could adversely affect our business. While some uncertainty exists regarding the future aspects of the ACA, we expect that the ACA will continue to have a significant impact on the delivery of healthcare in the United States and on our business in the near term.
Physician Payments Sunshine Act. The Physician Payments Sunshine Act, implemented as the Open Payments program, requires manufacturers of drugs and devices for which Medicare or Medicaid payment is available to track and report payments and other transfers of value provided to physicians and teaching hospitals, as well as ownership and investment interests held by physician and their immediate family members. Our failure to disclose reportable payments could subject us to penalties and materially adversely impact our business and financial results.
Additionally, as these laws and regulations continue to evolve, we lack definitive guidance as to the application of certain key aspects of these laws and regulations as they relate to certain of our arrangements and programs, including those with providers with respect to patient training. We cannot predict the final form of these federal and state regulations or the effect that application of those interpretations will have on us. As a result, our provider and training arrangements may ultimately be found not to be in compliance with applicable federal law. Even if we are not found to have violated the law, responding to lawsuits, government investigations or enforcement actions, defending any claims raised, and paying any resulting settlement amounts would be expensive and time-consuming, and could have a material adverse effect on our reputation and business operations.
Third-Party Reimbursement
In the United States, our products are generally reimbursed by third-party payors, and we bill those payors for products provided to patients. Our fulfillment and reimbursement systems are fully integrated such that product is generally shipped only after confirmation of a physician’s valid statement of medical necessity and current health insurance information. We maintain an insurance benefits investigation department that works to simplify and expedite claims processing and to assist patients in obtaining third-party reimbursement.
We continue to work with third-party payors in the United States to establish coverage and payment for the Omnipod System. Our coverage contracts with third-party payors typically have a term of between one and three years and set coverage amounts during that term. Typically, coverage contracts automatically renew for specified incremental periods upon expiration, unless one of the parties terminates the contract.
Common medical criteria for third-party payors approving reimbursement for CSII therapy include a patient having elevated A1c levels, a history of recurring hypoglycemia, fluctuations in blood glucose levels prior to meals or upon waking or, severe glycemic variability. Third-party payors may decline to reimburse for procedures, supplies or services determined not to be “medically necessary” or “reasonable.” In a limited number of cases, some third-party payors have declined to reimburse us for a particular patient because such patient failed to meet its criteria, most often because the patient already received reimbursement for an insulin pump from that payor within the warranty period, which is generally four years, or because the patient did not meet their medical criteria for an insulin infusion device. Reimbursement may also be declined by insurers based upon language in the contract between the insurer and the insured group. An example of this is certain employer self-insurance plans that may choose to decline coverage based on specific provisions within those individual plans.
Historically, there had not been an established mechanism for Medicare or broad Medicaid coverage for the majority of the Omnipod System. However, in January 2018, the CMS issued guidance clarifying that Medicare Part D Plan Sponsors are permitted to provide coverage for products such as the Omnipod System under the Medicare Part D (prescription drug) program. We have begun discussions with Medicare Part D Plan Sponsors to be listed on their formularies, which will allow many additional people with diabetes to begin accessing our product. Medicare Part D Plan Sponsors will be submitting bids to the government in the Spring of 2018 that include their formularies for 2019 plans.
The ability of Medicare Part D plans to cover the Omnipod System also provides us with a direct pathway to gain Medicaid coverage at the state level, as many state-run Medicaid programs follow CMS prescription drug guidance to determine coverage. This allows access for lower-income individuals and families on Medicaid for whom Omnipod is currently not an option. The Company estimates that obtaining Medicare and Medicaid coverage extends access to Insulet's Omnipod System to approximately 450,000 additional individuals with Type 1 diabetes in the United States.
As part of our international distribution agreements, our distribution partners establish appropriate reimbursement contracts with third-party payors in countries and provinces in which they distribute the Omnipod System prior to distributing the Omnipod System in each territory. In anticipation of our transition to direct distribution and commercial support of our product in Europe upon the expiration of our European distribution agreement in June 2018, we are working with local payors to establish coverage and a payment process for our Omnipod System.
Employees
As of December 31, 2017, we had 857 full-time employees. None of our employees are represented by a collective bargaining agreement, and we have never experienced any work stoppage. We believe that our employee relations are good.
Company Information
Insulet Corporation is a Delaware corporation formed in 2000. Our principal offices are located at 600 Technology Park Drive, Suite 200, Billerica, Massachusetts 01821, and our telephone number is (978) 600-7000. Our website address is http://www.insulet.com. We make available, free of charge, on or through our website, our annual reports on Form 10-K, quarterly reports on Form 10-Q, current reports on Form 8-K, proxy statements and any amendments to those reports filed or furnished pursuant to Section 13(a) or 15(d) of the Securities Exchange Act of 1934, as amended, as soon as reasonably practicable after such material is electronically filed with or furnished to the Securities and Exchange Commission. The information on our website is not part of this Annual Report on Form 10-K for the year ended December 31, 2017.
Item 1A. Risk Factors
This Annual Report on Form 10-K contains forward-looking statements. Forward-looking statements relate to future events or our future financial performance.
We generally identify forward looking statements by terminology such as “may,” “will,” “should,” “expects,” “plans,” “anticipates,” “could,” “intends,” “targets,” “projects,” “contemplates,” “believes,” “estimates,” “predicts,” “potential” or “continue” or the negative of these terms or other similar words. These statements are only predictions. We have based these forward-looking statements largely on our current expectations and projections about future events and financial trends that we believe may affect our business, results of operations and financial condition.
The outcomes of the events described in these forward-looking statements are subject to risks, uncertainties and other factors described in this Item 1A Risk Factors and elsewhere in this Annual Report on Form 10-K. Accordingly, you should not rely upon forward-looking statements as predictions of future events. We cannot assure you that the events and circumstances reflected in the forward-looking statements will be achieved or occur, and actual results could differ materially from those projected in the forward-looking statements. The forward-looking statements made in this Annual Report on Form 10-K relate only to events as of the date of this report. We undertake no obligation to update any forward-looking statement to reflect events or circumstances after the date on which the statement is made or to reflect the occurrence of unanticipated events.
Risks Relating to Our Business
We have incurred significant operating losses since inception and cannot assure you that we will achieve profitability.
Since our inception in 2000, we have incurred significant operating losses. We began commercial sales of the Omnipod System in 2005. For the year ended December 31, 2017, our operating loss was $7.4 million. Our net losses for the years ended December 31, 2017, 2016 and 2015 were $26.8 million, $28.9 million and $73.5 million, respectively. The extent of our future operating losses and the timing of profitability are uncertain, and we may never achieve or sustain profitability. As of December 31, 2017, we had an accumulated deficit of $707.3 million.
We may experience significant fluctuations in our quarterly results of operations.
The fluctuations in our quarterly results of operations have resulted, and may continue to result, from numerous factors, including:
| • | delays in shipping due to capacity constraints; |
| • | practices of health insurance companies and other third-party payors with respect to reimbursement for our current or future products; |
| • | market acceptance of the Omnipod System; |
| • | our ability to manufacture the Omnipod System efficiently; |
| • | transitions in our distribution channel; |
| • | timing of regulatory approvals and clearances; |
| • | new product introductions; |
| • | competition; and |
| • | timing of research and development expenditures. |
These factors, some of which are not within our control, may cause the price of our stock to fluctuate substantially. In particular, if our quarterly results of operations fail to meet or exceed the expectations of securities analysts or investors, our stock price could drop suddenly and significantly. We believe the quarterly comparisons of our financial results are not necessarily meaningful and should not be the only indication of our future performance.
We currently rely on sales of the Omnipod System to generate most of our revenue. The failure of the Omnipod System to achieve and maintain significant market acceptance or any factors that negatively impact sales of this product will adversely affect our business, financial condition and results of operations.
Our main product is the Omnipod System, which we introduced to the market in 2005. We expect to continue to derive a significant portion of our revenue from the sale of this product. Accordingly, our ability to generate revenue is highly reliant on our ability to market and sell the devices that comprise the Omnipod System. Our sales of the Omnipod System may be negatively impacted by many factors, including:
| • | the failure of the Omnipod System to achieve and maintain wide acceptance among opinion leaders in the diabetes treatment community, insulin-prescribing physicians, third-party payors and people with insulin-dependent diabetes; |
| • | manufacturing problems or capacity constraints; |
| • | actual or perceived quality problems; |
| • | changes in reimbursement rates or policies relating to the Omnipod System by third-party payors; |
| • | claims that any portion of the Omnipod System infringes on patent rights or other intellectual property rights owned by other parties; |
| • | adverse regulatory or legal actions relating to the Omnipod System; |
| • | damage, destruction or loss of any of the facilities where our products are manufactured or stored or of the equipment therein or failure to successfully open or expand new facilities; |
| • | conversion rate of patient referrals to actual sales of the Omnipod System; |
| • | write-offs of receivables from customers; |
| • | attrition rates of customers who cease using the Omnipod System; |
| • | competitive pricing and related factors; and |
| • | results of clinical studies relating to the Omnipod System or our competitors’ products. |
If any of these events occurs, our ability to generate revenue could be significantly reduced.
Our ability to achieve profitability from a current net loss level will depend on our ability to sustain or reduce the per unit cost of producing the Omnipod System by increasing customer orders, increasing manufacturing volume and productivity and reducing raw material and overhead costs per unit.
Currently, the gross profit from the sale of the Omnipod System is not sufficient to cover our operating expenses. To achieve profitability, we need to, among other things, sustain or reduce the per unit cost of the Omnipod System. If we are unable to sustain or reduce raw material and manufacturing overhead costs through volume purchase discounts, negotiation of improved pricing and increased productivity and production capacity, our ability to achieve profitability will be severely constrained. Any increase in manufacturing volumes must be supported by an associated increase in customer orders. Each Omnipod System contains limited amounts of precious metals, the costs of which have fluctuated over the recent past. The occurrence of one or more factors that negatively impact the manufacturing or sales of the Omnipod System or increase our raw material costs may prevent us from achieving our desired increase in manufacturing volume, which would prevent us from attaining profitability.
Adverse changes in general economic conditions in the United States and globally could adversely affect us.
We are subject to the risks arising from adverse changes in general economic market conditions. A U.S. or global recession, could negatively impact our current and prospective customers, adversely affect the financial ability of health insurers to pay claims, adversely impact our expenses and ability to obtain financing of our operations, cause delays or other problems with key suppliers and increase the risk of counterparty failures.
Healthcare spending in the United States, Canada and Europe could be negatively affected in the event
Showing the first 8K of 104K characters. Open the full section
Item 1B. Unresolved Staff Comments
None.
Item 2. Properties
We lease a total of approximately 143,000 square feet of office space, laboratory, warehousing and other related facilities. Approximately 100,000 of the total square footage consists of laboratory and office space for our corporate headquarters in Billerica, Massachusetts under leases expiring in November 2022.
Additionally, we lease approximately 29,000 square feet of warehousing space in Billerica, Massachusetts under a lease expiring in September 2019. We lease other facilities in Canada, China, the United Kingdom, California and Tennessee containing a total of approximately 14,000 square feet under leases expiring from April 2018 to December 2020.
In December 2016, we purchased property for our U.S. manufacturing facility in Acton, Massachusetts. The property includes 195,000 square feet of manufacturing and office space.
Item 3. Legal Proceedings
The information required by this Item is provided under "Legal Proceedings" in Note 12 to the consolidated financial statements included under Item 8 of this Form 10-K, and is incorporated herein by reference.
Item 4. Mine Safety Disclosures
Not applicable.
PART II
Item 5. Market for Registrant's Common Equity, Related Stockholder Matters and Issuer Purchases of Equity Securities
MARKET FOR REGISTRANT'S COMMON EQUITY
Our common stock has been listed on The NASDAQ Global Market under the trading symbol “PODD” since our initial public offering on May 15, 2007. The following table sets forth the high and low closing sales prices of our common stock, as reported by The NASDAQ Global Market, for each of the periods listed.
| High | Low | ||||||
| Fiscal Year 2016 | |||||||
| First Quarter | $ | 37.54 | $ | 24.68 | |||
| Second Quarter | $ | 35.15 | $ | 26.89 | |||
| Third Quarter | $ | 45.07 | $ | 30.46 | |||
| Fourth Quarter | $ | 40.72 | $ | 30.73 | |||
| Fiscal Year 2017 | |||||||
| First Quarter | $ | 47.22 | $ | 36.98 | |||
| Second Quarter | $ | 51.31 | $ | 39.10 | |||
| Third Quarter | $ | 59.46 | $ | 49.49 | |||
| Fourth Quarter | $ | 71.80 | $ | 55.67 |
As of February 16, 2018, there were approximately 11 registered holders of record of our common stock. The number of beneficial stockholders of our shares is greater than the number of stockholders of record.
Performance Graph
The chart set forth below shows the value of an investment of $100 on December 31, 2012 in each of Insulet Corporation common stock, the NASDAQ Composite Index, and the NASDAQ Health Care Index. All values assume reinvestment of the pre-tax value of dividends paid by companies included in these indices and are calculated as of December 31, 2017. The historical stock price performance of our common stock shown in the performance graph below is not necessarily indicative of future stock price performance.
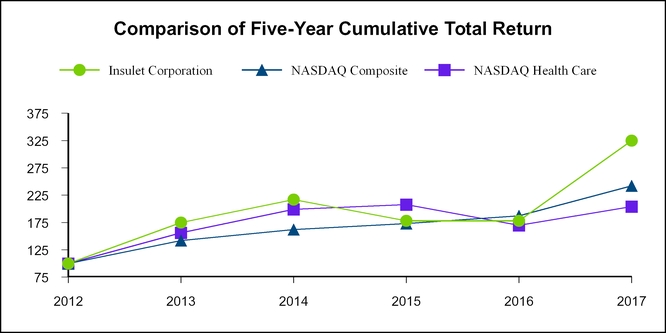
| 2012 | 2013 | 2014 | 2015 | 2016 | 2017 | |||||||||||||
| Insulet Corporation | $ | 100 | $ | 175 | $ | 217 | $ | 178 | $ | 178 | $ | 325 | ||||||
| NASDAQ Composite | 100 | 142 | 162 | 173 | 187 | 242 | ||||||||||||
| NASDAQ Health Care | 100 | 156 | 199 | 208 | 170 | 204 |
The material in this performance graph is not soliciting material, is not deemed filed with the Securities and Exchange Commission (“SEC”) and is not incorporated by reference in any filing of Insulet Corporation under the Securities Act of 1933, as amended (the “Securities Act”) or the Exchange Act of 1934, as amended, whether made on, before or after the date of this filing and irrespective of any general incorporation language in such filing.
Dividend Policy
We currently intend to retain future earnings for the development, operation and expansion of our business and do not anticipate paying any cash dividends in the foreseeable future.
Securities Authorized For Issuance Under Equity Compensation Plans
The following table sets forth information regarding securities authorized for issuance under our equity compensation plans as of December 31, 2017.
| Plan Category | Number of securities to be issued upon exercise of outstanding options, warrants and rights (a) | Weighted average exercise price of outstanding options, warrants and rights (b) | Number of securities remaining available for future issuance under equity compensation plans (excluding securities reflected in column (a)) (c) | |||||||
| Equity compensation plans approved by security holders(1) | 3,598,462 | $ | 35.10 | 5,058,556 | ||||||
| Equity compensation plans not approved by security holders(2) | 773,122 | $ | 35.08 | — | ||||||
| Total(4) | 4,371,584 | $ | 35.10 | 5,058,556 | (3) |
(1) Includes our Amended and Restated 2007 Stock Option and Incentive Plan. Outstanding restricted stock units convert to common stock without the payment of consideration. As of December 31, 2017, 860,123 restricted stock units were outstanding. The weighted-average exercise price of outstanding options as of such date issued under these Plans (excluding restricted stock units) was $32.76.
(2) Consists of the following inducement grants made to certain executive officers upon their initial hire by us:
| • | one inducement grant of 499,468 shares of non-qualified stock option awards made to Patrick J. Sullivan upon being hired by us in September 2014; |
| • | one inducement grant of 26,756 non-qualified stock options made to Bradley Thomas upon being hired by us in November 2014; |
| • | one inducement grant of 79,936 non-qualified stock options and 56,965 restricted stock units (37,976 of which have vested as of December 31, 2017) made to Shacey Petrovic upon being hired by us in February 2015; |
| • | one inducement grant of 58,852 non-qualified stock options and 43,028 restricted stock units (28,685 of which have vested as of December 31, 2017) made to Michael Levitz upon being hired by us in May 2015; |
| • | one inducement grant of 29,581 non-qualified stock options and 21,627 restricted stock units (14,418 of which have vested as of December 31, 2017) made to David Colleran upon being hired by us in June 2015; and |
| • | one inducement grant of 30,511 non-qualified stock options and 22,431 restricted stock units (14,954 of which have vested as of December 31, 2017) made to Michael Spears upon being hired by us in July 2015. |
These non-qualified stock option awards and restricted stock units were granted outside of our Amended and Restated 2007 Stock Option and Incentive Plan in compliance with Nasdaq Listing Rule 5635.
(3) The maximum number of shares of our common stock that remain available for future issuance under our 2017 Stock Option and Incentive Plan as of December 31, 2017 is 5,058,556 shares.
(4) As of December 31, 2017, 994,364 restricted stock units were outstanding. The weighted-average exercise price of outstanding options as of such date issued as inducement grants was $35.08.
For more information relating to our equity compensation plans, see footnote 13 to our consolidated financial statements.
Issuer Repurchases of Equity Securities
We did not repurchase any of our equity securities during the quarter ended December 31, 2017, nor issue any securities that were not registered under Securities Act.
Purchases of Equity Securities by the Issuer and Affiliated Purchasers
None.
Item 6. Selected Financial Data
| Years Ended December 31, | |||||||||||||||||||
| (In thousands, except share and per share data) | 2017 | 2016 | 2015 | 2014 | 2013 | ||||||||||||||
| Consolidated Statements of Operations Data: | |||||||||||||||||||
| Revenue | $ | 463,768 | $ | 366,989 | $ | 263,893 | $ | 231,321 | $ | 185,139 | |||||||||
| Cost of revenue | 186,599 | 155,903 | 130,622 | 104,195 | 95,364 | ||||||||||||||
| Gross profit | 277,169 | 211,086 | 133,271 | 127,126 | 89,775 | ||||||||||||||
| Operating expenses: | |||||||||||||||||||
| Research and development | 74,452 | 55,710 | 43,208 | 27,900 | 21,765 | ||||||||||||||
| Sales and marketing | 121,617 | 94,483 | 78,407 | 50,552 | 45,176 | ||||||||||||||
| General and administrative (1) | 88,487 | 71,597 | 60,392 | 57,548 | 49,509 | ||||||||||||||
| Total operating expenses | 284,556 | 221,790 | 182,007 | 136,000 | 116,450 | ||||||||||||||
| Operating loss | (7,387 | ) | (10,704 | ) | (48,736 | ) | (8,874 | ) | (26,675 | ) | |||||||||
| Interest expense and other, net (3) | (19,187 | ) | (16,114 | ) | (12,654 | ) | (39,006 | ) | (15,783 | ) | |||||||||
| Loss from continuing operations before income taxes | (26,574 | ) | (26,818 | ) | (61,390 | ) | (47,880 | ) | (42,458 | ) | |||||||||
| Income tax expense (benefit) | 257 | 392 | 212 | 60 | 22 | ||||||||||||||
| Net loss from continuing operations | (26,831 | ) | (27,210 | ) | (61,602 | ) | (47,940 | ) | (42,480 | ) | |||||||||
| Loss from discontinued operations, net of tax(2) | — | (1,669 | ) | (11,918 | ) | (3,560 | ) | (2,494 | ) | ||||||||||
| Net loss | $ | (26,831 | ) | $ | (28,879 | ) | $ | (73,520 | ) | $ | (51,500 | ) | $ | (44,974 | ) | ||||
| Net loss per share basic and diluted: | |||||||||||||||||||
| Net loss from continuing operations per share | (0.46 | ) | (0.48 | ) | (1.08 | ) | (0.86 | ) | (0.78 | ) | |||||||||
| Net loss from discontinued operations per share | — | (0.03 | ) | (0.21 | ) | (0.06 | ) | (0.05 | ) | ||||||||||
| Weighted-average number of shares used in calculating net loss per share | 58,003,434 | 57,251,377 | 56,785,646 | 55,628,542 | 54,010,887 | ||||||||||||||
| As of December 31, | |||||||||||||||||||
| (In thousands) | 2017 | 2016 | 2015 | 2014 | 2013 | ||||||||||||||
| Consolidated Balance Sheets Data: | |||||||||||||||||||
| Cash and cash equivalents | $ | 272,577 | $ | 137,174 | $ | 122,672 | $ | 151,193 | $ | 149,727 | |||||||||
| Short-term investments | $ | 167,479 | $ | 161,396 | $ | — | $ | — | $ | — | |||||||||
| Working capital | $ | 451,146 | $ | 314,263 | $ | 125,605 | $ | 163,900 | $ | 155,824 | |||||||||
| Long-term investments | $ | 125,549 | $ | — | $ | — | $ | — | $ | — | |||||||||
| Total assets | $ | 816,744 | $ | 456,647 | $ | 275,126 | $ | 297,182 | $ | 286,541 | |||||||||
| Current portion of long-term debt and capital lease obligations | $ | — | $ | 269 | $ | 5,519 | $ | 3,380 | $ | 2,637 | |||||||||
| Long-term debt and capital lease obligations(3) | $ | 566,173 | $ | 332,768 | $ | 171,967 | $ | 166,283 | $ | 117,627 | |||||||||
| Other long-term liabilities | $ | 6,030 | $ | 5,032 | $ | 3,952 | $ | 2,774 | $ | 1,943 | |||||||||
| Total stockholders’ equity | $ | 158,516 | $ | 63,150 | $ | 34,051 | $ | 83,829 | $ | 124,597 |
| (1) | Includes a charge of $6.1 million related to in-process internally developed software in 2016. |
| (2) | Includes an impairment charge of $9.0 million in 2015 related to the impairment of the Neighborhood Diabetes asset group. See Note 19 to our consolidated financial statements included in this Annual Report on Form 10-K. |
| (3) | In June 2008, we issued and sold $85.0 million principal amount of 5.375% Convertible Senior Notes due June 2013. In June 2011, we issued and sold $143.8 million of 3.75% Convertible Notes due June 2016 and repurchased $70 million in principal of the 5.375% Notes. In June 2014, we issued and sold $201.3 million of 2% Convertible Notes due June 2019 and repurchased $114.9 million in 3.75% Notes. In July 2014, the remaining principal balance of the 3.75% Notes were converted and the principal was settled in cash. In September 2016, we issued $345.0 million of 1.25% Convertible Notes due September 2021 and repurchased $134.2 million in principal of the 2% Notes. In November 2017, we issued $402.5 million of 1.375% Convertible Notes due November 2024 and repurchased $63.4 million in principal of the 2% Notes. See Note 11 to our consolidated financial statements included in this Annual Report on Form 10-K. |
Item 7. Management's Discussion and Analysis of Financial Condition and Results of Operations
Executive Level Overview
We are primarily engaged in the development, manufacturing and sale of our proprietary Omnipod System, an innovative, discreet and easy-to-use continuous insulin delivery system for people with insulin-dependent diabetes. The Omnipod System features a small, lightweight, self-adhesive disposable tubeless Omnipod device, which is worn on the body for approximately three days at a time, and its wireless companion, the handheld PDM. Conventional insulin pumps require people with insulin-dependent diabetes to learn to use, manage and wear a number of cumbersome components, including up to 42 inches of tubing. In contrast, the Omnipod System features only two discreet, easy-to-use devices that eliminate the need for a bulky pump and tubing, provides for virtually pain-free automated cannula insertion, communicates wirelessly and integrates a blood glucose meter. We believe that the Omnipod System’s unique proprietary design and features allow people with insulin-dependent diabetes to manage their diabetes with unprecedented freedom, comfort, convenience, and ease.
We began commercial sale of the Omnipod System in the United States in 2005. We sell the Omnipod System in the United States through direct sales to customers or through our distribution partners. The Omnipod System is currently available in multiple countries in Europe, as well as Canada and Israel.
In addition to the diabetes market space, we have partnered with pharmaceutical and biotechnology companies that utilize a customized form of the Omnipod System to deliver a drug over a specified interval of time, at a certain administered volume. The majority of our drug delivery revenue currently consists of sales of Amgen's Neulasta Onpro kit.
We are constructing a highly-automated manufacturing facility in Acton, Massachusetts, with planned production out of the facility beginning in early 2019. The facility will also serve as our global headquarters. We expect that the new facility will allow us to lower our manufacturing costs, increase supply redundancy, add capacity closer to our largest customer base and support growth. We expect capital expenditures for the construction of the Acton facility and related equipment purchases will approach $200 million when production begins in 2019 and will be funded by our cash flows from operations and proceeds from our senior convertible debt offerings.
We announced on July 20, 2017 our plans to assume, on July 1, 2018, all commercial activities (including, among other things, distribution, sales, marketing, training and support) of our Omnipod System across Europe following the expiration of our distribution agreement with our European distributor on June 30, 2018. Once we assume commercial activities following the expiration of the current distribution agreement, we expect our revenue and gross margins to increase, as average customer pricing in Europe is higher than the current distributor pricing to our European distributor. Throughout 2018, we expect to incur increased operating expenses as we invest in our European operations. Once European operations are established, excluding nonrecurring transition-related costs, we expect that the assumption of direct distribution will be accretive to our consolidated results of operations.
Highlights and Recent Developments:
| • | In January 2018, we announced that CMS has issued guidance clarifying that Medicare Part D Plan Sponsors are permitted to provide coverage for products such as the Omnipod System under the Medicare Part D (prescription drug) program. The CMS guidance empowers us to begin working with Medicare Part D carriers to ensure beneficiaries living with diabetes have access to the Omnipod System. Securing Medicare Part D coverage also provides us with a direct pathway to gain Medicaid coverage at the state level, as many state-run Medicaid programs follow CMS prescription drug guidance to determine coverage. This allows access for lower-income individuals and families on Medicaid for whom Omnipod currently is not a covered option. The Company estimates that obtaining Medicare and Medicaid coverage extends Omnipod System coverage access to approximately 450,000 additional individuals with Type 1 diabetes in the United States. |
| • | Also in January 2018, we submitted a premarket notification 510(k) to the FDA requesting clearance for commercial distribution of our DASH TM System, which is our next generation of the Omnipod System, featuring a secured Bluetooth Low Energy enabled Pod and PDM with a touch screen color user interface |
supported by smartphone connectivity. Upon clearance, we would begin a limited commercial release of the product prior to a full market launch.
| • | In November 2017, we issued and sold $402.5 million in principal amount of 1.375% Convertible Senior Notes due in 2024 and repurchased $63.4 million in principal amount of our 2.0% Convertible Senior Notes due in 2019. |
| • | In July 2017, we announced plans to assume distribution and commercial support for the Omnipod System in Europe as further discussed above. We believe that our strategy of accessing our customers directly in Europe will allow us to have better control over existing and future markets, be closer to our customers, gain a better understanding of innovation needs specific to the European market, and expand our customer base. |
| • | During 2017, we began construction of our new, highly-automated U.S. manufacturing facility in Acton, Massachusetts. We believe that this manufacturing facility will allow us to lower our manufacturing costs, increase supply redundancy, add capacity closer our growing U.S. customer base and support our growth. The facility will also serve as our global headquarters. |
2017 Revenue Results:
| • | Total revenue of $463.8 million |
| ◦ | U.S. Omnipod revenue of $271.6 million, an 18% increase year over year |
| ◦ | International Omnipod revenue of $120.0 million, a 67% increase year over year |
| ◦ | Drug Delivery revenue of $72.2 million, an 11% increase year over year |
Our long-term financial objective is to achieve and sustain profitable growth. We expect our efforts in 2018 and 2019 to focus primarily on the construction and commissioning of our U.S. manufacturing facility, the establishment of our European operations, the launch of new products, such as the DASH TM Omnipod System, continuing our product development efforts, and taking the necessary actions such as amending or creating payor or distributor contracts to allow us to service patients who receive benefits through the Medicare Part D and Medicaid programs. Achieving these objectives is expected to require additional investments in certain personnel and initiatives, as well as enhancements to our supply chain operation capacity, efficiency and effectiveness. We believe that we will continue to incur net losses in the near term in order to achieve these objectives. However, we believe that the accomplishment of our near term objectives will have a positive impact on our financial condition in the future.
Components of Financial Operations
Revenue. We derive most of our revenue from global sales of the Omnipod System. Our revenue also includes sales of devices based on the Omnipod System technology platform to global pharmaceutical and biotechnology companies for the delivery of subcutaneous drugs across multiple therapeutic areas.
Cost of revenue. Cost of revenue consists primarily of raw material, labor, warranty, inventory reserve and overhead costs such as freight-in and depreciation, and the cost of products we acquire from third party suppliers.
Research and development. Research and development expenses consist primarily of personnel costs and outside services within our product development, regulatory and clinical functions, and product development projects. We generally expense research and development costs as incurred.
Sales and marketing. Sales and marketing expenses consist primarily of personnel costs within our sales, marketing, reimbursement support, customer care and training functions, sales commissions paid to our sales representatives, costs associated with promotional activities and participation in industry trade shows.
General and administrative. General and administrative expenses consist primarily of salaries and other related costs for personnel serving the executive, finance, legal, information technology and human resource functions, as well as legal fees, accounting fees, insurance costs, bad debt expenses, shipping, handling and facilities-related costs.
Results of Operations
This section discusses our consolidated results of operations for 2017 compared to 2016, as well as 2016 compared to 2015, and should be read in conjunction with the consolidated financial statements and accompanying notes included under Item 8 of this Form 10-K.
| TABLE 1: RESULTS OF OPERATIONS | |||||||||||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Years Ended December 31, | Years Ended December 31, | ||||||||||||||||||||||||||||
| (In Thousands) | 2017 | 2016 | $ Change | % Change | 2016 | 2015 | $ Change | % Change | |||||||||||||||||||||
| Revenue | |||||||||||||||||||||||||||||
| U.S. Omnipod | $ | 271,597 | $ | 229,785 | $ | 41,812 | 18 | % | $ | 229,785 | $ | 189,604 | $ | 40,181 | 21 | % | |||||||||||||
| International Omnipod | 119,953 | 71,889 | 48,064 | 67 | % | 71,889 | 40,339 | 31,550 | 78 | % | |||||||||||||||||||
| Drug Delivery | 72,218 | 65,315 | 6,903 | 11 | % | 65,315 | 33,950 | 31,365 | 92 | % | |||||||||||||||||||
| Total Revenue | 463,768 | 366,989 | 96,779 | 26 | % | 366,989 | 263,893 | 103,096 | 39 | % | |||||||||||||||||||
| Cost of revenue | 186,599 | 155,903 | 30,696 | 20 | % | 155,903 | 130,622 | 25,281 | 19 | % | |||||||||||||||||||
| Gross profit | 277,169 | 211,086 | 66,083 | 31 | % | 211,086 | 133,271 | 77,815 | 58 | % | |||||||||||||||||||
| Gross margin | 59.8 | % | 57.5 | % | 2.3 | 57.5 | % | 50.5 | % | 7 | |||||||||||||||||||
| Operating expenses: | |||||||||||||||||||||||||||||
| Research and development | 74,452 | 55,710 | 18,742 | 34 | % | 55,710 | 43,208 | 12,502 | 29 | % | |||||||||||||||||||
| Sales and marketing | 121,617 | 94,483 | 27,134 | 29 | % | 94,483 | 78,407 | 16,076 | 21 | % | |||||||||||||||||||
| General and administrative | 88,487 | 71,597 | 16,890 | 24 | % | 71,597 | 60,392 | 11,205 | 19 | % | |||||||||||||||||||
| Total operating expenses | 284,556 | 221,790 | 62,766 | 28 | % | 221,790 | 182,007 | 39,783 | 22 | % | |||||||||||||||||||
| Operating loss | (7,387 | ) | (10,704 | ) | (3,317 | ) | (31 | )% | (10,704 | ) | (48,736 | ) | (38,032 | ) | (78 | )% | |||||||||||||
| Interest expense and other, net | (19,187 | ) | (16,114 | ) | (3,073 | ) | 19 | % | (16,114 | ) | (12,654 | ) | (3,460 | ) | 27 | % | |||||||||||||
| Loss from continuing operations before income taxes | (26,574 | ) | (26,818 | ) | (244 | ) | (1 | )% | (26,818 | ) | (61,390 | ) | (34,572 | ) | (56 | )% | |||||||||||||
| Income tax expense | 257 | 392 | (135 | ) | (34 | )% | 392 | 212 | 180 | 85 | % | ||||||||||||||||||
| Net loss from continuing operations | (26,831 | ) | (27,210 | ) | (379 | ) | (1 | )% | (27,210 | ) | (61,602 | ) | (34,392 | ) | (56 | )% | |||||||||||||
| Loss from discontinued operations, net of tax | — | (1,669 | ) | (1,669 | ) | (100 | )% | (1,669 | ) | (11,918 | ) | (10,249 | ) | (86 | )% | ||||||||||||||
| Net loss | $ | (26,831 | ) | $ | (28,879 | ) | $ | 2,048 | (7 | )% | $ | (28,879 | ) | $ | (73,520 | ) | $ | 44,641 | (61 | )% |
Comparison of the Years Ended December 31, 2017 and December 31, 2016
Revenue
Our total revenue increased to $463.8 million, up $96.8 million, or 26%, in 2017 compared to 2016, due to strong growth in our International Omnipod revenue, our U.S. Omnipod revenue and our on-body injection device for drug delivery. Our International Omnipod revenue increased to $120.0 million, up $48.1 million, or 67%, primarily due to growth in distributor sales from continued adoption in existing and newer markets within Europe such as France. Our U.S. Omnipod revenue increased to $271.6 million, up $41.8 million, or 18%, primarily due to growth in our installed base as we continue to expand awareness of the Omnipod System. Our drug delivery revenue increased to $72.2 million, up $6.9 million, or 11%, due to growth in demand for our primary drug delivery device on greater market adoption of Amgen's Neulasta Onpro kit.
For 2018, we expect strong revenue growth driven by our expansion in the U.S. and internationally, as well as the transition to direct distribution of our Omnipod System across Europe following the expiration of our global distribution agreement with our European distributor on June 30, 2018, partially offset by lower drug delivery revenue.
Cost of Revenue
Cost of revenue increased to $186.6 million, up $30.7 million, or 20%, in 2017 compared to 2016, primarily due to an increase in sales volumes, partially offset by improvements in supply chain operations in 2017.
Gross Margin
Gross margin increased to 59.8%, up approximately 2.3 points, in 2017 compared to 2016. The increase in gross margin was primarily due to improvements in supply chain operations, partially offset by the unfavorable mix impact of higher distributor sales in Europe. For 2018, we expect gross margin to increase as compared to 2017 primarily due to improvements in supply chain operations and our assumption of distribution of our Omnipod System in Europe in the second half of 2018.
Research and Development
Research and development expenses increased to $74.5 million, up $18.7 million, or 34%, in 2017 compared to 2016. The increase in research and development expenses in the current period was primarily due to an increase in expenses related to our development projects, including our digital mobile Omnipod platform, which involves interaction with continuous glucose monitoring technology, our concentrated insulin program and our artificial pancreas program. For 2018, we expect overall research and development spending to increase as compared to 2017 primarily due to the development efforts on our ongoing projects.
Sales and Marketing
Sales and marketing expenses increased to $121.6 million, up $27.1 million, or 29%, for 2017, compared to 2016. The increase in sales and marketing expenses in the current period was primarily due increased personnel-related expenses associated with the expansion of our customer support, market access and sales force personnel, investments to support our assumption in mid-2018 of direct commercial support for Omnipod in Europe, and increased advertising expenses associated with direct to patient marketing activities. We expect sales and marketing expenses in 2018 to increase as compared to 2017 due to the expansion of our sales force and customer support personnel and establishment of direct commercial operations in Europe.
General and Administrative
General and administrative expenses increased to $88.5 million, up $16.9 million, or 24%, for 2017, compared to 2016. The increase in general and administrative expenses in the current period was primarily attributable to increased personnel-related costs and fees related to external consultants and professional service providers to support the growth in our business. For 2018, we expect overall general and administrative expenses to increase as compared to 2017 as we continue to grow the business and make investments in our operating structure to support continued growth as well as the establishment of direct commercial operations in Europe.
Interest Expense and Other, Net
Interest expense and other, net, increased to $19.2 million, up $3.1 million, or 19%, for 2017, compared to 2016. The increase in interest expense and other, net, in the current period was primarily due to a net increase in our outstanding long-term debt, partially offset by lower losses on the extinguishment of debt in 2017. Non-cash interest expense, which includes the amortization of deferred financing and debt issuance costs, increased $7.9 million and cash interest expense increased $1.8 million in 2017 as compared to 2016. These increases were partially offset by a $1.9 million reduction in losses on the extinguishment of debt in 2017, higher capitalization of interest, and higher interest income. We expect that our interest expense and other, net, will increase in 2018 compared to the prior year primarily due to an increase in non-cash interest expense associated with the issuance in November 2017 of our 1.375% Notes, partially offset by higher capitalization of interest due to increased capital expenditures associated with the construction of our Acton, Massachusetts facility.
Income Tax Expense
Income tax expense was not material to our results of operations in the years 2017 or 2016 as we have generated net operating losses to date and have fully reserved our net operating loss carryforwards. For more information on our income tax expense, please refer to Note 15 to the consolidated financial statements.
Comparison of the Years Ended December 31, 2016 and December 31, 2015
Revenue
Our total revenue increased to $367.0 million, up $103.1 million, or 39%, in 2016, compared to 2015, primarily due to strong growth in our U.S. Omnipod revenue, International Omnipod revenue and our on-body injection device for drug delivery. Our U.S. Omnipod revenue increased to $229.8 million, up $40.2 million, or 21%, primarily due to growth in our installed base of Omnipod users which was greatly driven by the expansion in 2015 and 2016 of our sales force and customer support personnel and strategic initiatives introduced in mid-2015 to expand awareness of the Omnipod System. The results for 2015 were also partially impacted by unfavorable distributor ordering patterns in the first quarter of 2015 which stabilized thereafter. Our International Omnipod revenue increased to $71.9 million, up $31.6 million, or 78%, primarily due to growth in distributor sales from continued adoption in existing markets and to a lesser extent from entry into new markets. The results for 2015 included lower International Omnipod sales which partially resulted from unfavorable distributor ordering patterns in the first and second quarters of 2015, which stabilized thereafter. Our drug delivery revenue increased to $65.3 million, up $31.4 million due to strong growth in demand for our primary drug delivery device following regulatory approval in December 2014.
Cost of Revenue
Cost of revenue increased to $155.9 million, up $25.3 million, or 19%, in 2016 compared to 2015, primarily due to an increase in sales volumes, partially offset by $11.5 million of costs incurred during 2015 that were considered non-recurring in nature, along with supply chain operation efficiency and effectiveness improvements made in 2016.
Gross Margin
Gross margin increased to 57.5%, up approximately 7 points, in 2016 compared to 2015, primarily due to $11.5 million of costs incurred in 2015 that were considered non-recurring in nature, along with supply chain operation efficiencies and effectiveness improvements made in 2016.
Research and Development
Research and development expenses increased to $55.7 million, up $12.5 million, or 29%, in 2016 compared to 2015, primarily due to an increase in expenses related to our development projects, including our mobile application development which involves interaction with continuous glucose monitoring technology, artificial pancreas program, development efforts with Eli Lilly and Company for the use of concentrated insulin for patients with higher insulin-resistance and other Omnipod product improvement initiatives.
Sales and Marketing
Sales and marketing expenses increased to $94.5 million, up $16.1 million, or 21%, for 2016 compared to 2015, primarily due to an increase of $16.0 million in personnel-related expenses, including increased incentive compensation costs resulting from growth in the business, as well as costs associated with the expansion in 2015 of our sales force and customer support personnel.
General and Administrative
General and administrative expenses increased to $71.6 million, up $11.2 million, or 19%, for 2016 compared to 2015. This increase includes a charge of $6.1 million related to in-process internally developed software recorded in the fourth quarter of 2016 due to a change in our longer-term enterprise resource planning system requirements. In addition, the increase was also due to a $4.6 million increase that was primarily attributable to personnel-related costs on higher incentive compensation associated with growth in our business, as well as additional staff to support our growth expectations and fees paid for external consultants.
Interest Expense and Other, Net
Interest expense and other income, net increased to $16.1 million, up $3.5 million, or 27% for 2016 compared to 2015, due to $3.0 million of net additional interest expense associated with the issuance of the 1.25% Notes and a $2.6 million charge recorded for the extinguishment of debt related to the repurchase of $134.2 million in principal of the 2% Notes. This was partially offset from a slight decrease in capital lease interest expense.
Income Tax Expense
Income tax expense was not material to our results of operations in the years 2016 or 2015. For more information on our income tax expense, please refer to Note 15 to the consolidated financial statements.
Loss from Discontinued Operations, Net of Tax
The loss from discontinued operations decreased by approximately $10.2 million in 2016, compared to the year ended December 31, 2015. This decrease was primarily the result of a $9.1 million impairment charge recorded in the fourth quarter of 2015 for the long-lived assets of Neighborhood Diabetes which we sold in February 2016. As the Neighborhood Diabetes business was sold in February 2016, 2016 includes less than two months of full operations compared to a full year for 2015.
Liquidity and Capital Resources
As of December 31, 2017, we had $272.6 million in cash and cash equivalents and $293.0 million in short-term and long-term investments. We believe that our current liquidity will be sufficient to meet our projected operating, investing and debt service requirements for at least the next twelve months.
To lower our manufacturing costs, increase supply redundancy, add capacity closer to our largest customer base and support growth, we are constructing a highly-automated manufacturing facility in Acton, Massachusetts, with planned production out of the facility beginning in 2019. This facility will also serve as our global headquarters. As a result, capital expenditures have increased above historic levels to fund the construction of the Acton facility and related equipment purchases. As of December 31, 2017, investments in construction-in-progress related to the Acton facility were approximately $70 million. We expect that capital expenditures for this facility will approach $200 million when production begins in 2019.
In connection with our plans to assume, on July 1, 2018, all commercial activities of our Omnipod System across Europe following the expiration of our distribution agreement with our European distributor on June 30, 2018, we will be required to pay to the European distributor a per unit fee for sales of our Omnipod device, over the twelve months following the expiration of the global distribution agreement, to identified customers (as that term is defined in the distribution agreement) of the European distributor who had previously entered into an agreement with the distributor for the purchase of Omnipod devices. While the actual total fee could vary significantly, we estimate that the total fee could be in the range of approximately $10 million to $55 million. The fee will be determined and paid on a quarterly basis following the expiration of the distribution agreement and the actual amount of the fee will depend on a number of factors and will not be known until the number of qualifying sales of Omnipod devices is determined following each quarter beginning with the quarter ending September 30, 2018.
Convertible Senior Notes
In order to finance our operations and global expansion, we have periodically issued and sold Convertible Senior Notes, which are convertible into our common stock. As of December 31, 2017, the following Notes were outstanding:
| Issuance Date | Coupon | Principal Outstanding (in thousands) | Due Date | Initial Conversion Rate per Share of Common Stock | Conversion Price per Share of Common Stock | ||
| June 2014 | 2.000% | $ | 3,664 | June 15, 2019 | 21.5019 | $46.51 | |
| September 2016 | 1.250% | 345,000 | September 15, 2021 | 17.1332 | $58.37 | ||
| November 2017 | 1.375% | 402,500 | November 15, 2024 | 10.7315 | $93.18 | ||
| Total | $ | 751,164 |
Additional information regarding our debt issuances is provided in Note 11 to the consolidated financial statements included under Item 8 of this Form 10-K.
Capital Leases
As of December 31, 2017, we had no capital leases outstanding.
| Summary of Cash Flows | Years Ended December 31, | |||||||||||
| (In thousands) | 2017 | 2016 | 2015 | |||||||||
| Cash provided by (used in): | ||||||||||||
| Operating activities | $ | 41,207 | $ | 15,911 | $ | (12,552 | ) | |||||
| Investing activities | (210,797 | ) | (178,010 | ) | (15,323 | ) | ||||||
| Financing activities | 304,547 | 176,567 | (371 | ) | ||||||||
| Effect of exchange rate changes on cash | 446 | 34 | (275 | ) | ||||||||
| Net increase (decrease) in cash and cash equivalents | $ | 135,403 | $ | 14,502 | $ | (28,521 | ) |
Included in our summary of cash flows for the years ended December 31, 2016 and 2015 are the results of our discontinued operations. Additional information regarding our discontinued operations is provided in Note 19 to the consolidated financial statements included under Item 8 of this Form 10-K.
Operating Activities
Our net cash provided by operating activities for the year ended December 31, 2017 was $41.2 million compared to net cash provided by operating activities of $15.9 million in the same period of 2016, an increase of $25.3 million year over year. The increase in cash provided by operating activities in the current period is primarily due to reductions in working capital (excluding cash and cash equivalents and short-term investments) in the current period as compared to investments in working capital in 2016, which included additional inventory purchases in order to support customer demand. Reductions in working capital in the current period were primarily due to increases in accounts payable, accrued expenses and other liabilities, partially offset by increases in account receivable due to the growth of our business.
Our net cash provided by operating activities was $15.9 million for the year ended December 31, 2016 compared to net cash used in operating activities of $12.6 million in the same period in 2015. The increase was primarily due to a lower net loss recorded for the year and improved customer collections, partially offset by timing of cash disbursements and additional inventory purchases in order to support customer demand and to allow for alternative shipping methods.
Investing Activities
Net cash used in investing activities for the year ended December 31, 2017 was $210.8 million compared to net cash used in investing activities of $178.0 million in 2016, an increase of $32.8 million. The increase in investing activities in the current period is primarily due to an increase in capital expenditures, which were $77.2 million in 2017 compared to $22.1 million in 2016, primarily associated with the construction of our manufacturing facility in Acton, Massachusetts, partially offset by fewer net investments in marketable securities in the current period.
Net cash used in investing activities in the year ended December 31, 2016 was $178.0 million compared to $15.3 million in the same period of 2015. In the year ended December 31, 2016, we invested $161.6 million in marketable securities (net of proceeds from redemptions and sales) driven by the net proceeds from the issuance of our 1.25% Notes. There were no such investments in 2015. In addition, the increase in investing activities related to higher capital expenditures of $22.1 million in 2016 compared to $10.6 million in 2015, primarily associated with investments in supply chain operations including $10.7 million for equipment in process of construction to support our U.S. manufacturing initiatives.
Financing Activities
Net cash provided by financing activities for the year ended December 31, 2017 was $304.5 million compared to $176.6 million in net cash provided by financing activities in 2016, an increase of $127.9 million. The increase was primarily attributable to net proceeds of $391.6 million in November 2017 from the issuance of our 1.375% Notes as compared to $333.7 million of net proceeds from the issuance in 2016 of our 1.25% Notes, and lower repayments to retire outstanding debt in the current period as compared to 2016. In November 2017, we made payments of $98.6 million to extinguish $63.4 million of our outstanding 2% Notes as compared to $153.6 million of payments to extinguish a portion of our 2% Notes in 2016.
Net cash provided by financing activities in the year ended December 31, 2016 was $176.6 million compared to $0.4 million in net cash used in financing activities in the same period of 2015. The increase was primarily
attributable to net proceeds of $333.7 million in September 2016 from the issuance of our 1.25% Notes, offset by repayments of $153.6 million to extinguish $134.2 million, or approximately 67%, of our outstanding 2% Notes.
Commitments and Contingencies
We lease facilities in Massachusetts, California, Tennessee, the United Kingdom, Canada and China. These leases are accounted for as operating leases and generally provide for a base rent plus real estate taxes and certain operating expenses related to the leases. Certain of our operating lease agreements contain scheduled rent increases. Rent expense is recorded using the straight-line method and deferred rent is included in other liabilities in the accompanying consolidated balance sheets.
The following table summarizes our principal obligations as of December 31, 2017:
| (In millions) | ||||||||||||||||||||||||||||
| Contractual Obligations (3) | Total | 2018 | 2019 | 2020 | 2021 | 2022 | Later | |||||||||||||||||||||
| Operating lease obligations | $ | 13.1 | $ | 3.0 | $ | 3.0 | $ | 2.6 | $ | 2.4 | $ | 2.1 | $ | — | ||||||||||||||
| Debt obligations: principal (1) | 751.2 | — | 3.7 | — | 345.0 | — | 402.5 | |||||||||||||||||||||
| Debt obligations: cash interest (1) | 54.1 | 9.9 | 9.9 | 9.8 | 8.6 | 5.5 | 10.4 | |||||||||||||||||||||
| Purchase obligations(2) | 140.9 | 128.3 | 12.6 | — | — | — | — | |||||||||||||||||||||
| Total contractual obligations | $ | 959.3 | $ | 141.2 | $ | 29.2 | $ | 12.4 | $ | 356.0 | $ | 7.6 | $ | 412.9 |
| (1) | Debt obligations include principal and cash interest. Our senior convertible notes incur annual interest of 2%, 1.25% and 1.375%. |
| (2) | Our purchase obligations include commitments with certain of our suppliers, primarily for the purchase of Omnipod System components and manufacturing equipment along with other commitments to purchase goods or services in the normal course of business. We make such commitments through a combination of purchase orders, supplier contracts, and open orders based on projected demand information. These amounts include approximately $58.0 million of commitments with three major suppliers for the construction of our Acton, Massachusetts manufacturing facility and the establishment of highly-automated manufacturing operations. |
| (3) | The contractual obligations table excludes a fee that we will be required to pay to our European distributor following the expiration of our global distribution agreement on June 30, 2018. The actual amount of the fee is uncertain and is dependent on a number of factors. |
Legal Proceedings
The significant estimates and judgments related with establishing litigation reserves are discussed under "Legal Proceedings" in Note 12 of the consolidated financial statements included under Item 8 of this Form 10-K.
Off-Balance Sheet Arrangements
As of December 31, 2017, we did not have any off-balance sheet financing arrangements.
Critical Accounting Policies and Estimates
Our financial statements are based on the selection and application of generally accepted accounting principles, which require us to make estimates and assumptions about future events that affect the amounts reported in our financial statements and the accompanying notes. Future events and their effects cannot be determined with certainty. Therefore, the determination of estimates requires the exercise of judgment. Actual results could differ from those estimates, and any such differences may be material to our financial statements.
Based on the sensitivity of reported financial statement amounts to the underlying estimates and assumptions, the relatively more significant accounting policies applied by us have been identified by management as those associated with the following:
-
Revenue recognition
-
Fair value measurements
-
Accounts receivable and allowance for doubtful accounts
-
Inventories
-
Product warranty costs
-
Convertible debt
-
Commitments and contingencies
-
Stock-based compensation
Additional information on our critical accounting estimates and significant accounting policies, including references to applicable footnotes, is provided in Note 2 to the consolidated financial statements included under Item 8 of this Form 10-K.
Recent Accounting Pronouncements
Information with respect to recent accounting developments is provided in Note 2 to the consolidated financial statements included under Item 8 of this Form 10-K.
Item 7A. Quantitative and Qualitative Disclosures about Market Risk
We do not use derivative financial instruments in our investment portfolio and have no foreign exchange contracts.
Our financial instruments consist of cash, cash equivalents, short-term and long-term investments, accounts receivable, accounts payable, accrued expenses, debt and long-term obligations. We consider investments that, when purchased, have a remaining maturity of 90 days or less to be cash equivalents.The primary objectives of our investment strategy are to preserve principal, maintain proper liquidity to meet operating needs and maximize yields. To minimize our exposure to an adverse shift in interest rates, we invest in cash equivalents, short-term and long-term marketing securities. We do not believe that a 10% change in interest rates would have a material impact on the fair value of our investment portfolio or our interest income.
As of December 31, 2017, we had outstanding debt recorded on our consolidated balance sheet of $566.2 million, net of deferred financing costs and unamortized debt discount totaling $185.0 million, related to our Convertible Senior Notes. As the interest rates are fixed and the notes are not carried at fair value, changes in interest rates do not affect the value of our debt.
Our business is subject to risks, including, but not limited to: unique economic conditions, changes in political climate, differing tax structures, other regulations and restrictions, and foreign exchange rate volatility. We are primarily exposed to currency exchange rate fluctuations related to our subsidiary operation in Canada and, to a lesser extent, Europe. Currently, the majority of our sales outside of the U.S. are transacted in U.S. dollars and are not subject to material foreign currency fluctuations. We expect that as we establish our commercial operations in Europe during 2018 that our business will become more susceptible to foreign exchange rate volatility, primarily related to the Euro and the British Pound.
Fluctuations in foreign currency rates could affect our sales, cost of goods and operating margins and could result in exchange losses. In addition, currency devaluations can result in a loss if we hold deposits of that currency. A hypothetical 10% increase or decrease in foreign currencies that we transact in would not have a material adverse impact on our cash flows, financial condition or results of operations.
Item 8. Financial Statements and Supplementary Data
Our financial statements as of December 31, 2017 and 2016 and for each of the three years in the period ended December 31, 2017, and the Reports of the Registered Independent Public Accounting Firms are included in this report as listed in the index.
Report of Independent Registered Public Accounting Firm
Board of Directors and Shareholders
Insulet Corporation
Opinion on the financial statements
We have audited the accompanying consolidated balance sheets of Insulet Corporation (a Delaware corporation) and subsidiaries (the “Company”) as of December 31, 2017 and 2016, the related consolidated statements of operations, comprehensive loss, shareholders’ equity, and cash flows for each of the two years in the period ended December 31, 2017, and the related notes and schedule (collectively referred to as the "financial statements"). In our opinion, the financial statements present fairly, in all material respects, the financial position of the Company as of December 31, 2017 and 2016, and the results of its operations and its cash flows for each of the two years in the period ended December 31, 2017, in conformity with accounting principles generally accepted in the United States of America.
We also have audited, in accordance with the standards of the Public Company Accounting Oversight Board (United States) ("PCAOB"), the Company’s internal control over financial reporting as of December 31, 2017, based on criteria established in the 2013 Internal Control-Integrated Framework issued by the Committee of Sponsoring Organizations of the Treadway Commission ("COSO"), and our report dated February 21, 2018 expressed an unqualified opinion.
Basis for opinion
These financial statements are the responsibility of the Company's management. Our responsibility is to express an opinion on the Company's financial statements based on our audits. We are a public accounting firm registered with the PCAOB and are required to be independent with respect to the Company in accordance with the U.S federal securities laws and the applicable rules and regulations of the Securities and Exchange Commission and the PCAOB.
We conducted our audits in accordance with the standards of the PCAOB. Those standards require that we plan and perform the audit to obtain reasonable assurance about whether the financial statements are free of material misstatement, whether due to error or fraud. Our audits included performing procedures to assess the risks of material misstatement of the financial statements, whether due to error or fraud, and performing procedures that respond to those risks. Such procedures included examining, on a test basis, evidence supporting the amounts and disclosures in the financial statements. Our audits also included evaluating the accounting principles used and significant estimates made by management, as well as evaluating the overall presentation of the financial statements. We believe that our audits provide a reasonable basis for our opinion.
/s/ GRANT THORNTON LLP
We have served as the Company's auditor since 2016.
Boston, Massachusetts
February 21, 2018
Report of Independent Registered Public Accounting Firm
The Board of Directors and Stockholders of
Insulet Corporation
We have audited the accompanying consolidated statements of operations, comprehensive loss, stockholders' equity and cash flows of Insulet Corporation for the year ended December 31, 2015. Our audit also includes the financial statement schedule listed in the Index at Item 15(a) for the year ended December 31, 2015. These financial statements and schedule are the responsibility of the Company's management. Our responsibility is to express an opinion on these financial statements and schedule based on our audit.
We conducted our audit in accordance with the standards of the Public Company Accounting Oversight Board (United States). Those standards require that we plan and perform the audit to obtain reasonable assurance about whether the financial statements are free of material misstatement. An audit includes examining, on a test basis, evidence supporting the amounts and disclosures in the financial statements. An audit also includes assessing the accounting principles used and significant estimates made by management, as well as evaluating the overall financial statement presentation. We believe that our audit provides a reasonable basis for our opinion.
In our opinion, the financial statements referred to above present fairly, in all material respects, the consolidated results of its operations and its cash flows of Insulet Corporation for the year ended December 31, 2015, in conformity with U.S. generally accepted accounting principles. Also, in our opinion, the related financial statement schedule for the year ended December 31, 2015 when considered in relation to the basic financial statements taken as a whole, presents fairly in all material respects the information set forth therein.
/s/ Ernst & Young LLP
Boston, Massachusetts
February 29, 2016
(except for the effects of discontinued operations as discussed in Note 19 as to which the date is September 6, 2016 and the effects of the adoption of ASU 2016-19 and ASU 2016-18 as discussed in Notes 2 and 7, as to which the date is February 21, 2018 )
INSULET CORPORATION
CONSOLIDATED BALANCE SHEETS
| December 31, 2017 | December 31, 2016 | ||||||
| (In thousands, except share and per share data) | |||||||
| ASSETS | |||||||
| Current Assets | |||||||
| Cash and cash equivalents | $ | 272,577 | $ | 137,174 | |||
| Short-term investments | 167,479 | 161,396 | |||||
| Accounts receivable, net | 53,373 | 28,803 | |||||
| Inventories | 33,793 | 35,514 | |||||
| Prepaid expenses and other current assets | 9,949 | 7,073 | |||||
| Total current assets | 537,171 | 369,960 | |||||
| Long-term investments | 125,549 | — | |||||
| Property and equipment, net | 107,864 | 44,753 | |||||
| Other intangible assets, net | 4,351 | 2,041 | |||||
| Goodwill | 39,840 | 39,677 | |||||
| Other assets | 1,969 | 216 | |||||
| Total assets | $ | 816,744 | $ | 456,647 | |||
| LIABILITIES AND STOCKHOLDERS’ EQUITY | |||||||
| Current Liabilities | |||||||
| Accounts payable | $ | 24,413 | $ | 13,160 | |||
| Accrued expenses and other current liabilities | 59,256 | 41,228 | |||||
| Deferred revenue | 2,356 | 1,309 | |||||
| Total current liabilities | 86,025 | 55,697 | |||||
| Long-term |
Showing the first 8K of 136K characters. Open the full section
Item 9. CHANGES IN AND DISAGREEMENTS WITH ACCOUNTANTS ON ACCOUNTING AND FINANCIAL DISCLOSURE
None.
Item 9A. Controls and Procedures
Disclosure Controls and Procedures
Our management, with the participation of our chief executive officer and chief financial officer, evaluated the effectiveness of our disclosure controls and procedures as of December 31, 2017. The term “disclosure controls and procedures,” as defined in Rules 13a-15(e) and 15d-15(e) under the Securities Exchange Act of 1934, as amended (the “Exchange Act”) means controls and other procedures of a company that are designed to ensure that information required to be disclosed by a company in the reports that it files or submits under the Exchange Act is recorded, processed, summarized and reported, within the time periods specified in the Securities and Exchange Commission’s rules and forms. Disclosure controls and procedures include, without limitation, controls and procedures designed to ensure that information required to be disclosed by a company in the reports that it files or submits under the Exchange Act is accumulated and communicated to the company’s management, including its principal executive and principal financial officers, as appropriate to allow timely decisions regarding required disclosure. Management recognizes that any controls and procedures, no matter how well designed and operated, can provide only reasonable assurance of achieving their objectives and management necessarily applies its judgment in evaluating the cost-benefit relationship of possible controls and procedures. Based on the evaluation of our disclosure controls and procedures as of December 31, 2017, our chief executive officer and chief financial officer concluded that, as of such date, our disclosure controls and procedures were effective at a reasonable assurance level.
Changes in Internal Control Over Financial Reporting
There were no changes in our internal control over financial reporting during the three months ended December 31, 2017 that have materially affected, or are reasonably likely to materially affect, our internal control over financial reporting.
Management's Annual Report on Internal Control Over Financial Reporting
Our management is responsible for establishing and maintaining adequate internal control over financial reporting as such term is defined in Exchange Act Rule 13a — 15(f). Our internal control system was designed to provide reasonable assurance to our management and the Board of Directors regarding the preparation and fair presentation of published financial statements. All internal control systems, no matter how well designed have inherent limitations. Therefore, even those systems determined to be effective can provide only reasonable assurance with respect to financial statement preparation and presentation. Our management assessed the effectiveness of our internal control over financial reporting as of December 31, 2017. In making this assessment, our management used the criteria set forth by the Committee of Sponsoring Organizations of the Treadway Commission 2013 (“COSO”) in Internal Control — Integrated Framework (the COSO criteria).
Based on our assessment we believe that, as of December 31, 2017, our internal control over financial reporting is effective based on those criteria. The effectiveness of our internal control over financial reporting as of December 31, 2017 has been audited by Grant Thornton LLP, an independent registered public accounting firm, as stated in their report which appears below.
Report of Independent Registered Public Accounting Firm
Board of Directors and Shareholders
Insulet Corporation
Opinion on internal control over financial reporting
We have audited the internal control over financial reporting of Insulet Corporation (a Delaware corporation) and subsidiaries (the “Company”) as of December 31, 2017, based on criteria established in the 2013 Internal Control-Integrated Framework issued by the Committee of Sponsoring Organizations of the Treadway Commission (COSO). In our opinion, the Company maintained, in all material respects, effective internal control over financial reporting as of December 31, 2017, based on criteria established in the 2013 Internal Control-Integrated Framework issued by COSO.
We also have audited, in accordance with the standards of the Public Company Accounting Oversight Board (United States) (“PCAOB”), the consolidated financial statements of the Company as of and for the year ended December 31, 2017, and our report dated February 21, 2018 expressed an unqualified opinion on those financial statements.
Basis for opinion
The Company’s management is responsible for maintaining effective internal control over financial reporting and for its assessment of the effectiveness of internal control over financial reporting, included in the accompanying Management’s Annual Report on Internal Control Over Financial Reporting. Our responsibility is to express an opinion on the Company’s internal control over financial reporting based on our audit. We are a public accounting firm registered with the PCAOB and are required to be independent with respect to the Company in accordance with the U.S. federal securities laws and the applicable rules and regulations of the Securities and Exchange Commission and the PCAOB.
We conducted our audit in accordance with the standards of the PCAOB. Those standards require that we plan and perform the audit to obtain reasonable assurance about whether effective internal control over financial reporting was maintained in all material respects. Our audit included obtaining an understanding of internal control over financial reporting, assessing the risk that a material weakness exists, testing and evaluating the design and operating effectiveness of internal control based on the assessed risk, and performing such other procedures as we considered necessary in the circumstances. We believe that our audit provides a reasonable basis for our opinion.
Definition and limitations of internal control over financial reporting
A company’s internal control over financial reporting is a process designed to provide reasonable assurance regarding the reliability of financial reporting and the preparation of financial statements for external purposes in accordance with generally accepted accounting principles. A company’s internal control over financial reporting includes those policies and procedures that (1) pertain to the maintenance of records that, in reasonable detail, accurately and fairly reflect the transactions and dispositions of the assets of the company; (2) provide reasonable assurance that transactions are recorded as necessary to permit preparation of financial statements in accordance with generally accepted accounting principles, and that receipts and expenditures of the company are being made only in accordance with authorizations of management and directors of the company; and (3) provide reasonable assurance regarding prevention or timely detection of unauthorized acquisition, use, or disposition of the company’s assets that could have a material effect on the financial statements.
Because of its inherent limitations, internal control over financial reporting may not prevent or detect misstatements. Also, projections of any evaluation of effectiveness to future periods are subject to the risk that controls may become inadequate because of changes in conditions, or that the degree of compliance with the policies or procedures may deteriorate.
/s/ GRANT THORNTON LLP
Boston, Massachusetts
February 21, 2018
Item 9B. OTHER INFORMATION
None.
PART III
Item 10. Directors, Executive Officers and Corporate Governance
Certain information required by this Item 10 relating to our directors, executive officers and corporate governance is incorporated by reference herein from our proxy statement in connection with our 2018 annual meeting of stockholders, which proxy statement will be filed with the Securities and Exchange Commission (the “SEC”) not later than 120 days after the close of our year ended December 31, 2017.
Item 11. Executive Compensation
Certain information required by this Item 11 relating to remuneration of directors and executive officers and other transactions involving management is incorporated by reference herein from our proxy statement in connection with our 2018 annual meeting of stockholders, which proxy statement will be filed with the Securities and Exchange Commission not later than 120 days after the close of our year ended December 31, 2017.
Item 12. Security Ownership of Certain Beneficial Owners and Management and Related Stockholder Matters
Certain information required by this Item 12 relating to security ownership of certain beneficial owners and management is incorporated by reference herein from our proxy statement in connection with our 2018 annual meeting of stockholders, which proxy statement will be filed with the Securities and Exchange Commission not later than 120 days after the close of our fiscal year ended December 31, 2017. For information on securities authorized for issuance under equity compensation plans, see the section entitled “Market for Registrant’s Common Equity, Related Stockholders Matters, and Issuer Purchases of Equity Securities “ in Part II, Item 5, in this Annual Report on Form 10-K.
Item 13. Certain Relationships and Related Transactions, and Director Independence
Certain information required by this Item 13 relating to certain relationships and related transactions, and director independence is incorporated by reference herein from our proxy statement in connection with our 2018 annual meeting of stockholders, which proxy statement will be filed with the Securities and Exchange Commission not later than 120 days after the close of our year ended December 31, 2017.
Item 14. Principal Accounting Fees and Services
Certain information required by this Item 14 regarding principal accounting fees and services is set forth under “Principal Accounting Fees and Services” in our proxy statement in connection with our 2018 annual meeting of stockholders, which proxy statement will be filed with the Securities and Exchange Commission not later than 120 days after the close of our year ended December 31, 2017.
Item 15. Exhibits, Financial Statement Schedules
| (A)(1) FINANCIAL STATEMENTS | ||
| The following consolidated financial statements of Insulet Corporation are included in Item 8 hereof: | ||
| Report of Independent Registered Public Accounting Firm | ||
| Consolidated Balance Sheets - Years ended December 31, 2017 and 2016 | ||
| Consolidated Statements of Operations - Years ended December 31, 2017, 2016 and 2015 | ||
| Consolidated Statements of Comprehensive Loss - Years ended December 31, 2017, 2016 and 2015 | ||
| Consolidated Statements of Stockholders' Equity - Years ended December 31, 2017, 2016 and 2015 | ||
| Consolidated Statements of Cash Flows - Years ended December 31, 2017, 2016 and 2015 | ||
| Notes to Consolidated Financial Statements | ||
| (A)(2) FINANCIAL STATEMENT SCHEDULES | ||
| Certain schedules to the consolidated financial statements have been omitted if they were not required by Article 9 of Regulation S-X or if, under the related instructions, they were inapplicable, or the information was contained elsewhere herein. | ||
| (A)(3) EXHIBITS | ||
| The exhibits listed in the Exhibit Index following the signature page of this Form 10-K are filed herewith or are incorporated herein by reference to other SEC filings. |
Item 16. Form 10-K Summary
None.
SIGNATURES
Pursuant to the requirements of Section 13 or 15(d) of the Securities Exchange Act of 1934, the Registrant has caused this report to be signed on its behalf by the undersigned thereunto duly authorized.
| INSULET CORPORATION (Registrant) | |
| February 21, 2018 | /s/ Patrick J. Sullivan |
| Patrick J. Sullivan | |
| Chief Executive Officer (Principal Executive Officer) |
| February 21, 2018 | /s/ Michael L. Levitz |
| Michael L. Levitz | |
| Chief Financial Officer (Principal Financial and Accounting Officer) |
POWER OF ATTORNEY AND SIGNATURES
We, the undersigned officers and directors of Insulet Corporation, hereby severally constitute and appoint Patrick J. Sullivan and Michael L. Levitz, and each of them singly, our true and lawful attorneys, with full power to them and each of them singly, to sign for us in our names in the capacities indicated below, on all amendments to this Report, and generally to do all things in our names and on our behalf in such capacities to enable Insulet Corporation to comply with the provisions of the Securities Exchange Act of 1934, as amended, and all requirements of the Securities and Exchange Commission.
Pursuant to the requirements of the Securities Exchange Act of 1934, this Report has been signed below by the following persons on behalf of the Registrant and in the capacities on February 21, 2018.
| Signature | Title | |
| /s/ Patrick J. Sullivan | Chief Executive Officer | |
| Patrick J. Sullivan | (Principal Executive Officer) | |
| /s/ Michael L. Levitz | Chief Financial Officer | |
| Michael L. Levitz | (Principal Financial and Accounting Officer) | |
| /s/ Sally Crawford | ||
| Sally Crawford | Director | |
| /s/ John Fallon, M.D. | ||
| John Fallon, M.D. | Director | |
| /s/ Dr. Jessica Hopfield | ||
| Dr. Jessica Hopfield | Director | |
| /s/ David A. Lemoine | ||
| David Lemoine | Director | |
| /s/ Timothy J. Scannell | ||
| Timothy J. Scannell | Director | |
| /s/ Michael R. Minogue | ||
| Michael R. Minogue | Director | |
| /s/ James C. Mullen | ||
| James C. Mullen | Director |
EXHIBIT INDEX
Listed and indexed below are all Exhibits filed as part of this report.
| * | This certification shall not be deemed “filed” for purposes of Section 18 of the Securities Exchange Act of 1934, or otherwise subject to the liability of that Section, nor shall it be deemed to be incorporated by reference into any filing under the Securities Act of 1933 or the Securities Exchange Act of 1934. |
| + | Confidential treatment granted as to certain portions of this exhibit. |