 filings.tools
UnitedHealth Group 10-K 2022-12-31
Filed 2023-02-24. 23 sections, 408K characters. Original on sec.gov · Markdown · JSON
Cover and table of contents
UNITED STATES
SECURITIES AND EXCHANGE COMMISSION
Washington, D.C. 20549
Form 10-K
| ☒ | ANNUAL REPORT PURSUANT TO SECTION 13 OR 15(d) OF THE SECURITIES EXCHANGE ACT OF 1934 |
For the fiscal year ended December 31, 2022
| or | |||||
| ☐ | TRANSITION REPORT PURSUANT TO SECTION 13 OR 15(d) OF THE SECURITIES EXCHANGE ACT OF 1934 | ||||
| For the transition period from _____ to _____ |
Commission file number: 1-10864
__________________________________________________________

UnitedHealth Group Incorporated
(Exact name of registrant as specified in its charter)
| Delaware | 41-1321939 | ||||||||||
| (State or other jurisdiction of incorporation or organization) | (I.R.S. Employer Identification No.) | ||||||||||
| UnitedHealth Group Center | 55343 | ||||||||||
| 9900 Bren Road East | |||||||||||
| Minnetonka, | Minnesota | ||||||||||
| (Address of principal executive offices) | (Zip Code) |
(952) 936-1300
(Registrant’s telephone number, including area code)
______________________________________________________
Securities registered pursuant to Section 12(b) of the Act:
| Title of each class | Trading Symbol(s) | Name of each exchange on which registered | ||||||||||||
| Common Stock, $.01 par value | UNH | New York Stock Exchange |
Securities registered pursuant to Section 12(g) of the Act: None
________________________________________________________****_
Indicate by check mark if the registrant is a well-known seasoned issuer, as defined in Rule 405 of the Securities Act. Yes ☒ No ☐
Indicate by check mark if the registrant is not required to file reports pursuant to Section 13 or Section 15(d) of the Act. Yes ☐ No ☒
Indicate by check mark whether the registrant (1) has filed all reports required to be filed by Section 13 or 15(d) of the Securities Exchange Act of 1934 during the preceding 12 months (or for such shorter period that the registrant was required to file such reports), and (2) has been subject to such filing requirements for the past 90 days. Yes ☒ No ☐
Indicate by check mark whether the registrant has submitted electronically every Interactive Data File required to be submitted and posted pursuant to Rule 405 of Regulation S-T during the preceding 12 months (or for such shorter period that the registrant was required to submit and post such files). Yes ☒ No ☐
Indicate by check mark whether the registrant is a large accelerated filer, an accelerated filer, a non-accelerated filer, a smaller reporting company, or an emerging growth company. See the definitions of “large accelerated filer,” “accelerated filer,” “smaller reporting company,” and “emerging growth company” in Rule 12b-2 of the Exchange Act.
| Large accelerated filer | ☒ | Accelerated filer | ☐ | Non-accelerated filer | ☐ | ||||||||||||||||||
| Smaller reporting company | ☐ | Emerging growth company | ☐ |
If an emerging growth company, indicate by check mark if the registrant has elected not to use the extended transition period for complying with any new or revised financial accounting standards provided pursuant to Section 13(a) of the Exchange Act. ☐
Indicate by check mark whether the registrant has filed a report on and attestation to its management’s assessment of the effectiveness of its internal control over financial reporting under Section 404(b) of the Sarbanes-Oxley Act (15 U.S.C. 7262(b)) by the registered public accounting firm that prepared or issued its audit report. ☒
If securities are registered pursuant to Section 12(b) of the Act, indicate by check mark whether the financial statements of the registrant included in the filing reflect the correction of an error to previously issued financial statements. ☐
Indicate by check mark whether any of those error corrections are restatements that required a recovery analysis of incentive-based compensation received by any of the registrant’s executive officers during the relevant recovery period pursuant to §240.10D-1(b). ☐
Indicate by check mark whether the registrant is a shell company (as defined in Rule 12b-2 of the Act). Yes ☐ No ☒
The aggregate market value of voting stock held by non-affiliates of the registrant as of June 30, 2022 was $479,550,880,245 (based on the last reported sale price of $513.63 per share on June 30, 2022 as reported on the New York Stock Exchange), excluding only shares of voting stock held beneficially by directors, executive officers and subsidiaries of the registrant.
As of January 31, 2023, there were 932,846,602 shares of the registrant’s Common Stock, $.01 par value per share, issued and outstanding.
DOCUMENTS INCORPORATED BY REFERENCE
The information required by Part III of this report, to the extent not set forth herein, is incorporated by reference from the registrant’s definitive proxy statement relating to its 2023 Annual Meeting of Shareholders. Such proxy statement will be filed with the Securities and Exchange Commission within 120 days after the end of the fiscal year to which this report relates.
UNITEDHEALTH GROUP
Table of Contents
PART I
Item 1. BUSINESS
OUR BUSINESSES
Overview
The terms “we,” “our,” “us,” “its,” “UnitedHealth Group,” or the “Company” used in this report refer to UnitedHealth Group Incorporated and its subsidiaries.
UnitedHealth Group Incorporated is a health care and well-being company with a mission to help people live healthier lives and help make the health system work better for everyone. Our two distinct, yet complementary business platforms — Optum and UnitedHealthcare — are working to help build a modern, high-performing health system through improved access, affordability, outcomes and experiences for the individuals and organizations we are privileged to serve.
The ability to analyze complex data and apply deep health care expertise and insights allows us to serve people, care providers, businesses, communities and governments with more innovative products and complete, end-to-end offerings for many of the biggest challenges facing health care today.
Optum combines clinical expertise, technology and data to empower people, partners and providers with the guidance and tools they need to achieve better health. Optum serves the broad health care marketplace, including payers, care providers, employers, governments, life sciences companies and consumers, through its Optum Health, Optum Insight and Optum Rx businesses. These businesses improve overall health system performance by optimizing care quality and delivery, reducing costs and improving consumer and provider experience, leveraging distinctive capabilities in data and analytics, pharmacy care services, health care operations, population health and health care delivery.
UnitedHealthcare offers a full range of health benefits, enabling affordable coverage, simplifying the health care experience and delivering access to high-quality care. UnitedHealthcare Employer & Individual serves employers ranging from sole proprietorships to large, multi-site and national employers, public sector employers and individual consumers. UnitedHealthcare Medicare & Retirement delivers health and well-being benefits for Medicare beneficiaries and retirees. UnitedHealthcare Community & State manages health care benefit programs on behalf of state Medicaid and community programs and their participants.
We have four reportable segments:
-
Optum Health;
-
Optum Insight;
-
Optum Rx; and
-
UnitedHealthcare, which includes UnitedHealthcare Employer & Individual, UnitedHealthcare Medicare & Retirement and UnitedHealthcare Community & State.
Optum
Optum is an information and technology-enabled health services business serving the broad health care marketplace, including:
-
Those who need care: consumers who need the right care, information, resources, products and engagement to improve their health, achieve their health goals and receive an improved patient experience that is personalized and holistic and delivered in all care settings, including in-home and virtually.
-
Those who provide care: pharmacies, hospitals, physicians and other health care facilities seeking to improve the health system and reduce the administrative burden allowing for providers to focus time on patients leading to the best possible patient care and experiences while achieving better health outcomes at lower costs. Improved health outcomes are achieved by leveraging our clinical expertise, data and analytics to better predict, prevent and intercept consumers’ health conditions and ensure they receive the best evidence-based care.
-
Those who pay for care: employers; health plans; and state, federal and municipal agencies devoted to ensuring the people they sponsor receive high-quality care, administered and delivered efficiently and effectively, all while driving health equity so that every individual, family and community has access to the care they need.
-
Those who innovate for care: global life sciences organizations dedicated to developing more effective approaches to care, enabling technologies and medicines to improve care delivery and health outcomes.
Optum operates three business segments leveraging distinctive capabilities in health care delivery, population health, health care operations, data and analytics and pharmacy care services:
-
Optum Health delivers care, care management, wellness and consumer engagement, and health financial services;
-
Optum Insight offers data, analytics, research, consulting, technology and managed services solutions; and
-
Optum Rx provides diversified pharmacy care services.
Optum Health
Optum Health provides comprehensive and patient-centered care, addressing the physical, mental, social, and financial well-being of 102 million consumers and serves more than 100 health payer partners. We engage people in the most appropriate care settings, including clinical sites, in-home and virtual. Optum Health delivers primary, multi-specialty, behavioral, surgical and urgent care; helps patients and providers navigate and address complex, chronic and behavioral health needs; offers post-acute care planning services; and serves consumers and care providers through advanced, on-demand digital health technologies, such as telehealth and remote patient monitoring, and innovative health care financial services. Optum Health works directly with consumers, care delivery systems, providers, employers, payers, and public-sector entities to provide high quality, accessible and equitable care with improved health outcomes and reduced total cost of care.
Optum Health enables care providers to transition from traditional fee-for-service payment models to performance-based delivery and payment models designed to improve patient health outcomes and experience through value-based care. Through strategic partnerships, alliances and ownership arrangements, Optum Health helps care providers adopt new approaches and technologies improving the coordination of care across providers to serve patients more comprehensively.
Optum Health offerings include fully accountable value-based arrangements, where Optum Health assumes responsibility for health care costs in exchange for a monthly premium. Offerings also include administrative fee arrangements, where Optum Health manages or administers products and services in exchange for a monthly fee, and fee-for-service arrangements, where Optum Health delivers health-related products and medical services for patients at a contracted fee.
Optum Financial, including Optum Bank, serves consumers through nearly 20 million consumer accounts with nearly $20 billion in assets under management as of December 31, 2022. Organizations across the health system rely on Optum Financial to manage and improve payment flows through its highly automated, scalable, end-to-end digital payment systems and integrated card solutions. For financial services offerings, Optum Financial charges fees and earns investment income on managed funds.
Optum Health sells its products primarily through its direct sales force, strategic collaborations and external producers in three key areas: employers, including large, mid-sized and small employers; payers including health plans, third-party administrators (TPAs), underwriter/stop-loss carriers and individual product intermediaries; and public entities including the U.S. Departments of Health and Human Services (HHS), Veterans Affairs, Defense, and other federal, state and local health care agencies.
Optum Insight
Optum Insight connects the health care system with services, analytics and platforms that make clinical, administrative and financial processes simpler and more efficient for all participants in the health care system. Hospital systems, physicians, health plans, public entities, life sciences companies and other organizations comprising the health care industry depend on Optum Insight to help them improve performance and reduce costs through administrative efficiency and payment simplification, advance care quality through evidence-based standards built directly into clinical workflows, meet compliance mandates and modernize their core operating systems to meet the changing needs of the health system.
Health Systems. Serves hospitals, physicians and other care providers to improve operating performance, better coordinate care and reduce administrative costs through technology and services to improve population health management, patient engagement, revenue cycle management and strategic growth plans.
Health Plans. Serves health plans by improving financial performance and enhancing outcomes through proactive analytics, a comprehensive payment integrity portfolio and technology-enabled and staff-supported risk and quality services. Optum Insight helps health plans navigate a dynamic environment defined by shifts in employer vs. public-sector coverage, the demand for affordable benefit plans and the need to leverage new technology to reduce complexity.
State Governments. Provides advanced technology and analytics services to modernize the administration of critical safety net programs, such as Medicaid, while improving cost predictability.
Life Sciences Companies. Combines data and analytics expertise with comprehensive technologies and health care knowledge to help life sciences companies, including those in pharmaceuticals and medical technology, adopt a more comprehensive approach to advancing therapeutic discoveries and improving clinical outcomes.
Many of Optum Insight’s software and information products and professional services are delivered over extended periods, often several years. Optum Insight maintains an order backlog to track unearned revenues under these long-term arrangements. The backlog consists of estimated revenue from signed contracts, other legally binding agreements and anticipated contract renewals based on historical experience with Optum Insight’s customers. Optum Insight’s aggregate backlog as of December 31, 2022 was approximately $30.0 billion, of which $16.8 billion is expected to be realized within the next 12 months. The aggregate backlog includes $10.7 billion related to affiliated agreements. Optum Insight’s aggregate backlog as of December 31, 2021, was $22.4 billion, including $8.9 billion related to affiliated agreements.
Optum Insight’s products and services are sold primarily through a direct sales force. Optum Insight’s products are also supported and distributed through an array of alliances and business partnerships with other technology vendors, who integrate and interface Optum Insight’s products with their applications.
Optum Rx
Optum Rx provides a full spectrum of pharmacy care services through its network of more than 67,000 retail pharmacies, through home delivery, specialty and community health pharmacies, the provision of in-home and community-based infusion services and through rare disease and gene therapy support services. It also offers direct-to-consumer solutions.
Optum Rx manages a broad range of prescription drug spend, including widely available retail drugs as well as limited and ultra-limited distribution drugs in oncology, HIV, pain management and ophthalmology. Optum Rx serves the growing pharmacy needs of people with behavioral health and substance use disorders. In 2022, Optum Rx managed $124 billion in pharmaceutical spending, including $52 billion in specialty pharmaceutical spending.
Optum Rx serves health benefits providers, large national employer plans, unions and trusts, purchasing coalitions and public-sector entities. Optum Rx sells its services through direct sales, health insurance brokers and other health care consultants.
Optum Rx offers multiple clinical programs, digital tools and services to help clients manage overall pharmacy and health care costs in a clinically appropriate manner which are designed to deliver improved consumer experiences, better health outcomes and a lower total cost of care. Optum Rx provides various utilization management, medication management, quality assurance, adherence and counseling programs to complement each client’s plan design and clinical strategies. Optum Rx is accelerating the integration of medical, pharmacy and behavioral care and treating the whole patient by embedding our pharmacists as key members of the patient care team.
UnitedHealthcare
Through its health benefits offerings, UnitedHealthcare is enabling better health, creating a better health care experience for its customers and helping to control rising health care costs. UnitedHealthcare’s market position is built on:
-
strong local-market relationships;
-
the breadth of product offerings, based upon extensive expertise in distinct market segments in health care;
-
service and advanced technology, including digital consumer engagement;
-
competitive medical and operating cost positions;
-
effective clinical engagement; and
-
innovation for customers and consumers.
UnitedHealthcare uses Optum’s capabilities to help coordinate and provide patient care, improve affordability of medical care, analyze cost trends, manage pharmacy care services, work with care providers more effectively and create a simpler and more satisfying consumer and physician experience.
In the United States, UnitedHealthcare arranges for discounted access to care through networks which, as of December 31, 2022, include 1.7 million physicians and other health care professionals and 6,400 hospitals and other facilities.
UnitedHealthcare is subject to extensive government regulation. See further discussion of our regulatory environment below under “Government Regulation” and in Part II, Item 7, “Management’s Discussion and Analysis of Financial Condition and Results of Operations.”
UnitedHealthcare Employer & Individual
Domestically, UnitedHealthcare Employer & Individual offers a comprehensive array of consumer-oriented health benefit plans and services for large national employers, public sector employers, mid-sized employers, small businesses, and individuals. As of December 31, 2022, UnitedHealthcare Employer & Individual provides access to medical services for 26.7 million people. Globally, UnitedHealthcare Employer & Individual serves nearly 7.7 million people with medical and dental benefits, typically
in exchange for a monthly premium per member, residing principally in Brazil, Chile, Colombia and Peru, but also in more than 150 other countries. UnitedHealthcare Employer & Individual offers health care delivery in our principal global markets through nearly 45 hospitals, and more than 200 outpatient and ambulatory clinics and surgery centers to UnitedHealthcare Employer & Individual global members and consumers served by other payers.
Through its risk-based product offerings, UnitedHealthcare Employer & Individual assumes the risk of both medical and administrative costs for its customers in return for a monthly premium which is typically a fixed rate per individual served for a one-year period. Through its administrative and other management services arrangements to customers who elect to self-fund the health care costs of their employees and employees’ dependents, UnitedHealthcare Employer & Individual receives a fixed monthly service fee per individual served. These customers retain the risk of financing medical benefits for their employees and employees’ dependents, while UnitedHealthcare Employer & Individual provides services such as coordination and facilitation of medical and related services to customers, consumers and health care professionals, administration of transaction processing and access to a contracted network of physicians, hospitals and other health care professionals, including dental and vision professionals. UnitedHealthcare Employer & Individual is focused on providing informed benefit solutions that create customized plan designs and clinical programs for employers that contribute to well-being and reduce the total cost of care along with providing simpler consumer experiences in response to market dynamics.
UnitedHealthcare Employer & Individual typically distributes its products through a variety of channels, dependent upon the specific product, including: through consultants or direct sales, in collaboration with brokers and agents, through wholesale agents or agencies who contract with health insurance carriers to distribute individual or group benefits, through professional employer organizations and associations and through both multi-carrier and its own proprietary private exchange marketplaces.
UnitedHealthcare Employer & Individual’s major product families include consumer engagement products, such as high-deductible consumer driven benefit plans and a variety of innovative consumer centric products; traditional products; clinical and pharmacy products; and specialty benefits, such as vision, dental, hearing, accident protection, critical illness, disability and hospital indemnity offerings.
UnitedHealthcare Medicare & Retirement
UnitedHealthcare Medicare & Retirement provides health and well-being services to individuals age 50 and older, addressing their unique needs. UnitedHealthcare Medicare & Retirement has distinct benefit designs, pricing, underwriting, clinical program management and marketing capabilities dedicated to health products and services in this market.
UnitedHealthcare Medicare & Retirement offers a selection of products allowing people choice in obtaining the health coverage and services they need as their circumstances change. These offerings include care management and health system navigator services, clinical management programs, nurse health line services, 24-hour access to health care information, access to discounted health services from a network of care providers and administrative services.
UnitedHealthcare Medicare & Retirement has extensive distribution capabilities and experience, including direct marketing to consumers on behalf of its key clients, including AARP, the nation’s largest membership organization dedicated to the needs of people age 50 and over, and state and U.S. government agencies. Products are also offered through agents, employer groups and digital channels.
Major product categories include:
Medicare Advantage. Provides health care coverage for seniors and other eligible Medicare beneficiaries through the Medicare Advantage program administered by the Centers for Medicare & Medicaid Services (CMS), including Medicare Advantage HMO plans, Preferred Provider Organization (PPO) plans, Point-of-Service plans, Private-Fee-for-Service plans and Special Needs Plans (SNPs). Under the Medicare Advantage program, UnitedHealthcare Medicare & Retirement provides health benefits coverage in exchange for a fixed monthly premium per member from CMS plus, in some cases, monthly consumer premiums. Premium amounts received from CMS vary based on the geographic areas in which individuals reside; demographic factors such as age, gender and institutionalized status; and the health status of the individual. UnitedHealthcare Medicare & Retirement served 7.1 million people through its Medicare Advantage products as of December 31, 2022.
We have continued to enhance our offerings, focusing on more digital and physical care resources in the home, expanding our concierge navigation services and enabling the home as a safe and effective setting of care. For example, through our HouseCalls program, nurse practitioners performed nearly 2.3 million clinical preventive home care visits in 2022 to address unmet care opportunities and close gaps in care.
Medicare Part D. Provides Medicare Part D benefits to beneficiaries through its Medicare Advantage and stand-alone Medicare Part D plans. The stand-alone Medicare Part D plans address a large spectrum of people’s needs and preferences for their prescription drug coverage, including low-cost prescription options. As of December 31, 2022, UnitedHealthcare enrolled 9.6 million people in the Medicare Part D programs, including 3.3 million individuals in stand-alone Medicare Part D plans, with the remainder in Medicare Advantage plans incorporating Medicare Part D coverage.
Medicare Supplement. Provides a full range of supplemental products at diverse price points. These products cover various levels of coinsurance and deductible gaps to which seniors are exposed in the traditional Medicare program. UnitedHealthcare Medicare & Retirement served 4.4 million seniors nationwide through various Medicare Supplement products in association with AARP as of December 31, 2022.
Premium revenues from CMS represented 38% of UnitedHealth Group’s total consolidated revenues for the year ended December 31, 2022, most of which were generated by UnitedHealthcare Medicare & Retirement.
UnitedHealthcare Community & State
UnitedHealthcare Community & State is dedicated to serving state programs caring for the economically disadvantaged, the medically underserved and those without the benefit of employer-funded health care coverage, typically in exchange for a monthly premium per member from the state program. UnitedHealthcare Community & State’s primary customers oversee Medicaid plans, including Temporary Assistance to Needy Families; Children’s Health Insurance Programs (CHIP); Dual SNPs (DSNPs); Long-Term Services and Supports (LTSS); Aged, Blind and Disabled; and other federal, state and community health care programs. As of December 31, 2022, UnitedHealthcare Community & State participated in programs in 35 states and the District of Columbia, and served 8.2 million people; including 1.5 million people through Medicaid expansion programs in 19 states under the Patient Protection and Affordable Care Act (ACA).
States using managed care services for Medicaid beneficiaries select health plans by using a formal bid process or by awarding individual contracts. These health plans and care programs are designed to address the complex needs of the populations they serve, including the chronically ill, people with disabilities and people with a higher risk of medical, behavioral and social conditions. UnitedHealthcare Community & State administers benefits for the unique needs of children, pregnant women, adults, seniors and those who are institutionalized or are nursing home eligible. These individuals often live in medically underserved areas and are less likely to have a consistent relationship with the medical community or a care provider. They also often face significant social and economic challenges.
GOVERNMENT REGULATION
Our businesses are subject to comprehensive U.S. federal and state and international laws and regulations. We are regulated by agencies which generally have discretion to issue regulations and interpret and enforce laws and rules. U.S. federal and state and international governments continue to consider and enact various legislative and regulatory proposals which could materially impact certain aspects of the health care system. New laws, regulations and rules, or changes in the interpretation of existing laws, regulations and rules, including as a result of changes in the political environment, could adversely affect our businesses.
See Part I, Item 1A, “Risk Factors” for a discussion of the risks related to our compliance with U.S. federal and state and international laws and regulations.
U.S. Federal Laws and Regulation
When we contract with the federal government, we are subject to federal laws and regulations relating to the award, administration and performance of U.S. government contracts. CMS regulates our UnitedHealthcare businesses and certain aspects of our Optum businesses. Payments by CMS to our businesses are subject to regulations, including those governing fee-for-service and the submission of information relating to the health status of enrollees for purposes of determining the amounts of certain payments to us. CMS also has the right to audit our performance to determine our compliance with CMS contracts and regulations and the quality of care we provide to Medicare beneficiaries. Our commercial business is further subject to CMS audits related to medical loss ratios (MLRs) and risk adjustment data.
UnitedHealthcare Community & State has Medicaid and CHIP contracts, which are subject to federal regulations regarding services to be provided to Medicaid enrollees, payment for those services and other aspects of these programs. There are many regulations affecting Medicare and Medicaid compliance, and the regulatory environment with respect to these programs is complex.
Our businesses are also subject to laws and regulations relating to consumer protection, anti-fraud and abuse, anti-kickbacks, false claims, prohibited referrals, inappropriate reduction or limitation of health care services, anti-money laundering, securities and antitrust compliance.
Privacy, Security and Data Standards Regulation. Certain of our operations are subject to regulation under the administrative simplification provisions of the Health Insurance Portability and Accountability Act of 1996, as amended (HIPAA), which apply to both the group and individual health insurance markets, including self-funded employee benefit plans. Federal regulations related to HIPAA contain minimum standards for electronic transactions and code sets and for the privacy and security of protected health information.
Our businesses must comply with the Health Information Technology for Economic and Clinical Health Act (HITECH) which regulates matters relating to privacy, security and data standards. HITECH imposes requirements on uses and disclosures of health information; includes contracting requirements for HIPAA business associate agreements; extends parts of HIPAA privacy and security provisions to business associates; adds federal data breach notification requirements for covered entities and business associates and reporting requirements to HHS and the Federal Trade Commission (FTC) and, in some cases, to the local media; strengthens enforcement and imposes higher financial penalties for HIPAA violations and, in certain cases, imposes criminal penalties for individuals, including employees. In the conduct of our business, depending on the circumstances, we may act as either a covered entity or a business associate.
The use and disclosure of individually identifiable health data by our businesses are also regulated in some instances by other federal laws, including the Gramm-Leach-Bliley Act (GLBA) or state statutes implementing GLBA. These federal laws and state statutes generally require insurers to provide customers with notice regarding how their non-public personal health and financial information is used and the opportunity to “opt out” of certain disclosures before the insurer shares such information with a third party, and generally prescribe safeguards for the protection of personal information. Neither the GLBA nor HIPAA privacy regulations preempt more stringent state laws and regulations, which may apply to us, as discussed below. Federal consumer protection laws may also apply in some instances to privacy and security practices related to personally identifiable information.
ERISA. The Employee Retirement Income Security Act of 1974, as amended (ERISA), regulates how our services are provided to or through certain types of employer-sponsored health benefit plans. ERISA is a set of laws and regulations subject to interpretation by the U.S. Department of Labor (DOL) as well as the federal courts. ERISA sets forth standards on how our business units may do business with employers who sponsor employee health benefit plans, particularly those who maintain self-funded plans. Regulations established by the DOL subject us to additional requirements for administration of benefits, claims payment and member appeals under health care plans governed by ERISA.
State Laws and Regulation
Health Care Regulation. Our insurance and HMO subsidiaries must be licensed by the jurisdictions in which they conduct business. All of the states in which our subsidiaries offer insurance and HMO products regulate those products and operations. The states require periodic financial reports and establish minimum capital or restricted cash reserve requirements. The National Association of Insurance Commissioners (NAIC) has adopted model regulations, which require expanded governance practices and risk and solvency assessment reporting. Most states have adopted these or similar measures to expand the scope of regulations relating to corporate governance and internal control activities of HMOs and insurance companies. We are required to maintain a risk management framework and file a confidential self-assessment report with state insurance regulators. We file reports annually with Connecticut, our lead regulator, and with New York, as required by the state’s regulation.
Our health plans and insurance companies are regulated under state insurance holding company regulations. Such regulations generally require registration with applicable state departments of insurance and the filing of reports describing capital structure, ownership, financial condition, certain affiliated transactions and general business operations. Most state insurance holding company laws and regulations require prior regulatory approval of acquisitions and material affiliated transfers of assets, as well as transactions between the regulated companies and their parent holding companies or affiliates. These laws may restrict the ability of our regulated subsidiaries to pay dividends to our holding companies.
Some of our business activity is subject to other health care-related regulations and requirements, including PPO, Managed Care Organization (MCO), utilization review (UR), TPA, pharmacy care services, durable medical equipment or care provider-related regulations and licensure requirements. These regulations differ from state to state and may contain network, contracting, product and rate, licensing and financial and reporting requirements. Health care-related laws and regulations set specific standards for delivery of services, appeals, grievances and payment of claims, adequacy of health care professional networks, fraud prevention, protection of consumer health information, pricing and underwriting practices and covered benefits and services. State health care anti-fraud and abuse prohibitions encompass a wide range of activities, including kickbacks for referral of members, billing for unnecessary medical services and improper marketing. Certain of our businesses are subject to state general agent, broker and sales distribution laws and regulations. UnitedHealthcare Community & State and certain of our Optum businesses are subject to regulation by state Medicaid agencies which oversee the provision of benefits to our Medicaid and CHIP beneficiaries and to our beneficiaries dually eligible for Medicare and Medicaid. We also contract with state governmental entities and are subject to state laws and regulations relating to the award, administration and performance of state government contracts.
State Privacy and Security Regulations. A number of states have adopted laws and regulations which may affect our privacy and security practices, such as state laws governing the use, disclosure and protection of social security numbers and protected health information or which are designed to implement GLBA or protect credit card account data. State and local authorities increasingly focus on the importance of protecting individuals from identity theft, with a significant number of states enacting laws requiring businesses to meet minimum cyber-security standards and notify individuals of security breaches involving
personal information. State consumer protection laws may also apply to privacy and security practices related to personally identifiable information, including information related to consumers and care providers. Different approaches to state privacy and insurance regulation and varying enforcement philosophies may materially and adversely affect our ability to standardize our products and services across state lines. See Part I, Item 1A, “Risk Factors” for a discussion of the risks related to compliance with state privacy and security regulations.
Corporate Practice of Medicine and Fee-Splitting Laws. Certain of our businesses function as direct medical service providers and, as such, are subject to additional laws and regulations. Some states have corporate practice of medicine laws prohibiting specific types of entities from practicing medicine or employing physicians to practice medicine. Moreover, some states prohibit certain entities from engaging in fee-splitting practices, which involve sharing in the fees or revenues of a professional practice. These prohibitions may be statutory or regulatory, or may be imposed through judicial or regulatory interpretation. The laws, regulations and interpretations in certain states have been subject to limited judicial and regulatory interpretation and are subject to change.
Pharmacy and Pharmacy Benefits Management (PBM) Regulations
Optum Rx’s businesses include home delivery, specialty and compounding pharmacies, as well as clinic-based pharmacies which must be licensed as pharmacies in the states in which they are located. Certain of our pharmacies must also register with the U.S. Drug Enforcement Administration (DEA) and individual state controlled substance authorities to dispense controlled substances. In addition to adhering to the laws and regulations in the states where our pharmacies are located, we also are required to comply with laws and regulations in some non-resident states where we deliver pharmaceuticals, including those requiring us to register with the board of pharmacy in the non-resident state. These non-resident states generally expect our pharmacies to follow the laws of the state in which the pharmacies are located, but some non-resident states also require us to comply with their laws where pharmaceuticals are delivered. Additionally, certain of our pharmacies which participate in programs for Medicare and state Medicaid providers are required to comply with applicable Medicare and Medicaid provider rules and regulations. Other laws and regulations affecting our pharmacies include federal and state statutes and regulations governing the labeling, packaging, advertising and adulteration of prescription drugs and dispensing of controlled substances. See Part I, Item 1A, “Risk Factors” for a discussion of the risks related to our pharmacy care services businesses.
Federal and state legislation regulating PBM activities affects both our ability to limit access to a pharmacy provider network or remove network providers. Additionally, many states limit our ability to manage and establish maximum allowable costs for generic prescription drugs. With respect to formulary services, a number of government entities, including CMS, HHS and state departments of insurance, regulate the administration of prescription drug benefits offered through federal or state exchanges. Many states also regulate the scope of prescription drug coverage, as well as the delivery channels to receive such prescriptions, for insurers, MCOs and Medicaid managed care plans. These regulations could limit or preclude (i) certain plan designs, (ii) limited networks, (iii) use of particular care providers or distribution channels, (iv) copayment differentials among providers and (v) formulary tiering practices.
Legislation seeking to regulate PBM activities introduced or enacted at the federal or state level could impact our business practices with others in the pharmacy supply chain, including pharmaceutical manufacturers and network providers. In addition, organizations like the NAIC periodically issue model regulations while credentialing organizations, like the National Committee for Quality Assurance (NCQA) and the Utilization Review Accreditation Commission (URAC), may establish standards impacting PBM pharmacy activities. Although these model regulations and standards do not have the force of law, they may influence states to adopt their recommendations and impact the services we deliver to our clients.
Consumer Protection Laws
Certain of our businesses participate in direct-to-consumer activities and are subject to regulations applicable to online communications and other general consumer protection laws and regulations such as the Federal Tort Claims Act, the Federal Postal Service Act and the FTC’s Telemarketing Sales Rule. Most states also have similar consumer protection laws.
Certain laws, such as the Telephone Consumer Protection Act, give the FTC, the Federal Communications Commission (FCC) and state attorneys general the ability to regulate, and bring enforcement actions relating to, telemarketing practices and certain automated outbound contacts such as phone calls, texts or emails. Under certain circumstances, these laws may provide consumers with a private right of action. Violations of these laws could result in substantial statutory penalties and other sanctions.
Banking Regulation
Optum Bank is subject to regulation by federal banking regulators, including the Federal Deposit Insurance Corporation (FDIC), which performs annual examinations to ensure the bank is operating in accordance with federal safety and soundness requirements, and the Consumer Financial Protection Bureau, which may perform periodic examinations to ensure the bank is
in compliance with applicable consumer protection statutes, regulations and agency guidelines. Optum Bank is also subject to supervision and regulation by the Utah State Department of Financial Institutions, which carries out annual examinations to ensure the bank is operating in accordance with state safety and soundness requirements and performs periodic examinations of the bank’s compliance with applicable state banking statutes, regulations and agency guidelines. In the event of unfavorable examination results from any of these agencies, the bank could become subject to increased operational expenses and capital requirements, enhanced governmental oversight and monetary penalties.
Non-U.S. Regulation
Certain of our businesses operate internationally and are subject to regulation in the jurisdictions in which they are organized or conduct business. These regulatory regimes vary from jurisdiction to jurisdiction. In addition, our non-U.S. businesses and operations are subject to U.S. laws regulating the conduct and activities of U.S.-based businesses operating abroad, such as the Foreign Corrupt Practices Act (FCPA), which prohibits offering, promising, providing or authorizing others to give anything of value to a foreign government official to obtain or retain business or otherwise secure a business advantage.
COMPETITION
As a diversified health care company, we operate in highly competitive markets across the full expanse of health care benefits and services. Our competitors include organizations ranging from startups to highly sophisticated Fortune 50 global enterprises, for-profit and non-profit companies, and private and government-sponsored entities. New entrants to our markets and business combinations among our competitors and suppliers also contribute to a dynamic and competitive environment. We compete fundamentally on the quality and value we provide to those we serve which can include elements such as product and service innovation; use of technology; consumer and provider engagement and satisfaction; and sales, marketing and pricing. See Part I, Item 1A, “Risk Factors” for additional discussion of our risks related to competition.
INTELLECTUAL PROPERTY RIGHTS
We have obtained trademark registration for the UnitedHealth Group, Optum and UnitedHealthcare names and logos. We own registrations for certain of our other trademarks in the United States and abroad. We hold a portfolio of patents and have patent applications pending from time to time. We are not substantially dependent on any single patent or group of related patents.
Unless otherwise noted, trademarks appearing in this report are trademarks owned by us. We disclaim any proprietary interest in the marks and names of others.
HUMAN CAPITAL RESOURCES
Our nearly 400,000 employees, as of December 31, 2022, including more than 140,000 clinical professionals, are guided by our mission to help people live healthier lives and help make the health system work better for everyone. Our mission and cultural values of integrity, compassion, relationships, innovation and performance align with our long-term business strategy to increase access to care, make care more affordable, enhance the care experience, improve health outcomes and advance health equity. Our mission and values attract individuals who are determined to make a difference – individuals whose talent, innovation, engagement and empowerment are critical in our ability to achieve our mission. Similar to other businesses, in 2022 we experienced moderately higher levels of employment attrition, but due to increased recruiting capacity, upgraded digital capabilities and continued investment in our workforce, we continue to be able to meet the needs of those we serve.
We are committed to developing our people and culture by creating an inclusive environment where people of diverse backgrounds, experiences and perspectives make us better. Our approach is data-driven and leader led and uses enterprise and business scorecards to ensure our leaders are accountable for a consistent focus on hiring, developing, advancing and retaining diverse talent. We have embedded inclusion and diversity throughout our culture, including in our talent acquisition and talent management practices; leadership development; careers; learning and skills; and systems and processes. We strive to maintain a sustainable and diverse talent pipeline by building strong strategic partnerships and outreach through early career programs, internships and apprenticeships. We support career coaching, mentorship and accelerated leadership development programs to ensure mobility and advancement for our diverse talent. To foster an engaged workforce and an inclusive culture, we invest in a broad array of learning and culture development programs. We rely on a shared leadership framework, which clearly and objectively defines our expectations, enables an environment where everyone has the opportunity to learn and grow, and helps us identify, develop and deploy talent to help achieve our mission.
We prioritize pay equity by regularly evaluating and reviewing our compensation practices by gender, ethnicity and race. Receiving on-going feedback from our team members is another way to strengthen and reinforce a culture of inclusion. Our Employee Experience Index measures an employee’s sense of commitment and belonging to our company and is a metric in the Stewardship section of our annual incentive plan. Our Sustainability Report, which can be accessed on our website at www.unitedhealthgroup.com, provides further information about our people and culture.
INFORMATION ABOUT OUR EXECUTIVE OFFICERS
The following sets forth certain information regarding our executive officers as of February 24, 2023, including the business experience of each executive officer during the past five years:
| Name | Age | Position | ||||||||||||
| Andrew Witty | 58 | Chief Executive Officer | ||||||||||||
| Dirk McMahon | 63 | President and Chief Operating Officer | ||||||||||||
| John Rex | 61 | Executive Vice President and Chief Financial Officer | ||||||||||||
| Rupert Bondy | 61 | Executive Vice President, Chief Legal Officer and Corporate Secretary | ||||||||||||
| Erin McSweeney | 58 | Executive Vice President and Chief People Officer | ||||||||||||
| Thomas Roos | 50 | Senior Vice President and Chief Accounting Officer | ||||||||||||
| Brian Thompson | 48 | Chief Executive Officer of UnitedHealthcare |
Our Board of Directors elects executive officers annually. Our executive officers serve until their successors are duly elected and qualified, or until their earlier death, resignation, removal or disqualification.
Andrew Witty has served as Chief Executive Officer and a member of the Board of Directors of UnitedHealth Group since February 2021. Previously, Andrew served as Chief Executive Officer of Optum from July 2018 to April 2021, President of UnitedHealth Group from November 2019 to February 2021 and as a UnitedHealth Group director from August 2017 to March 2018. Prior to joining UnitedHealth Group, he was Chief Executive Officer and a board member of GlaxoSmithKline, a global pharmaceutical company, from 2008 to 2017.
Dirk McMahon has served as President and Chief Operating Officer of UnitedHealth Group since February 2021. He previously served as Chief Executive Officer of UnitedHealthcare June 2019 to April 2021, President and Chief Operating Officer of Optum from April 2017 to June 2019 and Executive Vice President, Operations at UnitedHealth Group from November 2014 to April 2017. Dirk also served as Chief Executive Officer of Optum Rx from November 2011 to November 2014. Prior to 2011, he held various positions in UnitedHealthcare in operations, technology and finance.
John Rex has served as Executive Vice President and Chief Financial Officer of UnitedHealth Group since June 2016. From March 2012 to June 2016, he served as Executive Vice President and Chief Financial Officer of Optum. Prior to joining Optum in 2012, John was a Managing Director at JP Morgan, a global financial services firm.
Rupert Bondy has served as Executive Vice President and Chief Legal Officer of UnitedHealth Group since March 2022 and additionally as Corporate Secretary since April 2022. Prior to joining UnitedHealth Group, Rupert served as Senior Vice President, General Counsel and Corporate Secretary at Reckitt Benckiser Group, a consumer goods group focused on hygiene, health and nutrition products, from January 2017 to February 2022. Prior to joining Reckitt Benckieser Group, he served as Group General Counsel of BP plc, an international energy company, and, among his prior positions, as Senior Vice President and General Counsel of GlaxoSmithKline, a global pharmaceutical company.
Erin McSweeney has served as Executive Vice President and Chief People Officer of UnitedHealth Group since March 2022. From February 2021 to March 2022, Erin served as chief of staff to UnitedHealth Group’s Office of the Chief Executive. From January 2017 to February 2021, she served as Executive Vice President and Chief Human Resources Officer at Optum. Prior to joining UnitedHealth Group, Erin was Executive Vice President and Chief Human Resources Officer for EMC Corporation, an international technology company.
Tom Roos has served as Senior Vice President and Chief Accounting Officer of UnitedHealth Group since August 2015. Prior to joining UnitedHealth Group, Tom was a Partner at Deloitte & Touche LLP, an independent registered public accounting firm.
Brian Thompson has served as Chief Executive Officer of UnitedHealthcare since April 2021. Prior to this role, he served as Chief Executive Officer of UnitedHealthcare's government programs including Medicare & Retirement and Community & State from July 2019 to April 2021; as Chief Executive Officer of Medicare & Retirement from April 2017 to July 2019; and as Chief Financial Officer of UnitedHealthcare’s Employer & Individual and Medicare & Retirement businesses from August 2010 to April 2017.
Additional Information
Our executive offices are located at UnitedHealth Group Center, 9900 Bren Road East, Minnetonka, Minnesota 55343; our telephone number is (952) 936-1300.
You can access our website at www.unitedhealthgroup.com to learn more about our company. We make periodic and current reports and amendments available, free of charge, on our website, as soon as reasonably practicable after we file or furnish these reports to the Securities and Exchange Commission (SEC). Information on or linked to our website is neither part of nor incorporated by reference into this Annual Report on Form 10-K or any other SEC filings.
Item 1A. RISK FACTORS
CAUTIONARY STATEMENTS
The statements, estimates, projections or outlook contained in this Annual Report on Form 10-K include forward-looking statements within the meaning of the Private Securities Litigation Reform Act of 1995 (PSLRA). When used in this Annual Report on Form 10-K and in future filings by us with the SEC, in our news releases, presentations to securities analysts or investors, and in oral statements made by or with the approval of one of our executive officers, the words “believe,” “expect,” “intend,” “estimate,” “anticipate,” “forecast,” “outlook,” “plan,” “project,” “should” or similar words or phrases are intended to identify such forward-looking statements. These statements are intended to take advantage of the “safe harbor” provisions of the PSLRA. These forward-looking statements involve risks and uncertainties which may cause our actual results to differ materially from the expectations expressed or implied in the forward-looking statements. Any forward-looking statement in this report speaks only as of the date of this report and, except as required by law, we undertake no obligation to update any forward-looking statement to reflect events or circumstances, including unanticipated events, after the date of this report.
The following discussion contains cautionary statements regarding our business, which investors and others should consider. We do not undertake to address in future filings or communications regarding our business or results of operations how any of these factors may have caused our results to differ from discussions or information contained in previous filings or communications. In addition, any of the matters discussed below may have affected past, as well as current, forward-looking statements about future results. Any or all forward-looking statements in this Annual Report on Form 10-K and in any other SEC filings or public statements we make may turn out to be wrong. Our forward-looking statements can be affected by inaccurate assumptions we might make or by known or unknown risks and uncertainties. Many factors discussed below will be important in determining our future results. By their nature, forward-looking statements are not guarantees of future performance or results and are subject to risks, uncertainties and assumptions which are difficult to predict or quantify.
Risks Related to Our Business and Our Industry
If we fail to estimate, price for and manage our medical costs or set benefit designs in an effective manner, the profitability of our risk-based products and services could decline and could materially and adversely affect our results of operations, financial position and cash flows.
Through our risk-based benefit products, we assume the risk of both medical and administrative costs for our customers in return for monthly premiums. We generally use approximately 80% to 85% of our premium revenues to pay the costs of health care services delivered to these customers. The profitability of our products depends in large part on our ability to predict, price for and effectively manage medical costs. Our Optum Health business also enters into fully accountable value-based arrangements with payers. Premium revenues from risk-based products comprise nearly 80% of our total consolidated revenues. If we fail to predict accurately, or effectively price for or manage, the costs of providing care under risk-based arrangements, our results of operations could be materially and adversely affected.
We manage medical costs through underwriting criteria, product design, negotiation of competitive provider contracts and care management programs. Total medical costs are affected by the number of individual services rendered, the cost of each service and the type of service rendered. Our premium revenue on commercial policies and Medicaid contracts is typically based on a fixed monthly rate per individual or family served for a 12-month period and is generally priced one to six months before the contract commences. Our revenue on certain Medicare policies is based on bids submitted to CMS in June of the year before the contract year. Our premium revenue on fully accountable value-based care products at Optum Health is typically based on a fixed monthly rate per individual served. Although we base the commercial, Medicaid and value-based premiums we charge and our Medicare bids on our estimates of future medical costs over the fixed contract period, many factors may cause actual costs to exceed those estimated and reflected in premiums or bids. These factors may include medical cost inflation, increased use of services, increased cost of individual services, costs to deliver care, large-scale medical emergencies, the potential effects of climate change, pandemics, the introduction of new or costly drugs, treatments and technology, new treatment guidelines, newly mandated benefits or other regulatory changes and insured population characteristics. For Optum Health’s fully accountable value-based care, our inability to provide higher-quality outcomes and better experiences at lower costs or our
inability to integrate our care delivery models could impact our results of operations, financial positions and cash flows. Relatively small differences between predicted and actual medical costs or utilization rates as a percentage of revenues can result in significant changes in our financial results.
In addition, the financial results we report for any particular period include estimates of costs incurred for which claims are still outstanding. These estimates involve an extensive degree of judgment. If these estimates prove inaccurate, our results of operations could be materially and adversely affected.
If we fail to maintain properly the integrity or availability of our data or successfully consolidate, integrate, upgrade or expand our existing information systems, or if our technology products do not operate as intended, our business could be materially and adversely affected.
Our business depends on the integrity and timeliness of the data we use to serve our members, customers and health care professionals and to operate our business. If the data we rely upon to run our businesses is found to be inaccurate or unreliable or if we fail to maintain or protect our information systems and data integrity effectively, we could experience failures in our health, wellness and information technology products; lose existing customers; have difficulty attracting new customers; experience problems in determining medical cost estimates and establishing appropriate pricing; have difficulty preventing, detecting and controlling fraud; have disputes with customers, physicians and other health care professionals; become subject to regulatory sanctions, penalties, investigations or audits; incur increases in operating expenses; or suffer other adverse consequences.
The volume of health care data generated, and the uses of data, including electronic health records, are rapidly expanding. Our ability to implement new and innovative services, automate and deploy new technologies to simplify administrative processes and clinical decision making, price our products and services adequately, provide effective service to our customers and consumers in an efficient and uninterrupted fashion, provide timely payments to care providers, and report accurately our results of operations depends on the integrity of the data in our information systems. In addition, connectivity among technologies is becoming increasingly important and recent trends toward greater consumer engagement in health care require new and enhanced technologies, including more sophisticated applications for mobile devices. Our information systems require an ongoing commitment of significant resources to maintain, protect and enhance existing systems and develop new systems to keep pace with continuing changes in information processing technology, ev
Showing the first 8K of 66K characters. Open the full section
Item 1B. UNRESOLVED STAFF COMMENTS
None.
Item 2. PROPERTIES
We own and lease real properties to support our business operations in the United States and other countries. Our reportable segments use these facilities for their respective business purposes, and we believe the current facilities are suitable for their respective uses and are adequate for our anticipated future needs.
Item 3. LEGAL PROCEEDINGS
The information required by this Item 3 is incorporated herein by reference to the information set forth under the captions “Legal Matters” and “Governmental Investigations, Audits and Reviews” in Note 12 of the Notes to the Consolidated Financial Statements included in Part II, Item 8, “Financial Statements and Supplementary Data”
Item 4. MINE SAFETY DISCLOSURES
Not Applicable.
PART II
Item 5. MARKET FOR REGISTRANT’S COMMON EQUITY, RELATED STOCKHOLDER MATTERS AND ISSUER PURCHASES OF EQUITY SECURITIES
MARKET AND HOLDERS
Our common stock is traded on the New York Stock Exchange (NYSE) under the symbol UNH. On January 31, 2023, there were 10,260 holders of record of our common stock.
DIVIDEND POLICY
In June 2022, the Company’s Board of Directors increased the Company’s quarterly cash dividend to shareholders to an annual rate of $6.60 compared to $5.80 per share, which the Company had paid since June 2021. Declaration and payment of future quarterly dividends is at the discretion of the Board and may be adjusted as business needs or market conditions change.
ISSUER PURCHASES OF EQUITY SECURITIES
Issuer Purchases of Equity Securities (a)
Fourth Quarter 2022
| For the Month Ended | Total Number of Shares Purchased | Average Price Paid Per Share | Total Number of Shares Purchased as Part of Publicly Announced Plans or Programs | Maximum Number of Shares That May Yet Be Purchased Under The Plans or Programs | ||||||||||||||||||||||
| (in millions) | (in millions) | (in millions) | ||||||||||||||||||||||||
| October 31, 2022 | 0.7 | $ | 519.51 | 0.7 | 32.3 | |||||||||||||||||||||
| November 30, 2022 | 0.6 | 533.81 | 0.6 | 31.7 | ||||||||||||||||||||||
| December 31, 2022 | 0.6 | 533.56 | 0.6 | 31.1 | ||||||||||||||||||||||
| Total | 1.9 | $ | 528.87 | 1.9 |
(a) In November 1997, our Board of Directors adopted a share repurchase program, which the Board evaluates periodically. In June 2018, the Board of Directors renewed our share repurchase program with an authorization to repurchase up to 100 million shares of our common stock in open market purchases or other types of transactions (including prepaid or structured repurchase programs). There is no established expiration date for the program.
PERFORMANCE GRAPH
The following performance graph compares the cumulative five-year total return to shareholders on our common stock relative to the cumulative total returns of the S&P Health Care Index, the Dow Jones US Industrial Average Index and the S&P 500 Index for the five-year period ended December 31, 2022. The comparisons assume the investment of $100 on December 31, 2017 in our common stock and in each index, and dividends were reinvested when paid.
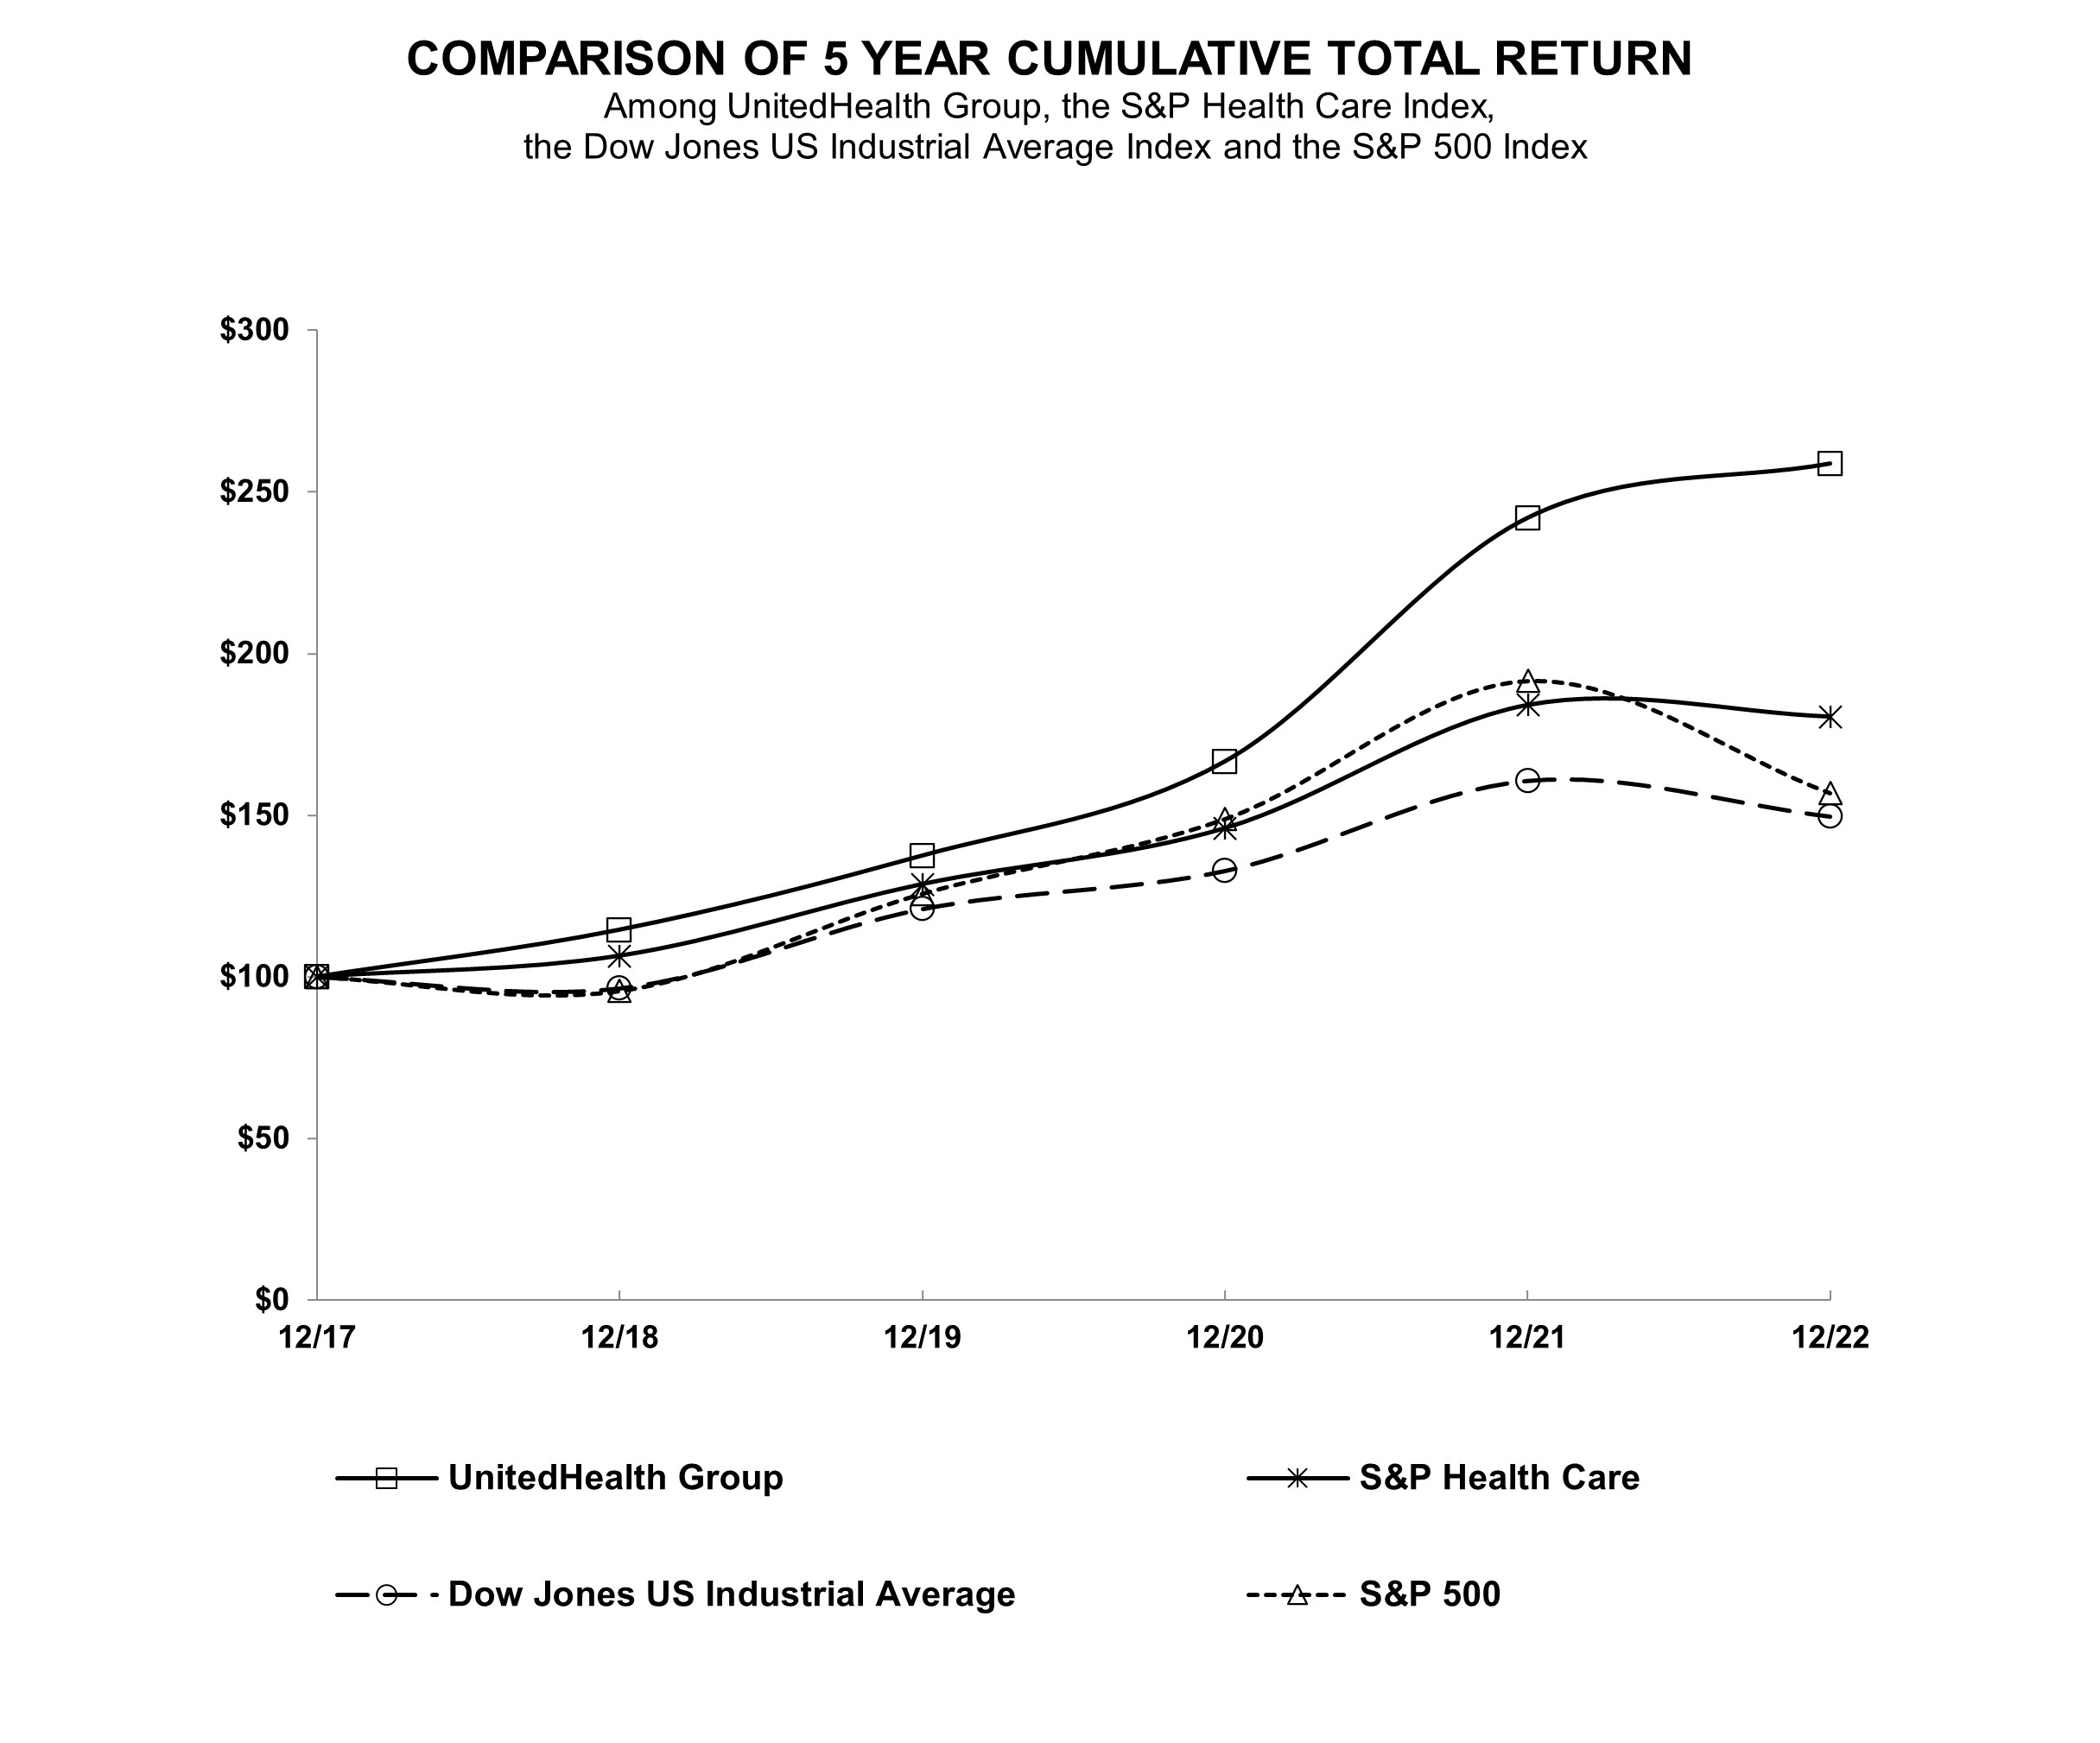
| 12/17 | 12/18 | 12/19 | 12/20 | 12/21 | 12/22 | ||||||||||||||||||||||||||||||
| UnitedHealth Group | $ | 100.00 | $ | 114.52 | $ | 137.41 | $ | 166.55 | $ | 241.85 | $ | 258.65 | |||||||||||||||||||||||
| S&P Health Care Index | 100.00 | 106.47 | 128.64 | 145.93 | 184.07 | 180.47 | |||||||||||||||||||||||||||||
| Dow Jones US Industrial Average | 100.00 | 96.52 | 120.98 | 132.75 | 160.55 | 149.53 | |||||||||||||||||||||||||||||
| S&P 500 Index | 100.00 | 95.62 | 125.72 | 148.85 | 191.58 | 156.89 |
The stock price performance included in this graph is not necessarily indicative of future stock price performance.
Item 6. [Reserved]
Item 7. MANAGEMENT’S DISCUSSION AND ANALYSIS OF FINANCIAL CONDITION AND RESULTS OF OPERATIONS
The following discussion should be read together with the accompanying Consolidated Financial Statements and Notes to the Consolidated Financial Statements thereto included in Part II Item 8, “Financial Statements and Supplementary Data.” Readers are cautioned the statements, estimates, projections or outlook contained in this report, including discussions regarding financial prospects, economic conditions, trends and uncertainties contained in this Item 7, may constitute forward-looking statements within the meaning of the PSLRA. These forward-looking statements involve risks and uncertainties which may cause our actual results to differ materially from the expectations expressed or implied in the forward-looking statements. A description of some of the risks and uncertainties can be found further below in this Item 7 and in Part I, Item 1A, “Risk Factors.”
Discussions of year-over-year comparisons between 2021 and 2020 are not included in this Form 10-K and can be found in Part II, Item 7, “Management’s Discussion and Analysis of Financial Condition and Results of Operations” of the Company’s Form 10-K for the fiscal year ended December 31, 2021.
EXECUTIVE OVERVIEW
General
UnitedHealth Group is a diversified health care company with a mission to help people live healthier lives and help make the health system work better for everyone. Our two complementary businesses — Optum and UnitedHealthcare — are driven by this unified mission and vision to improve health care access, affordability, experiences and outcomes for the individuals and organizations we are privileged to serve.
We have four reportable segments across our two business platforms, Optum and UnitedHealthcare:
-
Optum Health;
-
Optum Insight;
-
Optum Rx; and
-
UnitedHealthcare, which includes UnitedHealthcare Employer & Individual, UnitedHealthcare Medicare & Retirement and UnitedHealthcare Community & State.
Further information on our business and reportable segments is presented in Part I, Item 1, “Business” and in Note 14 of the Notes to the Consolidated Financial Statements included in Part II, Item 8, “Financial Statements and Supplementary Data.”
Business Trends
Our businesses participate in the United States, South America and certain other international health markets. In the United States, health care spending has grown consistently for many years and comprises 18% of gross domestic product (GDP). We expect overall spending on health care to continue to grow in the future, due to inflation, medical technology and pharmaceutical advancement, regulatory requirements, demographic trends in the population and national interest in health and well-being. The rate of market growth may be affected by a variety of factors, including macroeconomic conditions, which could impact our results of operations, including our continued efforts to control health care costs.
Pricing Trends. To price our health care benefits, products and services, we start with our view of expected future costs, including inflation and labor market dynamics. We frequently evaluate and adjust our approach in each of the local markets we serve, considering relevant factors, such as product positioning, price competitiveness and environmental, competitive, legislative and regulatory considerations, including minimum medical loss ratio (MLR) thresholds and similar revenue adjustments. We will continue seeking to balance growth and profitability across all these dimensions.
The commercial risk market remains highly competitive in the small group, large group and individual segments. We expect broad-based competition to continue as the industry adapts to individual and employer needs.
Medicare Advantage funding continues to be pressured, as discussed below in “Regulatory Trends and Uncertainties.”
In Medicaid, we believe the payment rate environment creates the risk of continued downward pressure on Medicaid margin percentages. We continue to take a prudent, market-sustainable posture for both new business and maintenance of existing relationships. We continue to advocate for actuarially sound rates commensurate with our medical cost trends and we remain dedicated to partnering with those states that are committed to the long-term viability of their programs.
Medical Cost Trends. Our medical cost trends primarily relate to changes in unit costs; care activity; and prescription drug costs. We endeavor to mitigate those increases by engaging physicians and consumers with information and helping them make clinically sound choices, with the objective of helping them achieve high-quality, affordable care.
Medicaid Redeterminations. In December 2022, Congress passed the 2023 Omnibus Appropriations bill that allows states to resume Medicaid redeterminations beginning in April 2023. Redeterminations will result in a decline in people served through our Medicaid business and an expected increase in people served through our commercial and exchange-based offerings as we endeavor to ensure that people have continued access to benefits.
Delivery System and Payment Modernization. The health care market continues to change based on demographic shifts, new regulations, political forces and both payer and patient expectations. Health plans and care providers are being called upon to work together to close gaps in care and improve overall care quality and patient experience, improve the health of populations and reduce costs. We are working to accelerate this vision through the innovation and integration of our care delivery models including in clinic, in-home, behavioral and virtual care, and by using our data and analytics to provide clinicians with the necessary information in order to provide the best possible care in the most cost efficient setting. We continue to see a greater number of people enrolled in fully accountable value-based plans rewarding high-quality, affordable care and fostering collaboration.
This trend is creating needs for health management services which can coordinate care around the primary care physician, including new primary care channels, and for investments in new clinical and administrative information and management systems, which we believe provide growth opportunities for our Optum business platform.
Regulatory Trends and Uncertainties
Following is a summary of management’s view of the trends and uncertainties related to regulatory matters. For additional information regarding regulatory trends and uncertainties, see Part I, Item 1 “Business - Government Regulation” and Item 1A, “Risk Factors.”
Medicare Advantage Rates. Medicare Advantage rate notices over the years have at times resulted in industry base rates well below industry forward medical trend. For example, the February 2023 Advance Notice for 2024 rates would result in an industry base rate decrease, well short of what is an increasing industry forward medical cost trend, creating continued pressure in the Medicare Advantage program. Further, proposed substantial revisions to the risk adjustment model, which serves to adjust rates to reflect a patient’s health status and care resource needs, would result in reduced funding and benefits for people, especially those with some of the greatest health and social challenges.
As a result of ongoing Medicare funding pressures, there are adjustments we can make to partially offset these rate pressures and reductions for a particular period. For example, we can seek to intensify our medical and operating cost management, make changes to the size and composition of our care provider networks, adjust member benefits and implement or increase the member premiums supplementing the monthly payments we receive from the government. Additionally, we decide annually on a county-by-county basis where we will offer Medicare Advantage plans.
SELECTED OPERATING PERFORMANCE ITEMS
The following represents a summary of select 2022 year-over-year operating comparisons to 2021.
-
Consolidated revenues increased by 13%, UnitedHealthcare revenues increased 12% and Optum revenues grew 17%.
-
UnitedHealthcare served nearly 1.1 million more people, led by growth in community-based and senior offerings.
-
Earnings from operations increased by 19%, including an increase of 20% at UnitedHealthcare and 17% at Optum.
-
Diluted earnings per common share increased 17% to $21.18.
-
Cash flows from operations were $26.2 billion.
-
Return on equity was 27.2%.
RESULTS SUMMARY
The following table summarizes our consolidated results of operations and other financial information:
| (in millions, except percentages and per share data) | For the Years Ended December 31, | Change | ||||||||||||||||||||||||||||||
| 2022 | 2021 | 2020 | 2022 vs. 2021 | |||||||||||||||||||||||||||||
| Revenues: | ||||||||||||||||||||||||||||||||
| Premiums | $ | 257,157 | $ | 226,233 | $ | 201,478 | $ | 30,924 | 14 | % | ||||||||||||||||||||||
| Products | 37,424 | 34,437 | 34,145 | 2,987 | 9 | |||||||||||||||||||||||||||
| Services | 27,551 | 24,603 | 20,016 | 2,948 | 12 | |||||||||||||||||||||||||||
| Investment and other income | 2,030 | 2,324 | 1,502 | (294) | (13) | |||||||||||||||||||||||||||
| Total revenues | 324,162 | 287,597 | 257,141 | 36,565 | 13 | |||||||||||||||||||||||||||
| Operating costs: | ||||||||||||||||||||||||||||||||
| Medical costs | 210,842 | 186,911 | 159,396 | 23,931 | 13 | |||||||||||||||||||||||||||
| Operating costs | 47,782 | 42,579 | 41,704 | 5,203 | 12 | |||||||||||||||||||||||||||
| Cost of products sold | 33,703 | 31,034 | 30,745 | 2,669 | 9 | |||||||||||||||||||||||||||
| Depreciation and amortization | 3,400 | 3,103 | 2,891 | 297 | 10 | |||||||||||||||||||||||||||
| Total operating costs | 295,727 | 263,627 | 234,736 | 32,100 | 12 | |||||||||||||||||||||||||||
| Earnings from operations | 28,435 | 23,970 | 22,405 | 4,465 | 19 | |||||||||||||||||||||||||||
| Interest expense | (2,092) | (1,660) | (1,663) | (432) | 26 | |||||||||||||||||||||||||||
| Earnings before income taxes | 26,343 | 22,310 | 20,742 | 4,033 | 18 | |||||||||||||||||||||||||||
| Provision for income taxes | (5,704) | (4,578) | (4,973) | (1,126) | 25 | |||||||||||||||||||||||||||
| Net earnings | 20,639 | 17,732 | 15,769 | 2,907 | 16 | |||||||||||||||||||||||||||
| Earnings attributable to noncontrolling interests | (519) | (447) | (366) | (72) | 16 | |||||||||||||||||||||||||||
| Net earnings attributable to UnitedHealth Group common shareholders | $ | 20,120 | $ | 17,285 | $ | 15,403 | $ | 2,835 | 16 | % | ||||||||||||||||||||||
| Diluted earnings per share attributable to UnitedHealth Group common shareholders | $ | 21.18 | $ | 18.08 | $ | 16.03 | $ | 3.10 | 17 | % | ||||||||||||||||||||||
| Medical care ratio (a) | 82.0 | % | 82.6 | % | 79.1 | % | (0.6) | % | ||||||||||||||||||||||||
| Operating cost ratio | 14.7 | 14.8 | 16.2 | (0.1) | ||||||||||||||||||||||||||||
| Operating margin | 8.8 | 8.3 | 8.7 | 0.5 | ||||||||||||||||||||||||||||
| Tax rate | 21.7 | 20.5 | 24.0 | 1.2 | ||||||||||||||||||||||||||||
| Net earnings margin (b) | 6.2 | 6.0 | 6.0 | 0.2 | ||||||||||||||||||||||||||||
| Return on equity (c) | 27.2 | % | 25.2 | % | 24.9 | % | 2.0 | % |
(a)Medical care ratio (MCR) is calculated as medical costs divided by premium revenue.
(b)Net earnings margin attributable to UnitedHealth Group common shareholders.
(c)Return on equity is calculated as net earnings attributable to UnitedHealth Group common shareholders divided by average shareholders’ equity. Average shareholders’ equity is calculated using the shareholders’ equity balance at the end of the preceding year and the shareholders’ equity balances at the end of each of the four quarters of the year presented.
2022 RESULTS OF OPERATIONS COMPARED TO 2021 RESULTS
Consolidated Financial Results
Revenues
The increases in revenues were primarily driven by growth in the number of people served through Medicare Advantage and Medicaid, pricing trends and growth across the Optum businesses.
Medical Costs and MCR
Medical costs increased due to growth in people served. The MCR decreased due to COVID-19 effects, partially offset by decreased prior years favorable development and business mix.
Operating Cost Ratio
The operating cost ratio decreased primarily due to productivity gains, partially offset by investments and business mix.
Reportable Segments
See Note 14 of Notes to the Consolidated Financial Statements included in Part II, Item 8, “Financial Statements and Supplementary Data ” for more information on our segments. We utilize various metrics to evaluate and manage our reportable segments, including individuals served by UnitedHealthcare by major market segment and funding arrangement, people served by Optum Health and adjusted scripts for Optum Rx. These metrics are the main drivers of revenue, earnings and cash flows at each business. The metrics also allow management and investors to evaluate and understand business mix, including the level and scope of services provided to people and pricing trends when comparing the metrics to revenue by segment.
The following table presents a summary of the reportable segment financial information:
| For the Years Ended December 31, | Change | |||||||||||||||||||||||||||||||
| (in millions, except percentages) | 2022 | 2021 | 2020 | 2022 vs. 2021 | ||||||||||||||||||||||||||||
| Revenues | ||||||||||||||||||||||||||||||||
| UnitedHealthcare | $ | 249,741 | $ | 222,899 | $ | 200,875 | $ | 26,842 | 12 | % | ||||||||||||||||||||||
| Optum Health | 71,174 | 54,065 | 39,808 | 17,109 | 32 | |||||||||||||||||||||||||||
| Optum Insight | 14,581 | 12,199 | 10,802 | 2,382 | 20 | |||||||||||||||||||||||||||
| Optum Rx | 99,773 | 91,314 | 87,498 | 8,459 | 9 | |||||||||||||||||||||||||||
| Optum eliminations | (2,760) | (2,013) | (1,800) | (747) | 37 | |||||||||||||||||||||||||||
| Optum | 182,768 | 155,565 | 136,308 | 27,203 | 17 | |||||||||||||||||||||||||||
| Eliminations | (108,347) | (90,867) | (80,042) | (17,480) | 19 | |||||||||||||||||||||||||||
| Consolidated revenues | $ | 324,162 | $ | 287,597 | $ | 257,141 | $ | 36,565 | 13 | % | ||||||||||||||||||||||
| Earnings from operations | ||||||||||||||||||||||||||||||||
| UnitedHealthcare | $ | 14,379 | $ | 11,975 | $ | 12,359 | $ | 2,404 | 20 | % | ||||||||||||||||||||||
| Optum Health | 6,032 | 4,462 | 3,434 | 1,570 | 35 | |||||||||||||||||||||||||||
| Optum Insight | 3,588 | 3,398 | 2,725 | 190 | 6 | |||||||||||||||||||||||||||
| Optum Rx | 4,436 | 4,135 | 3,887 | 301 | 7 | |||||||||||||||||||||||||||
| Optum | 14,056 | 11,995 | 10,046 | 2,061 | 17 | |||||||||||||||||||||||||||
| Consolidated earnings from operations | $ | 28,435 | $ | 23,970 | $ | 22,405 | $ | 4,465 | 19 | % | ||||||||||||||||||||||
| Operating margin | ||||||||||||||||||||||||||||||||
| UnitedHealthcare | 5.8 | % | 5.4 | % | 6.2 | % | 0.4 | % | ||||||||||||||||||||||||
| Optum Health | 8.5 | 8.3 | 8.6 | 0.2 | ||||||||||||||||||||||||||||
| Optum Insight | 24.6 | 27.9 | 25.2 | (3.3) | ||||||||||||||||||||||||||||
| Optum Rx | 4.4 | 4.5 | 4.4 | (0.1) | ||||||||||||||||||||||||||||
| Optum | 7.7 | 7.7 | 7.4 | — | ||||||||||||||||||||||||||||
| Consolidated operating margin | 8.8 | % | 8.3 | % | 8.7 | % | 0.5 | % |
UnitedHealthcare
The following table summarizes UnitedHealthcare revenues by business:
| For the Years Ended December 31, | Change | |||||||||||||||||||||||||||||||
| (in millions, except percentages) | 2022 | 2021 | 2020 | 2022 vs. 2021 | ||||||||||||||||||||||||||||
| UnitedHealthcare Employer & Individual - Domestic | $ | 63,599 | $ | 60,023 | $ | 55,872 | $ | 3,576 | 6 | % | ||||||||||||||||||||||
| UnitedHealthcare Employer & Individual - Global (a) | 8,668 | 8,345 | 7,752 | 323 | 4 | |||||||||||||||||||||||||||
| UnitedHealthcare Employer & Individual - Total (a) | 72,267 | 68,368 | 63,624 | 3,899 | 6 | |||||||||||||||||||||||||||
| UnitedHealthcare Medicare & Retirement | 113,671 | 100,552 | 90,764 | 13,119 | 13 | |||||||||||||||||||||||||||
| UnitedHealthcare Community & State | 63,803 | 53,979 | 46,487 | 9,824 | 18 | |||||||||||||||||||||||||||
| Total UnitedHealthcare revenues | $ | 249,741 | $ | 222,899 | $ | 200,875 | $ | 26,842 | 12 | % |
(a) On January 1, 2022, we realigned our operating segments to combine UnitedHealthcare Global and UnitedHealthcare Employer & Individual.
The following table summarizes the number of individuals served by our UnitedHealthcare businesses, by major market segment and funding arrangement:
| December 31, | Change | |||||||||||||||||||||||||||||||
| (in thousands, except percentages) | 2022 | 2021 | 2020 | 2022 vs. 2021 | ||||||||||||||||||||||||||||
| Commercial - domestic: | ||||||||||||||||||||||||||||||||
| Risk-based | 8,045 | 7,985 | 7,910 | 60 | 1 | % | ||||||||||||||||||||||||||
| Fee-based | 18,640 | 18,595 | 18,310 | 45 | — | |||||||||||||||||||||||||||
| Total commercial - domestic | 26,685 | 26,580 | 26,220 | 105 | — | |||||||||||||||||||||||||||
| Medicare Advantage | 7,105 | 6,490 | 5,710 | 615 | 9 | |||||||||||||||||||||||||||
| Medicaid | 8,170 | 7,655 | 6,620 | 515 | 7 | |||||||||||||||||||||||||||
| Medicare Supplement (Standardized) | 4,375 | 4,395 | 4,460 | (20) | — | |||||||||||||||||||||||||||
| Total community and senior | 19,650 | 18,540 | 16,790 | 1,110 | 6 | |||||||||||||||||||||||||||
| Total UnitedHealthcare - domestic medical | 46,335 | 45,120 | 43,010 | 1,215 | 3 | |||||||||||||||||||||||||||
| Commercial - global | 5,360 | 5,510 | 5,425 | (150) | (3) | |||||||||||||||||||||||||||
| Total UnitedHealthcare - medical | 51,695 | 50,630 | 48,435 | 1,065 | 2 | % | ||||||||||||||||||||||||||
| Supplemental Data: | ||||||||||||||||||||||||||||||||
| Medicare Part D stand-alone | 3,295 | 3,700 | 4,045 | (405) | (11) | % |
Medicare Advantage increased due to growth in people served through individual and group Medicare Advantage plans. The increase in people served through Medicaid was primarily driven by states continuing to ease redetermination requirements and growth in people served through Dual Special Needs Plans.
UnitedHealthcare’s revenues increased due to growth in the number of people served through Medicare Advantage and Medicaid. Earnings from operations increased due to growth in people served and COVID-19 effects, partially offset by decreased prior years favorable development.
Optum
Total revenues and earnings from operations increased due to growth across the Optum businesses. The results by segment were as follows:
Optum Health
Revenues at Optum Health increased primarily due to organic growth in patients served under value-based care arrangements and business combinations. Earnings from operations increased due to organic growth in the number of people served under value-based care arrangements, cost management initiatives, asset dispositions and COVID-19 effects. Optum Health served approximately 102 million people as of December 31, 2022 compared to 100 million people as of December 31, 2021.
Optum Insight
Revenues and earnings from operations at Optum Insight increased due to growth in technology and managed services, with managed services revenue growth driven by business combinations and new health system partnerships.
Optum Rx
Revenues and earnings from operations at Optum Rx increased due to higher script volumes from growth in people served, increased utilization and organic growth in pharmacy care services, including community health, specialty and home delivery pharmacies. Earnings from operations also increased as a result of continued supply chain management initiatives. Optum Rx fulfilled 1,438 million and 1,368 million adjusted scripts in 2022 and 2021, respectively.
LIQUIDITY, FINANCIAL CONDITION AND CAPITAL RESOURCES
Liquidity
Introduction
We manage our liquidity and financial position in the context of our overall business strategy. We continually forecast and manage our cash, investments, working capital balances and capital structure to meet the short-term and long-term obligations of our businesses while seeking to maintain liquidity and financial flexibility. Cash flows generated from operating activities are principally from earnings before noncash expenses.
Our regulated subsidiaries generate significant cash flows from operations and are subject to, among other things, minimum levels of statutory capital, as defined by their respective jurisdictions, and restrictions on the timing and amount of dividends paid to their parent companies.
Our U.S. regulated subsidiaries paid their parent companies dividends of $8.8 billion and $8.0 billion in 2022 and 2021, respectively. See Note 10 of the Notes to the Consolidated Financial Statements included in Part II, Item 8, “Financial Statements and Supplementary Data” for further detail concerning our regulated subsidiary dividends.
Our nonregulated businesses also generate significant cash flows from operations available for general corporate use. Cash flows generated by these entities, combined with dividends from our regulated entities and financing through the issuance of long-term debt as well as issuance of commercial paper or the ability to draw under our committed credit facilities, further strengthen our operating and financial flexibility. We use these cash flows to expand our businesses through acquisitions, reinvest in our businesses through capital expenditures, repay debt and return capital to our shareholders through dividends and repurchases of our common stock.
Summary of our Major Sources and Uses of Cash and Cash Equivalents
| For the Years Ended December 31, | Change | |||||||||||||||||||||||||
| (in millions) | 2022 | 2021 | 2020 | 2022 vs. 2021 | ||||||||||||||||||||||
| Sources of cash: | ||||||||||||||||||||||||||
| Cash provided by operating activities | $ | 26,206 | $ | 22,343 | $ | 22,174 | $ | 3,863 | ||||||||||||||||||
| Issuances of long-term debt and short-term borrowings, net of repayments | 12,536 | 2,481 | 2,586 | 10,055 | ||||||||||||||||||||||
| Proceeds from common share issuances | 1,253 | 1,355 | 1,440 | (102) | ||||||||||||||||||||||
| Customer funds administered | 5,548 | 622 | 1,677 | 4,926 | ||||||||||||||||||||||
| Cash received for dispositions | 3,414 | 15 | 221 | 3,399 | ||||||||||||||||||||||
| Total sources of cash | 48,957 | 26,816 | 28,098 | |||||||||||||||||||||||
| Uses of cash: | ||||||||||||||||||||||||||
| Cash paid for acquisitions, net of cash assumed | (21,458) | (4,821) | (7,139) | (16,637) | ||||||||||||||||||||||
| Cash dividends paid | (5,991) | (5,280) | (4,584) | (711) | ||||||||||||||||||||||
| Common share repurchases | (7,000) | (5,000) | (4,250) | (2,000) | ||||||||||||||||||||||
| Purchases of property, equipment and capitalized software | (2,802) | (2,454) | (2,051) | (348) | ||||||||||||||||||||||
| Purchases of investments, net of sales and maturities | (6,837) | (1,843) | (2,836) | (4,994) | ||||||||||||||||||||||
| Purchases of redeemable noncontrolling interests | (176) | (1,338) | — | 1,162 | ||||||||||||||||||||||
| Other | (2,737) | (1,564) | (1,186) | (1,173) | ||||||||||||||||||||||
| Total uses of cash | (47,001) | (22,300) | (22,046) | |||||||||||||||||||||||
| Effect of exchange rate changes on cash and cash equivalents | 34 | (62) | (116) | 96 | ||||||||||||||||||||||
| Net increase in cash and cash equivalents | $ | 1,990 | $ | 4,454 | $ | 5,936 | $ | (2,464) |
2022 Cash Flows Compared to 2021 Cash Flows
Increased cash flows provided by operating activities were primarily driven by changes in working capital accounts and increased net earnings. Other significant changes in sources or uses of cash year-over-year included increased net issuances of long-term debt, customer funds administered, primarily driven by Medicare Part D timing and increased HSA deposits, cash received for dispositions and decreased purchases of redeemable noncontrolling interests, partially offset by increased cash paid for acquisitions, net purchases of investments and common stock repurchases.
Financial Condition
As of December 31, 2022, our cash, cash equivalent, available-for-sale debt securities and equity securities balances of $69.4 billion included $23.4 billion of cash and cash equivalents (of which $1.3 billion was available for general corporate use), $42.3 billion of debt securities and $3.7 billion of equity securities. Given the significant portion of our portfolio held in cash equivalents, we do not anticipate fluctuations in the aggregate fair value of our financial assets to have a material impact on our liquidity or capital position. Other sources of liquidity, primarily from operating cash flows and our commercial paper program, which is fully supported by our bank credit facilities, reduce the need to sell investments during adverse market conditions. See Note 4 of the Notes to the Consolidated Financial Statements included in Part II, Item 8, “Financial Statements and Supplementary Data” for further detail concerning our fair value measurements.
Our available-for-sale debt portfolio had a weighted-average duration of 4.0 years and a weighted-average credit rating of “Double A” as of December 31, 2022. When multiple credit ratings are available for an individual security, the average of the available ratings is used to determine the weighted-average credit rating.
Capital Resources and Uses of Liquidity
Cash Requirements. The Company’s cash requirements within the next twelve months include medical costs payable, accounts payable and accrued liabilities, short-term borrowings and current maturities of long-term debt, other current liabilities, and purchase commitments and other obligations. We expect the cash required to meet these obligations to be primarily generated through cash flows from current operations; cash available for general corporate use; and the realization of current assets, such as accounts receivable.
Our long-term cash requirements under our various contractual obligations and commitments include:
-
Debt obligations. See Note 8 of the Notes to the Consolidated Financial Statements included in Part II, Item 8, “Financial Statements and Supplementary Data” for further detail of our long-term debt and the timing of expected future payments. Interest coupon payments are typically paid semi-annually.
-
Operating leases. See Note 12 of the Notes to the Consolidated Financial Statements included in Part II, Item 8, “Financial Statements and Supplementary Data” for further detail of our obligations and the timing of expected future payments.
-
Purchase and other obligations. These include $5.6 billion, $2.9 billion of which is expected to be paid within the next twelve months, of fixed or minimum commitments under existing purchase obligations for goods and services, including agreements cancelable with the payment of an early termination penalty, and remaining capital commitments for venture capital funds and other funding commitments. These amounts exclude agreements cancelable without penalty and liabilities to the extent recorded in our Consolidated Balance Sheets as of December 31, 2022.
-
Other liabilities. These include other long-term liabilities reflected in our Consolidated Balance Sheets as of December 31, 2022, including obligations associated with certain employee benefit programs, unrecognized tax benefits and various long-term liabilities, which have some inherent uncertainty in the timing of these payments.
-
Redeemable noncontrolling interests. See Note 2 of the Notes to the Consolidated Financial Statements included in Part II, Item 8, “Financial Statements and Supplementary Data” for further detail. We do not have any material expected redemptions in the next twelve months.
We expect the cash required to meet our long-term obligations to be primarily generated through future cash flows from operations. However, we also have the ability to generate cash to satisfy both our current and long-term requirements through the issuance of commercial paper, issuance of long-term debt, or drawing under our committed credit facilities or the ability to sell investments. We believe our capital resources are sufficient to meet future, short-term and long-term, liquidity needs.
Short-Term Borrowings. Our revolving bank credit facilities provide liquidity support for our commercial paper borrowing program, which facilitates the private placement of senior unsecured debt through independent broker-dealers, and are available for general corporate purposes. For more information on our commercial paper and bank credit facilities, see Note 8 of the Notes to the Consolidated Financial Statements included in Part II, Item 8, “Financial Statements and Supplementary Data.”
Our revolving bank credit facilities contain various covenants, including covenants requiring us to maintain a defined debt to debt-plus-shareholders’ equity ratio of not more than 60%, subject to increase in certain circumstances set forth in the applicable credit agreement. As of December 31, 2022, our debt to debt-plus-shareholders’ equity ratio, as defined and calculated under the credit facilities, was 38%.
Long-Term Debt. Periodically, we access capital markets to issue long-term debt for general corporate purposes, such as to meet our working capital requirements, to refinance debt, to finance acquisitions or for share repurchases. For more information on our debt, see Note 8 of the Notes to the Consolidated Financial Statements included in Part II, Item 8 “Financial Statements and Supplementary Data.”
Credit Ratings. Our credit ratings as of December 31, 2022 were as follows:
| Moody’s | S&P Global | Fitch | A.M. Best | ||||||||||||||||||||||||||||||||||||||||||||
| Ratings | Outlook | Ratings | Outlook | Ratings | Outlook | Ratings | Outlook | ||||||||||||||||||||||||||||||||||||||||
| Senior unsecured debt | A3 | Positive | A+ | Stable | A | Stable | A | Stable | |||||||||||||||||||||||||||||||||||||||
| Commercial paper | P-2 | n/a | A-1 | n/a | F1 | n/a | AMB-1+ | n/a |
The availability of financing in the form of debt or equity is influenced by many factors, including our profitability, operating cash flows, debt levels, credit ratings, debt covenants and other contractual restrictions, regulatory requirements and economic and market conditions. A significant downgrade in our credit ratings or adverse conditions in the capital markets may increase the cost of borrowing for us or limit our access to capital.
Share Repurchase Program. As of December 31, 2022, we had Board of Directors’ authorization to purchase up to 31 million shares of our common stock. For more information on our share repurchase program, see Note 10 of the Notes to the Consolidated Financial Statements included in Part II, Item 8, “Financial Statements and Supplementary Data.”
Dividends. In June 2022, the Company’s Board of Directors increased the Company’s quarterly cash dividend to shareholders to an annual rate of $6.60 compared to $5.80 per share. For more information on our dividend, see Note 10 of the Notes to the Consolidated Financial Statements included in Part II, Item 8, “Financial Statements and Supplementary Data.”
Pending Acquisitions. As of December 31, 2022, we have entered into agreements to acquire companies in the health care sector, most notably, LHC Group, Inc. (NASDAQ: LHCG), subject to regulatory approval and other customary closing conditions. The total anticipated capital required for these acquisitions, excluding the payoff of acquired indebtedness, is approximately $9 billion. We completed the acquisition of LHC Group, Inc. on February 22, 2023.
We do not have other significant contractual obligations or commitments requiring cash resources. However, we continually evaluate opportunities to expand our operations, which include internal development of new products, programs and technology applications and may include acquisitions.
CRITICAL ACCOUNTING ESTIMATES
Critical accounting estimates are those estimates requiring management to make challenging, subjective or complex judgments, often because they must estimate the effects of matters inherently uncertain and may change in subsequent periods. Critical accounting estimates involve judgments and uncertainties which are sufficiently sensitive and may result in materially different results under different assumptions and conditions.
Medical Costs Payable
Medical costs and medical costs payable include estimates of our obligations for medical care services rendered on behalf of consumers, but for which claims have either not yet been received or processed. Depending on the health care professional and type of service, the typical billing lag for services can be up to 90 days from the date of service. Approximately 90% of claims related to medical care services are known and settled within 90 days from the date of service.
In each reporting period, our operating results include the effects of more completely developed medical costs payable estimates associated with previously reported periods. If the revised estimate of prior period medical costs is less than the previous estimate, we will decrease reported medical costs in the current period (favorable development). If the revised estimate of prior period medical costs is more than the previous estimate, we will increase reported medical costs in the current period (unfavorable development). Medical costs in 2022, 2021 and 2020 included favorable medical cost development related to prior years of $410 million, $1.7 billion and $880 million, respectively.
In developing our medical costs payable estimates, we apply different estimation methods depending on the month for which incurred claims are being estimated. For example, for the most recent two months, we estimate claim costs incurred by applying observed medical cost trend factors to the average per member per month (PMPM) medical costs incurred in prior months for which more complete claim data is available, supplemented by a review of near-term completion factors.
Completion Factors. A completion factor is an actuarial estimate, based upon historical experience and analysis of current trends, of the percentage of incurred claims during a given period adjudicated by us at the date of estimation. Completion factors are the most significant factors we use in developing our medical costs payable estimates for periods prior to the most recent two months. Completion factors include judgments in relation to claim submissions such as the time from date of service to claim receipt, claim levels and processing cycles, as well as other factors. If actual claims submission rates from providers (which can be influenced by a number of factors, including provider mix and electronic versus manual submissions), actual care activity incurred (which can be influenced by pandemics or seasonal illnesses, such as influenza), or our claim processing patterns are different than estimated, our reserve estimates may be significantly impacted.
The following table illustrates the sensitivity of these factors and the estimated potential impact on our medical costs payable estimates for those periods as of December 31, 2022:
| Completion Factors (Decrease) Increase in Factors | Increase (Decrease) In Medical Costs Payable | |||||||
| (in millions) | ||||||||
| (0.75)% | $ | 765 | ||||||
| (0.50) | 508 | |||||||
| (0.25) | 254 | |||||||
| 0.25 | (252) | |||||||
| 0.50 | (503) | |||||||
| 0.75 | (753) |
Medical Cost Per Member Per Month Trend Factors. Medical cost PMPM trend factors are significant factors we use in developing our medical costs payable estimates for the most recent two months. Medical cost trend factors are developed through a comprehensive analysis of claims incurred in prior months, provider contracting and expected unit costs, benefit design and a review of a broad set of health care utilization indicators. These factors include but are not limited to pharmacy utilization trends, inpatient hospital authorization data and seasonal and other incidence data from the National Centers for Disease Control. We also consider macroeconomic variables such as GDP growth, employment and disposable income. A large number of factors can cause the medical cost trend to vary from our estimates, including: our ability and practices to manage medical and pharmaceutical costs, changes in level and mix of services utilized; mix of benefits offered, including the impact of co-pays and deductibles; changes in medical practices; and catastrophes, epidemics and pandemics.
The following table illustrates the sensitivity of these factors and the estimated potential impact on our medical costs payable estimates for the most recent two months as of December 31, 2022:
| Medical Cost PMPM Quarterly Trend Increase (Decrease) in Factors | Increase (Decrease) In Medical Costs Payable | |||||||
| (in millions) | ||||||||
| 3% | $ | 985 | ||||||
| 2 | 656 | |||||||
| 1 | 328 | |||||||
| (1) | (328) | |||||||
| (2) | (656) | |||||||
| (3) | (985) |
The completion factors and medical costs PMPM trend factors analyses above include outcomes considered reasonably likely based on our historical experience estimating liabilities for incurred but not reported benefit claims.
Management believes the amount of medical costs payable is reasonable and adequate to cover our liability for unpaid claims as of December 31, 2022; however, actual claim payments may differ from established estimates as discussed above. Assuming a hypothetical 1% difference between our December 31, 2022 estimates of medical costs payable and actual medical costs payable, excluding AARP Medicare Supplement Insurance and any potential offsetting impact from premium rebates, 2022 net earnings would have increased or decreased by approximately $215 million.
For more detail related to our medical cost estimates, see Note 2 of the Notes to the Consolidated Financial Statements included in Part II, Item 8, “Financial Statements and Supplementary Data.”
Goodwill
We evaluate goodwill for impairment annually or more frequently when an event occurs or circumstances change indicating the carrying value may not be recoverable. When testing goodwill for impairment, we may first assess qualitative factors to determine if it is more likely than not the carrying value of a reporting unit exceeds its estimated fair value. During a qualitative analysis, we consider the impact of changes, if any, to the following factors: macroeconomic, industry and market factors; cost factors; changes in overall financial performance; and any other relevant events and uncertainties impacting a reporting unit. If our qualitative assessment indicates a goodwill impairment is more likely than not, we perform additional quantitative analyses. We may also elect to skip the qualitative testing and proceed directly to the quantitative testing. For reporting units where a quantitative analysis is performed, we perform a test measuring the fair values of the reporting units and comparing them to their carrying values, including goodwill. If the fair value is less than the carrying value of the reporting unit, an impairment is recognized for the difference, up to the carrying amount of goodwill.
We estimate the fair values of our reporting units using a discounted cash flow method which includes assumptions about a wide variety of internal and external factors. Significant assumptions used in the discounted cash flow method include financial projections of free cash flow, including revenue trends, medical costs trends, operating productivity, income taxes and capital levels; long-term growth rates for determining terminal value beyond the discretely forecasted periods; and discount rates. For each reporting unit, comparative market multiples are used to corroborate the results of our discounted cash flow test.
Financial projections and long-term growth rates used for our reporting units are consistent with, and use inputs from, our internal long-term business plan and strategies. Discount rates are determined for each reporting unit and include consideration of the implied risk inherent in their forecasts. Our most significant estimate in the discount rate determinations involves our adjustments to the peer company weighted average costs of capital reflecting reporting unit-specific factors. We have not made any adjustments to decrease a discount rate below the calculated peer company weighted average cost of capital for any reporting unit. Company-specific adjustments to discount rates are subjective and thus are difficult to measure with certainty. The passage of time and the availability of additional information regarding areas of uncertainty with respect to the reporting units’ operations could cause these assumptions to change in the future. Additionally, as part of our quantitative impairment testing, we perform various sensitivity analyses on certain key assumptions, such as discount rates and cash flow projections to analyze the potential for a material impact. As of October 1, 2022, we completed our annual impairment tests for goodwill with all of our reporting units having fair values substantially in excess of their carrying values.
LEGAL MATTERS
A description of our legal proceedings is presented in Note 12 of Notes to the Consolidated Financial Statements included in Part II, Item 8, “Financial Statements and Supplementary Data.”
CONCENTRATIONS OF CREDIT RISK
Investments in financial instruments such as marketable securities and accounts receivable may subject us to concentrations of credit risk. Our investments in marketable securities are managed under an investment policy authorized by our Board of Directors. This policy limits the amounts which may be invested in any one issuer and generally limits our investments to U.S. government and agency securities, state and municipal securities and corporate debt obligations of investment grade. Concentrations of credit risk with respect to accounts receivable are limited due to the large number of employer groups and other customers constituting our client base. As of December 31, 2022, there were no significant concentrations of credit risk.
Item 7A. QUANTITATIVE AND QUALITATIVE DISCLOSURES ABOUT MARKET RISK
Our primary market risks are exposures to changes in interest rates impacting our investment income and interest expense and the fair value of certain of our fixed-rate investments and debt, as well as foreign currency exchange rate risk of the U.S. dollar primarily to the Brazilian real and Chilean peso.
As of December 31, 2022, we had $31 billion of financial assets on which the interest rates received vary with market interest rates, which may significantly impact our investment income. Also as of December 31, 2022, $16 billion of our financial liabilities, which include debt and deposit liabilities, were at interest rates which vary with market rates, either directly or through the use of related interest rate swap contracts.
The fair value of our fixed-rate investments and debt also varies with market interest rates. As of December 31, 2022, $38 billion of our investments were fixed-rate debt securities and $43 billion of our debt was non-swapped fixed-rate term debt. An increase in market interest rates decreases the market value of fixed-rate investments and fixed-rate debt. Conversely, a decrease in market interest rates increases the market value of fixed-rate investments and fixed-rate debt.
We manage exposure to market interest rates by diversifying investments across different fixed-income market sectors and debt across maturities, as well as by matching a portion of our floating-rate assets and liabilities, either directly or through the use of interest rate swap contracts. Unrealized gains and losses on investments in available-for-sale debt securities are reported in comprehensive income.
The following tables summarize the impact of hypothetical changes in market interest rates across the entire yield curve by 1% point or 2% points as of December 31, 2022 and 2021 on our investment income and interest expense per annum and the fair value of our investments and debt (in millions, except percentages):
| December 31, 2022 | ||||||||||||||||||||||||||
| Increase (Decrease) in Market Interest Rate | Investment Income Per Annum | Interest Expense Per Annum | Fair Value of Financial Assets | Fair Value of Financial Liabilities | ||||||||||||||||||||||
| 2 % | $ | 629 | $ | 327 | $ | (3,390) | $ | (7,365) | ||||||||||||||||||
| 1 | 314 | 164 | (1,746) | (4,002) | ||||||||||||||||||||||
| (1) | (314) | (135) | 1,838 | 4,808 | ||||||||||||||||||||||
| (2) | (629) | (266) | 3,746 | 10,641 | ||||||||||||||||||||||
| December 31, 2021 | ||||||||||||||||||||||||||
| Increase (Decrease) in Market Interest Rate | Investment Income Per Annum | Interest Expense Per Annum | Fair Value of Financial Assets | Fair Value of Financial Liabilities | ||||||||||||||||||||||
| 2% | $ | 499 | $ | 133 | $ | (3,080) | $ | (8,664) | ||||||||||||||||||
| 1 | 250 | 67 | (1,564) | (4,723) | ||||||||||||||||||||||
| (1) | (85) | (7) | 1,398 | 5,655 | ||||||||||||||||||||||
| (2) | (85) | (7) | 1,857 | 10,892 |
Note: The impact of hypothetical changes in interest rates may not reflect the full 100 or 200 basis point change on interest income and interest expense or on the fair value of financial assets and liabilities as the rates are assumed to not fall below zero.
We have an exposure to changes in the value of foreign currencies, primarily the Brazilian real and the Chilean peso, to the U.S. dollar in translation of UnitedHealthcare Employer & Individual’s international business operating results at the average exchange rate over the accounting period, and assets and liabilities at the exchange rate at the end of the accounting period. The gains or losses resulting from translating foreign assets and liabilities into U.S. dollars are included in equity and comprehensive income.
An appreciation of the U.S. dollar against the Brazilian real or Chilean peso reduces the carrying value of the net assets denominated in those currencies. For example, as of December 31, 2022, a hypothetical 10% and 25% increase in the value of the U.S. dollar against those currencies would have caused a reduction in net assets of approximately $560 million and $1.2 billion, respectively. We manage exposure to foreign currency earnings risk primarily by conducting our international business operations in their functional currencies.
As of December 31, 2022, we had $3.7 billion of investments in equity securities, primarily consisting of investments in employee savings plan related investments, other venture investments and non-U.S. dollar fixed-income funds. Valuations in non-U.S. dollar funds are subject to foreign exchange rates.
Item 8. FINANCIAL STATEMENTS AND SUPPLEMENTARY DATA
REPORT OF INDEPENDENT REGISTERED PUBLIC ACCOUNTING FIRM
To the shareholders and the Board of Directors of UnitedHealth Group Incorporated and Subsidiaries:
Opinion on the Financial Statements
We have audited the accompanying consolidated balance sheets of UnitedHealth Group Incorporated and Subsidiaries (the “Company”) as of December 31, 2022 and 2021, the related consolidated statements of operations, comprehensive income, changes in equity and cash flows for each of the three years in the period ended December 31, 2022, and the related notes (collectively referred to as the “financial statements”). In our opinion, the financial statements referred to above present fairly, in all material respects, the financial position of the Company as of December 31, 2022 and 2021, and the results of its operations and its cash flows for each of the three years in the period ended December 31, 2022, in conformity with accounting principles generally accepted in the United States of America.
We have also audited, in accordance with the standards of the Public Company Accounting Oversight Board (United States) (PCAOB), the Company’s internal control over financial reporting as of December 31, 2022, based on criteria established in Internal Control — Integrated Framework (2013) issued by the Committee of Sponsoring Organizations of the Treadway Commission and our report dated February 24, 2023 expressed an unqualified opinion on the Company’s internal control over financial reporting.
Basis for Opinion
These financial statements are the responsibility of the Company’s management. Our responsibility is to express an opinion on the Company’s financial statements based on our audits. We are a public accounting firm registered with the PCAOB and are required to be independent with respect to the Company in accordance with the U.S. federal securities laws and applicable rules and regulations of the Securities and Exchange Commission and the PCAOB.
We conducted our audits in accordance with the standards of the PCAOB. Those standards require that we plan and perform the audits to obtain reasonable assurance about whether the financial statements are free of material misstatement, whether due to error or fraud. Our audits included performing procedures to assess the risks of material misstatement of the financial statements, whether due to error or fraud, and performing procedures that respond to those risks. Such procedures included examining, on a test basis, evidence regarding the amounts and disclosures in the financial statements. Our audits also included evaluating the accounting principles used and significant estimates made by management, as well as evaluating the overall presentation of the financial statements. We believe that our audits provide a reasonable basis for our opinion.
Critical Audit Matter
The critical audit matter communicated below is a matter arising from the current-period audit of the financial statements that was communicated or required to be communicated to the Audit and Finance Committee and that (1) relates to accounts or disclosures that are material to the financial statements and (2) involved our especially challenging, subjective, or complex judgments. The communication of critical audit matters does not alter in any way our opinion on the financial statements, taken as a whole, and we are not, by communicating the critical audit matter below, providing a separate opinion on the critical audit matter or on the accounts or disclosures to which it relates.
Incurred but not Reported (IBNR) Claim Liability - Refer to Notes 2 and 7 to the financial statements.
Critical Audit Matter Description
Medical costs payable includes estimates of the Company’s obligations for medical care services rendered on behalf of insured consumers, for which claims have either not yet been received or processed. These estimates are referred to as incurred but not reported (IBNR) claim liabilities. At December 31, 2022, the Company’s IBNR balance was $20 billion. The Company develops IBNR estimates using an actuarial model that requires management to exercise certain judgments in developing its estimates. Judgments made by management include medical cost per member per month trend factors and completion factors, which include assumptions over the time from date of service to claim receipt, the impact of actual care activity, and processing cycles.
We identified the IBNR claim liability as a critical audit matter because of the significant assumptions made by management in estimating the liability. This required complex auditor judgment, and an increased extent of effort, including the involvement of actuarial specialists in performing procedures to evaluate the reasonableness of management’s methods, assumptions and judgments in d
Showing the first 8K of 150K characters. Open the full section
Item 9. CHANGES IN AND DISAGREEMENTS WITH ACCOUNTANTS ON ACCOUNTING AND FINANCIAL DISCLOSURE
None.
Item 9A. CONTROLS AND PROCEDURES
EVALUATION OF DISCLOSURE CONTROLS AND PROCEDURES
We maintain disclosure controls and procedures as defined in Rules 13a-15(e) and 15d-15(e) under the Securities Exchange Act of 1934 (Exchange Act) designed to provide reasonable assurance the information required to be disclosed by us in reports we file or submit under the Exchange Act is (i) recorded, processed, summarized and reported within the time periods specified in SEC rules and forms; and (ii) accumulated and communicated to our management, including our principal executive officer and principal financial officer, as appropriate to allow timely decisions regarding required disclosure.
In connection with the filing of this Annual Report on Form 10-K, management evaluated, under the supervision and with the participation of our Chief Executive Officer and Chief Financial Officer, the effectiveness of the design and operation of our disclosure controls and procedures as of December 31, 2022. Based upon their evaluation, our Chief Executive Officer and Chief Financial Officer concluded our disclosure controls and procedures were effective at the reasonable assurance level as of December 31, 2022.
CHANGES IN INTERNAL CONTROL OVER FINANCIAL REPORTING
There have been no changes in our internal control over financial reporting during the quarter ended December 31, 2022 which have materially affected, or are reasonably likely to materially affect, our internal control over financial reporting.
Report of Management on Internal Control Over Financial Reporting as of December 31, 2022
Management of UnitedHealth Group Incorporated and Subsidiaries (the Company) is responsible for establishing and maintaining adequate internal control over financial reporting as defined in Rules 13a-15(f) and 15d-15(f) under the Securities Exchange Act of 1934. The Company’s internal control system is designed to provide reasonable assurance to our management and board of directors regarding the reliability of financial reporting and the preparation of consolidated financial statements for external purposes in accordance with generally accepted accounting principles. The Company’s internal control over financial reporting includes those policies and procedures that (i) pertain to the maintenance of records that, in reasonable detail, accurately and fairly reflect the transactions and dispositions of the assets of the Company; (ii) provide reasonable assurance that transactions are recorded as necessary to permit preparation of consolidated financial statements in accordance with generally accepted accounting principles, and that receipts and expenditures of the Company are being made only in accordance with authorizations of management and directors of the Company; and (iii) provide reasonable assurance regarding prevention or timely detection of unauthorized acquisition, use or disposition of the Company’s assets that could have a material effect on the consolidated financial statements.
Because of its inherent limitations, internal control over financial reporting may not prevent or detect misstatements. Also, projections of any evaluation of effectiveness to future periods are subject to the risk that controls may become inadequate because of changes in conditions, or that the degree of compliance with the policies or procedures may deteriorate.
Management assessed the effectiveness of the Company’s internal control over financial reporting as of December 31, 2022. In making this assessment, we used the criteria set forth by the Committee of Sponsoring Organizations of the Treadway Commission (COSO) in Internal Control-Integrated Framework (2013). Based on our assessment and the COSO criteria, we believe that, as of December 31, 2022, the Company maintained effective internal control over financial reporting.
The Company’s independent registered public accounting firm has audited the Company’s internal control over financial reporting as of December 31, 2022, as stated in the Report of Independent Registered Public Accounting Firm, appearing under Item 9A.
REPORT OF INDEPENDENT REGISTERED PUBLIC ACCOUNTING FIRM
To the shareholders and the Board of Directors of UnitedHealth Group Incorporated and Subsidiaries:
Opinion on Internal Control over Financial Reporting
We have audited the internal control over financial reporting of UnitedHealth Group Incorporated and subsidiaries (the “Company”) as of December 31, 2022, based on criteria established in Internal Control — Integrated Framework (2013) issued by the Committee of Sponsoring Organizations of the Treadway Commission (COSO). In our opinion, the Company maintained, in all material respects, effective internal control over financial reporting as of December 31, 2022, based on criteria established in Internal Control — Integrated Framework (2013) issued by COSO.
We have also audited, in accordance with the standards of the Public Company Accounting Oversight Board (United States) (PCAOB), the consolidated financial statements as of and for the year ended December 31, 2022, of the Company and our report dated February 24, 2023, expressed an unqualified opinion on those financial statements.
Basis for Opinion
The Company’s management is responsible for maintaining effective internal control over financial reporting and for its assessment of the effectiveness of internal control over financial reporting, included in the accompanying Report of Management on Internal Control Over Financial Reporting as of December 31, 2022. Our responsibility is to express an opinion on the Company’s internal control over financial reporting based on our audit. We are a public accounting firm registered with the PCAOB and are required to be independent with respect to the Company in accordance with the U.S. federal securities laws and the applicable rules and regulations of the Securities and Exchange Commission and the PCAOB.
We conducted our audit in accordance with the standards of the PCAOB. Those standards require that we plan and perform the audit to obtain reasonable assurance about whether effective internal control over financial reporting was maintained in all material respects. Our audit included obtaining an understanding of internal control over financial reporting, assessing the risk that a material weakness exists, testing and evaluating the design and operating effectiveness of internal control based on the assessed risk, and performing such other procedures as we considered necessary in the circumstances. We believe that our audit provides a reasonable basis for our opinion.
Definition and Limitations of Internal Control over Financial Reporting
A company’s internal control over financial reporting is a process designed to provide reasonable assurance regarding the reliability of financial reporting and the preparation of financial statements for external purposes in accordance with generally accepted accounting principles. A company’s internal control over financial reporting includes those policies and procedures that (1) pertain to the maintenance of records that, in reasonable detail, accurately and fairly reflect the transactions and dispositions of the assets of the company; (2) provide reasonable assurance that transactions are recorded as necessary to permit preparation of financial statements in accordance with generally accepted accounting principles, and that receipts and expenditures of the company are being made only in accordance with authorizations of management and directors of the company; and (3) provide reasonable assurance regarding prevention or timely detection of unauthorized acquisition, use, or disposition of the company’s assets that could have a material effect on the financial statements.
Because of its inherent limitations, internal control over financial reporting may not prevent or detect misstatements. Also, projections of any evaluation of effectiveness to future periods are subject to the risk that controls may become inadequate because of changes in conditions, or that the degree of compliance with the policies or procedures may deteriorate.
| /s/ DELOITTE & TOUCHE LLP | ||
| Minneapolis, Minnesota | ||
| February 24, 2023 |
Item 9B. OTHER INFORMATION
None.
Item 9C. DISCLOSURE REGARDING FOREIGN JURISDICTIONS THAT PREVENT INSPECTIONS
Not Applicable.
PART III
Item 10. DIRECTORS, EXECUTIVE OFFICERS AND CORPORATE GOVERNANCE
DIRECTORS OF THE REGISTRANT
The following sets forth certain information regarding our directors as of February 24, 2023, including their name and principal occupation or employment:
| Timothy Flynn | F. William McNabb III | |||||||
| Retired Chair KPMG International | Former Chairman and Chief Executive Officer The Vanguard Group, Inc. | |||||||
| Paul Garcia | Valerie Montgomery Rice, M.D. | |||||||
| Retired Chair and Chief Executive Officer Global Payments Inc. | President and Chief Executive Officer Morehouse School of Medicine | |||||||
| Kristen Gil | John Noseworthy, M.D. | |||||||
| Vice President and Business Finance Officer Alphabet Inc. | Former Chief Executive Officer and President Mayo Clinic | |||||||
| Stephen Hemsley | Andrew Witty | |||||||
| Chair UnitedHealth Group | Chief Executive Officer UnitedHealth Group | |||||||
| Michele Hooper | ||||||||
| Lead Independent Director UnitedHealth Group President and Chief Executive Officer The Directors’ Council |
Pursuant to General Instruction G(3) to Form 10-K and the Instruction to Item 401 of Regulation S-K, information regarding our executive officers is provided in Part I, Item 1 under the caption “Information About our Executive Officers.”
We have adopted a code of ethics applicable to our principal executive officer and other senior financial officers, who include our principal financial officer, principal accounting officer, controller and persons performing similar functions. The code of ethics, entitled Code of Conduct: Our Principles of Ethics and Integrity, is posted on our website at www.unitedhealthgroup.com. For information about how to obtain the Code of Conduct, see Part I, Item 1, “Business.” We intend to satisfy the SEC’s disclosure requirements regarding amendments to, or waivers of, the code of ethics for our senior financial officers by posting such information on our website indicated above.
The remaining information required by Items 401, 405, 406 and 407(c)(3), (d)(4) and (d)(5) of Regulation S-K will be included under the headings “Corporate Governance” and “Proposal 1-Election of Directors” in our definitive proxy statement for our 2023 Annual Meeting of Shareholders, and such required information is incorporated herein by reference.
Item 11. EXECUTIVE COMPENSATION
The information required by Items 402 and 407(e)(4) and (e)(5) of Regulation S-K will be included under the headings “Executive Compensation,” “Director Compensation,” “Corporate Governance - Risk Oversight” and “Compensation Committee Interlocks and Insider Participation” in our definitive proxy statement for our 2023 Annual Meeting of Shareholders, and such required information is incorporated herein by reference.
Item 12. SECURITY OWNERSHIP OF CERTAIN BENEFICIAL OWNERS AND MANAGEMENT AND RELATED STOCKHOLDER MATTERS
Equity Compensation Plan Information
The following table sets forth certain information as of December 31, 2022, concerning shares of common stock authorized for issuance under all of our equity compensation plans:
| Plan category | (a) Number of securities to be issued upon exercise of outstanding options, warrants and rights | (b) Weighted-average exercise price of outstanding options, warrants and rights | (c) Number of securities remaining available for future issuance under equity compensation plans (excluding securities reflected in column (a)) | ||||||||||||||||||||
| (in millions) | (in millions) | ||||||||||||||||||||||
| Equity compensation plans approved by shareholders (1) | 23 | $ | 279 | 77 | (3) | ||||||||||||||||||
| Equity compensation plans not approved by shareholders (2) | — | — | |||||||||||||||||||||
| Total (2) | 23 | $ | 279 | 77 |
(1)Consists of the UnitedHealth Group Incorporated 2020 Stock Incentive Plan, as amended, and the UnitedHealth Group 1993 Employee Stock Purchase Plan, as amended.
(2)Excludes 459,000 shares underlying stock options assumed by us in connection with acquisitions. These options have a weighted-average exercise price of $358 and an average remaining term of approximately 4 years. These options are administered pursuant to the terms of the plans under which the options originally were granted. No future awards will be granted under these acquired plans.
(3)Includes 18 million shares of common stock available for future issuance under the 1993 Employee Stock Purchase Plan as of December 31, 2022, and 59 million shares available under the 2020 Stock Incentive Plan as of December 31, 2022. Shares available under the 2020 Stock Incentive Plan may become the subject of future awards in the form of stock options, stock appreciation rights, restricted stock, restricted stock units, performance awards and other stock-based awards.
The information required by Item 403 of Regulation S-K will be included under the heading “Security Ownership of Certain Beneficial Owners and Management” in our definitive proxy statement for our 2023 Annual Meeting of Shareholders, and such required information is incorporated herein by reference.
Item 13. CERTAIN RELATIONSHIPS AND RELATED TRANSACTIONS, AND DIRECTOR INDEPENDENCE
The information required by Items 404 and 407(a) of Regulation S-K will be included under the headings “Certain Relationships and Transactions” and “Corporate Governance” in our definitive proxy statement for our 2023 Annual Meeting of Shareholders, and such required information is incorporated herein by reference.
Item 14. PRINCIPAL ACCOUNTANT FEES AND SERVICES
The information required by Item 9(e) of Schedule 14A will be included under the heading “Disclosure of Fees Paid to Independent Registered Public Accounting Firm” in our definitive proxy statement for our 2023 Annual Meeting of Shareholders, and such required information is incorporated herein by reference.
PART IV
Item 15. EXHIBIT AND FINANCIAL STATEMENT SCHEDULES
(a) 1*. Financial Statements*
The financial statements are included under Item 8 of this report:
-
Consolidated Balance Sheets as of December 31, 2022 and 2021.
-
Consolidated Statements of Operations for the years ended December 31, 2022, 2021, and 2020.
-
Consolidated Statements of Comprehensive Income for the years ended December 31, 2022, 2021, and 2020.
-
Consolidated Statements of Changes in Equity for the years ended December 31, 2022, 2021, and 2020.
-
Consolidated Statements of Cash Flows for the years ended December 31, 2022, 2021, and 2020.
2*. Financial Statement Schedules*
The following financial statement schedule of the Company is included in Item 15(c):
All other schedules for which provision is made in the applicable accounting regulations of the SEC are not required under the related instructions, are inapplicable, or the required information is included in the consolidated financial statements, and therefore have been omitted.
(b) The following exhibits are filed or incorporated by reference herein in response to Item 601 of Regulation S-K. The Company files Annual Reports on Form 10-K, Quarterly Reports on Form 10-Q and Current Reports on Form 8-K pursuant to the Securities Exchange Act of 1934 under Commission File No. 1‑10864.
EXHIBIT INDEX**
| 11.1 | Statement regarding computation of per share earnings (incorporated by reference to the information contained under the heading “Net Earnings Per Common Share” in Note 2 of Notes to the Consolidated Financial Statements included in Part II, Item 8, “Financial Statements and Supplementary Data”) | |||||||
| 21.1 | Subsidiaries of UnitedHealth Group Incorporated | |||||||
| 23.1 | Consent of Independent Registered Public Accounting Firm | |||||||
| 24.1 | Power of Attorney | |||||||
| 31.1 | Certifications pursuant to Section 302 of the Sarbanes-Oxley Act of 2002 | |||||||
| 32.1 | Certifications pursuant to Section 906 of the Sarbanes-Oxley Act of 2002 | |||||||
| 101.INS | XBRL Instance Document - the instance document does not appear in the Interactive Data File because its XBRL tags are embedded within the Inline XBRL document. | |||||||
| 101.SCH | Inline XBRL Taxonomy Extension Schema Document. | |||||||
| 101.CAL | Inline XBRL Taxonomy Extension Calculation Linkbase Document. | |||||||
| 101.DEF | Inline XBRL Taxonomy Extension Definition Linkbase Document. | |||||||
| 101.LAB | Inline XBRL Taxonomy Extension Label Linkbase Document. | |||||||
| 101.PRE | Inline XBRL Taxonomy Extension Presentation Linkbase Document. | |||||||
| 104 | Cover Page Interactive Data File (formatted as Inline XBRL and embedded within Exhibit 101). |
________________________________________________
| * | Denotes management contracts and compensation plans in which certain directors and named executive officers participate and which are being filed pursuant to Item 601(b)(10)(iii)(A) of Regulation S-K. | |||||||
| ** | Pursuant to Item 601(b)(4)(iii) of Regulation S-K, copies of instruments defining the rights of certain holders of long-term debt are not filed. The Company will furnish copies thereof to the SEC upon request. |
(c) Financial Statement Schedule
Schedule I - Condensed Financial Information of Registrant (Parent Company Only).
Schedule I
REPORT OF INDEPENDENT REGISTERED PUBLIC ACCOUNTING FIRM
To the shareholders and the Board of Directors of UnitedHealth Group Incorporated and Subsidiaries:
Opinion on the Financial Statement Schedule
We have audited the consolidated financial statements of UnitedHealth Group Incorporated and Subsidiaries (the “Company”) as of December 31, 2022 and 2021, and for each of the three years in the period ended December 31, 2022, and the Company’s internal control over financial reporting as of December 31, 2022, and have issued our reports thereon dated February 24, 2023; such reports are included elsewhere in this Form 10-K. Our audits also included the financial statement schedule of the Company listed in the Index at Item 15. This financial statement schedule is the responsibility of the Company’s management. Our responsibility is to express an opinion on the Company’s financial statement schedule based on our audits. In our opinion, the financial statement schedule, when considered in relation to the consolidated financial statements taken as a whole, presents fairly, in all material respects, the information set forth therein.
| /s/ DELOITTE & TOUCHE LLP | ||
| Minneapolis, Minnesota | ||
| February 24, 2023 |
Schedule I
Condensed Financial Information of Registrant
(Parent Company Only)
UnitedHealth Group
Condensed Balance Sheets
| (in millions, except per share data) | December 31, 2022 | December 31, 2021 | ||||||||||||
| Assets | ||||||||||||||
| Current assets: | ||||||||||||||
| Cash and cash equivalents | $ | 266 | $ | 2,167 | ||||||||||
| Other current assets | 753 | 503 | ||||||||||||
| Total current assets | 1,019 | 2,670 | ||||||||||||
| Equity in net assets of subsidiaries | 136,562 | 116,907 | ||||||||||||
| Long-term notes receivable from subsidiaries | 6,201 | 5,680 | ||||||||||||
| Other assets | 504 | 32 | ||||||||||||
| Total assets | $ | 144,286 | $ | 125,289 | ||||||||||
| Liabilities and shareholders’ equity | ||||||||||||||
| Current liabilities: | ||||||||||||||
| Accounts payable and accrued liabilities | $ | 835 | $ | 605 | ||||||||||
| Current portion of notes payable to subsidiaries | 8,699 | 8,105 | ||||||||||||
| Short-term borrowings and current maturities of long-term debt | 2,918 | 3,009 | ||||||||||||
| Total current liabilities | 12,452 | 11,719 | ||||||||||||
| Long-term debt, less current maturities | 53,838 | 41,623 | ||||||||||||
| Other liabilities | 224 | 187 | ||||||||||||
| Total liabilities | 66,514 | 53,529 | ||||||||||||
| Commitments and contingencies (Note 4) | ||||||||||||||
| Shareholders’ equity: | ||||||||||||||
| Preferred stock, $0.001 par value -10 shares authorized; no shares issued or outstanding | — | — | ||||||||||||
| Common stock, $0.01 par value - 3,000 shares authorized; 934 and 941 issued and outstanding | 9 | 10 | ||||||||||||
| Retained earnings | 86,156 | 77,134 | ||||||||||||
| Accumulated other comprehensive loss | (8,393) | (5,384) | ||||||||||||
| Total UnitedHealth Group shareholders’ equity | 77,772 | 71,760 | ||||||||||||
| Total liabilities and shareholders’ equity | $ | 144,286 | $ | 125,289 |
See Notes to the Condensed Financial Statements of Registrant
Schedule I
Condensed Financial Information of Registrant
(Parent Company Only)
UnitedHealth Group
Condensed Statements of Comprehensive Income
| For the Years Ended December 31, | ||||||||||||||||||||
| (in millions) | 2022 | 2021 | 2020 | |||||||||||||||||
| Revenues: | ||||||||||||||||||||
| Investment and other income | $ | 255 | $ | 494 | $ | 194 | ||||||||||||||
| Total revenues | 255 | 494 | 194 | |||||||||||||||||
| Operating costs: | ||||||||||||||||||||
| Operating costs | 121 | 40 | 27 | |||||||||||||||||
| Interest expense | 2,110 | 1,583 | 1,594 | |||||||||||||||||
| Total operating costs | 2,231 | 1,623 | 1,621 | |||||||||||||||||
| Loss before income taxes | (1,976) | (1,129) | (1,427) | |||||||||||||||||
| Benefit for income taxes | 429 | 231 | 300 | |||||||||||||||||
| Loss of parent company | (1,547) | (898) | (1,127) | |||||||||||||||||
| Equity in undistributed income of subsidiaries | 21,667 | 18,183 | 16,530 | |||||||||||||||||
| Net earnings | 20,120 | 17,285 | 15,403 | |||||||||||||||||
| Other comprehensive loss | (3,009) | (1,570) | (236) | |||||||||||||||||
| Comprehensive income | $ | 17,111 | $ | 15,715 | $ | 15,167 |
See Notes to the Condensed Financial Statements of Registrant
Schedule I
Condensed Financial Information of Registrant
(Parent Company Only)
UnitedHealth Group
Condensed Statements of Cash Flows
| For the Years Ended December 31, | ||||||||||||||||||||
| (in millions) | 2022 | 2021 | 2020 | |||||||||||||||||
| Operating activities | ||||||||||||||||||||
| Cash flows from operating activities | $ | 14,754 | $ | 11,439 | $ | 8,842 | ||||||||||||||
| Investing activities | ||||||||||||||||||||
| Issuances of notes to subsidiaries | (567) | (444) | (628) | |||||||||||||||||
| Repayments of notes to subsidiaries | 281 | 37 | 1,089 | |||||||||||||||||
| Cash paid for acquisitions | (20,728) | (4,953) | (7,706) | |||||||||||||||||
| Return of capital to parent company | 1,424 | 245 | 943 | |||||||||||||||||
| Capital contributions to subsidiaries | (570) | (747) | (43) | |||||||||||||||||
| Cash received from dispositions | 2,787 | — | 143 | |||||||||||||||||
| Cash flows used for investing activities | (17,373) | (5,862) | (6,202) | |||||||||||||||||
| Financing activities | ||||||||||||||||||||
| Common stock repurchases | (7,000) | (5,000) | (4,250) | |||||||||||||||||
| Proceeds from common stock issuances | 1,253 | 1,355 | 1,440 | |||||||||||||||||
| Cash dividends paid | (5,991) | (5,280) | (4,584) | |||||||||||||||||
| Proceed from (repayments of) short-term borrowings, net | 732 | (1,302) | 872 | |||||||||||||||||
| Proceeds from issuance of long-term debt | 14,819 | 6,933 | 4,864 | |||||||||||||||||
| Repayments of long-term debt | (3,015) | (3,150) | (3,150) | |||||||||||||||||
| Proceeds from notes from subsidiaries | 594 | 3,223 | 2,818 | |||||||||||||||||
| Other, net | (674) | (447) | (438) | |||||||||||||||||
| Cash flows from (used for) financing activities | 718 | (3,668) | (2,428) | |||||||||||||||||
| (Decrease) increase in cash and cash equivalents | (1,901) | 1,909 | 212 | |||||||||||||||||
| Cash and cash equivalents, beginning of period | 2,167 | 258 | 46 | |||||||||||||||||
| Cash and cash equivalents, end of period | $ | 266 | $ | 2,167 | $ | 258 | ||||||||||||||
| Supplemental cash flow disclosures | ||||||||||||||||||||
| Cash paid for interest | $ | 1,969 | $ | 1,575 | $ | 1,633 | ||||||||||||||
| Cash paid for income taxes | 4,298 | 3,050 | 4,185 |
See Notes to the Condensed Financial Statements of Registrant
Schedule I
Condensed Financial Information of Registrant
(Parent Company Only)
UnitedHealth Group
Notes to Condensed Financial Statements
1. Basis of Presentation
UnitedHealth Group’s parent company financial information has been derived from its consolidated financial statements and should be read in conjunction with the consolidated financial statements included in this Form 10-K. The accounting policies for the registrant are the same as those described in Note 2 of the Notes to the Consolidated Financial Statements included in Part II, Item 8, “Financial Statements and Supplementary Data.”
2. Subsidiary Transactions
Investment in Subsidiaries. UnitedHealth Group’s investment in subsidiaries is stated at cost plus equity in undistributed earnings of subsidiaries.
Dividends and Capital Distributions. Cash dividends received from subsidiaries and included in Cash Flows from Operating Activities in the Condensed Statements of Cash Flows were $15.6 billion, $10.8 billion and $10.0 billion in 2022, 2021 and 2020, respectively. Additionally, $1.4 billion, $0.2 billion and $0.9 billion in cash were received as a return of capital to the parent company during 2022, 2021 and 2020, respectively.
3. Short-Term Borrowings and Long-Term Debt
Discussion of short-term borrowings and long-term debt can be found in Note 8 of the Notes to the Consolidated Financial Statements included in Part II, Item 8, “Financial Statements and Supplementary Data.” Long-term debt obligations of the parent company do not include other financing obligations at subsidiaries which totaled $0.9 billion and $1.4 billion at December 31, 2022 and 2021.
Maturities of short-term borrowings and long-term debt for the years ending December 31 are as follows:
| (in millions) | ||||||||
| 2023 | $ | 2,925 | ||||||
| 2024 | 3,000 | |||||||
| 2025 | 3,050 | |||||||
| 2026 | 2,500 | |||||||
| 2027 | 2,925 | |||||||
| Thereafter | 43,502 |
UnitedHealth Group’s parent company had notes payable to subsidiaries of $8.7 billion and $8.1 billion as of December 31, 2022 and 2021, respectively, which included on-demand features.
4. Commitments and Contingencies
Certain regulated subsidiaries are guaranteed by UnitedHealth Group’s parent company in the event of insolvency. UnitedHealth Group’s parent company also provides guarantees related to its service level under certain contracts. None of the amounts accrued, paid or charged to income for service level guarantees were material as of December 31, 2022, 2021 or 2020.
For a summary of commitments and contingencies, see Note 12 of the Notes to the Consolidated Financial Statements included in Part II, Item 8, “Financial Statements and Supplementary Data.”
Item 16. FORM 10-K SUMMARY
None.
SIGNATURES
Pursuant to the requirements of Section 13 or 15(d) of the Securities Exchange Act of 1934, the registrant has duly caused this report to be signed on its behalf by the undersigned, thereunto duly authorized.
Dated: February 24, 2023
| UNITEDHEALTH GROUP INCORPORATED | |||||
| By | /s/ ANDREW WITTY | ||||
| Andrew Witty Chief Executive Officer |
Pursuant to the requirements of the Securities Exchange Act of 1934, this report has been signed below by the following persons on behalf of the registrant and in the capacities and on the dates indicated.
| Signature | Title | Date | ||||||||||||
| /s/ ANDREW WITTY | Director and Chief Executive Officer (principal executive officer) | February 24, 2023 | ||||||||||||
| Andrew Witty | ||||||||||||||
| /s/ JOHN REX | Executive Vice President and Chief Financial Officer (principal financial officer) | February 24, 2023 | ||||||||||||
| John Rex | ||||||||||||||
| /s/ THOMAS ROOS | Senior Vice President and Chief Accounting Officer (principal accounting officer) | February 24, 2023 | ||||||||||||
| Thomas Roos | ||||||||||||||
| * | Director | February 24, 2023 | ||||||||||||
| Timothy Flynn | ||||||||||||||
| * | Director | February 24, 2023 | ||||||||||||
| Paul Garcia | ||||||||||||||
| * | Director | February 24, 2023 | ||||||||||||
| Kristen Gil | ||||||||||||||
| * | Director | February 24, 2023 | ||||||||||||
| Stephen Hemsley | ||||||||||||||
| * | Director | February 24, 2023 | ||||||||||||
| Michele Hooper | ||||||||||||||
| * | Director | February 24, 2023 | ||||||||||||
| F. William McNabb III | ||||||||||||||
| * | Director | February 24, 2023 | ||||||||||||
| Valerie Montgomery Rice, M.D. | ||||||||||||||
| * | Director | February 24, 2023 | ||||||||||||
| John Noseworthy, M.D. |
| *By | /s/ KUAI LEONG | ||||
| Kuai Leong As Attorney-in-Fact |