 filings.tools
Item 1. Business
106K characters. Original on sec.gov · Markdown
Item 1. Business
Overview
Biogen is a global biopharmaceutical company focused on discovering, developing, manufacturing and delivering therapies to people living with serious neurological, rare and autoimmune diseases.
Our marketed products include TECFIDERA, AVONEX, PLEGRIDY, TYSABRI, ZINBRYTA and FAMPYRA for multiple sclerosis (MS), FUMADERM for the treatment of severe plaque psoriasis and SPINRAZA for the treatment of spinal muscular atrophy (SMA). We also have certain business and financial rights with respect to RITUXAN for the treatment of non-Hodgkin's lymphoma, chronic lymphocytic leukemia (CLL) and other conditions, GAZYVA indicated for the treatment of CLL and follicular lymphoma and other potential anti-CD20 therapies under a collaboration agreement with Genentech, Inc. (Genentech), a wholly-owned member of the Roche Group (Roche Group).
We support our drug discovery and development efforts through the commitment of significant resources to discovery, research and development programs and business development opportunities, particularly within areas of our scientific, manufacturing and technical capabilities. For nearly two decades we have led in the research and development of new therapies to treat MS, resulting in our leading portfolio of MS treatments. Now our research is focused on additional improvements in the treatment of MS, such as the development of next generation therapies for MS, with a goal to reverse or possibly repair damage caused by the disease. We are also applying our scientific expertise to solve some of the most challenging and complex diseases, including Alzheimer's disease, Parkinson's disease and amyotrophic lateral sclerosis (ALS), and are employing innovative technologies to discover potential treatments for rare and genetic disorders, including new ways of treating diseases through gene therapy.
Our innovative drug development and commercialization activities are complemented by our biosimilar therapies that expand access to medicines and reduce the cost burden for healthcare systems. We are leveraging our manufacturing capabilities and know-how to develop, manufacture and market biosimilars through Samsung Bioepis, our joint venture with Samsung BioLogics Co. Ltd. (Samsung Biologics). Under this agreement, we are currently manufacturing and commercializing two anti-tumor necrosis factor (TNF) biosimilars in certain European Union (E.U.) countries.
Key Developments
During 2016 we had a number of key developments affecting our business.
Corporate Matters
Hemophilia Spin-Off
In May 2016 we announced our intention to spin off our hemophilia business, Bioverativ Inc. (Bioverativ), as an independent, publicly traded company. Bioverativ will focus on the discovery, development and commercialization of therapies for treatment of hemophilia and other blood disorders, including ELOCTATE for the treatment of hemophilia A and ALPROLIX for the treatment of hemophilia B. Bioverativ will also assume all of our rights and obligations under our collaboration agreement with Swedish Orphan Biovitrum AB (Sobi) and our collaboration and license agreement with Sangamo Biosciences Inc. (Sangamo).
On February 1, 2017, we completed the distribution of all the then outstanding shares of common stock of Bioverativ to Biogen stockholders, who received one share of Bioverativ common stock for every two shares of Biogen common stock. As a result of the distribution, Bioverativ is now an independent public company whose shares of common stock are trading under the symbol "BIVV" on the Nasdaq Global Select Market.
The financial results of Bioverativ are included in our consolidated results of operations and financial position in our audited consolidated financial statements for the periods presented in this Form 10-K. The financial results of Bioverativ will be excluded from our consolidated results of operations and financial position commencing February 1, 2017. For additional information regarding the separation of Bioverativ, please read Note 26, Subsequent Events to our consolidated financial statements included in this report.
Management Changes
During 2016 we appointed several new executives, each of whom has significant experience in the biopharmaceutical industry and is a leader in his or her functional area. These include Michel Vounatsos, Chief Executive Officer, Michael D. Ehlers, Executive Vice President, Research and Development and Paul McKenzie, Executive Vice President, Pharmaceutical Operations and Technology. For additional information related to these and our other Executive Officers, please read "Our Executive Officers" included in this report.
Cost Saving Initiatives
In 2016 we initiated cost saving measures intended to realign our organizational structure in anticipation of the changes in roles and workforce resulting from our decision to spin off our hemophilia business, as well as to achieve further targeted cost reductions.
In December 2016 after an evaluation of our manufacturing capacity and needs, we ceased manufacturing at our Cambridge, MA manufacturing facility and subleased our rights to this facility to Brammer Bio MA, LLC (Brammer). In addition to the sublease, Brammer purchased certain leasehold improvements and other assets at this facility and agreed to provide certain manufacturing and other transition and support services to us.
TECFIDERA Settlement and License Agreement
In January 2017 we agreed to enter into a settlement and license agreement with Forward Pharma A/S (Forward Pharma). The settlement and license agreement provides us an irrevocable license to all intellectual property owned by Forward Pharma and results in the termination of the German Infringement Litigation. Under the terms of the settlement and license agreement with Forward Pharma, we agreed to pay Forward Pharma $1.25 billion in cash. During the fourth quarter of 2016 we recognized a pre-tax charge of $454.8 million related to this matter. For more information on the settlement and license agreement please read Note 21, Commitments and Contingencies to our consolidated financial statements included in this report.
Product/Pipeline Developments
| Multiple Sclerosis | |
| TYSABRI (natalizumab) | |
| l | In June 2016 the European Commission (EC) approved a variation to the marketing authorization of TYSABRI, which extended its indication to include relapsing-remitting MS patients with highly active disease activity despite a full and adequate course of treatment with at least one disease modifying therapy. TYSABRI was previously indicated only for patients who had failed to respond to beta-interferon or glatiramer acetate in the E.U. |
| ZINBRYTA (daclizumab) | |
| l | ZINBRYTA was approved for the treatment of relapsing forms of MS in the U.S. in May 2016 and the E.U. in July 2016. |
| Opicinumab (Anti-LINGO-1) | |
| l | In June 2016 we reported top-line results from SYNERGY, our Phase 2 trial evaluating opicinumab in people with relapsing forms of MS. Opicinumab did not meet the primary endpoint or its secondary efficacy endpoint. However, based on these results, there was a subset of patients within the study that we believe have potential to benefit from treatment, and we are therefore planning another Phase 2 clinical trial related to opicinumab. |
| Neurodegeneration | |
| Aducanumab (BIIB037) | |
| l | In June 2016 we announced that aducanumab, our investigational treatment for early Alzheimer’s disease, was accepted into the European Medicines Agency's (EMA's) Priority Medicines (PRIME) program. PRIME aims to bring treatments to patients more quickly by enhancing the EMA's support for the development of investigational medicines for diseases without available treatments or in need of better treatment options. |
| l | In September 2016 aducanumab was granted "Fast Track" designation by the U.S. Food and Drug Administration (FDA). The FDA’s Fast Track program supports the development of new treatments for serious conditions with an unmet medical need such as Alzheimer’s disease. |
| l | In September 2016 we announced that efficacy and safety data from an additional interim analysis from our Phase 1b study of aducanumab in early Alzheimer's disease were consistent with results previously reported from the Phase 1b study. |
| l | In December 2016 we presented new data from the Phase 1b study of aducanumab, which included interim results from the titration cohort of the placebo-controlled period of the Phase 1b study as well as data from the first year of the long-term extension. The results supported the ongoing Phase 3 studies of aducanumab for early Alzheimer’s disease. |
| Rare Diseases | |
| SPINRAZA (nusinersen) | |
| l | In August 2016 we and Ionis Pharmaceuticals, Inc. (Ionis) announced that SPINRAZA met the primary endpoint for the interim analysis of ENDEAR, the Phase 3 trial evaluating SPINRAZA in infantile-onset (consistent with Type 1) SMA. Based on these results, we exercised our option under our collaboration agreement with Ionis to assume development and commercialization of SPINRAZA, and paid Ionis a $75.0 million license fee in connection with our option exercise. |
| l | In September 2016 we completed the rolling submission of a New Drug Application (NDA) to the FDA for the approval of SPINRAZA, and in October 2016 we filed a marketing authorization application (MAA) with the EMA, which had already granted Accelerated Assessment status to SPINRAZA. These applications have been accepted for review by the applicable regulatory authorities. |
| l | In October 2016 we dosed our first patient in our infantile-onset SMA Expanded Access Program to provide patient access to SPINRAZA. |
| l | In November 2016 we and Ionis announced that SPINRAZA met the primary endpoint for the interim analysis of CHERISH, the Phase 3 trial evaluating SPINRAZA in later-onset (consistent with Type 2) SMA. The analysis found that children receiving SPINRAZA experienced a highly statistically significant improvement in motor function compared to those who did not receive treatment. SPINRAZA demonstrated a favorable safety profile in the study. |
| l | In December 2016 SPINRAZA was approved by the FDA for the treatment of SMA in pediatric and adult patients in the U.S. The FDA also issued us a rare pediatric disease priority review voucher with the approval of SPINRAZA, which confers priority review to a subsequent drug application that would not otherwise qualify for priority review. |
| Biosimilars (Samsung Bioepis - Biogen's Joint Venture with Samsung Biologics) | |
| BENEPALI | |
| l | In January 2016 the EC approved Samsung Bioepis' MAA for BENEPALI, an etanercept biosimilar referencing ENBREL, for marketing in the E.U. Under our agreement with Samsung Bioepis, we are manufacturing and commercializing BENEPALI in specified E.U. countries. |
| FLIXABI | |
| l | In May 2016 the EC approved Samsung Bioepis' MAA for FLIXABI, an infliximab biosimilar candidate referencing REMICADE, for marketing in the E.U. Under our agreement with Samsung Bioepis, we are manufacturing and commercializing FLIXABI in specified E.U. countries. |
| Adalimumab (SB5) | |
| l | In July 2016 the EMA accepted Samsung Bioepis' MAA for SB5, an adalimumab biosimilar candidate referencing HUMIRA. |
| Genentech Relationships | |
| GAZYVA (obinutuzumab) | |
| l | In February 2016 the Roche Group announced that the FDA approved GAZYVA plus bendamustine chemotherapy followed by GAZYVA alone as a new treatment for people with follicular lymphoma who did not respond to a RITUXAN-containing regiment, or whose follicular lymphoma returned after such treatment. |
| l | In May 2016 the Roche Group announced positive results from the Phase 3 GALLIUM study, which investigated the efficacy and safety of GAZYVA in combination with chemotherapy followed by maintenance with GAZYVA alone, compared to RITUXAN in combination with chemotherapy followed by maintenance with RITUXAN alone in previously untreated patients with follicular lymphoma. Results from pre-planned interim analysis showed that GAZYVA-based treatment significantly reduced the risk of disease worsening or death compared to RITUXAN-based treatment. |
| l | In July 2016 the Roche Group announced that the Phase 3 GOYA study evaluating GAZYVA plus CHOP chemotherapy in people with previously untreated diffuse large B-cell lymphoma did not meet its primary endpoint of significantly reducing the risk of disease worsening or death compared to RITUXAN plus CHOP chemotherapy. Adverse events with GAZYVA and RITUXAN were consistent with those seen in previous clinical trials when each was combined with various chemotherapies. |
| OCREVUS (ocrelizumab) | |
| l | In June 2016 the Roche Group announced that the EMA validated its MAA of OCREVUS for the treatment of relapsing multiple sclerosis (RMS) and primary progressive multiple sclerosis (PPMS) in the E.U. The FDA has also accepted for review the Roche Group's Biologics License Application (BLA) for OCREVUS for the treatment of RMS and PPMS. |
| RITUXAN (rituximab) | |
| l | In November 2016 Genentech announced the FDA accepted its BLA for a subcutaneous formulation of RITUXAN. |
| Discontinued Programs | |
| l | During 2016 we discontinued development of amiselimod (MT-1303) under our agreement with Mitsubishi Tanabe Pharma Corporation, and IONIS-DMPKRx under one of our collaboration agreements with Ionis. Additionally, we terminated our collaboration agreements with Rodin Therapeutics, Inc. and Ataxion Inc. |
Marketed Products
The following graphs show our revenues by product and revenues from anti-CD20 therapeutic programs and geography as a percentage of revenue for the years ended December 31, 2016, 2015 and 2014.
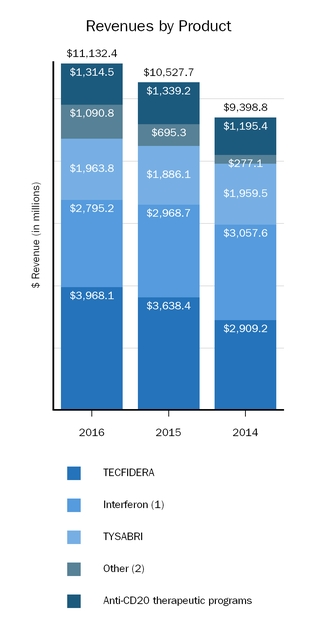
(1) Interferon includes AVONEX and PLEGRIDY
(2) Other includes ZINBRYTA, FAMPYRA, ELOCTATE, ALPROLIX, FUMADERM, SPINRAZA, BENEPALI and FLIXABI

Product sales for TECFIDERA, AVONEX and TYSABRI and anti-CD20 therapeutic programs for RITUXAN each accounted for more than 10% of our total revenue for the years ended December 31, 2016, 2015 and 2014. For additional financial information about our product and other revenues and geographic areas in which we operate, please read Note 24, Segment Information to our consolidated financial statements, Item 6. Selected Financial Data and Item 7. Management's Discussion and Analysis of Financial Condition and Results of Operations included in this report. A discussion of the risks attendant to our operations is set forth in the “Risk Factors” section of this report.
Multiple Sclerosis
We develop, manufacture and market a number of products designed to treat patients with MS. MS is a progressive neurological disease in which the body loses the ability to transmit messages along nerve cells, leading to a loss of muscle control, paralysis and, in some cases, death. Patients with active relapsing MS experience an uneven pattern of disease progression characterized by periods of stability that are interrupted by flare-ups of the disease after which the patient returns to a new baseline of functioning.
Our MS products and major markets include:
| Product | Indication | Collaborator | Major Markets | ||
 | Relapsing forms of MS in the U.S. Relapsing-remitting MS (RRMS) in the E.U. | None | U.S. France Germany Italy Spain United Kingdom | ||
 | Relapsing forms of MS | None | U.S. France Germany Italy Spain United Kingdom | ||
 | Relapsing forms of MS in the U.S. RRMS in the E.U. | None | U.S. France Germany Italy Spain United Kingdom | ||
 | Relapsing forms of MS Crohn's disease in the U.S. | None | U.S. France Germany Italy Spain United Kingdom | ||
 | Relapsing forms of MS | AbbVie Inc. (AbbVie) | U.S. Germany | ||
 | Walking ability for patients with MS | Acorda Therapeutics, Inc. (Acorda) | France Germany Spain |
Spinal Muscular Atrophy
SMA is characterized by loss of motor neurons in the spinal cord and lower brain stem, resulting in severe and progressive muscular atrophy and weakness. Ultimately, individuals with the most severe type of SMA can become paralyzed and have difficulty performing the basic functions of life, like breathing and swallowing. Due to a loss of, or defect in the SMN1 gene, people with SMA do not produce enough survival motor neuron (SMN) protein, which is critical for the maintenance of motor neurons. The severity of SMA correlates with the amount of SMN protein. People with Type 1 SMA, the most severe life-threatening form, produce very little SMN protein and do not achieve the ability to sit without support or live beyond two years without respiratory support. People with Type 2 and Type 3 produce greater amounts of SMN protein and have less severe, but still life-altering, forms of SMA.
In December 2016 the FDA approved SPINRAZA for the treatment of SMA in pediatric and adult patients. We are currently in the early stages of commercial launch in the U.S.
Our products for SMA and major markets include:
| Product | Indication | Collaborator | Major Markets | ||
 | Spinal muscular atrophy | Ionis | U.S. |
Other
| Product | Indication | Collaborator | Major Markets | ||
 | Moderate to severe plaque psoriasis | None | Germany |
Biosimilars
Biosimilars are a group of biologic medicines that are similar to currently available biologic therapies known as originators. Under our agreement with Samsung Bioepis, we manufacture and commercialize two anti-TNF biosimilars in certain countries in the E.U.: BENEPALI, an etanercept biosimilar referencing ENBREL and FLIXABI, an infliximab biosimilar referencing REMICADE:
| Product | Indication | Major Markets | |
 | Moderate to severe rheumatoid arthritis Progressive psoriatic arthritis Axial spondyloarthritis Moderate to severe plaque psoriasis | Denmark Germany Netherlands Norway United Kingdom | |
 | Rheumatoid arthritis Moderate to severe Crohn's disease Severe ulcerative colitis Severe ankylosing spondylitis Psoriatic arthritis Moderate to severe plaque psoriasis | Germany Netherlands United Kingdom |
Genentech Relationships
We have a collaboration agreement with Genentech that entitles us to certain business and financial rights with respect to RITUXAN, GAZYVA and other anti-CD20 product candidates. Current products include:
| Product | Indication | Major Markets | |
 | Non-Hodgkin's lymphoma CLL Rheumatoid arthritis Two forms of ANCA-associated vasculitis | U.S. Canada | |
 | In combination with chlorambucil for previously untreated CLL Follicular lymphoma | U.S. |
For information about our anti-CD20 therapeutic programs and related agreements with Genentech, please read Note 1, Summary of Significant Accounting Policies and Note 19, Collaborative and Other Relationships to our consolidated financial statements included in this report.
Patient Support and Access
We interact with patients, advocacy organizations and healthcare societies in order to gain insights into unmet needs. The insights gained from these engagements help us support patients with services, programs and applications that are designed to help patients lead better lives. Among other things, we provide customer service and other related programs for our products, such as disease and product specific websites, insurance research services, financial assistance programs, and the facilitation of the procurement of our marketed products.
We are dedicated to helping patients obtain access to our therapies. Our patient representatives have access to a comprehensive suite of financial assistance tools. With those tools, we help patients understand their insurance coverage and, if needed, help patients compare and select new insurance options and programs. In the U.S., we have established programs that provide co-pay assistance or free marketed product for qualified uninsured or underinsured patients, based on specific eligibility criteria. We also provide charitable contributions to independent charitable organizations that assist patients with out-of-pocket expenses associated with their therapy.
Marketing and Distribution
Sales Force and Marketing
We promote our products worldwide, including in the U.S., most of the major countries of the E.U. and Japan, primarily through our own sales forces and marketing groups. In some countries, particularly in areas where we continue to expand into new geographic areas, we partner with third parties. We co-promote ZINBRYTA with AbbVie in the U.S., E.U. and Canadian territories.
We focus our sales and marketing efforts on specialist physicians in private practice or at major medical centers. We use customary pharmaceutical company practices to market our products and to educate physicians, such as sales representatives calling on individual physicians, advertisements, professional symposia, direct mail, public relations and other methods.
Distribution Arrangements
We distribute our products in the U.S. principally through wholesale distributors of pharmaceutical products, mail order specialty distributors or shipping service providers. In other countries, the distribution of our products varies from country to country, including through wholesale distributors of pharmaceutical products and third-party distribution partners who are responsible for most marketing and distribution activities.
AbbVie distributes ZINBRYTA in the U.S., and we distribute ZINBRYTA in ex-U.S. markets.
RITUXAN and GAZYVA are marketed and distributed by the Roche Group and its sublicensees.
Our product sales to two wholesale distributors, AmerisourceBergen and McKesson, each accounted for more than 10% of our total revenues for the years ended December 31, 2016, 2015 and 2014, and on a combined basis, accounted for approximately 60% of our gross product revenues for such years, respectively. For additional information, please read Note 1, Summary of Significant Accounting Policies to our consolidated financial statements included in this report.
Patents and Other Proprietary Rights
Patents are important to obtaining and protecting exclusive rights in our products and product candidates. We regularly seek patent protection in the U.S. and in selected countries outside the U.S. for inventions originating from our research and development efforts. In addition, we license rights to various patents and patent applications.
U.S. patents, as well as most foreign patents, are generally effective for 20 years from the date the earliest application was filed; however, U.S. patents that issue on applications filed before June 8, 1995 may be effective until 17 years from the issue date, if that is later than the 20 year date. In some cases, the patent term may be extended to recapture a portion of the term lost during regulatory review of the claimed therapeutic or, in the case of the U.S., because of U.S. Patent and Trademark Office (USPTO) delays in prosecuting the application. Specifically, in the U.S., under the Drug Price Competition and Patent Term Restoration Act of 1984, commonly known as the Hatch-Waxman Act, a patent that covers an FDA-approved drug may be eligible for patent term extension (for up to five years, but not beyond a total of 14 years from the date of product approval) as compensation for patent term lost during the FDA regulatory review process. The duration and extension of the term of foreign patents varies, in accordance with local law. For example, supplementary protection certificates (SPCs) on some of our products have been granted in a number of European countries, compensating in part for delays in obtaining marketing approval.
Regulatory exclusivity, which may consist of regulatory data protection and market protection, also can provide meaningful protection for our products. Regulatory data protection provides to the holder of a drug or biologic marketing authorization, for a set period of time, the exclusive use of the proprietary pre-clinical and clinical data that it created at significant cost and submitted to the applicable regulatory authority to obtain approval of its product. After the applicable set period of time, third parties are then permitted to rely upon our data to file for approval of their abbreviated applications for, and to market (subject to any applicable market protection), their generic drugs and biosimilars referencing our data. Market protection provides to the holder of a drug or biologic marketing authorization the exclusive right to commercialize its product for a set period of
time, thereby preventing the commercialization of another product containing the same active ingredient(s) during that period. Although the World Trade Organization's agreement on trade-related aspects of intellectual property rights (TRIPS) requires signatory countries to provide regulatory exclusivity to innovative pharmaceutical products, implementation and enforcement varies widely from country to country.
We also rely upon other forms of unpatented confidential information to remain competitive. We protect such information principally through confidentiality agreements with our employees, consultants, outside scientific collaborators, scientists whose research we sponsor and other advisers. In the case of our employees, these agreements also provide, in compliance with relevant law, that inventions and other intellectual property conceived by such employees during their employment shall be our exclusive property.
Our trademarks are important to us and are generally covered by trademark applications or registrations in the USPTO and the patent or trademark offices of other countries. We also use trademarks licensed from third parties, such as the trademark FAMPYRA which we license from Acorda. Trademark protection varies in accordance with local law, and continues in some countries as long as the trademark is used and in other countries as long as the trademark is registered. Trademark registrations generally are for fixed but renewable terms.
Our Patent Portfolio
The following table describes our patents in the U.S. and Europe that we currently consider of primary importance to our marketed products, including the territory, patent number, general subject matter and expected expiration dates. Except as otherwise noted, the expected expiration dates include any granted patent term extensions and issued SPCs. In some instances, there are later-expiring patents relating to our products directed to, among other things, particular forms or compositions, methods of manufacturing, or use of the drug in the treatment of particular diseases or conditions. We also continue to pursue additional patents and patent term extensions in the U.S. and other territories covering various aspects of our products that may, if issued, extend exclusivity beyond the expiration of the patents listed in the table.
| Product | Territory | Patent No. | General Subject Matter | Patent Expiration(1) | ||||
| TECFIDERA | U.S. | 7,619,001 | Methods of treatment | 2018 | ||||
| U.S. | 7,803,840 | Methods of treatment | 2018 | |||||
| U.S. | 8,399,514 | Methods of treatment | 2028 | |||||
| U.S. | 8,524,773 | Methods of treatment | 2018 | |||||
| U.S. | 6,509,376 | Formulations of dialkyl fumarates for use in the treatment of autoimmune diseases | 2019 | |||||
| U.S. | 8,759,393 | Formulations | 2019 | |||||
| U.S. | 7,320,999 | Methods of treatment | 2020 | |||||
| Europe | 1131065 | Formulations of dialkyl fumarates and their use for treating autoimmune diseases | 2019(2) | |||||
| Europe | 2137537 | Methods of use | 2028(3) | |||||
| AVONEX and PLEGRIDY | U.S. | 7,588,755 | Use of recombinant beta interferon for immunomodulation | 2026 | ||||
| PLEGRIDY | U.S. | 7,446,173 | Polymer conjugates of interferon beta-1a | 2022 | ||||
| U.S. | 8,524,660 | Methods of treatment | 2023 | |||||
| U.S. | 8,017,733 | Polymer conjugates of interferon beta-1a | 2025 | |||||
| Europe | 1656952 | Polymer conjugates of interferon-beta-1a and uses thereof | 2019 | |||||
| Europe | 1476181 | Polymer conjugates of interferon-beta-1a and uses thereof | 2023 | |||||
| TYSABRI | U.S. | 5,840,299 | Humanized immunoglobulins; nucleic acids; pharmaceutical compositions; methods of use | 2017 | ||||
| U.S. | 6,602,503 | Humanized recombinant antibodies; nucleic acids and host cells; processes for production; therapeutic compositions; methods of use | 2020 | |||||
| U.S. | 7,807,167 | Methods of treatment | 2023 | |||||
| U.S. | 9,493,567 | Methods of treatment | 2027 | |||||
| Europe | 0804237 | Humanized immunoglobulins; nucleic acids; pharmaceutical compositions; medical uses | 2020(4) | |||||
| Europe | 1485127 | Methods of use | 2023 | |||||
| FAMPYRA | Europe | 1732548 | Sustained-release aminopyridine compositions for increasing walking speed in patients with MS | 2025(5) | ||||
| Europe | 23775536 | Sustained-release aminopyridine compositions for treating MS | 2025(6) | |||||
| ZINBRYTA | U.S. | 8,454,965 | Methods of treatment | 2024 | ||||
| U.S. | 7,258,859 | Methods of treatment | 2024 | |||||
| U.S. | 9,340,619 | Daclizumab HYP compositions | 2032 | |||||
| Europe | 1539200 | Anti-IL-2-receptor antibody for use in a method of treating a subject with MS | 2023 | |||||
| SPINRAZA | U.S. | 6,166,197 | Oligomeric Compounds Having Pyrimidine Nucleotide(s) | 2017 | ||||
| U.S. | 6,210,892 | Alteration of Cellular Behavior By Antisense Modulation of MRNA Processing | 2018 | |||||
| U.S. | 7,101,993 | Oligonucleotides Containing 2’-O-Modified Purines | 2023 | |||||
| U.S. | 7,838,657 | SMA Treatment Via Targeting of SMN2 Splice Site Inhibitory Sequences | 2027 | |||||
| U.S. | 8,110,560 | SMA Treatment Via Targeting of SMN2 Splice Site Inhibitory Sequences | 2025 | |||||
| U.S. | 8,361,977 | Compositions And Methods For Modulation of SMN2 Splicing | 2030 | |||||
| U.S. | 8,980,853 | Compositions And Methods For Modulation of SMN2 Splicing | 2030 | |||||
| Europe | 1910395 | Compositions And Methods For Modulation of SMN2 Splicing | 2026 | |||||
| Europe | 2548560 | Compositions And Methods For Modulation of SMN2 Splicing | 2026 |
Footnotes follow on next page.
| (1) | In addition to patent protection, certain of our products are entitled to regulatory exclusivity in the U.S. and the E.U. expected until the dates set forth below: |
| Product | Territory | Expected Expiration | ||
| TECFIDERA | U.S. | 2018 | ||
| E.U. | 2024 | |||
| PLEGRIDY | U.S. | 2026 | ||
| E.U. | 2024 | |||
| TYSABRI | U.S. | 2016 | ||
| E.U. | 2016 | |||
| FAMPYRA | E.U. | 2021 | ||
| ZINBRYTA | U.S. | 2028 | ||
| E.U. | * | |||
| SPINRAZA | U.S. | 2023 |
*ZINBRYTA was not designated a new active substance at the time of its approval in the E.U. and is not automatically entitled to regulatory exclusivity. Regulatory exclusivity may, however, be available for independent development of known active substances. We intend to assert the protection of its data on this basis.
| (2) | This patent is subject to granted SPCs in certain European countries, which extended the patent term in those countries to 2024. |
| (3) | This patent was revoked in a European opposition. This decision is being appealed. The patent is subject to granted SPCs in certain European countries, which extended the patent term in those countries to 2029. |
| (4) | Reflects SPCs granted in most European countries. |
| (5) | This patent is subject to granted SPCs in certain European countries, which extended the patent term in those countries to 2026. |
| (6) | This patent is subject to granted SPCs in certain European countries, which extended the patent term in those countries to 2026. |
The existence of patents does not guarantee our right to practice the patented technology or commercialize the patented product. Patents relating to pharmaceutical, biopharmaceutical and biotechnology products, compounds and processes, such as those that cover our existing compounds, products and processes and those that we will likely file in the future, do not always provide complete or adequate protection. Litigation, interferences, oppositions, inter partes reviews or other proceedings are, have been and may in the future be necessary in some instances to determine the validity and scope of certain of our patents, regulatory exclusivities or other proprietary rights, and in other instances to determine the validity, scope or non-infringement of certain patent rights claimed by third parties to be pertinent to the manufacture, use or sale of our products. We may also face challenges to our patents, regulatory exclusivities and other proprietary rights covering our products by manufacturers of generics and biosimilars. A discussion of certain risks and uncertainties that may affect our patent position, regulatory exclusivities and other proprietary rights is set forth in the “Risk Factors” section of this report, and a discussion of legal proceedings related to certain patents described above is set forth in Note 20, Litigation to our consolidated financial statements included in this report.
Competition
Competition in the biopharmaceutical industry is intense and comes from many sources, including specialized biotechnology firms and large pharmaceutical companies. Many of our competitors are working to develop products similar to those we are developing or already market and have considerable experience in undertaking clinical trials and in obtaining regulatory approval to market pharmaceutical products. Certain of these companies have substantially greater financial, marketing and research and development resources than we do.
We believe that competition and leadership in the industry is based on managerial and technological excellence and innovation as well as establishing patent and other proprietary positions through research and development. The achievement of a leadership position also depends largely upon our ability to maximize the approval, acceptance and use of products resulting from research and the availability of adequate financial resources to fund facilities, equipment, personnel, clinical testing, manufacturing and marketing. Another key aspect of remaining competitive within the industry is recruiting and retaining leading scientists and technicians. We believe that we have been successful in attracting and retaining skilled and experienced scientific personnel.
Competition among products approved for sale may be based, among other things, on patent position, product efficacy, safety, convenience/delivery devices, reliability, availability and price. In addition, early entry of a new pharmaceutical product into the market may have important advantages in gaining product acceptance and market share. Accordingly, the relative speed with which we can develop products, complete the testing and approval process and supply commercial quantities of products will have a significant impact on our competitive position.
The introduction of new products or technologies, including the development of new processes or technologies by competitors or new information about existing products or technologies, may result in increased competition for our marketed products or pricing pressure on our marketed products. It is also possible that the development of new or improved treatment options or standards of care or cures for the diseases our products treat could reduce or eliminate the use of our products or may limit the utility and application of ongoing clinical trials for our product candidates. We may also face increased competitive pressures as a result of generics and the emergence of biosimilars in the U.S. and E.U. If a generic or biosimilar version of one of our products were approved, it could reduce our sales of that product.
Additional information about the competition that our marketed products face is set forth below.
Multiple Sclerosis
TECFIDERA, AVONEX, PLEGRIDY, TYSABRI and ZINBRYTA each compete with one or more of the following products:
| Competing Product | Competitor | |
| AUBAGIO (teriflunomide) | Sanofi | |
| BETASERON/BETAFERON (interferon-beta-1b) | Bayer Group | |
| COPAXONE (glatiramer acetate) | Teva Pharmaceuticals Industries Ltd. | |
| EXTAVIA (interferon-beta-1b) | Novartis AG | |
| GLATOPA (glatiramer acetate) | Sandoz, a division of Novartis AG | |
| GILENYA (fingolimod) | Novartis AG | |
| LEMTRADA (alemtuzumab) | Sanofi | |
| REBIF (interferon-beta-1) | Merck KGaA (and co-promoted with Pfizer Inc. in the U.S.) |
FAMPYRA is indicated as a treatment to improve walking in adult patients with MS who have walking disability and is the first treatment that addresses this unmet medical need with demonstrated efficacy in people with all types of MS. FAMPYRA is currently the only therapy approved to improve walking in patients with MS.
Competition in the MS market is intense. Along with us, a number of companies are working to develop additional treatments for MS that may in the future compete with our MS products. One such product candidate is OCREVUS, a potential treatment for RMS and PPMS being developed by Genentech. While we have a financial interest in OCREVUS, future sales of our MS products may be adversely affected by the commercialization of OCREVUS, as well as by other MS products we or our competitors are developing. Future sales may also be negatively impacted by the introduction of generics, prodrugs of existing therapeutics or biosimilars of existing products.
Spinal Muscular Atrophy
SPINRAZA is the only approved treatment for SMA. We are aware of other products in development that, if successfully developed and approved, may compete with SPINRAZA in the SMA market.
Psoriasis
FUMADERM competes with several different types of therapies in the psoriasis market within Germany, including oral systemics such as methotrexate and cyclosporine.
Biosimilars
BENEPALI and FLIXABI, the two biosimilars we currently manufacture and commercialize in the E.U. for Samsung Bioepis, compete with their applicable reference products, ENBREL and REMICADE, respectively, as well as other biosimilars of those reference products.
Genentech Relationships in Other Indications
RITUXAN and GAZYVA in Oncology
RITUXAN and GAZYVA compete with a number of therapies in the oncology market, including TREANDA (bendamustine HCL), ARZERRA (ofatumumab), IMBRUVICA (ibrutinib) and ZYDELIG (idelalisib).
We also expect that over time GAZYVA will increasingly compete with RITUXAN in the oncology market. In addition, we are aware of other anti-CD20 molecules, including biosimilars, in development that, if successfully developed and approved, may compete with RITUXAN and GAZYVA in the oncology market.
RITUXAN in Rheumatoid Arthritis
RITUXAN competes with several different types of therapies in the rheumatoid arthritis market, including, among others, traditional disease-modifying anti-rheumatic drugs such as steroids, methotrexate and cyclosporine, TNF inhibitors, ORENCIA (abatacept), ACTEMRA (tocilizumab) and XELJANZ (tofacitinib).
We are also aware of other products, including biosimilars, in development that, if successfully developed and approved, may compete with RITUXAN in the rheumatoid arthritis market.
Research and Development Programs
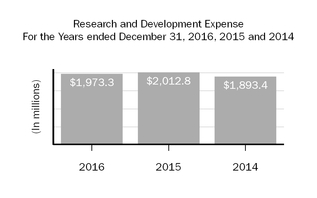
A commitment to research is fundamental to our mission. Our research efforts are focused on better understanding the underlying biology of diseases so we can discover and deliver treatments that have the potential to make a real difference in the lives of patients with high unmet medical needs. By applying our expertise in biologics and our growing capabilities in small molecule, antisense, gene therapy, gene editing and other technologies, we target specific medical needs where we believe new or better treatments are needed.
We intend to continue committing significant resources to research and development opportunities. As part of our ongoing research and development efforts, we have devoted significant resources to conducting clinical studies to advance the development of new pharmaceutical products and technologies and to explore the utility of our existing products in treating disorders beyond those currently approved in their labels.
The table below highlights our current research and development programs that are in clinical trials and the current phase of such programs. Drug development involves a high degree of risk and investment, and the status, timing and scope of our development programs are subject to change. Important factors that could adversely affect our drug development efforts are discussed in the “Risk Factors” section of this report.
| Product Candidate | Collaborator | PHASE 1 | PHASE 2 | PHASE 3 | FILED | ||||||||
| OCREVUS | Genentech (Roche Group) | Primary Progressive & Relapsing Multiple Sclerosis | |||||||||||
| Biosimilar adalimumab | Samsung Bioepis | Multiple Immunology Indications in Europe | |||||||||||
| GAZYVA | Genentech (Roche Group) | Front-Line Indolent Non Hodgkin’s Lymphoma | |||||||||||
| Aducanumab | Neurimmune SubOne AG | Alzheimer's Disease | |||||||||||
| E2609 | Eisai Co., Ltd. (Eisai) | Alzheimer's Disease | |||||||||||
| BIIB074 | None | Trigeminal Neuralgia | |||||||||||
| BIIB074 | None | Lumbosacral Radiculopathy | |||||||||||
| BIIB074 | None | Erythromelalgia | |||||||||||
| BAN2401 | Eisai | Alzheimer's Disease | |||||||||||
| Opicinumab (anti-LINGO-1) | None | Multiple Sclerosis | |||||||||||
| TYSABRI | None | Acute Ischemic Stroke | |||||||||||
| rAAV-XLRS | AGTC | X-linked Juvenile Retinoschisis | |||||||||||
| BG00011 (STX-100) | None | Idiopathic Pulmonary Fibrosis | |||||||||||
| Dapirolizumab pegol | UCB Pharma | Lupus | |||||||||||
| BIIB059 (Anti-BDCA02) | None | Lupus | |||||||||||
| BIIB061 | None | MS | |||||||||||
| BIIB054 | None | PD* | |||||||||||
| BIIB067 (IONIS-SOD1Rx) | Ionis | ALS** | |||||||||||
| BIIB068 (BTK Inhibitor) | None | A*** |
- Parkinson's Disease
** Amyotrophic Lateral Sclerosis
*** Autoimmune
For information about certain of our agreements with collaborators and other third parties, please read the subsection entitled “Business Relationships” below and Note 19, Collaborative and Other Relationships to our consolidated financial statements included in this report.
Late Stage Product Candidates
Additional information about our late stage product candidates, which includes programs in Phase 3 development or in registration stage, is set forth below.
| Neurodegeneration | |
| Aducanumab (BIIB037) | |
| l | In September 2015 we enrolled our first patient in our two global Phase 3 studies, ENGAGE and EMERGE. ENGAGE and EMERGE will assess the efficacy and safety of aducanumab, our investigational treatment for early Alzheimer's disease, in approximately 2,700 people with early Alzheimer's disease. The studies are identical in design and eligibility criteria. Each study will be conducted in more than 20 countries in North America, Europe and Asia. In October 2015 we announced that we received FDA agreement on a special protocol assessment on the Phase 3 study protocols. |
| l | In June 2016 we announced that aducanumab was accepted into the European Medicines Agency's (EMA's) Priority Medicines (PRIME) program. PRIME aims to bring treatments to patients more quickly by enhancing the EMA's support for the development of investigational medicines for diseases without available treatments or in need of better treatment options. |
| l | In September 2016 aducanumab was granted Fast Track designation by the FDA. The FDA’s Fast Track program supports the development of new treatments for serious conditions with an unmet medical need such as Alzheimer’s disease. We also announced that in a recently completed interim analysis from our Phase 1b study of aducanumab in early Alzheimer's disease efficacy and safety data were consistent with results previously reported. |
| l | In December 2016 we presented new data from the Phase 1b study of aducanumab, which included interim results from the titration cohort of the placebo-controlled period of the Phase 1b study as well as data from the first year of the long-term extension. The results supported the ongoing Phase 3 studies of aducanumab for early Alzheimer’s disease. |
| E2609 | |
| l | In October 2016 Eisai announced enrollment has commenced in MISSION AD, a Phase 3 clinical program of the beta secretase cleaving enzyme (BACE) inhibitor E2609 in patients with early Alzheimer's disease in the U.S. |
| Biosimilars (Samsung Bioepis - Biogen's Joint Venture with Samsung Biologics) | |
| Adalimumab (SB5) | |
| l | In July 2016 the EMA accepted Samsung Bioepis' MAA for SB5, an adalimumab biosimilar candidate referencing HUMIRA. If approved by the EC, we will manufacture and commercialize SB5 in specified E.U. countries. |
| Genentech Relationships | |
| GAZYVA (obinutuzumab) | |
| l | The Roche Group is managing GALLIUM, a Phase 3 study examining the efficacy and safety of GAZYVA plus chemotherapy followed by GAZYVA alone for up to two years, as compared head-to-head against RITUXAN plus chemotherapy followed by RITUXAN alone for up to two years. At a pre-planned interim analysis in May 2016, an independent data monitoring committee determined that the study met its primary endpoint early. The results showed GAZYVA-based treatment significantly reduced the risk of disease worsening or death (progression-free survival) compared to RITUXAN-based treatment. |
| OCREVUS (ocrelizumab) | |
| l | In June 2015 the Roche Group announced positive results from two Phase 3 studies evaluating OCREVUS compared with interferon beta-1a in people with relapsing forms of MS. Treatment with OCREVUS compared with interferon beta-1a significantly reduced the annualized relapse rate over a two-year period; significantly reduced the progression of clinical disability; and led to a significant reduction in the number of lesions in the brain as measured by MRI. |
| l | In September 2015 the Roche Group announced positive results from a Phase 3 study evaluating OCREVUS in people with PPMS. Treatment with OCREVUS significantly reduced the progression of clinical disability compared with placebo, as measured by the Expanded Disability Status Scale. |
| l | In June 2016 the Roche Group announced that the EMA validated its MAA of OCREVUS for the treatment of RMS and PPMS in the E.U. The FDA has also accepted for review its BLA for OCREVUS for the treatment of RMS and PPMS, and has granted the application priority review designation. Under our agreement with Genentech, if OCREVUS is approved, we will receive tiered royalty payments on sales of OCREVUS in the U.S. |
Business Relationships
As part of our business strategy, we establish business relationships, including joint ventures and collaborative arrangements with other companies, universities and medical research institutions, to assist in the clinical development and/or commercialization of certain of our products and product candidates and to provide support for our research programs. We also evaluate opportunities for acquiring products or rights to products and technologies that are complementary to our business from other companies, universities and medical research institutions.
Below is a brief description of certain business relationships and collaborations that expand our pipeline and provide us with certain rights to existing and potential new products and technologies. For more information regarding certain of these relationships, including their ongoing financial and accounting impact on our business, please read Note 19, Collaborative and Other Relationships to our consolidated financial statements included in this report.
AbbVie, Inc.
We have a collaboration agreement with AbbVie aimed at advancing the development and commercialization of ZINBRYTA in MS. Under the agreement, we and AbbVie conduct ZINBRYTA co-promotion activities in the U.S., E.U. and Canadian territories, and we are responsible for manufacturing and research and development activities.
Acorda Therapeutics, Inc.
We collaborate with Acorda to develop and commercialize products containing fampridine, such as FAMPYRA, in markets outside the U.S. We also have responsibility for regulatory activities and the future clinical development of related products in those markets.
Applied Genetic Technologies Corporation
We have a collaboration agreement with Applied Genetic Technologies Corporation (AGTC) to develop gene-based therapies for multiple ophthalmic diseases. The collaboration focuses on the development of a clinical-stage candidate for X-linked Retinoschisis (XLRS) and a preclinical candidate for the treatment of X-linked Retinitis Pigmentosa (XLRP), for which we were granted worldwide commercialization rights. The agreement also provides us with options to early stage discovery programs in two ophthalmic diseases and one non-ophthalmic condition.
Eisai Co., Ltd.
We have a collaboration with Eisai to jointly develop and commercialize E2609 and BAN2401, two Eisai product candidates for the treatment of Alzheimer’s disease. Eisai serves as the global operational and regulatory lead for E2609 and BAN2401 and all costs, including research, development, sales and marketing expenses, are shared equally between us and Eisai. Following marketing approval in major markets, we will co-promote E2609 and BAN2401 with Eisai and share profits equally. In smaller markets, Eisai will distribute these products and pay us a royalty.
The agreement also provides Eisai with options to jointly develop and commercialize two of our candidates for Alzheimer’s disease, aducanumab and an anti-tau monoclonal antibody, upon the exchange or provision of clinical data. Upon exercise of the applicable option, we will execute a separate collaboration agreement with Eisai on terms and conditions that mirror the financial arrangements we have with Eisai with respect to E2609 and BAN2401.
Genentech (Roche Group)
We have a collaboration agreement with Genentech which entitles us to certain financial and other rights with respect to RITUXAN, GAZYVA and other anti-CD20 product candidates. Additionally, under our agreement with Genentech, if OCREVUS is approved, we will receive tiered royalty payments on sales of OCREVUS in the U.S.
Ionis Pharmaceuticals, Inc.
We have an exclusive, worldwide option and collaboration agreement with Ionis relating to the development and commercialization of up to three gene targets, and an exclusive worldwide option and collaboration agreement with Ionis under which both companies are developing and commercializing SPINRAZA for the treatment of SMA.
We also have a six-year research collaboration agreement with Ionis, under which both companies perform discovery level research and will develop and commercialize antisense and other therapeutics for the treatment of neurological disorders.
Samsung Bioepis
We and Samsung Biologics established a joint venture, Samsung Bioepis, to develop, manufacture and market biosimilar pharmaceuticals. We also have an agreement with Samsung Bioepis to commercialize, over a 10-year term, three anti-TNF biosimilar product candidates in specified E.U. countries and, in the case of BENEPALI, Japan. Under this agreement, we are manufacturing and commercializing BENEPALI, an etanercept biosimilar referencing ENBREL and FLIXABI, an infliximab biosimilar referencing REMICADE.
In addition to our joint venture and commercialization agreement with Samsung Bioepis, we license certain of our proprietary technology to Samsung Bioepis in connection with Samsung Bioepis' development, manufacture and commercialization of its biosimilar products. We also provide technical development and technology transfer services to Samsung Bioepis, and manufacture clinical and commercial quantities of bulk drug substance of Samsung Bioepis' biosimilar products.
University of Pennsylvania
We have a collaboration and alliance with the University of Pennsylvania to advance gene therapy and gene editing technologies. The collaboration will primarily focus on the development of therapeutic approaches that target the eye, skeletal muscle and the central nervous system. The alliance is also expected to focus on the research and validation of next-generation gene transfer technology using adeno-associated virus gene delivery vectors and exploring the expanded use of genome editing technology as a potential therapeutic platform.
Regulatory
Our current and contemplated activities and the products, technologies and processes that result from such activities are subject to substantial government regulation.
Regulation of Pharmaceuticals
Product Approval and Post-Approval Regulation in the U.S.
APPROVAL PROCESS
Before new pharmaceutical products may be sold in the U.S., preclinical studies and clinical trials of the products must be conducted and the results submitted to the FDA for approval. With limited exceptions, the FDA requires companies to register both pre-approval and post-approval clinical trials and disclose clinical trial results in public databases. Failure to register a trial or disclose study results within the required time periods could result in penalties, including civil monetary penalties. Clinical trial programs must establish efficacy, determine an appropriate dose and dosing regimen, and define the conditions for safe use. This is a high-risk process that requires stepwise clinical studies in which the candidate product must successfully meet predetermined endpoints. The results of the preclinical and clinical testing of a product are then submitted to the FDA in the form of a BLA or a NDA. In response to a BLA or NDA, the FDA may grant marketing approval, request additional information or deny the application if it determines the application does not provide an adequate basis for approval.
Product development and receipt of regulatory approval takes a number of years, involves the expenditure of substantial resources and depends on a number of factors, including the severity of the disease in question, the availability of alternative treatments, potential safety signals observed in preclinical or clinical tests, and the risks and benefits of the product as demonstrated in clinical trials. The FDA has substantial discretion in the product approval process, and it is impossible to predict with any certainty whether and when the FDA will grant marketing approval. The agency may require the sponsor of a BLA or NDA to conduct additional clinical studies or to provide other scientific or technical information about the product, and these additional requirements may lead to unanticipated delay or expense. Furthermore, even if a product is approved, the approval may be subject to limitations based on the FDA's interpretation of the existing pre-clinical or clinical data.
The FDA has developed four distinct approaches intended to make therapeutically important drugs available as rapidly as possible, especially when the drugs are the first available treatment or have advantages over existing treatments: accelerated approval, fast track, breakthrough therapy and priority review.
| • | Accelerated Approval: The FDA may grant “accelerated approval” status to products that treat serious or life-threatening illnesses and that provide meaningful therapeutic benefits to patients over existing treatments. Under this pathway, the FDA may approve a product based on surrogate endpoints, or clinical endpoints other than survival or irreversible morbidity. When approval is based on surrogate endpoints or clinical endpoints other than survival or morbidity, the sponsor will be required to conduct additional post-approval clinical studies to verify and describe clinical benefit. Under the agency's accelerated approval regulations, if the FDA concludes that a drug that has been shown to be effective can be safely used only if distribution or use is restricted, it may require certain post-marketing restrictions as necessary to assure safe use. In addition, for products approved under accelerated approval, sponsors may be required to submit all copies of their promotional materials, including advertisements, to the FDA at least thirty days prior to initial dissemination. The FDA may withdraw approval under accelerated approval after a hearing if, for instance, post-marketing studies fail to verify any clinical benefit, it becomes clear that restrictions on the distribution of the product are inadequate to ensure its safe use, or if a sponsor fails to comply with the conditions of the accelerated approval. |
| • | Fast Track Status: The FDA may grant "fast track" status to products that treat a serious condition and have data demonstrating the potential to address an unmet medical need or a drug that has been designated as a qualified infectious disease product. |
| • | Breakthrough Therapy: The FDA may grant “breakthrough therapy” status to drugs designed to treat, alone or in combination with another drug or drugs, a serious or life-threatening disease or condition and for which preliminary clinical evidence suggests a substantial improvement over existing therapies. Such drugs need not address an unmet need, but are nevertheless eligible for expedited review if they offer the potential for an improvement. Breakthrough therapy status entitles the sponsor to earlier and more frequent meetings with the FDA regarding the development of nonclinical and clinical data and permits the FDA to offer product development or regulatory advice for the purpose of shortening the time to product approval. Breakthrough therapy status does not guarantee that a product will be developed or reviewed more quickly and does not ensure FDA approval. |
| • | Priority Review: Priority Review only applies to applications (original or efficacy supplement) for a drug that treats a serious condition and, if approved, would provide a significant improvement in safety or effectiveness. Priority Review may also be granted for any supplement that proposes a labeling change due to studies completed in response to a written request from FDA for pediatric studies, for an application for a drug that has been designated as a qualified infectious disease product, or any application or supplement for a drug submitted with a priority review voucher. |
POST-MARKETING STUDIES
Regardless of the approval pathway employed, the FDA may require a sponsor to conduct additional post-marketing studies as a condition of approval to provide data on safety and effectiveness. If a sponsor fails to conduct the required studies, the agency may withdraw its approval. In addition, if the FDA concludes that a drug that has been shown to be effective can be safely used only if distribution or use is restricted, it can mandate post-marketing restrictions as necessary to assure safe use. In such a case, the sponsor may be required to establish rigorous systems to assure use of the product under safe conditions. These systems are usually referred to as Risk Evaluation and Mitigation Strategies (REMS). The FDA can impose financial penalties for failing to comply with certain post-marketing commitments, including REMS. In addition, any changes to an approved REMS must be reviewed and approved by the FDA prior to implementation.
ADVERSE EVENT REPORTING
We monitor information on side effects and adverse events reported during clinical studies and after marketing approval and report such information and events to regulatory agencies. Non-compliance with the FDA's safety reporting requirements may result in civil or criminal penalties. Side effects or adverse events that are reported during clinical trials can delay, impede, or prevent marketing approval. Based on new safety information that emerges after approval, the FDA can mandate product labeling changes, impose a new REMS or the addition of elements to an existing REMS, require new post-marketing studies (including additional clinical trials), or suspend or withdraw approval of the product. These requirements may affect our ability to maintain marketing approval of our products or require us to make significant expenditures to obtain or maintain such approvals.
APPROVAL OF CHANGES TO AN APPROVED PRODUCT
If we seek to make certain types of changes to an approved product, such as adding a new indication, making certain manufacturing changes, or changing manufacturers or suppliers of certain ingredients or components, the FDA will need to review and approve such changes in advance. In the case of a new indication, we are required to demonstrate with additional clinical data that the product is safe and effective for a use other than that initially approved. FDA regulatory review may result in denial or modification of the planned changes, or requirements to conduct additional tests or evaluations that can substantially delay or increase the cost of the planned changes.
REGULATION OF PRODUCT ADVERTISING AND PROMOTION
The FDA regulates all advertising and promotion activities and communications for products under its jurisdiction both before and after approval. A company can make only those claims relating to safety and efficacy that are approved by the FDA. However, physicians may prescribe legally available drugs for uses that are not described in the drug's labeling. Such off-label uses are common across medical specialties, and often reflect a physician's belief that the off-label use is the best treatment for patients. The FDA does not regulate the behavior of physicians in their choice of treatments, but FDA regulations do impose stringent restrictions on manufacturers' communications regarding off-label uses. Failure to comply with applicable FDA requirements may subject a company to adverse publicity, enforcement action by the FDA, corrective advertising, and the full range of civil and criminal penalties available to the government.
Regulation of Combination Products
Combination products are defined by the FDA to include products comprising two or more regulated components (e.g., a biologic and a device). Biologics and devices each have their own regulatory requirements, and combination products may have additional requirements. Some of our marketed products meet this definition and are regulated under this framework and similar regulations outside the U.S., and we expect that some of our pipeline product candidates may be evaluated for regulatory approval under this framework as well.
Product Approval and Post-Approval Regulation Outside the U.S.
We market our products in numerous jurisdictions outside the U.S. Most of these jurisdictions have product approval and post-approval regulatory processes that are similar in principle to those in the U.S. In Europe, for example, where a substantial part of our ex-U.S. efforts are focused, there are several tracks for marketing approval, depending on the type of product for which approval is sought. Under the centralized procedure, a company submits a single application to the EMA. The marketing application is similar to the NDA or BLA in the U.S. and is evaluated by the Committee for Medicinal Products for Human Use (CHMP), the expert scientific committee of the EMA. If the CHMP determines that the marketing application fulfills the requirements for quality, safety, and efficacy, it will submit a favorable opinion to the EC. The CHMP opinion is not binding, but is typically adopted by the EC. A marketing application approved by the EC is valid in all member states. The centralized procedure is required for all biological products, orphan medicinal products, and new treatments for neurodegenerative disorders, and it is available for certain other products, including those which constitute a significant therapeutic, scientific or technical innovation.
In addition to the centralized procedure, Europe also has:
| • | a nationalized procedure, which requires a separate application to and approval determination by each country; |
| • | a decentralized procedure, whereby applicants submit identical applications to several countries and receive simultaneous approval; and |
| • | a mutual recognition procedure, where applicants submit an application to one country for review and other countries may accept or reject the initial decision. |
Regardless of the approval process employed, various parties share responsibilities for the monitoring, detection, and evaluation of adverse events post-approval, including national authorities, the EMA, the EC, and the marketing authorization holder. In some regions, it is possible to receive an “accelerated” review whereby the national regulatory authority will commit to truncated review timelines for products that meet specific medical needs.
Good Manufacturing Practices
Regulatory agencies regulate and inspect equipment, facilities and processes used in the manufacturing and testing of pharmaceutical and biologic products prior to approving a product. If, after receiving clearance from regulatory agencies, a company makes a material change in manufacturing equipment, location or process, additional regulatory review and approval may be required. We also must adhere to current Good Manufacturing Practices (cGMP) and product-specific regulations enforced by regulatory agencies following product approval. The FDA, the EMA and other regulatory agencies also conduct periodic visits to re-inspect equipment, facilities and processes following the initial approval of a product. If, as a result of these inspections, it is determined that our equipment, facilities or processes do not comply with applicable regulations and conditions of product approval, regulatory agencies may seek civil, criminal or administrative sanctions or remedies against us, including significant financial penalties and the suspension of our manufacturing operations.
Good Clinical Practices
The FDA, the EMA and other regulatory agencies promulgate regulations and standards for designing, conducting, monitoring, auditing and reporting the results of clinical trials to ensure that the data and results are accurate and that the rights and welfare of trial participants are adequately protected (commonly referred to as current Good Clinical Practices (cGCP)). Regulatory agencies enforce cGCP through periodic inspections of trial sponsors, principal investigators and trial sites, contract research organizations (CROs), and institutional review boards. If our studies fail to comply with applicable cGCP, the clinical data generated in our clinical trials may be deemed unreliable and relevant regulatory agencies may require us to perform additional clinical trials before approving our marketing applications. Noncompliance can also result in civil or criminal sanctions. We rely on third parties, including CROs, to carry out many of our clinical trial-related activities. Failure of such third parties to comply with cGCP can likewise result in rejection of our clinical trial data or other sanctions.
Approval of Biosimilars
The Patient Protection and Affordable Care Act (PPACA) amended the Public Health Service Act (PHSA) to authorize the FDA to approve biological products, referred to as biosimilars or follow-on biologics, that are shown to be highly similar to previously approved biological products based upon potentially abbreviated data packages. The biosimilar must show it has no clinically meaningful differences in terms of safety and effectiveness from the reference product, and only minor differences in clinically inactive components are allowable in biosimilars products. The approval pathway for biosimilars does, however, grant a biologics manufacturer a 12-year period of exclusivity from the date of approval of its biological product before biosimilar competition can be introduced. There is uncertainty, however, as the approval framework for biosimilars originally was enacted as part of the PPACA. In 2017, there are likely to be federal legislative and administrative efforts to repeal, substantially modify or invalidate some or all of the provisions of the PPACA. If the PPACA is repealed, substantially modified or invalidated, it is unclear what, if any, impact such action would have on biosimilar regulation.
Biosimilars legislation has also been in place in the E.U. since 2003. In December 2012 guidelines issued by the EMA for approving biosimilars of marketed monoclonal antibody products became effective. In the E.U., biosimilars have been approved under a specialized pathway of centralized procedures. The pathway allows sponsors of a biosimilar to seek and obtain regulatory approval based in part on the clinical trial data of an innovator product to which the biosimilar has been demonstrated to be “similar”. In many cases, this allows biosimilars to be brought to market without conducting the full complement of clinical trials typically required for novel biologic drugs.
Orphan Drug Act
Under the U.S. Orphan Drug Act, the FDA may grant orphan drug designation to drugs or biologics intended to treat a “rare disease or condition,” which generally is a disease or condition that affects fewer than 200,000 individuals in the U.S. If a product which has an orphan drug designation subsequently receives the first FDA approval for the indication for which it has such designation, the product is entitled to orphan exclusivity, i.e., the FDA may not approve any other applications to market the same drug for the same indication for a period of seven years following marketing approval, except in certain very limited circumstances, such as if the later product is shown to be clinically superior to the orphan product. Legislation similar to the U.S. Orphan Drug Act has been enacted in other countries to encourage the research, development and marketing of medicines to treat, prevent or diagnose rare diseases. In the E.U., medicinal products intended for diagnosis, prevention or treatment of life-threatening or very serious diseases affecting less than five in 10,000 people receive 10-year market exclusivity, protocol assistance and access to the centralized procedure for marketing authorization. SPINRAZA has been granted orphan drug designation in the U.S., E.U. and Japan.
Regulation Pertaining to Pricing and Reimbursement
In both domestic and foreign markets, sales of our products depend, in part, on the availability and amount of reimbursement by third-party payors, including governments, private health plans and other organizations. Substantial uncertainty exists regarding the pricing reimbursement of our products, and drug prices continue to receive significant scrutiny. Governments may regulate coverage, reimbursement and pricing of our products to control cost or affect utilization of our products. Challenges to our pricing strategies, by either government or private stakeholders, could harm our business. The U.S. and foreign governments have enacted and regularly consider additional reform measures that affect health care coverage and costs. Private health plans may also seek to manage cost and utilization by implementing coverage and reimbursement limitations. Other payors, including managed care organizations, health insurers, pharmacy benefit managers, government health administration authorities and private health insurers, seek price discounts or rebates in connection with the placement of our products on their formularies and, in some cases, the imposition of restrictions on access or coverage of particular drugs or pricing determined based on perceived value.
Within the U.S.
| • | Medicaid: Medicaid is a joint federal and state program that is administered by the states for low income and disabled beneficiaries. Under the Medicaid Drug Rebate Program, we are required to pay a rebate for each unit of product reimbursed by the state Medicaid programs. The amount of the rebate is established by law and is adjusted upward if average manufacture price (AMP) increases more than inflation (measured by the Consumer Price Index - Urban). The rebate amount is calculated each quarter based on our report of current AMP and best price for each of our products to the Centers for Medicare & Medicaid Services (CMS). The requirements for calculating AMP and best price are complex. We are required to report any revisions to AMP or best price previously reported within a certain period, which revisions could affect our rebate liability for prior quarters. In addition, if we fail to provide information timely or we are found to have knowingly submitted false information to the government, the statute governing the Medicaid Drug Rebate Program provides for civil monetary penalties. |
| • | Medicare: Medicare is a federal program that is administered by the federal government that covers individuals age 65 and over as well as those with certain disabilities. Medicare Part B generally covers drugs that must be administered by physicians or other health care practitioners; are provided in connection with certain durable medical equipment; or are certain oral anti-cancer drugs and certain oral immunosuppressive drugs. In addition, clotting factors for hemophilia are typically paid under Medicare Part B. Medicare Part B pays for such drugs under a payment methodology based on the average sales price (ASP) of the drugs. Manufacturers, including us, are required to provide ASP information to the CMS on a quarterly basis. The manufacturer-submitted information is used to calculate Medicare payment rates. If a manufacturer is found to have made a misrepresentation in the reporting of ASP, the governing statute provides for civil monetary penalties. |
| • | Medicare Part D provides coverage to enrolled Medicare patients for self-administered drugs (i.e., drugs that are not administered by a physician). Medicare Part D is administered by private prescription drug plans approved by the U.S. government and each drug plan establishes its own Medicare Part D formulary for prescription drug coverage and pricing, which the drug plan may modify from time-to-time. The prescription drug plans negotiate pricing with |
manufacturers and pharmacies, and may condition formulary placement on the availability of manufacturer discounts. In addition, manufacturers, including us, are required to provide to CMS a 50% discount on brand name prescription drugs utilized by Medicare Part D beneficiaries when those beneficiaries reach the coverage gap in their drug benefits.
| • | Federal Agency Discounted Pricing: Our products are subject to discounted pricing when purchased by federal agencies via the Federal Supply Schedule (FSS). FSS participation is required for our products to be covered and reimbursed by the Veterans Administration (VA), Department of Defense, Coast Guard and Public Health Service (PHS). Coverage under Medicaid, Medicare and the PHS pharmaceutical pricing program is also conditioned upon FSS participation. FSS pricing is intended not to exceed the price that we charge our most-favored non-federal customer for a product. In addition, prices for drugs purchased by the VA, Department of Defense (including drugs purchased by military personnel and dependents through the TriCare retail pharmacy program), Coast Guard and PHS are subject to a cap on pricing equal to 76% of the non-federal average manufacturer price (non-FAMP). An additional discount applies if non-FAMP increases more than inflation (measured by the Consumer Price Index - Urban). In addition, if we fail to provide information timely or we are found to have knowingly submitted false information to the government, the governing statute provides for civil monetary penalties. |
| • | 340B Discounted Pricing: To maintain coverage of our products under the Medicaid Drug Rebate Program and Medicare Part B, we are required to extend significant discounts to certain covered entities that purchase products under Section 340B of the PHS pharmaceutical pricing program. Purchasers eligible for discounts include hospitals that serve a disproportionate share of financially needy patients, community health clinics, hemophilia treatment centers and other entities that receive certain types of grants under the PHSA. For all of our products, we must agree to charge a price that will not exceed the amount determined under statute (the “ceiling price”) when we sell outpatient drugs to these covered entities. In addition, we may, but are not required to, offer these covered entities a price lower than the 340B ceiling price. The 340B discount formula is based on AMP and is generally similar to the level of rebates calculated under the Medicaid Drug Rebate Program. |
Outside the U.S.
Outside the U.S., the E.U. represents a major market. Within the E.U., our products are paid for by a variety of payors, with governments being the primary source of payment. Governments may determine or influence reimbursement of products. Governments may also set prices or otherwise regulate pricing. Negotiating prices with governmental authorities can delay commercialization of our products. Governments may use a variety of cost-containment measures to control the cost of products, including price cuts, mandatory rebates, value-based pricing, and reference pricing (i.e., referencing prices in other countries and using those reference prices to set a price). Budgetary pressures in many E.U. countries are continuing to cause governments to consider or implement various cost-containment measures, such as price freezes, increased price cuts and rebates, and expanded generic substitution and patient cost-sharing.
Regulation Pertaining to Sales and Marketing
We are subject to various federal and state laws pertaining to health care “fraud and abuse,” including anti-kickback laws and false claims laws. Anti-kickback laws generally prohibit a prescription drug manufacturer from soliciting, offering, receiving, or paying any remuneration to generate business, including the purchase or prescription of a particular drug. Although the specific provisions of these laws vary, their scope is generally broad and there may be no regulations, guidance or court decisions that clarify how the laws apply to particular industry practices. There is therefore a possibility that our practices might be challenged under the anti-kickback or similar laws. False claims laws prohibit anyone from knowingly and willingly presenting, or causing to be presented for payment to third-party payors (including Medicare and Medicaid) claims for reimbursed drugs or services that are false or fraudulent, claims for items or services not provided as claimed, or claims for medically unnecessary items or services. Our activities relating to the sale and marketing of our products may be subject to scrutiny under these laws. Violations of fraud and abuse laws may be punishable by criminal or civil sanctions, including fines and civil monetary penalties, and exclusion from federal health care programs (including Medicare and Medicaid). In the U.S., federal and state authorities are paying increased attention to enforcement of these laws within the pharmaceutical industry and private individuals have been active in alleging violations of the laws and bringing suits on behalf of the government under the federal civil False Claims Act. If we were subject to allegations concerning, or were convicted of violating, these laws, our business could be harmed.
Laws and regulations have been enacted by the federal government and various states to regulate the sales and marketing practices of pharmaceutical manufacturers. The laws and regulations generally limit financial interactions between manufacturers and health care providers or require disclosure to the government and public of such interactions. The laws include federal “sunshine” provisions. The sunshine provisions apply to pharmaceutical manufacturers with products reimbursed under certain government programs and require those manufacturers to disclose annually to the federal government (for re-disclosure to the public) certain payments made to physicians and certain other healthcare practitioners or to teaching hospitals. State laws may also require disclosure of pharmaceutical pricing information and marketing expenditures. Many of these laws and regulations contain ambiguous requirements. Given the lack of clarity in laws and their implementation, our reporting actions could be subject to the penalty provisions of the pertinent federal and state laws and regulations. Outside the U.S., other countries have implemented requirements for disclosure of financial interactions with healthcare providers and additional countries may consider or implement such laws.
Other Regulations
Foreign Anti-Corruption
We are subject to various federal and foreign laws that govern our international business practices with respect to payments to government officials. Those laws include the U.S. Foreign Corrupt Practices Act (FCPA), which prohibits U.S. companies and their representatives from paying, offering to pay, promising, or authorizing the payment of anything of value to any foreign government official, government staff member, political party, or political candidate for the purpose of obtaining or retaining business or to otherwise obtain favorable treatment or influence a person working in an official capacity. In many countries, the health care professionals we regularly interact with may meet the FCPA's definition of a foreign government official. The FCPA also requires public companies to make and keep books and records that accurately and fairly reflect their transactions and to devise and maintain an adequate system of internal accounting controls.
The laws to which we are subject also include the U.K. Bribery Act 2010 (Bribery Act) which proscribes giving and receiving bribes in the public and private sectors, bribing a foreign public official, and failing to have adequate procedures to prevent employees and other agents from giving bribes. U.S. companies that conduct business in the United Kingdom generally will be subject to the Bribery Act. Penalties under the Bribery Act include potentially unlimited fines for companies and criminal sanctions for corporate officers under certain circumstances.
NIH Guidelines
We seek to conduct research at our U.S. facilities in compliance with the current U.S. National Institutes of Health Guidelines for Research Involving Recombinant DNA Molecules (NIH Guidelines). By local ordinance, we are required to, among other things, comply with the NIH Guidelines in relation to our facilities in RTP, North Carolina and are required to operate pursuant to certain permits.
Other Laws
Our present and future business has been and will continue to be subject to various other laws and regulations. Various laws, regulations and recommendations relating to data privacy and protection, safe working conditions, laboratory practices, the experimental use of animals, and the purchase, storage, movement, import, export and use and disposal of hazardous or potentially hazardous substances, including radioactive compounds and infectious disease agents, used in connection with our research work are or may be applicable to our activities. Certain agreements entered into by us involving exclusive license rights may be subject to national or international antitrust regulatory control, the effect of which cannot be predicted. The extent of government regulation, which might result from future legislation or administrative action, cannot accurately be predicted.
Environmental Matters
We strive to comply in all material respects with applicable laws and regulations concerning the environment. While it is impossible to predict accurately the future costs associated with environmental compliance and potential remediation activities, compliance with environmental laws is not expected to require significant capital expenditures and has not had, and is not expected to have, a material adverse effect on our operations or competitive position.
Manufacturing
We are committed to ensuring an uninterrupted supply of medicines to patients around the world. To that end, we continually review our manufacturing capacity, capabilities, processes and facilities. We believe that our manufacturing facilities, together with the third-party contract manufacturing organizations we outsource to, currently provide sufficient capacity for our products and the contract manufacturing services we provide to Samsung Bioepis, our joint venture that develops, manufactures and markets biosimilars, and other strategic contract manufacturing partners. In light of the development of our pipeline, we are expanding our production capacity by building a large-scale biologics manufacturing facility in Solothurn, Switzerland, which is expected to be operational by the end of the decade.
Manufacturing Facilities
Our drug substance manufacturing facilities include:
| Facility | Drug Substance Manufactured | |
| RTP, North Carolina | ALPROLIX AVONEX ELOCTATE PLEGRIDY TYSABRI ZINBRYTA Other* | |
| Hillerød, Denmark | TYSABRI Biosimilars |
- Other includes products manufactured for contract manufacturing partners
In addition to our drug substance manufacturing facilities, we have a drug product manufacturing facility and supporting infrastructure in RTP, North Carolina. This parenteral facility adds capabilities and capacity for filling biologics into vials.
We also lease from Eisai an oral solid dose products manufacturing facility in RTP, North Carolina, where we manufacture TECFIDERA and other oral solid dose products, including products for Eisai. This facility supplements our outsourced small molecule manufacturing capabilities. Under our lease arrangement, Eisai may provide us with packaging services for oral solid dose products. In August 2015 we agreed to purchase this facility following the expiration of our current three-year lease in the third quarter of 2018 and Eisai's completion of certain activities.
For a period of time following the spin-off of Bioverativ, we agreed to manufacture and supply, exclusively for Bioverativ, drug substance, drug product and finished goods with respect to ELOCTATE and ALPROLIX and pipeline product candidates.
Genentech is responsible for all worldwide manufacturing activities for bulk RITUXAN and GAZYVA and has sourced the manufacture of certain bulk RITUXAN and GAZYVA requirements to a third party, Acorda Therapeutics supplies FAMPYRA to us pursuant to its supply agreement with Alkermes, Inc. and Ionis supplies the active pharmaceutical ingredient (API) for SPINRAZA.
Third-Party Suppliers and Manufacturers
We principally use third parties to manufacture the API, except as noted above for SPINRAZA, and, to a lesser extent, the final product for our small molecule products and product candidates, including TECFIDERA and FUMADERM and the final drug product for our large molecule products and product candidates, including SPINRAZA.
We source all of our fill-finish and the majority of final product assembly and storage operations for our products, along with a substantial part of our packaging operations, to a concentrated group of third-party contract manufacturing organizations. We have internal label and packaging capability for clinical and commercial products at our Hillerød facility. Raw materials, delivery devices, such as syringes and auto-injectors, and other supplies required for the production of our products and product candidates are procured from various third-party suppliers and manufacturers in quantities adequate to meet our needs. Continuity of supply of such raw materials, devices and supplies is assured using a strategy of dual sourcing where possible or by a risk-based inventory strategy. Our third-party service providers, suppliers and manufacturers may be subject to routine cGMP inspections by the FDA or comparable agencies in other jurisdictions and undergo assessment and certification by our quality management group.
Our Employees
As of December 31, 2016, we had approximately 7,400 employees worldwide.
Our Executive Officers (as of February 2, 2017)
| Officer | Current Position | Age | Year Joined Biogen | |||
| Michel Vounatsos | Chief Executive Officer | 55 | 2016 | |||
| Susan H. Alexander | Executive Vice President, Chief Legal Officer and Corporate Secretary | 60 | 2006 | |||
| Paul J. Clancy | Executive Vice President, Finance and Chief Financial Officer | 55 | 2001 | |||
| Gregory F. Covino | Vice President, Finance and Chief Accounting Officer | 51 | 2012 | |||
| Michael D. Ehlers | Executive Vice President, Research and Development | 48 | 2016 | |||
| Paul McKenzie | Executive Vice President, Pharmaceutical Operations and Technology | 51 | 2016 | |||
| Kenneth DiPietro | Executive Vice President, Human Resources | 58 | 2012 | |||
| Adriana (Andi) Karaboutis | Executive Vice President, Technology, Business Solutions and Corporate Affairs | 54 | 2014 | |||
| Alfred W. Sandrock, Jr., M.D., Ph.D. | Chief Medical Officer and Executive Vice President of Neurology Discovery and Development | 59 | 1998 |
| Michel Vounatsos | |
| Experience | |
| Mr. Vounatsos has served as our Chief Executive Officer since January 2017. Prior to that, from April 2016 to December 2016, Mr. Vounatsos served as our Executive Vice President and Chief Commercial Officer. Prior to joining Biogen, Mr. Vounatsos spent 20 years at Merck where he most recently served as President, Primary Care, Customer Business Line. In this role, he led Merck’s global primary care business unit, a role which encompassed Merck’s cardiology-metabolic, general medicine, women’s health and biosimilars groups and developed and instituted a strategic framework for enhancing the company’s relationships with key constituents, including the most significant providers, payers and retailers and the world’s largest governments. Mr. Vounatsos previously held leadership positions across Europe and in China for Merck. Prior to that, Mr. Vounatsos held management positions at Ciba-Geigy. | |
| Education | |
| l | Universite Victor Segalen, Bordeaux II, France, C.S.C.T. Certificate in Medicine |
| l | HEC School of Management - Paris, M.B.A. |
| Susan H. Alexander | |
| Experience | |
| Ms. Alexander has served as our Executive Vice President, Chief Legal Officer and Corporate Secretary since December 2011. Prior to that, from 2006 to December 2011, Ms. Alexander served as our Executive Vice President, General Counsel and Corporate Secretary. From 2003 to January 2006, Ms. Alexander served as the Senior Vice President, General Counsel and Corporate Secretary of PAREXEL International Corporation, a biopharmaceutical services company. From 2001 to 2003, Ms. Alexander served as General Counsel of IONA Technologies, a software company. From 1995 to 2001, Ms. Alexander served as Counsel at Cabot Corporation, a specialty chemicals and performance materials company. Prior to that, Ms. Alexander was a partner at the law firms of Hinckley, Allen & Snyder and Fine & Ambrogne. | |
| Public Company Boards | |
| l | Board of Directors of Invacare Corporation, a medical and healthcare product company |
| Education | |
| l | Wellesley College, B.A |
| l | Boston University School of Law, J.D. |
| Paul J. Clancy | |
| Experience | |
| Mr. Clancy has served as our Executive Vice President, Finance and Chief Financial Officer since August 2007. Mr. Clancy joined Biogen, Inc. in 2001 and has held several senior executive positions with us, including Vice President of Business Planning, Portfolio Management and U.S. Marketing, and Senior Vice President of Finance with responsibilities for leading the Treasury, Tax, Investor Relations and Business Planning groups. Prior to that, he spent 13 years at PepsiCo, a food and beverage company, serving in a range of financial and general management positions. | |
| Public Company Boards | |
| l | Board of Directors of Agios Pharmaceuticals, Inc., a biopharmaceutical company |
| l | Board of Directors of Incyte Corporation, a biopharmaceutical company |
| Education | |
| l | Babson College, B.S. in Finance |
| l | Columbia University, M.B.A. |
| Gregory F. Covino | |
| Experience | |
| Mr. Covino has served as our Vice President, Finance and Chief Accounting Officer since April 2012. Prior to that, Mr. Covino served at Boston Scientific Corporation, a medical device company, as Vice President, Corporate Analysis and Control since March 2010, having responsibility for the company's internal audit function, and as Vice President, Finance, International from February 2008 to March 2010, having responsibility for the financial activities of the company's international division. Prior to that, Mr. Covino held several finance positions at Hubbell Incorporated, an electrical products company, including Vice President, Chief Accounting Officer and Controller from 2002 to January 2008, Interim Chief Financial Officer from 2004 to 2005, and Director, Corporate Accounting from 1999 to 2002. | |
| Education | |
| l | Bryant University, B.S. in Business Administration |
| Michael D. Ehlers | |
| Experience | |
| Dr. Ehlers has served as our Executive Vice President, Head of R&D since May 2016. Prior to joining Biogen, Dr. Ehlers served in leadership positions at Pfizer, Inc., including Senior Vice President & Head BioTherapeutics R&D and Chief Scientific Officer, Neuroscience & Pain. Prior to that, Dr. Ehlers was the George Barth Geller Professor of Neurobiology and an Investigator of the Howard Hughes Medical Institute at Duke University Medical Center. He is the recipient of numerous awards including the Eppendorf & Science Prize in Neurobiology, the John J. Abel Award in Pharmacology, the Society for Neuroscience Young Investigator Award, a National Institute of Mental Health MERIT Award, the National Alliance for Schizophrenia and Depression Distinguished Investigator Award, and the Massachusetts Medical Society Honored Business Leader Award. In 2013, Dr. Ehlers became the 11th recipient of the Thudichum Medal of the Biochemical Society of the United Kingdom. Past recipients include two Nobel laureates. Dr. Ehlers has authored over 100 scientific papers, has served on the Editorial Boards of Annual Reviews in Medicine, Annual Reviews in Pharmacology and Toxicology, the Journal of Neuroscience, the Journal of Biological Chemistry, the Journal of Molecular and Cellular Neuroscience, and has sat on advisory committees of the National Institutes of Health. | |
| Outside Affiliations | |
| l | PhRMA Foundation Basic Pharmacology Advisory Committee |
| l | Janelia Research Institute Advisory Committee |
| l | McKnight Endowment Fund for Neuroscience Board |
| l | World Economic Forum Global Agenda Council on Brain Research |
| Education | |
| l | California Institute of Technology, B.S. Chemistry |
| l | The John Hopkins University School of Medicine, M.D. |
| l | The John Hopkins University School of Medicine, Ph.D. Neuroscience |
| Paul McKenzie | |
| Experience | |
| Dr. McKenzie has served as our Executive Vice President, Pharmaceutical Operations and Technology since July 2016. Prior to that, from February 2016 to June 2016, he served as our Senior Vice President for Global Biologics Manufacturing & Technical Operations. Prior to joining Biogen, since 2008, Dr. McKenzie held a number of positions of increasing responsibility at Johnson & Johnson (J&J), including Vice President of R&D for J&J’s Ethicon business where he led the manufacturing and technical operations team responsible for internal and external manufacturing of Janssen’s pharmaceutical portfolio. He also ran global Development for Janssen R&D, helping to manage pipeline activities from discovery through clinical development and commercialization. Prior to J&J, Dr. McKenzie also held various R&D and manufacturing positions at Bristol-Myers Squibb and Merck & Co. | |
| Education | |
| l | University of Pennsylvania, B.S. Chemical Engineering |
| l | Carnegie Mellon University, Ph.D. Chemical Engineering |
| Kenneth DiPietro | |
| Experience | |
| Mr. DiPietro has served as our Executive Vice President, Human Resources since January 2012. Mr. DiPietro joined Biogen from Lenovo Group, a technology company, where he served as Senior Vice President, Human Resources from 2005 to June 2011. From 2003 to 2005, he served as Corporate Vice President, Human Resources at Microsoft Corporation, a technology company. From 1999 to 2002, Mr. DiPietro worked as Vice President, Human Resources at Dell Inc., a technology company. Prior to that, he spent 17 years at PepsiCo, a food and beverage company, serving in a range of human resource and general management positions. | |
| Public Company Boards | |
| l | Board of Directors of InVivo Therapeutics Corporation, a medical device company |
| Education | |
| l | Cornell University, B.S. in Industrial and Labor Relations |
| Adriana (Andi) Karaboutis | |
| Experience | |
| Ms. Karaboutis has served as our Executive Vice President, Technology, Business Solutions and Corporate Affairs since December 2015 and prior to that served as our Executive Vice President, Technology and Business Solutions since joining Biogen in September 2014. Prior to that, Ms. Karaboutis was Vice President and Global Chief Information Officer of Dell, Inc., where she was responsible for leading a global IT organization focused on powering Dell as an end-to-end technology solutions provider. Prior to joining Dell in 2010, Ms. Karaboutis spent over 20 years at General Motors and Ford Motor Company in various international leadership positions including computer-integrated manufacturing, supply chain operations, and information technology. | |
| Public Company Boards | |
| l | Board of Directors of Advance Auto Parts, an automotive aftermarket parts provider |
| Education | |
| l | Wayne State University, B.S. in Computer Science |
| Alfred W. Sandrock, Jr., M.D., Ph.D. | |
| Experience | |
| Dr. Sandrock has served as our Chief Medical Officer and Executive Vice President of Neurology Discovery and Development since November 2015. Prior to that, Dr. Sandrock served as our Chief Medical Officer and Group Senior Vice President from May 2013 to October 2015, and as our Chief Medical Officer and Senior Vice President of Development Sciences from February 2012 to April 2013. Prior to that, Dr. Sandrock held several senior executive positions since joining us in 1998, including Senior Vice President of Neurology Research and Development and Vice President of Clinical Development, Neurology. | |
| Public Company Boards | |
| l | Board of Directors of Neurocrine Biosciences, Inc., a life sciences company |
| Education | |
| l | Stanford University, B.A. in Human Biology |
| l | Harvard Medical School, M.D. |
| l | Harvard University, Ph.D. in Neurobiology |
| l | Massachusetts General Hospital, internship in Medicine, residency and chief residency in Neurology, and clinical fellowship in Neuromuscular Disease and Clinical Neurophysiology (electromyography) |
Available Information
Our principal executive offices are located at 225 Binney Street, Cambridge, MA 02142 and our telephone number is (617) 679-2000. Our website address is www.biogen.com. We make available free of charge through the Investors section of our website our Annual Reports on Form 10-K, Quarterly Reports on Form 10-Q, Current Reports on Form 8-K and all amendments to those reports as soon as reasonably practicable after such material is electronically filed with or furnished to the Securities and Exchange Commission (SEC). We include our website address in this report only as an inactive textual reference and do not intend it to be an active link to our website. The contents of our website are not incorporated into this report.
Previous: Cover and table of contents · Next: Item 1A. Risk Factors