 filings.tools
Item 1. Business
61K characters. Original on sec.gov · Markdown
Item 1. Business
Overview
We are primarily engaged in the development, manufacturing and sale of our proprietary Omnipod® System, an innovative, discreet and easy-to-use continuous insulin delivery system for people with insulin-dependent diabetes. The Omnipod System consists of two product lines: the Omnipod Insulin Management System (“Omnipod”), which we have been selling since 2005, and our next generation Omnipod DASHTM Insulin Management System ("Omnipod DASH" or "DASH"), which began a U.S. limited market release in 2018. Collectively, we refer to these products as the "Omnipod System".
There are two primary types of insulin therapy practiced today: multiple daily injection (“MDI”) therapy using syringes or insulin pens; and pump therapy using insulin pumps. Insulin pumps are used to perform continuous subcutaneous insulin infusion and typically use a programmable device and an infusion set to administer insulin into the person’s body. Insulin pump therapy has been shown to provide people with insulin-dependent diabetes with numerous advantages relative to MDI therapy. We estimate that approximately one-third of the Type 1 diabetes population in the United States and less than one fifth of the Type 1 diabetes population outside the United States use insulin pump therapy. An even smaller portion of the insulin-dependent Type 2 diabetes population in the United States use insulin pump therapy. We believe these factors present a significant available market for the Omnipod System globally.
The Omnipod System features two discreet, easy-to-use devices: a small, lightweight, self-adhesive disposable tubeless Pod ("Pod"), which is worn on the body and provides up to three days of non-stop insulin delivery without the need to see or handle a needle; and a handheld Personal Diabetes Manager ("PDM"). The Pod can be worn in multiple locations, including the abdomen, hip, back of upper arm, upper thigh or lower back and, because it is waterproof, there is no need to remove it when showering, swimming or performing other activities. The Omnipod System communicates wirelessly, provides for virtually pain-free automated cannula insertion and eliminates the need for traditional MDI therapy or the use of traditional pump and tubing. We believe that the Omnipod System’s unique proprietary design and features allow people with insulin-dependent diabetes to manage their diabetes with unprecedented freedom, comfort, convenience, and ease.
We began commercial sales of the Omnipod in the United States in 2005 and we sell the Omnipod directly to end-users or through intermediaries. The Omnipod is also available in multiple countries in Europe, as well as in Canada and Israel. On July 1, 2018, we commenced direct commercial operations for the Omnipod in Europe immediately following the expiration of our distribution agreement with our former European distributor. In June 2018, the U.S. Food and Drug Administration ("FDA") cleared for commercial sale our Omnipod DASH, which is our next-generation digital mobile Omnipod platform within the Omnipod System family, featuring secured Bluetooth wireless technology for connectivity between the Pod and the color touchscreen smartphone PDM. The DASH PDM is optimized for use with the CONTOUR® NEXT ONE Blood Glucose (BG) Meter for the direct transfer of blood glucose readings to the PDM's bolus calculator. Bluetooth functionality will also provide connectivity to our smartphone apps. We commenced a limited commercial release of Omnipod DASH in 2018 prior to a planned full market launch in the U.S. in the first half of 2019.
For the year ended December 31, 2018, approximately 69% of our consolidated revenue was from sales in the United States and approximately 31% from international sales.
In January 2018, the Centers for Medicare & Medicaid Services (“CMS”) issued guidance clarifying that Medicare Part D Plan Sponsors may provide coverage for products such as the Omnipod System under the Medicare Part D (prescription drug) program. During 2018, we began securing coverage with Medicare Part D carriers to ensure beneficiaries living with diabetes have access to the Omnipod System. Securing Medicare Part D coverage also provides a direct pathway to increased Medicaid coverage at the state level, as many state-run Medicaid programs follow CMS prescription drug guidance to determine coverage. This increased Medicaid access allows access for lower-income individuals and families for whom Omnipod had previously not been a covered option. In April 2018, we also significantly increased our market access when we secured in-network coverage of Omnipod with UnitedHealthcare, the largest commercial payer in the United States.
In addition to the diabetes market space, we have partnered with pharmaceutical and biotechnology companies to tailor the Omnipod System technology platform for the delivery of subcutaneous drugs across other therapeutic areas. The majority of our drug delivery revenue currently consists of sales of Pods used in Amgen's Neulasta Onpro kit, an innovative delivery system for Amgen’s white blood cell booster to help reduce the risk of infection during intense chemotherapy.
We have substantially completed the construction of a highly-automated manufacturing facility in Acton, Massachusetts, with planned production out of the facility beginning in the first half of 2019. The facility also serves as our global headquarters. We expect that, following start-up related activities, the new facility will allow us to lower our manufacturing costs, increase supply redundancy, add capacity closer to our largest customer base and support our growth trajectory.
Market Opportunity: Management of Diabetes
Diabetes is a chronic, life-threatening disease for which there is no known cure. It is caused by the body’s inability to produce or effectively utilize the hormone insulin, which prevents the body from adequately regulating blood glucose levels. Glucose, the primary source of energy for cells, must be maintained at certain concentrations in the blood in order to permit optimal cell function and health. In people with diabetes, blood glucose levels fluctuate between very high levels, a condition known as hyperglycemia, and very low levels, a condition called hypoglycemia. Hyperglycemia can lead to serious short-term complications, such as confusion, vomiting, dehydration and loss of consciousness and long-term complications, such as blindness, kidney disease, nervous system disease, occlusive vascular diseases, stroke and cardiovascular disease, or death. Hypoglycemia can lead to confusion, loss of consciousness or death.
Diabetes is typically classified as either Type 1 or Type 2:
| • | Type 1 diabetes is characterized by the body’s nearly complete inability to produce insulin. It is frequently diagnosed during childhood or adolescence. Individuals with Type 1 diabetes require daily insulin therapy to survive. It is estimated that approximately one million to two million people in the United States have Type 1 diabetes. |
| • | Type 2 diabetes, the more common form, is characterized by the body’s inability to either properly utilize insulin or produce enough insulin. Historically, Type 2 diabetes has occurred in later adulthood, but its incidence is increasing among the younger population, due primarily to increasing obesity. Initially, many people with Type 2 diabetes attempt to manage their diabetes with improvements in diet, exercise and/or oral medications. As their diabetes advances, some patients progress to multiple drug therapies, which often include insulin therapy. It is estimated that approximately two million to three million people in the United States have Type 2 diabetes that requires daily insulin administration. |
Throughout this Annual Report on Form 10-K, we refer to both Type 1 diabetes and insulin-requiring Type 2 diabetes as insulin-dependent diabetes.
Diabetes Management Challenges
Diabetes is often frustrating and difficult for patients to manage. Blood glucose levels can be affected by the carbohydrate and fat content of meals, exercise, stress, illness or impending illness, hormonal releases, variability in insulin absorption and changes in the effects of insulin on the body. For people with insulin-dependent diabetes, many corrections, consisting of the administration of additional insulin or ingestion of additional carbohydrates, are needed throughout the day in order to maintain blood glucose levels within normal ranges. Achieving this result can be very difficult without multiple daily injections of insulin or insulin pump therapy. Patients attempting to control their blood glucose levels tightly to prevent the long-term complications associated with fluctuations in blood glucose levels are at greater risk for overcorrection and the resultant hypoglycemia. As a result, many patients have difficulty managing their diabetes. Additionally, the time spent managing fluctuations in blood glucose levels and the fear associated with hypoglycemia can be incredibly stressful to patients and their families.
Current Insulin Therapy
People with insulin-dependent diabetes need a continuous supply of insulin, known as basal insulin, to provide for background metabolic needs. In addition to basal insulin, people with insulin-dependent diabetes require supplemental insulin, known as bolus insulin, to compensate for carbohydrates ingested during meals or snacks or for a high blood glucose level.
As previously noted, there are two primary types of insulin therapy practiced today: MDI therapy and insulin pump therapy. Insulin pumps are used to perform continuous subcutaneous insulin infusion and typically use a programmable device and an infusion set to administer insulin into the person’s body. MDI therapy involves the administration of fast-acting insulin before meals (bolus) to lower blood glucose levels to a healthy range. MDI therapy may also require a separate injection of a long-acting (basal) insulin, to control glucose levels between meals; typically once or twice per day. By comparison, insulin pump therapy uses only fast-acting insulin to fulfill both mealtime (bolus) and background (basal) requirements. Insulin pump therapy allows individuals to customize their bolus and basal insulin doses to meet their insulin needs throughout the day, and is intended to more closely resemble the physiologic function of a healthy pancreas.
Insulin pump therapy has been shown to provide numerous advantages relative to MDI therapy. For example, insulin pump therapy eliminates individual insulin injections (approximately five per day), delivers insulin more accurately and precisely than injections, often improves HbA1c (a common measure of blood glucose levels) over time, provides greater flexibility with meals, exercise and daily schedules, and can reduce severe low blood glucose levels.
We believe that these distinct advantages, including technological advancements and increased awareness of insulin pump therapy as compared to other available insulin therapies will continue to generate demand for insulin pump devices.
Our Solution: The Omnipod System
The Omnipod System is an innovative continuous insulin delivery system that provides all the benefits of insulin pump therapy in a way no conventional insulin pump can. The Omnipod System's innovative design and differentiated features allow people with insulin-dependent diabetes to live their lives, and manage their diabetes, with unprecedented freedom, comfort, convenience and ease.
 | 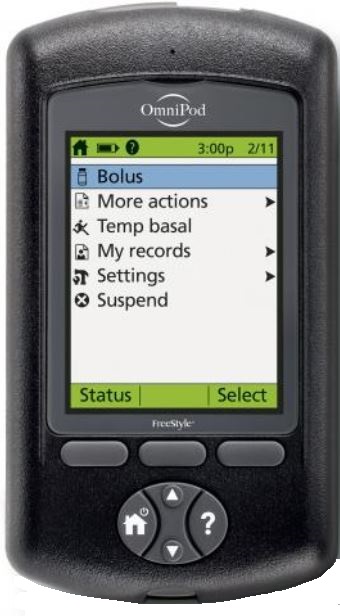 |  |
| Pod | Omnipod PDM | Omnipod DASH PDM |
The Omnipod System is a discreet two-part design, the Pod and the PDM, that eliminates the need for the external tubing required with conventional pumps.
| • | The Pod is a small, lightweight, self-adhesive device that the user fills with insulin and wears directly on the body. The Pod delivers precise, personalized doses of insulin into the body through a small flexible tube (called a cannula), based on instructions that the patient programs into the Pod's wireless companion, the PDM. |
| • | The PDM is a wireless, handheld device that programs the Pod with the user's personalized insulin-delivery instructions and, wirelessly monitors the Pod's operation. |
The Omnipod System provides continuous insulin delivery at preset rates, eliminating the need for individual insulin injections and the interruptions that come with them. In addition, insulin delivery can be changed with the press of a button to adapt to snacks or unexpected changes in daily routine.
The Omnipod System works much like the pancreas of a person without diabetes by delivering insulin in two ways:
| • | A small, constant background supply of insulin is delivered automatically at a programmed rate, all day and night. |
| • | An extra dose of insulin can be delivered when a patient needs it to match the carbohydrates in a meal or snacks or to correct high blood glucose. |
We have designed the Omnipod System to fit within the normal daily routines of patients. The Omnipod System consists of just two devices as opposed to up to seven for conventional tubed insulin pumps. As a result, the Omnipod System is easy for patients to use, which also reduces the training burden on healthcare professionals and end-users. We believe that the Omnipod System’s overall ease of use, flexibility, and substantially lower training burden make it very attractive to people with insulin-dependent diabetes and help redefine for whom insulin pump therapy is appropriate, allowing healthcare professionals to prescribe pump therapy to a broader group of patients.
The Omnipod System’s unique patented design and proprietary manufacturing process allow us to provide pump therapy at a relatively low up-front investment compared to conventional tubed insulin pumps. We believe that our pricing model, which includes little or no initial investment, reduces the risk to third-party payors of significant up-front investments commonly associated with traditional tubed insulin pumps.
Several publications over the past decade have found that compared to multiple daily injections therapy, the use of the Omnipod System by individuals with both Type 1 and Type 2 diabetes across all age groups is associated with good glycemic control, reduced total daily dose of insulin, and reduced frequency and severity of hypoglycemic episodes. These results are consistent with other published literature of other continuous subcutaneous insulin infusion devices similar to the Omnipod System. In addition, research in adults with Type 1 diabetes has found that compared to prior treatment modality, the use of the Omnipod System is associated with improved quality of life. We believe that this data is clinically meaningful to healthcare providers and provides support for the use of the Omnipod System in the treatment of both Type 1 and Type 2 diabetes.
We have partnered with Glooko Inc. ("Glooko") to connect our Omnipod System user data with Glooko's comprehensive diabetes data management system (including Glooko and Diasend in selected regions). Glooko provides a cloud-based application for clinicians and patients accessible through a kiosk, home computer or a mobile application on the user's smartphone that provides patients and their health care providers access to insulin delivery trends, blood glucose levels and other integrated data.
Third-Party Reimbursement
In the United States, our products are generally reimbursed by third-party payors when sold directly to end-users, and we bill those payors for products provided to end-users. Prior to 2018, coverage was more limited in the United States due to the lack of an established mechanism for Medicare or broad Medicaid coverage for the majority of the Omnipod System. In January 2018, CMS issued guidance clarifying that Medicare Part D Plan Sponsors may provide coverage for products such as the Omnipod System under the Medicare Part D (prescription drug) program. We have been successful in securing coverage with Medicare Part D plans, which allows many additional people with diabetes to access our product. The ability of Medicare Part D plans to cover the Omnipod System also provides us with a direct pathway to gain Medicaid coverage at the state level, as many state-run Medicaid look to Medicare to determine coverage. This allows access for lower-income individuals and families on Medicaid for whom Omnipod is currently not an option. In addition, in April 2018, we also significantly increased our third-party reimbursement when we secured in-network coverage of Omnipod with UnitedHealthcare, the largest commercial payer in the United States.
We continue to work with third-party payors in the United States to establish coverage and payment for the Omnipod System. Our coverage contracts with third-party payors typically have a term of between one and three years and set coverage amounts during that term. Typically, coverage contracts automatically renew for specified incremental periods upon expiration, unless one of the parties terminates the contract.
Our fulfillment and reimbursement systems are fully integrated such that product is generally shipped only after confirmation of a physician’s valid statement of medical necessity and current health insurance information. We maintain an insurance benefits investigation department that works to simplify and expedite claims processing and to assist patients in obtaining third-party reimbursement. Common medical criteria for third-party payors approving reimbursement for pump therapy may include a patient having elevated A1c levels, a history of recurring hypoglycemia, fluctuations in blood glucose levels prior to meals or upon waking or, severe glycemic variability. Third-party payors may decline to reimburse for procedures, supplies or services determined not to be “medically necessary” or “reasonable.” Reimbursement may also be declined by insurers based upon the contract between the insurer and the insured group.
In Europe, in connection with of our recent assumption of direct operations in mid-2018, we have worked with local healthcare systems to establish coverage and payment processes for the Omnipod System. In certain non-U.S. locations in which we sell through a distributor, our distribution partners establish appropriate reimbursement contracts with healthcare systems in those countries and provinces.
Markets and Distribution Methods
We sell the Omnipod directly to patients or indirectly through intermediaries, such as independent distributors and the pharmacy channel, in the United States, Canada, Europe, and Israel. In 2018, following FDA clearance, we also commenced a limited commercial release of Omnipod DASH directly to customers in the U.S. For the year ended December 31, 2018, approximately 46% of our Omnipod System sales in the United States were through intermediaries. Consistent with CMS’s decision in 2018 that products such as the Omnipod System are coverable under the Medicare Part D prescription drug benefit, we have been expanding access to our Omnipod System through the pharmacy channel, which we believe provides several competitive advantages over the durable medical equipment ("DME") distribution method used by traditional pump companies. Internationally, the majority of our sales are through intermediaries.
Our sales and marketing efforts are focused on patient retention and growing patient, clinician and payor demand for the Omnipod System. We have a uniform sales and marketing approach, aligned across patients, physicians and providers, to capitalize on the unique benefits of our Omnipod System technology. We have three areas of focus:
| • | First, build patient awareness about the features and benefits that the Omnipod System provides. |
| • | Second, build physician support by increasing the clinical evidence that demonstrates the benefits that the Omnipod System provides and improving the patient-monitoring data available to physicians providing diabetes care. |
| • | Third, provide payors with the clinical and economic justification for why the Omnipod System is a unique value to the patients whom they insure. |
Training. We believe that training patients how to use the Omnipod System is an important factor to promote successful outcomes and patient retention. We have streamlined and standardized our patient training by developing improved online resources and increased our field clinician team to directly train new Omnipod System customers.
Customer Support. We seek to provide our customers with high quality customer support, from product ordering to insurance investigation, order fulfillment and ongoing support. We have integrated our customer support systems with our sales, reimbursement and billing processes and also offer support by telephone and through our website to provide customers with seamless and reliable support.
Competition
The diabetes medical device market is highly competitive, subject to rapid change and significantly affected by new product introductions. The Omnipod System competes for patients in the insulin delivery market. Because the majority of new Omnipod System end-users come from MDI therapy, which currently is the most prevalent method of insulin delivery, we believe that we primarily compete with companies that provide MDI therapy. To a smaller extent, we also compete with companies in the insulin pump market, which today consists of conventional tubed pump companies, including Medtronic MiniMed, a division of Medtronic Public Limited Company ("Medtronic"), and Tandem Inc. Medtronic historically has held the majority share of the conventional tubed insulin pump market in the United States. The competitive landscape in our industry continues to undergo significant change. For example, Animas Corporation, a division of Johnson & Johnson, exited the insulin pump market in the United States and other countries in late 2017. In addition to the established insulin pump competitors, several companies are working to develop and market new insulin patch pumps and smart pens. These companies are at various stages of development and the number of such companies often changes as they enter or exit the market. Our non-insulin drug delivery product line also competes with drug delivery device companies such as West Pharmaceutical Services, Inc.
Research and Development
Our current research and development efforts are primarily focused on making improvements to the Omnipod System, including adding features and functionality that will deliver economic value, convenience and simplicity to our customers, and improving our supply chain operations. These efforts include:
Omnipod DASH. We have developed Omnipod DASH, our next generation of the Omnipod System, which features a secure Bluetooth-enabled Pod and PDM with a touch screen color user interface supported by smartphone connectivity incorporating state-of-the-art security features. Bluetooth functionality also provides connectivity to our smartphone apps, allowing users and those they approve (e.g. caregivers) to view their Omnipod DASH data on their personal smartphones. In June 2018, the FDA provided clearance for the commercial distribution of DASH in the U.S. We commenced a limited commercial release of DASH in 2018 and expect to commence a full market launch in the U.S. in the first half of 2019.
Omnipod HorizonTM Automated Insulin Delivery System ("Omnipod Horizon System"). We also are developing a hybrid closed loop control system that utilizes the DASH mobile platform to allow the Pod to communicate with Dexcom Inc.'s ("Dexcom") continuous glucose monitor and help control insulin delivery utilizing an algorithm located on the Pod. The Omnipod Horizon System is intended to be controllable through a secure mobile app on the user's smartphone (i.e. "phone control"). In July 2018, we announced positive results from a clinical trial finding that the Omnipod Horizon System performed well and was safe for over five days of use in adults, adolescents, and children with Type 1 diabetes. The Omnipod Horizon System recently was granted designation in the FDA's breakthrough device program, which is a program intended to help patients have more timely access to certain medical devices and device-led combination products that provide for more effective treatment or diagnosis of life-threatening or irreversibly debilitating diseases or conditions by expediting the development and review process. We believe that recent and ongoing developments in the use of Continuous Glucose Monitoring ("CGM") technology and Automated Insulin Delivery ("AID") algorithms in conjunction with insulin pump therapy will continue to provide people with insulin-dependent diabetes benefits that will make insulin pump therapy an even more attractive treatment alternative to the existing MDI therapy market.
Paramount to our ability to deliver phone control is our commitment to cyber and information security. Just recently, Omnipod DASH became the first FDA-cleared insulin pump to be certified under the Diabetes Technology Society’s “Standard for
Wireless Diabetes Device Security” cybersecurity assurance standard and program, known as DTSec. This certification is a cybersecurity standard with the goal of raising confidence in the security of network connected medical devices through independent expert evaluation. In addition, Omnipod DASH recently received International Standards Organization ("ISO") 27001 certification, which is the international standard for best practice in an information security management system globally. With the DTSec and ISO 27001 certifications, Omnipod DASH is now globally recognized for incorporating the highest standards for cyber and information security and safety, including secure data transfer between the Pod and PDM, as well as secure cloud storage.
Concentrated Insulin Delivery. In collaboration with Eli Lilly, we are developing new products that leverage the DASH mobile platform to support the use of concentrated insulins for Type 1 and Type 2 patients with higher insulin-requirements, utilizing the same form factor as our existing Pod. These new products are being specifically designed to deliver Humalog -® 200 units/mL and Humulin® R U-500 insulin, which are concentrated forms of insulin used by people with highly insulin resistant Type 2 diabetes. Together with our Omnipod DASH System, we believe these innovations significantly expand our access to more of the Type 2 diabetes market.
Supply Chain Operation Improvements. We continue to invest in improvements and efficiencies to our entire supply chain, including improvements in automation at our suppliers and contract manufacturer as well as our U.S. manufacturing facility in Acton, Massachusetts, set to commence manufacturing in the first half of 2019.
Manufacturing and Quality Assurance
We believe a key contributing factor to the overall attractiveness and success of the Omnipod System is the disposable nature of the Pod. In order to manufacture sufficient volumes and achieve a cost-effective per unit production price for the Omnipod, we have designed the Omnipod System to be manufactured through automation.
We produce our devices on varying degrees of semi-automated manufacturing lines at a facility in China, operated by a subsidiary of Flex Ltd. (“Flex”) pursuant to a multi-year materials supply agreement. The agreement expires in December 2022 and is subject to an automatic renewal thereafter, unless otherwise canceled by the parties under the contract terms.
We have substantially completed the construction of a highly automated manufacturing facility that we own and will operate in Acton, Massachusetts. This facility now serves as our global headquarters and we plan to produce devices there beginning in the first half of 2019. We expect that, following start up related activities, the new facility will allow us to lower our manufacturing costs, increase supply redundancy, add capacity closer to our largest customer base, and support our strong growth trajectory. To date, we have invested approximately $193 million in property, equipment and infrastructure related to the new facility. We expect to continue to expand our investment in this facility in 2019 to support the growth of our business.
We utilize outside vendors for the supply of components, sub-assemblies, and various services used in the manufacture of the Omnipod System. Our outside vendors produce the components to our specifications and they are audited periodically by our Quality Assurance Department to confirm conformity with the specifications, policies and procedures for the Omnipod System. Our Quality Assurance Department also inspects and tests the Omnipod System at various steps in the manufacturing cycle to facilitate compliance with our specifications. We have received approval of our Quality Management System from the BSI Group London, U.K., an accredited Notified Body for CE Marking and the International Standards Organization. Processes utilized in the manufacture, test and release of the Omnipod System have been verified and validated as required by the FDA and other regulatory bodies. As a medical device manufacturer and distributor, our manufacturing facilities and the facilities of our suppliers are subject to periodic inspection by the FDA and certain corresponding state agencies.
Intellectual Property
To maintain a competitive advantage, we believe we must develop and preserve the proprietary aspect of our technologies. We rely on a combination of copyright, patent, trademark, trade secret and other intellectual property laws, non-disclosure agreements and other measures to protect our proprietary rights. Currently, we require our employees, consultants and advisers to execute non-disclosure agreements in connection with their employment, consulting or advisory relationships with us, where appropriate. We also require employees, consultants and advisers who work on our products to agree to disclose and assign to us all inventions conceived during their work with us that are developed using our property or relate to our business. Despite any measures taken to protect our intellectual property, unauthorized parties may attempt to copy aspects of the Omnipod System or to obtain and use information that we regard as proprietary.
Patents. As of December 31, 2018, we had 21 granted and active U.S. patents with expiration dates ranging from 2020 through 2034, and had 56 additional pending U.S. patent applications. We believe that it will take at least several years for the most recent of these U.S. patent applications to result in issued patents. We are also seeking patent protection for our proprietary technology in other countries and regions throughout the world. The issued patents and pending patent applications cover, among other things:
| • | the basic architecture of the Omnipod System, including the pump and the PDM; |
| • | the Omnipod shape memory alloy drive system; |
| • | the Omnipod System cannula insertion system; |
| • | communication features between system components for the Omnipod System and next generation products; |
| • | software, such as apps, for controlling the Omnipod System and next generation products; and |
| • | various novel aspects of the Omnipod System, potential future generations of Omnipod Systems, and other mechanisms for the delivery of pharmaceuticals. |
Trademarks. We have registered various trademarks associated with our business with the United States Patent and Trademark Office on the Principal Register and in other appropriate jurisdictions. Our trademarks include OMNIPOD(R), DASHTM, Omnipod CONTROLTM, Omnipod DISPLAYTM, Omnipod VIEWTM, Omnipod OMNIPOD U-200TM, OMNIPOD U-500TM, HORIZONTM, Pod PalsTM and PodderTM.
Government Regulation
United States FDA Regulation
The Omnipod System is a medical device subject to extensive and ongoing regulation by the FDA and other federal, state, and local regulatory bodies. FDA regulations govern, among other things, product design and development, preclinical and clinical testing, manufacturing, labeling, post-market adverse event reporting, post-market surveillance, complaint handling, repair or recall of products, product storage, record keeping, pre-market clearance or approval, advertising and promotion, and sales and distribution.
FDA’s Pre-Market Notification 510(k) and Pre-Market Approval Requirements. Unless an exemption applies, each medical device we seek to commercially distribute in the United States will require either prior 510(k) clearance or pre-market approval (“PMA”) from the FDA. We have obtained 510(k) clearance for the Omnipod and Omnipod DASH Systems and expect that PMA approval may be needed for some of our future products. We may be required to obtain a new 510(k) clearance or pre-market approval for significant post-market modifications to our products. Both the 510(k) clearance and PMA processes can be expensive and lengthy and entail significant user fees, unless an exemption is available.
510(k) Clearance. To obtain 510(k) clearance for any of our potential future devices (or for certain modifications to devices that have previously received 510(k) clearance), we must submit a pre-market notification demonstrating that the proposed device is substantially equivalent to a previously cleared 510(k) device. The FDA’s 510(k) clearance pathway generally takes from three to twelve months from the date the application is completed, but can take significantly longer. After a medical device receives 510(k) clearance, any modification that could significantly affect its safety or effectiveness, or that would constitute a significant change in its intended use, requires a new 510(k) clearance or, depending on the modification, could require a PMA application. The FDA requires each manufacturer to make this determination initially, but the FDA can review any such decision and can disagree with a manufacturer’s determination. If the FDA disagrees with a manufacturer’s determination regarding whether a new premarket submission is required for the modification of an existing device, the FDA can, at its discretion, require the manufacturer to cease marketing and/or recall the modified device until 510(k) clearance or approval of a PMA application is obtained. In addition, in these circumstances, we may be subject to significant regulatory fines or penalties for failure to submit the requisite PMA application(s).
PMA. Devices deemed by the FDA to pose the greatest risk, such as life-sustaining, life-supporting or implantable devices, devices deemed not substantially equivalent to a previously cleared 510(k) device generally require a PMA before they can be commercially distributed. A PMA application must be supported by extensive data, including technical information, pre-clinical and clinical trials, manufacturing and labeling to demonstrate the safety and effectiveness of the device to the FDA’s satisfaction. After a PMA application is complete, the FDA begins an in-depth review of the submitted information, which generally takes between one and three years, but may take significantly longer. During this review period, the FDA may request additional information or clarification of information already provided. Also during the review period, an advisory panel of experts from outside the FDA may be convened to review and evaluate the application and provide recommendations to the FDA as to the approvability of the device. The FDA will conduct a pre-approval inspection of the manufacturing facility to ensure compliance with Quality System Regulations, or QSRs, which impose elaborate design development, testing, control, documentation and other quality assurance procedures in the design and manufacturing process. The FDA may approve a PMA application with post-approval conditions intended to ensure the safety and effectiveness of the device including, among other things, restrictions on labeling, promotion, sale and distribution and collection of long-term follow-up data from patients in the clinical study that supported approval. Failure to comply with the conditions of approval can result in materially adverse enforcement action, including the loss or withdrawal of the approval. After any pre-market approval, a new pre-market approval application or application supplement may be required in the event of modifications to the device, its labeling, intended use or
indication or its manufacturing process. PMA supplements often require submission of the same type of information as a PMA application, except that the supplement is limited to information needed to support any changes from the device covered by the original PMA application, and may not require as extensive clinical data or the convening of an advisory panel.
Clinical Trials. Clinical trials are almost always required to support a PMA application and sometimes also 510(k) submissions. If the device presents a “significant risk” to human health as defined by the FDA, the FDA requires the device sponsor to submit an investigational device exemption ("IDE") to the FDA and obtain IDE approval prior to commencing the human clinical trials. The IDE must be supported by appropriate data, such as animal and laboratory testing results, showing that it is safe to test the device in humans and that the testing protocol is scientifically sound. The IDE must be approved in advance by the FDA for a specified number of patients, unless the product is deemed a “non-significant risk” device, in which case an IDE approval from the FDA would not be required, although the clinical trial would need to meet other requirements including IRB approval. Clinical trials for a significant risk device may begin once an IDE is approved by the FDA and the appropriate Institutional Review Board ("IRB") at each clinical trial site. Future clinical trials may require that we obtain an IDE from the FDA prior to commencing any such clinical trial and that the trial be conducted with the oversight of an IRB at the clinical trial site.
Our clinical trials must be conducted in accordance with FDA regulations and federal and state regulations concerning human subject protection, including informed consent and healthcare privacy. A clinical trial may be suspended by the FDA or at a specific site by the relevant IRB at any time for various reasons, including a belief that the risks to the trial participants outweigh the benefits of participation in the clinical trial. Even if a clinical trial is completed, the results of our clinical testing may not demonstrate the safety and efficacy of the device, or may be equivocal or otherwise not be sufficient for us to obtain approval of our product.
Ongoing Regulation by FDA. Even after a device is placed on the market, regardless of its classification or premarket pathway, numerous regulatory requirements apply. These include, but are not limited to:
| • | establishment registration and device listing; |
| • | quality system regulation, or QSR, which requires manufacturers, including third party manufacturers, to follow stringent design, testing, control, documentation and other quality assurance procedures during all aspects of the development and manufacturing process; |
| • | labeling regulations and FDA prohibitions against the promotion of products for uncleared, unapproved or “off-label” uses, and other requirements related to promotional activities; |
| • | medical device reporting regulations, which require that manufacturers report to the FDA if their device may have caused or contributed to a death or serious injury or malfunctioned in a way that would likely cause or contribute to a death or serious injury if the malfunction were to recur; |
| • | corrections and removals reporting regulations, which require that manufacturers report to the FDA field corrections and product recalls or removals if undertaken to reduce a risk to health posed by the device or to remedy a violation of the federal Food, Drug and Cosmetic Act that may present a risk to health. In addition, FDA may order a mandatory recall if there is a reasonable probability that the device would cause serious adverse health consequences or death; and |
| • | post-market surveillance regulations, which apply when necessary to protect the public health or to provide additional safety and effectiveness data for the device. |
Failure to comply with applicable regulatory requirements can result in enforcement actions by the FDA and other regulatory agencies, which may include any of the following sanctions: untitled letters or warning letters, fines, injunctions, consent decrees, civil or criminal penalties, recall or seizure of our current or future products, operating restrictions, partial suspension or total shutdown of production, refusal of or delay in granting 510(k) clearance or PMA approval of new products or modified products, rescinding previously granted 510(k) clearances or withdrawing previously granted PMA approvals, or refusal to grant import or export approval of our products.
We are subject to announced and unannounced inspections by the FDA, and these inspections may include the manufacturing facilities of our subcontractors. If, as a result of these inspections, the FDA determines that our equipment, facilities, laboratories or processes do not comply with applicable FDA regulations and conditions of product approval, the FDA may seek civil, criminal or administrative sanctions and/or remedies against us, including the suspension of our manufacturing operations. Since approval of the Omnipod System, we have been subject to FDA inspections of our facility on multiple occasions.
International Product Regulations
International sales of medical devices are subject to foreign government regulations, which may vary substantially from country to country. The time required to obtain approval by a foreign country may be longer or shorter than that required for FDA clearance or approval, and the requirements may differ. There is a trend towards harmonization of quality system standards among the European Union, United States, Canada and various other industrialized countries.
The primary regulatory body in Europe is that of the European Union, which includes most of the major countries in Europe. Other countries, such as Switzerland, have voluntarily adopted laws and regulations that mirror those of the European Union with respect to medical devices. The European Union has adopted numerous directives and standards regulating the design, manufacture, clinical trials, labeling and adverse event reporting for medical devices, including the Medical Device Directive ("MDD"). Devices that comply with the requirements of a relevant directive will be entitled to bear the CE conformity marking, indicating that the device conforms to the essential requirements of the applicable directives and, accordingly, can be commercially distributed throughout Europe. The method of assessing conformity varies depending on the class of the product, but normally involves a combination of self-assessment by the manufacturer and a third party assessment by a “Notified Body.” This third-party assessment may consist of an audit of the manufacturer’s quality system and specific testing of the manufacturer’s product. An assessment by a Notified Body of one country within the European Union is required in order for a manufacturer to commercially distribute the product throughout the European Union. Outside of the European Union, regulatory approval needs to be sought on a country-by-country basis in order for us to market our products.
We have obtained the right to affix the CE Mark to the Omnipod and Omnipod DASH Systems. The CE Mark gives us authorization to distribute these products throughout the European Union and in other countries that recognize the CE Mark. In September 2009, we received Health Canada approval to distribute the Omnipod throughout Canada. We have been distributing the Omnipod in certain countries in Europe through intermediaries or directly to end-users since 2010.
Other Regulations
Licensure. Several states require that DME providers be licensed in order to sell products to patients in that state. Certain of these states require, among other things, that DME providers maintain an in-state location. In order to sell our product through the pharmacy channel, we are required to work with intermediaries who have the appropriate pharmacy license for the applicable market in which we provide customers with access to our product through the pharmacy.
In addition, we are subject to certain state laws regarding professional licensure. We believe that our certified diabetes educators are in compliance with all such state laws. However, if our educators or we were to be found non-compliant in a given state, we may need to modify our approach to providing education, clinical support and customer service.
Federal Anti-Kickback and Self-Referral Laws. The federal healthcare Anti-Kickback Statute prohibits the knowing and willful offer, payment, solicitation or receipt of any form of remuneration (anything of value) in return for, or to induce:
| • | the referral of an individual; |
| • | furnishing or arranging for the furnishing of items or services reimbursable under Medicare, Medicaid or other federal health care programs; or |
| • | the purchase, lease, or order of, or the arrangement or recommendation of the purchasing, leasing, or ordering of, any item or service reimbursable under Medicare, Medicaid or other federal health care programs. |
The federal Anti-Kickback Statute has been interpreted to apply to arrangements between drug and medical device manufacturers and suppliers on one hand and prescribers, patients, purchasers and formulary managers on the other. Liability under the statute may be established without a person or entity having actual knowledge of the statute or specific intent to violate it. In addition, claims resulting from a violation of the federal Anti-Kickback Statute constitute false or fraudulent claims for purposes of the federal civil False Claims Act, which is addressed below. Although there are a number of statutory exemptions and regulatory safe harbors protecting certain common business practices from prosecution and administrative sanctions, the exemptions and safe harbors are drawn narrowly, and practices that involve remuneration that may be perceived as inducing the prescription, purchase, or recommendation of the Omnipod System may be subject to scrutiny under the law. For example, we provide the initial training to patients necessary for appropriate use of the Omnipod System either through our own diabetes educators or by contracting with outside diabetes educators that have completed a Certified Pod Trainer training course. We compensate outside diabetes educators for their services at contracted rates deemed to be consistent with the market. We have structured our arrangements with diabetes educators and other business practices to comply with statutory exemptions and regulatory safe harbors whenever possible, but our practices may be subject to scrutiny if they fail to strictly comply with the criteria in the exemption or regulatory safe harbor. Moreover, there are no safe harbors for many common practices such providing reimbursement assistance, coding and billing information or other patient assistance and product support programs. If any of our practices, arrangements or programs are found not to be in compliance with the federal Anti-Kickback Statute, we can be subject to significant criminal, civil and administrative penalties, including imprisonment, fines, damages, and exclusion
from Medicare, Medicaid or other governmental programs, any of which could have an adverse effect on our business and results of operations.
Federal law also includes a provision commonly known as the “Stark Law,” which prohibits a physician from referring Medicare or Medicaid patients to an entity for the furnishing of certain “designated health services,” including durable medical equipment, in which the physician has an ownership or investment interest or with which the physician has entered into a compensation arrangement. Violation of the Stark Law could result in denial of payment, disgorgement of reimbursements received for items and services referred by a physician with a noncompliant arrangement, civil damages and penalties, and exclusion from Medicare, Medicaid or other governmental programs. Although there are a number of statutory and regulatory exceptions protecting certain common business practices implicating the Stark Law, and we have structured our arrangements with physicians and other providers to comply with these exceptions, these arrangements may not expressly meet the requirements for applicable exceptions from the law.
Federal civil False Claims Act. The federal civil False Claims Act imposes penalties against any person or entity who, among other things, knowingly presents, or causes to be presented, a false or fraudulent claim for payment of government funds or knowingly making, using or causing to be made or used a false record or statement material to a false or fraudulent claim. Actions under the False Claims Act may be brought by the Attorney General or as a qui tam action by a private individual in the name of the government. Violations of the False Claims Act are subject to the imposition of significant per claim penalties, three times the amount of damages that the federal government sustained and possible exclusion from participation in federal health care programs like Medicare and Medicaid. We believe that we are in compliance with the federal government’s laws and regulations concerning the filing of claims for reimbursement. However, many drug and medical device manufacturers have been investigated or subject to lawsuits by whistleblowers and have reached substantial financial settlements with the federal government under the False Claims Act for a variety of alleged improper marketing activities, including providing free product to customers with the expectation that the customers would bill federal programs for the product; or causing submission of false claims by providing inaccurate coding or billing information to actual or prospective purchasers, and our business practices could be subject to scrutiny and enforcement under the federal False Claims Act. We also may be subject to other federal false claim laws, including federal criminal statutes that prohibit making a false statement to the federal government.
Civil Monetary Penalties Law. We are also subject to the federal Civil Monetary Penalties Law, which prohibits, among other things, the offering or transferring of remuneration to a Medicare or Medicaid beneficiary that the person knows or should know is likely to influence the beneficiary’s selection of a particular supplier of Medicare or Medicaid payable items or services. Noncompliance can result in significant civil money penalties for each wrongful act, assessment of three times the amount claimed for each item or service and exclusion from the federal healthcare programs.
Federal Health Care Fraud Statutes. We are also subject to a federal health care fraud statute that, among other things, imposes criminal and civil liability for executing a scheme to defraud any health care benefit program including non-governmental programs, and prohibits knowingly and willfully falsifying, concealing or covering up a material fact or making any materially false or fraudulent statement or representation, or making or using any false writing or document with knowledge that it contains a materially false or fraudulent statement in connection with the delivery of or payment for health care benefits, items or services. Violations of these statutes can result in significant civil, criminal and administrative penalties, fines, damages, and exclusion from federal health care programs.
State Fraud and Abuse Laws and Marketing Restrictions. Many states have also adopted anti-kickback, anti-referral laws, and false claims laws and regulations analogous to the federal civil Anti-Kickback Statute and federal False Claims Act, and in some cases these state laws apply regardless of the payer, including private payors. We believe that we are in conformance with such laws. Moreover, several states have imposed requirements to disclose payments to health care providers, restrictions on marketing and other expenditures, and requirements to adopt a code of conduct or compliance program with specific elements. Liability under such laws could result in fines and penalties and restrictions on our ability to operate in these jurisdictions.
Administrative Simplification of the Health Insurance Portability and Accountability Act of 1996. The Health Insurance Portability and Accountability Act of 1996 (“HIPAA”) mandated the adoption of standards for the exchange of electronic health information in an effort to encourage overall administrative simplification and enhance the effectiveness and efficiency of the healthcare industry. Ensuring privacy and security of patient information is one of the key factors driving the legislation. If we are found to be in violation of HIPAA, we could be subject to civil or criminal penalties.
General Data Protection Regulation. The General Data Protection Regulation ("GDPR") is a comprehensive update to the data protection regime in the European Economic Area that is effective in fiscal 2018. The GDPR imposes new requirements relating to, among other things, consent to process personal data of individuals, the information provided to individuals regarding the processing of their personal data, the security and confidentiality of personal data, notifications in the event of data breaches and use of third party processors. If we fail to comply with these standards, we could be subject to criminal penalties and civil sanctions, including fines and penalties for noncompliance with the GDPR.
Patient Protection and Affordable Care Act. The Patient Protection and Affordable Care Act as amended by the Health Care and Education Reconciliation Act of 2010 (“ACA”) enacted significant changes to the provision of and payment for healthcare in the United States. Under the ACA and related laws and regulations, federal and state government initiatives are focused on limiting the growth of healthcare costs and implementing changes to healthcare delivery structures. These reforms are intended in part to put increased emphasis on the delivery to patients of more cost-effective therapies and could adversely affect our business. Some of the provisions of the ACA have yet to be fully implemented, and certain provisions have been subject to judicial and Congressional challenges. In addition, there have been efforts by the Trump administration to repeal or replace certain aspects of the ACA and to alter the implementation of the ACA and related laws. It is unclear how the ACA and its implementation, as well as efforts to repeal or replace, or invalidate, the ACA, or portions thereof, will affect our business. Additional legislative changes, regulatory changes, and judicial challenges related to the ACA remain possible. While some uncertainty exists regarding the future aspects of the ACA, we expect that the ACA will continue to have a significant impact on the delivery of healthcare in the United States and on our business in the near term.
Physician Payments Sunshine Act. The Physician Payments Sunshine Act, implemented as the Open Payments program, requires manufacturers of drugs and devices for which payment is available under Medicare, Medicaid, or the Children’s Health Insurance Program (with certain exceptions) to report annually to CMS information related to direct or indirect payments and other transfers of value provided to physicians and teaching hospitals, as well as ownership and investment interests held by physician and their immediate family members. Beginning in 2022, applicable manufacturers also will be required to report information regarding payments and transfers of value provided to physician assistants, nurse practitioners, clinical nurse specialists, certified nurse anesthetists, and certified nurse-midwives. Our failure to disclose reportable payments could subject us to penalties and materially adversely impact our business and financial results.
Additionally, as these laws and regulations continue to evolve, we lack definitive guidance as to the application of certain key aspects of these laws and regulations as they relate to certain of our arrangements and programs, including those with providers with respect to patient training. We cannot predict the final form of these federal and state regulations or the effect that application of those interpretations will have on us. As a result, our provider and training arrangements may ultimately be found not to be in compliance with applicable federal law. Moreover, these laws continue to evolve. The Bipartisan Budget Act of 2018 increased the criminal and civil penalties that can be imposed for violating certain federal health care laws, including the Anti‑Kickback Statute. Most recently, on February 6, 2019, the United States Department of Health and Human Services’ Office of the Inspector General (“OIG”) issued a proposed rule to remove protection from the discount safe harbor to the federal healthcare Anti-Kickback Statute for manufacturers rebates to pharmacy benefit managers (or “PBMs”), Medicare Part D plans, and Medicaid managed care organizations (MCOs). The rule also proposes a new safe harbor for point-of sale-reductions offered by manufacturers to Part D plans, Medicaid MCOs and their PBMs, and a new safe harbor for certain fees manufacturers pay to PBMs for services to the manufacturers. If finalized, the rule will be one of the most significant amendments to the Anti-Kickback Statute regulatory safe harbors in decades and likely will transform manufacturer interactions with Part D plans, Medicaid MCOs and their PBMs.
Ensuring that our business arrangements and interactions with healthcare professionals, third‑party payors, patients and others comply with applicable healthcare laws and regulations requires substantial resources. Because of the breadth of these laws and the narrowness of the exceptions or safe harbors, it is possible that some of our business activities could be subject to challenge under one or more of such laws. Such a challenge could have a material adverse effect on our business, financial condition and results of operations. Even if we are not found to have violated the law, responding to lawsuits, government investigations or enforcement actions, defending any claims raised, and paying any resulting settlement amounts would be expensive and time-consuming, and could have a material adverse effect on our reputation and business operations.
Employees
As of December 31, 2018, we had 1,169 full-time employees. None of our employees are represented by a collective bargaining agreement, and we have never experienced any work stoppage. We believe that our employee relations are strong.
Company Information
Insulet Corporation is a Delaware corporation formed in 2000. Our principal office is located at 100 Nagog Park, Acton, Massachusetts, 01720 and our website address is http://www.insulet.com. We make available, free of charge, on or through our website, our annual reports on Form 10-K, quarterly reports on Form 10-Q, current reports on Form 8-K, proxy statements and any amendments to those reports filed or furnished pursuant to Section 13(a) or 15(d) of the Securities Exchange Act of 1934, as amended, as soon as reasonably practicable after such material is electronically filed with or furnished to the Securities and Exchange Commission. The information on our website is not part of this Annual Report on Form 10-K for the year ended December 31, 2018.
Previous: Cover and table of contents · Next: Item 1A. Risk Factors