 filings.tools
Universal Health Services (UHS) 10-K risk factor changes: FY2022 vs FY2021
The 2022-12-31 10-K against the 2021-12-31 one, compared heading by heading and sentence by sentence.
Item 1A79 rewritten47 added56 removed318 unchanged
All filing items1,573 rewritten937 added543 removed2,137 unchanged
Summary
counted, not written
- Item 1A headings could not be compared: only 3 carried over between the two years, which usually means one filing was read wrongly, so none is reported as new or removed.
- Sentence by sentence, 937 added, 543 removed, 1,573 rewritten and 2,137 unchanged across 23 items that differ.
Sentences by item
23 items, with every count and a link to each item that changed
Underlined words on a shaded ground are new in FY2022; struck-through words were in FY2021. Sentences that are wholly new or wholly gone are labelled rather than marked.
Item 1A. Risk Factors
79 rewritten, 47 added, 56 removed, 318 unchanged
[removed: Risks] [added: Risks] Related to Business [removed: Operations][added: Operations]
[removed: Texas:] [added: Texas:] We own 7 inpatient acute care [removed: hospitals] [added: hospitals, 12 free-standing emergency departments] and [removed: 22] [added: 21] inpatient behavioral healthcare facilities as listed in *Item 2.
On a combined basis, these facilities contributed [added: 17% and] 16% of our consolidated net revenues during [removed: each of 2021] [added: 2022] and [removed: 2020.][added: 2021, respectively.]
On a combined basis, after deducting an allocation for corporate overhead expense, these facilities generated [removed: 11%] [added: 27%] in [removed: 2021] [added: 2022] and 13% in [removed: 2020,] [added: 2021,] of our income from operations after net income attributable to noncontrolling interest.
[removed: Nevada:] [added: California:] We own [removed: 9] [added: 5] inpatient acute care [removed: hospitals] [added: hospitals, 2 acute outpatient centers, 8 inpatient behavioral healthcare facilities] and 3 [removed: inpatient] behavioral healthcare [added: outpatient] facilities as listed in *Item 2.
On a combined basis, these facilities contributed 17% [added: and 18%] of our consolidated net revenues during [removed: each of 2021] [added: 2022] and [removed: 2020.][added: 2021, respectively.]
On a combined basis, after deducting an allocation for corporate overhead expense, these facilities generated [removed: 22%] [added: 14%] in [removed: 2021] [added: 2022] and [removed: 17%] [added: 24%] in [removed: 2020,] [added: 2021,] of our income from operations after net income attributable to noncontrolling interest.
[removed: California:] [added: Nevada:] We own [removed: 5] [added: 10] inpatient acute care [removed: hospitals] [added: hospitals, 5 free-standing emergency departments, 1 acute outpatient center] and [removed: 8] [added: 3] inpatient behavioral healthcare facilities as listed in *Item 2.
On a combined basis, these facilities contributed 11% of our consolidated net revenues during each of [removed: 2021] [added: 2022] and [removed: 2020.][added: 2021.]
On a combined basis, after deducting an allocation for corporate overhead expense, these facilities generated [removed: 20% during each of 2021] [added: 15% in 2022] and [removed: 2020,] [added: 14% in 2021,] of our income from operations after net income attributable to noncontrolling interest.
[removed: Our] [added: Our] revenues and results of operations are significantly affected by payments received from the government and other third party [removed: payers.][added: payers.]
We receive annual Medicaid revenues of approximately $100 million, or greater, from each of Texas, California, Nevada, Illinois, Pennsylvania, Washington, D.C., [removed: Kentucky, Florida] [added: Florida, Kentucky] and Massachusetts.
We also receive Medicaid disproportionate share hospital payments [removed: in] [added: from] certain states [removed: including Texas and South Carolina.][added: including, most significantly, Texas.]
[removed: If] [added: If] we are not able to provide high quality medical care at a reasonable price, patients may choose to receive their health care from our [removed: competitors.][added: competitors.]
Additionally, the [removed: Legislation] [added: Patient Protection and Affordable Care Act (the “Legislation”)] requires all hospitals to annually establish, update and make public a list [added: of their standard charges for products and services.]
[removed: If any of our hospitals achieve poor] results on the quality measures or patient satisfaction surveys (or results that are lower than our competitors) or if our standard charges are higher than our competitors, our patient volume could decline because patients may elect to use competing hospitals or other health care providers that have better metrics and pricing.
[removed: An] [added: An] increase in uninsured and underinsured patients in our acute care facilities or the deterioration in the collectability of the accounts of such patients could harm our results of [removed: operations.][added: operations.]
[removed: Our] [added: Our] hospitals face competition for patients from other hospitals and health care [removed: providers.][added: providers.]
[removed: Our] [added: Our] performance depends on our ability to recruit and retain quality [removed: physicians.][added: physicians.]
If we are unable to [removed: provide] [added: maintain] high ethical and professional standards, adequate support personnel and technologically advanced equipment and facilities that meet the needs of those physicians, they may be discouraged from referring patients to our facilities and our results of operations may decline.
[removed: If our facilities do not stay current with] technological advances in the health care industry, patients may seek treatment from other providers and/or physicians may refer their patients to alternate sources, which could adversely affect our results of operations and harm our business.
[removed: Our] [added: Our] performance depends on our ability to attract and retain qualified nurses and medical support staff and we face competition for staffing that may increase our labor costs and harm our results of [removed: operations.][added: operations.]
The length and extent of the disruptions caused by the COVID‑19 pandemic are currently unknown; however, we expect such disruptions to continue into [removed: 2022 and potentially throughout] the [removed: duration of the pandemic and beyond.][added: future.]
[removed: The] [added: The] failure of certain employers, or the closure of certain facilities, could have a disproportionate impact on our [removed: hospitals.][added: hospitals.]
[removed: The] [added: The] trend toward value-based purchasing may negatively impact our [removed: revenues.][added: revenues.]
We expect value-based purchasing programs, including programs that condition reimbursement on patient outcome measures, [added: to become more common and to involve a higher percentage of reimbursement amounts.]
[removed: Controls] [added: Controls] designed to reduce inpatient services and increasing rates of “denials” may reduce our [removed: revenues.][added: revenues.]
[removed: We] [added: We] depend heavily on key management personnel and the departure of one or more of our key executives or a significant portion of our local hospital management personnel could harm our [removed: business.][added: business.]
Miller, our Founder, Chairman and Chief Executive Officer [removed: has] stepped down as Chief Executive Officer and Mr. Marc D.
[removed: Risks] [added: Risks] Related to the COVID-19 [removed: Pandemic][added: Pandemic]
[removed: COVID-19] [added: COVID-19] and other pandemics, epidemics, or public health threats may adversely affect our business, results of operations and financial [removed: condition.][added: condition.]
[removed: If facilities fail to comply] with the IFR by the deadlines established, they are subject to potential termination from the Medicare and Medicaid program for non-compliance.
Legal challenges to these rules ensued, and the U.S. Supreme Court [removed: has] upheld a stay of the ETS requirements but permitted the IFR vaccination requirements to go into effect pending additional litigation.
Hospitals in states that were involved in the Supreme Court litigation [removed: must now] [added: were required to] come into compliance with first dose requirements by February 13, 2022 and second dose requirements by March 15, 2022.
Hospitals in Texas [removed: must] [added: were required to] come into compliance with the first dose requirements by February 19, 2022 and the second dose requirements by March 21, [removed: 2022, due to the recent termination of separate litigation there.][added: 2022.]
We are not able to fully quantify the impact that these factors will have on our future financial results, but expect developments related to the COVID-19 pandemic to materially affect our financial performance [removed: in 2022.][added: for the foreseeable future.]
[removed: There] [added: There] is a high degree of uncertainty regarding the implementation and impact of the Coronavirus Aid, Relief, and Economic Security Act (the “CARES Act”) and the Paycheck Protection Program and Health Care Enhancement Act (“PPPHCE [removed: Act”).][added: Act”).]
[added: The CARES Act also makes other] forms of financial assistance available to healthcare providers, including through Medicare and Medicaid payment adjustments and an expansion of the Medicare Accelerated and Advance Payment Program, which makes available accelerated payments of Medicare funds in order to increase cash flow to providers.
[removed: Risks] [added: Risks] Related to the Regulatory [removed: Environment][added: Environment]
[removed: Reductions] [added: Reductions] or changes in Medicare and Medicaid funding could have a material adverse effect on our future results of [removed: operations.][added: operations.]
Excluding the impact of the $57.6 million provision for asset impairment recorded during 2022, as discussed in *Item 7.
Management's Discussion and Analysis of Financial Condition and Results of Operations - Provision for Asset Impairments,* after deducting an allocation for corporate overhead expense, these facilities generated 18% of our income from operations after net income attributable to noncontrolling interest during 2022.
If any of our hospitals achieve poor
If our facilities do not stay current with
The length and extent of the disruptions caused by the COVID‑19 pandemic are currently unknown; however, we expect such disruptions to continue for the foreseeable future.
If these states increase mandatory nurse-staffing ratios or additional states in which we operate adopt mandatory nurse-staffing ratios, such changes could significantly affect labor costs and have an adverse impact on revenues if we are required to limit admissions in order to meet the required ratios.
The impact of the COVID-19 pandemic, which began during the second half of March, 2020, has had a material effect on our operations and financial results since that time.
Since the future volumes and severity of COVID-19 patients remain highly uncertain and subject to change, including potential increases in future COVID-19 patient volumes caused by new variants of the virus, as well as related pressures on staffing and wage rates, we are not able to fully quantify the impact that these factors will have on our future financial results.
However, developments related to the COVID-19 pandemic could continue to materially affect our financial performance.
The healthcare industry is labor intensive and salaries, wages and benefits are subject to inflationary pressures, as are supplies expense and other operating expenses.
Our ability to pass on increased costs associated with providing healthcare to Medicare and Medicaid patients is limited due to various federal, state and local laws which, in certain circumstances, limit our ability to increase prices.
In addition, the nationwide shortage of nurses and other clinical staff and support personnel has been a significant operating issue facing us and other healthcare providers.
Like others in the healthcare industry, we continue to experience a shortage of nurses and other clinical staff and support personnel at our acute care and behavioral health care hospitals in many geographic areas.
In some areas, the labor scarcity is putting a strain on our resources and staff, which has required us to utilize higher‑cost temporary labor and pay premiums above standard compensation for essential workers.
This staffing shortage has required us to hire expensive temporary personnel and/or enhance wages and benefits to recruit and retain nurses and other clinical staff and support personnel.
At certain facilities, particularly within our behavioral health care segment, we have been unable to fill all vacant positions and, consequently, have been required to limit patient volumes.
These factors, which had a material unfavorable impact on our results of operations during 2022, have been moderating to a certain degree but are expected to continue to have an unfavorable material impact on our results of operations for the foreseeable future.
If facilities fail to comply
If general economic conditions, including inflation, deteriorate or remain volatile or uncertain for an extended period of time, our liquidity and ability to repay our outstanding debt may be harmed and the trading price of our common stock could decline.
These factors may affect the availability, terms or timing on which we may obtain any additional funding.
There can be no assurance that we will be able to raise additional funds on terms acceptable to us, if at all.
We are not able to fully quantify the impact that these factors will have on our future financial results, but expect developments related to the COVID-19 pandemic to materially affect our financial performance for the foreseeable future.
HHS had adopted certain reimbursement policies and regulatory flexibilities favorable to providers during the Public Health Emergency (“PHE”) declared in response to the COVID-19 pandemic.
HHS has published guidance indicating its intent for the PHE to expire on May 11, 2023.
The end of the PHE status will result in the conclusion of those policies over various designated timeframes.
We cannot predict whether the loss of any such favorable conditions available to providers during the declared PHE will ultimately have a negative financial impact on us.
The most recent legislation extended these reductions through 2032.
of the Legislation.
On September 7, 2022, the same Texas Federal District Court judge, in the case of *Braidwood Management v.
Becerra*, ruled that the requirement that certain health plans cover services with an “A” or “B” recommendation from the U.S. Preventive Services Task Force without cost sharing violates the Appointments Clause of the U.S. Constitution and that the coverage of certain HIV prevention medication violates the Religious Freedom Restoration Act.
We are unable to predict the outcome of this litigation or its potential impact at this time.
On March 11, 2021, President Biden signed the American Rescue Plan (“ARP”) into law.
The ARP extends eligibility for Legislation health insurance subsidies to people buying their own health coverage on the Marketplace who have household incomes above 400% of the federal poverty level.
ARP also increased the amount of financial assistance for people at lower incomes who were already eligible under the Legislation.
The Inflation Reduction Act of 2022 (“IRA”) was passed on August 16, 2022, which among other things, allows for CMS to negotiate prices for certain single-source drugs and biologics reimbursed under Medicare Part B and Part D, beginning with 10 high-cost drugs paid for by Medicare Part D starting in 2026, followed by 15 Part D drugs in 2027, 15 Part B or Part D drugs in 2028, and 20 Part B or Part D drugs in 2029 and beyond.
The IRA also continued the expanded subsidies for individuals to obtain private health insurance under the Legislation through 2025.
The effect of IRA on hospitals and the healthcare industry in general is not yet known.
The failure of certain employers, or the closure of certain facilities, could have a disproportionate impact on our hospitals.
weather conditions or natural disasters or other changes to weather patterns, all of which may result in physical damage to or a decrease in demand for properties affected by these conditions.
The increase in interest rates has substantially increased our borrowing costs and reduced our ability to access the capital markets on favorable terms.
| --- | --- |
Effective January, 2020, United/Sierra Healthcare in Las Vegas, entered into an agreement with a competitor health system that was previously excluded from their contractual network in the area.
As a result, we believe that our 6 acute care hospitals in the Las Vegas, Nevada market, will likely experience a decline in patient volumes.
However, we have entered into an amended agreement with United/Sierra Healthcare related to our hospitals in the Las Vegas market that provided for various rate increases that began in January, 2020.
Although we estimate that the unfavorable impact of the projected declines in patient volumes should be largely offset by the favorable impact of the increased rates, we can provide no assurance that these developments on the Las Vegas market, will not have a material adverse impact on our future results of operations.
The significant portion of our revenues and earnings derived from these facilities makes us particularly sensitive to legislative, regulatory, economic, environmental and competition changes in Texas, Nevada and California.
Any material change in the current payment programs or regulatory, economic, environmental or competitive conditions in these states could have a disproportionate effect on our overall business results.
of their standard charges for products and services.
to become more common and to involve a higher percentage of reimbursement amounts.
We are subject to risks associated with public health threats and epidemics, including the health concerns relating to the COVID-19 pandemic.
In January 2020, the Centers for Disease Control and Prevention (“CDC”) confirmed the spread of the disease to the United States.
In March 2020, the World Health Organization declared the COVID-19 outbreak a pandemic.
The federal government has declared COVID-19 a national emergency, as many federal and state authorities have implemented aggressive measures to “flatten the curve” of confirmed individuals diagnosed with COVID-19 in an attempt to curtail the spread of the virus and to avoid overwhelming the health care system.
The COVID-19 pandemic has adversely impacted and is likely to further adversely impact us, our employees, our patients, our vendors and supply chain partners, and financial institutions, which could continue to have a material adverse effect on our business, results of operations and financial condition.
In an effort to slow the spread of the disease, since March, 2020, at various times, most state and local governments mandated general “shelter-in-place” orders or other similar restrictions that require or strongly encourage social distancing and, face coverings, and that have closed or limited non-essential business activities.
Some of these restrictions remain in place.
Additionally, evidence suggests that individuals to deciding to forego medical care delivered in traditional venues.
These dynamics have manifested themselves in our hospitals in, among other ways, reduced emergency room visits, elective/scheduled procedures and acute and behavioral health patient days.
While such measures are expected to assist in responding to the recent outbreak, self-quarantines, shelter-in-place orders, and suspension of voluntary procedures and surgeries have had, and will likely continue to have, an adverse impact on the operations and financial position of health care provider systems due to increased costs (including labor costs which have been pressured during the COVID-19 pandemic due to a shortage of clinicians and increased wage rates due to increased demand for those services), actual reduction and potential reduction in overall patient volume, and shifts in payor mix.
Despite these measures, there have been waves of escalated COVID-19 cases at various times, including the fourth quarter of 2020 and into the first quarter of 2021, as well as the fourth quarter of 2021 and into the first quarter of 2022, in many states in the U.S., including many states in which we operate hospitals.
Since the first quarter of 2021, COVID-19 vaccinations have begun to be administered.
Since that time, through the second quarter of 2021, we had generally experienced a decline in COVID-19 patients as well as a corresponding recovery in non-COVID-19 patient activity.
However, during the third quarter of 2021, our facilities generally experienced an increase in COVID-19 patients resulting primarily from the Delta variant.
Also, since late in 2021, the newly discovered and highly transmissible Omicron variant has resulted in an increase in COVID-19 infections.
Since the third quarter of 2021, booster doses for COVID-19 vaccination have begun to be administered, and while we expect the administration of booster doses to assist in easing the number of COVID-19 patients, the pace at which this is likely to occur is difficult to predict.
The CARES Act also makes other
parameters; such hospitals will include those with excessive readmission or hospital-acquired condition rates.
In addition to legislative changes, the Legislation can be significantly impacted by executive branch actions.
President Biden is expected to undertake executive actions that will strengthen the Legislation and may reverse the policies of the prior administration.
The Trump Administration had directed the issuance of final rules (i) enabling the formation of association health plans that would be exempt from certain Legislation requirements such as the provision of essential health benefits; (ii) expanding the availability of short-term, limited duration health insurance, (iii) eliminating cost-sharing reduction payments to insurers that would otherwise offset deductibles and other out-of-pocket expenses for health plan enrollees at or below 250 percent of the federal poverty level; (iv) relaxing requirements for state innovation waivers that could reduce enrollment in the individual and small group markets and lead to additional enrollment in short-term, limited duration insurance and association health plans; and (v) incentivizing the use of health
reimbursement accounts by employers to permit employees to purchase health insurance in the individual market.
The uncertainty resulting from these Executive Branch policies has led to reduced Exchange enrollment in 2018, 2019 and 2020 is expected to further worsen the individual and small group market risk pools in future years.
It is also anticipated that these policies may create additional cost and reimbursement pressures on hospitals.
The case was appealed to the U.S. Court of Appeals for the Fifth Circuit and on December 18, 2019, a three-judge panel declared the Legislation’s individual mandate unconstitutional and remanded the case back to the Texas Federal District Court to determine which of the Legislation’s provisions should be stricken with the mandate or whether the entire law is unconstitutional without the individual mandate.
As a result, the Legislation will continue to remain law, in its entirety, likely for the foreseeable future.
decrease in demand for properties affected by these conditions.
The phase-out of LIBOR on January 1, 2022 and June 30, 2023.
In 2017, the U.K. Financial Conduct Authority (“FCA”) that regulates LIBOR announced it intends to phase out LIBOR and stop compelling banks to submit rates for its calculation.
In 2021, the FCA further announced that effective January 1, 2022, the one week and two-month USD LIBOR tenors are no longer being published, and all other USD LIBOR tenors will cease to be published after June 30, 2023.
The Federal Reserve Board and the Federal Reserve Bank of New York organized the Alternative Reference Rates Committee which identified the Secured Overnight Financing Rate ("SOFR") as its preferred alternative to USD-LIBOR in derivatives and other financial contracts.
An excerpt. Shown here: 40 of 79 rewritten, 40 of 47 added and 40 of 56 removed. The counts are complete. For every sentence, read Item 1A. Risk Factors in the FY2022 filing and the FY2021 filing.
Item 7. Management’s Discussion and Analysis of Financial Condition and Results of Operations
446 rewritten, 445 added, 204 removed, 396 unchanged
This section generally discusses our results of operations for the year ended December 31, [removed: 2021] [added: 2022,] as compared to the year ended December 31, [removed: 2020.][added: 2021.]
[removed: For discussion of our result of operations and changes in our financial condition for the year ended December 31, 2020 as compared to the year ended December 31, 2019, please refer to *Part II,] Management’s Discussion and Analysis of Financial Condition and Results of Operations* in our Annual Report on Form 10-K for the year ended December 31, [removed: 2020,] [added: 2021,] as filed with the Securities and Exchange Commission on February [removed: 25, 2021.][added: 24, 2022.]
[removed: Overview][added: Overview]
As of February [removed: 24, 2022,] [added: 27, 2023,] we owned and/or operated [removed: 363] [added: 359] inpatient facilities and [removed: 40] [added: 39] outpatient and other facilities including the following located in 39 states, Washington, D.C., the United Kingdom and Puerto Rico:
[removed: Acute] [added: Acute] care facilities located in the [removed: U.S.:][added: U.S.:]
[removed: | | • | 19] [added: 21] free-standing emergency departments, and; [removed: |]
[removed: | | • | 6] [added: 7] outpatient centers & 1 surgical hospital. [removed: |]
[removed: Behavioral] [added: Behavioral] health care facilities [removed: (335] [added: (331] inpatient facilities and [removed: 14] [added: 10] outpatient [removed: facilities):][added: facilities):]
[removed: Located] [added: Located] in the [removed: U.S.:][added: U.S.:]
[removed: | | • | 187] [added: 185] inpatient behavioral health care facilities, and; [removed: |]
[removed: | | • | 12] [added: 8] outpatient behavioral health care facilities. [removed: |]
[removed: Located] [added: Located] in the [removed: U.K.:][added: U.K.:]
[removed: | | • | 145] [added: 143] inpatient behavioral health care facilities, and; [removed: |]
[removed: | | • |] 2 outpatient behavioral health care facilities. [removed: |]
[removed: Located] [added: Located] in Puerto [removed: Rico:][added: Rico:]
[removed: | | • |] 3 inpatient behavioral health care facilities. [removed: |]
Net revenues from our acute care hospitals, outpatient facilities and commercial health insurer accounted for [removed: 56%] [added: 57%] of our consolidated net revenues during [removed: 2021] [added: 2022] and [removed: 55%] [added: 56%] during [removed: 2020.][added: 2021.]
Net revenues from our behavioral health care facilities and commercial health insurer accounted for [removed: 44%] [added: 43%] of our consolidated net revenues during [removed: 2021] [added: 2022] and [removed: 45%] [added: 44%] during [removed: 2020.][added: 2021.]
Our behavioral health care facilities located in the U.K. generated net revenues of approximately [removed: $688] [added: $685] million in [removed: 2021] [added: 2022] and [removed: $584] [added: $688] million in [removed: 2020.][added: 2021.]
Total assets at our U.K. behavioral health care facilities were approximately [removed: $1.351] [added: $1.235] billion as of December 31, [removed: 2021] [added: 2022] and [removed: $1.334] [added: $1.351] billion as of December 31, [removed: 2020.][added: 2021.]
[removed: Forward-Looking] [added: Forward-Looking] Statements and Risk [removed: Factors][added: Factors]
You should carefully review the information contained in this Annual Report, and should particularly consider any risk factors that we set forth in this Annual Report on Form 10-K for the year ended December 31, [removed: 2021,] [added: 2022,] and in other reports or documents that we file from time to time with the Securities and Exchange Commission (the “SEC”).
strategies, financing plans, expectations that regulatory developments or other matters will [added: or will] not have a material adverse effect on our business or financial condition, our competitive position and the effects of competition, the projected growth of the industry in which we operate, and the benefits and synergies to be obtained from our completed and any future acquisitions, and statements of our goals and objectives, and other similar expressions concerning matters that are not historical facts.
Words such as “may,” “will,” “should,” “could,” “would,” “predicts,” “potential,” “continue,” “expects,” “anticipates,” “future,” “intends,” “plans,” “believes,” “estimates,” “appears,” “projects” and similar expressions, [added: or the negative of those words and expressions,] as well as statements in future tense, identify forward-looking statements.
Forward-looking information is based on information available at the time and/or our good faith belief with respect to future events, and is subject to risks and uncertainties that [removed: could cause actual performance or results] [added: are difficult] to [removed: differ materially from those expressed in the statements.][added: predict and many of which are outside of our control.]
[removed: | | • | we are subject to risks associated with public health threats and epidemics, including the health concerns relating to the COVID-19 pandemic. In January 2020, the Centers for Disease Control and Prevention (“CDC”) confirmed the spread of the disease to the United States. In March 2020, the World Health Organization declared the COVID-19 outbreak a pandemic.] The federal government has declared COVID-19 a national emergency, as many federal and state authorities have implemented aggressive measures to “flatten the curve” of confirmed individuals diagnosed with COVID-19 in an attempt to curtail the spread of the virus and to avoid overwhelming the health care system; [removed: |]
[removed: | | • |] the Centers for Medicare and Medicaid Services (“CMS”) issued an Interim Final Rule (“IFR”) effective November 5, 2021 mandating COVID-19 vaccinations for all applicable staff at all Medicare and Medicaid certified facilities. [removed: Under the IFR, facilities covered by this regulation must establish a policy ensuring all eligible staff have received the first dose |]
[removed: | | • |] our ability to comply with the existing laws and government regulations, and/or changes in laws and government regulations; [removed: |]
[removed: | | • | under the Legislation, hospitals are required to make public a list of their standard charges, and effective January 1, 2019, CMS has required that this disclosure be in machine-readable format and include charges for all hospital items and services and average charges for diagnosis-related groups.] On November 27, 2019, CMS published a final rule on “Price Transparency Requirements for Hospitals to Make Standard Charges Public.” This rule took effect on January 1, 2021 and requires all hospitals to also make public their [removed: payor-specific] [added: payer-specific] negotiated rates, minimum negotiated rates, maximum negotiated rates, and [added: discounted] cash [added: rates,] for all items and services, including individual items and services and service packages, that could be provided by a hospital to a patient. [removed: Failure to comply with these requirements may result in daily monetary penalties. On November 2, 2021, CMS released a final rule amending several hospital price transparency policies and increasing the amount of penalties for noncompliance through the use of a scaling factor based on hospital bed count; |]
[removed: | | • |] possible unfavorable changes in the levels and terms of reimbursement for our charges by third party payers or government based payers, including Medicare or Medicaid in the United States, and government based payers in the United Kingdom; [removed: |]
[removed: | | • |] our ability to enter into managed care provider agreements on acceptable terms and the ability of our competitors to do the same; [removed: |]
[removed: | | • |] the outcome of known and unknown litigation, government investigations, false claims act allegations, and liabilities and other claims asserted against us and other matters as disclosed in *Note [removed: 6] [added: 8] to the Consolidated Financial Statements - Commitments and Contingencies* and the effects of adverse publicity relating to such matters*;* [removed: |]
[removed: | | • |] competition from other healthcare providers (including physician owned facilities) in certain markets; [removed: |]
[removed: | | • |] technological and pharmaceutical improvements that increase the cost of providing, or reduce the demand for healthcare; [removed: |]
[removed: | | • |] our ability to attract and retain qualified personnel, nurses, physicians and other healthcare professionals and the impact on our labor expenses resulting from a shortage of nurses and other healthcare professionals; [removed: |]
[removed: | | • |] demographic changes; [removed: |]
[removed: | | • |] the availability of suitable acquisition and divestiture opportunities and our ability to successfully integrate and improve our acquisitions since failure to achieve expected acquisition benefits from certain of our prior or future acquisitions could result in impairment charges for goodwill and purchased intangibles; [removed: |]
[removed: | | • |] the impact of severe weather conditions, including the effects of hurricanes and climate change; [removed: |]
[removed: | | • |] our ability to continue to obtain capital on acceptable terms, including borrowed funds, to fund the future growth of our business; [removed: |]
[removed: | | • |] our inpatient acute care and behavioral health care facilities may experience decreasing admission and length of stay trends; [removed: |]
For discussion of our result of operations and changes in our financial condition for the year ended December 31, 2021 as compared to the year ended December 31, 2020, please refer to *Part II, Item 7.
28 inpatient acute care hospitals;
Many factors, including those set forth herein in *Item 1A.
Risk Factors*, and other important factors disclosed in this report, and from time to time in our other filings with the SEC, could cause actual performance or results to differ materially from those expressed in the statements.
we are subject to risks associated with public health threats and epidemics, including the health concerns relating to the COVID-19 pandemic.
In January 2020, the Centers for Disease Control and Prevention (“CDC”) confirmed the spread of the disease to the United States.
In March 2020, the World Health Organization declared the COVID-19 outbreak a pandemic.
the impact of the COVID-19 pandemic, which began during the second half of March, 2020, has had a material effect on our operations and financial results since that time.
Since the future volumes and severity of COVID-19 patients remain highly uncertain and subject to change, including potential increases in future COVID-19 patient volumes caused by new variants of the virus, as well as related pressures on staffing and wage rates, we are not able to fully quantify the impact that these factors will have on our future financial results.
However, developments related to the COVID-19 pandemic could continue to materially affect our financial performance.
Even after the COVID-19 pandemic has subsided, we may continue to experience materially adverse impacts on our financial condition and our results of operations as a result of its macroeconomic impact, including the risks of a global recession or a recession in one or more of our key markets, the impact they may have on us and our customers and our assessment of that impact, and any disruptions and inefficiencies in the supply chain, and many of our known risks described in the *Risk Factors* section of our Annual Report on Form 10-K for the year ended December 31, 2022;
This staffing shortage has required us to hire expensive temporary personnel and/or enhance wages and benefits to recruit and retain nurses and other clinical staff and support personnel.
At certain facilities, particularly within our behavioral health care segment, we have been unable to fill all vacant positions and, consequently, have been required to limit patient volumes.
These factors, which had a material unfavorable impact on our results of operations during 2022, are expected to continue to have an unfavorable material impact on our results of operations for the foreseeable future;
Under the IFR, facilities covered by this regulation must establish a policy ensuring all eligible staff have received the COVID-19 vaccine prior to providing any care, treatment, or other services.
All eligible staff must have received the necessary shots to be fully vaccinated.
The regulation also provides for exemptions based on recognized medical conditions or religious beliefs, observances, or practices.
Under the IFR, facilities must develop a similar process or plan for permitting exemptions in alignment with federal law.
If facilities fail to comply with the IFR by the deadlines established, they are subject to potential termination from the Medicare and Medicaid program for non-compliance.
We cannot predict at this time the potential viability or impact of any additional vaccination requirements.
Implementation of these rules could have an impact on staffing at our facilities for those employees that are not vaccinated in accordance with IFR requirements, and associated loss of revenues and increased costs resulting from staffing issues could have a material adverse effect on our financial results;
the Coronavirus Aid, Relief, and Economic Security Act (the “CARES Act”), a stimulus package signed into law on March 27, 2020, authorizes $100 billion in grant funding to hospitals and other healthcare providers to be distributed through the Public Health and Social Services Emergency Fund (the “PHSSEF”).
These funds are not required to be repaid provided the recipients attest to and comply with certain terms and conditions, including limitations on balance billing and not using PHSSEF funds to reimburse expenses or losses that other sources are obligated to reimburse.
However, since the expenses and losses will be ultimately measured over the life of the COVID-19 pandemic, potential retrospective unfavorable adjustments in future periods, of funds recorded as revenues in prior periods, could occur.
The U.S. Department of Health and Human Services (“HHS”) initially distributed $30 billion of this funding based on each provider’s share of total Medicare fee-for-service reimbursement in 2019.
Subsequently, HHS determined that CARES Act funding (including the $30 billion already distributed) would be allocated proportional to providers’ share of 2018 net patient revenue.
We have received payments from these initial distributions of the PHSSEF as disclosed herein.
HHS has indicated that distributions of the remaining $50 billion will be targeted primarily to hospitals in COVID-19 high impact areas, to rural providers, safety net hospitals and certain Medicaid providers and to reimburse providers for COVID-19 related treatment of uninsured patients.
We have received payments from these targeted distributions of the PHSSEF, as disclosed herein.
The CARES Act also makes other forms of financial assistance available to healthcare providers, including through Medicare and Medicaid payment adjustments and an expansion of the Medicare Accelerated and Advance Payment Program, which made available accelerated payments of Medicare funds in order to increase cash flow to providers.
On April 26, 2020, CMS announced it was reevaluating and temporarily suspending the Medicare Accelerated and Advance Payment Program in light of the availability of the PHSSEF and the significant funds available through other programs.
We have received accelerated payments under this program during 2020, and returned early all of those funds during the first quarter of 2021, as disclosed herein.
The Paycheck Protection Program and Health Care Enhancement Act (the “PPPHCE Act”), a stimulus package signed into law on April 24, 2020, includes additional emergency appropriations for COVID-19 response, including $75 billion to be distributed to eligible providers through the PHSSEF.
A third phase of PHSSEF allocations made $24.5 billion available for providers who previously received, rejected or accepted PHSSEF payments.
Applicants that had not yet received PHSSEF payments of 2 percent of patient revenue were to receive a payment that, when combined with prior payments (if any), equals 2 percent of patient care revenue.
Providers that have already received payments of approximately 2 percent of annual revenue from patient care were potentially eligible for an additional payment.
Recipients will not be required to repay the government for PHSSEF funds received, provided they comply with HHS defined terms and conditions.
On December 27, 2020, the Consolidated Appropriations Act, 2021 (“CAA”) was signed into law.
The CAA appropriated an additional $3 billion to the PHSSEF, codified flexibility for providers to calculate lost revenues, and permitted parent organizations to allocate PHSSEF targeted distributions to subsidiary organizations.
The CAA also provides that not less than 85 percent of the unobligated PHSSEF amounts and any future funds recovered from health care providers should be used for additional distributions that consider financial losses and changes in operating expenses in the third or fourth quarters of 2020 and the first quarter of 2021 that are attributable to the coronavirus.
| --- | --- |
| | • | 28 inpatient acute care hospitals (including a newly constructed, 170-bed hospital located in Reno, Nevada, that is scheduled to be completed and opened during the first quarter of 2022); |
| --- | --- | --- |
| | • | the impact of the COVID-19 pandemic, which began during the second half of March, 2020, has had a material effect on our operations and financial results since that time. The COVID-19 vaccination process commenced during the first quarter of 2021. Since that time through the second quarter of 2021, we had generally experienced a decline in COVID-19 patients as well as a corresponding recovery in non-COVID patient activity. However, during the third and fourth quarters of 2021, and continuing into the first quarter of 2022, our facilities generally experienced an increase in COVID-19 patients resulting from the Delta and, more recently, the highly transmissible Omicron variants. Booster doses for COVID-19 vaccinations began during the third quarter of 2021, and while we expect the administration of vaccines booster doses will assist in easing the number of COVID-19 patients, the pace at which this is likely to occur is very difficult to predict. Also, the COVID-19 pandemic has led to a constrained supply environment which could result in higher cost to procure, and potential unavailability of, critical personal protection equipment, pharmaceuticals and medical supplies. Should a supply disruption result in the inability to obtain especially high margin drugs and compound components necessary for patient care, our consolidated financial statements could be negatively impacted. As of December 31, 2021, we have not experienced a significant impact in the availability of supplies from the COVID-19 pandemic. Since the future volumes and severity of COVID-19 patients remain highly uncertain and subject to change, including potential increases in future COVID-19 patient volumes caused by new variants of the virus, as well as related pressures on staffing and wage rates and the strained supply environment, we are not able to fully quantify the impact that these factors will have on our future financial results. However, developments related to the COVID-19 pandemic could materially affect our financial performance during 2022. Even after the COVID-19 pandemic has subsided, we may continue to experience materially adverse impacts on our financial condition and our results of operations as a result of its macroeconomic impact, and many of our known risks described in the *Risk Factors* section of our Annual Report on Form 10-K for the year ended December 31, 2021; |
| | • | the nationwide shortage of nurses and other clinical staff and support personnel has been a significant operating issue facing us and other healthcare providers. In particular, like others in the healthcare industry, we continue to experience a shortage of nurses and other clinical staff and support personnel at our acute care and behavioral health care hospitals in many geographic areas, which shortage has been exacerbated by the COVID‑19 pandemic. We are treating patients with COVID‑19 in our facilities and, in some areas, the increased demand for care is putting a strain on our resources and staff, which has required us to utilize higher‑cost temporary labor and pay premiums above standard compensation for essential workers. The length and extent of the disruptions caused by the COVID‑19 pandemic are currently unknown; however, we expect such disruptions to continue into 2022 and potentially throughout the duration of the pandemic and beyond. This staffing shortage may require us to further enhance wages and benefits to recruit and retain nurses and other clinical staff and support personnel or require us to hire expensive temporary personnel. To the extent we cannot maintain sufficient staffing levels at our hospitals, we may be required to limit the acute and behavioral health care services provided at certain of our hospitals which would have a corresponding adverse effect on our net revenues. In addition, in some markets like California, there are requirements to maintain specified nurse-staffing levels which could adversely affect our net revenues to the extent we cannot meet those levels; |
| | | of a two-dose COVID-19 vaccine or a one-dose COVID-19 vaccine prior to providing any care, treatment, or other services by December 5, 2021. All eligible staff must have received the necessary shots to be fully vaccinated – either two doses of Pfizer or Moderna or one dose of Johnson & Johnson – by January 4, 2022. The regulation also provides for exemptions based on recognized medical conditions or religious beliefs, observances, or practices. Under the IFR, facilities must develop a similar process or plan for permitting exemptions in alignment with federal law. If facilities fail to comply with the IFR by the deadlines established, they are subject to potential termination from the Medicare and Medicaid program for non-compliance. In addition, the Occupational Safety and Health Administration also issued an Emergency Temporary Standard (“ETS”) requiring all businesses with 100 or more employees to be vaccinated by January 4, 2022. Pursuant to the ETS, those employees not vaccinated by that date will need to show a negative COVID-19 test weekly and wear a face mask in the workplace. Legal challenges to these rules ensued, and the U.S. Supreme Court has upheld a stay of the ETS requirements but permitted the IFR vaccination requirements to go into effect pending additional litigation. CMS has indicated that hospitals in states not involved in the Supreme Court litigation are expected to be in compliance with IFR vaccination requirements consistent with the dates referenced above. Hospitals in states that were involved in the Supreme Court litigation must now come into compliance with first dose requirements by February 13, 2022 and second dose requirements by March 15, 2022. Hospitals in Texas must come into compliance with first dose requirements by February 19, 2022 and second dose requirements by March 21, 2022 due to the recent termination of separate litigation. We cannot predict at this time the potential viability or impact of any such additional litigation. Implementation of these rules could have an impact on staffing at our facilities for those employees that are not vaccinated in accordance with IFR and ETS requirements, and associated loss of revenues and increased costs resulting from staffing issues could have a material adverse effect on our financial results; |
| | • | the Coronavirus Aid, Relief, and Economic Security Act (the “CARES Act”), a stimulus package signed into law on March 27, 2020, authorizes $100 billion in grant funding to hospitals and other healthcare providers to be distributed through the Public Health and Social Services Emergency Fund (the “PHSSEF”). These funds are not required to be repaid provided the recipients attest to and comply with certain terms and conditions, including limitations on balance billing and not using PHSSEF funds to reimburse expenses or losses that other sources are obligated to reimburse. However, since the expenses and losses will be ultimately measured over the life of the COVID-19 pandemic, potential retrospective unfavorable adjustments in future periods, of funds recorded as revenues in prior periods, could occur. The U.S. Department of Health and Human Services (“HHS”) initially distributed $30 billion of this funding based on each provider’s share of total Medicare fee-for-service reimbursement in 2019. Subsequently, HHS determined that CARES Act funding (including the $30 billion already distributed) would be allocated proportional to providers’ share of 2018 net patient revenue. We have received payments from these initial distributions of the PHSSEF as disclosed herein. HHS has indicated that distributions of the remaining $50 billion will be targeted primarily to hospitals in COVID-19 high impact areas, to rural providers, safety net hospitals and certain Medicaid providers and to reimburse providers for COVID-19 related treatment of uninsured patients. We have received payments from these targeted distributions of the PHSSEF, as disclosed herein. The CARES Act also makes other forms of financial assistance available to healthcare providers, including through Medicare and Medicaid payment adjustments and an expansion of the Medicare Accelerated and Advance Payment Program, which made available accelerated payments of Medicare funds in order to increase cash flow to providers. On April 26, 2020, CMS announced it was reevaluating and temporarily suspending the Medicare Accelerated and Advance Payment Program in light of the availability of the PHSSEF and the significant funds available through other programs. We have received accelerated payments under this program during 2020, and returned early all of those funds during the first quarter of 2021, as disclosed herein. The Paycheck Protection Program and Health Care Enhancement Act (the “PPPHCE Act”), a stimulus package signed into law on April 24, 2020, includes additional emergency appropriations for COVID-19 response, including $75 billion to be distributed to eligible providers through the PHSSEF. A third phase of PHSSEF allocations made $24.5 billion available for providers who previously received, rejected or accepted PHSSEF payments. Applicants that had not yet received PHSSEF payments of 2 percent of patient revenue were to receive a payment that, when combined with prior payments (if any), equals 2 percent of patient care revenue. Providers that have already received payments of approximately 2 percent of annual revenue from patient care were potentially eligible for an additional payment. Recipients will not be required to repay the government for PHSSEF funds received, provided they comply with HHS defined terms and conditions. On December 27, 2020, the Consolidated Appropriations Act, 2021 (“CAA”) was signed into law. The CAA appropriated an additional $3 billion to the PHSSEF, codified flexibility for providers to calculate lost revenues, and permitted parent organizations to allocate PHSSEF targeted distributions to subsidiary organizations. The CAA also provides that not less than 85 percent of the unobligated PHSSEF amounts and any future funds recovered from health care providers should be used for additional distributions that consider financial losses and changes in operating expenses in the third or fourth quarters of 2020 and the first quarter of 2021 that are attributable to the coronavirus. The CAA provided additional funding for testing, contact tracing and vaccine administration. Providers receiving payments were required to sign terms and conditions regarding utilization of the payments. Any provider receiving funds in excess of $10,000 in the aggregate will be required to report data elements to HHS detailing utilization of the payments, and we will be required to file such reports. We, and other providers, will report healthcare related expenses attributable to COVID-19 that have not been reimbursed by another source, which may include general and administrative or healthcare related operating expenses. Funds may also be applied to lost revenues, represented as a negative change in year-over-year net patient care operating income. The deadline for using all Provider |
| | | Relief Fund payments depends on the date of the payment received period; payments received in the first period of April 10, 2020 to June 30, 2020 were to have been expended by June 30, 2021 and payments received in the fourth period of July 1, 2021 to December 31, 2021 must be expended by December 31, 2022. The American Rescue Plan Act of 2021 (“ARPA”), enacted on March 11, 2021, included funding directed at detecting, diagnosing, tracing, and monitoring COVID-19 infections; establishing community vaccination centers and mobile vaccine units; promoting, distributing, and tracking COVID-19 vaccines; and reimbursing rural hospitals and facilities for healthcare-related expenses and lost revenues attributable to COVID-19. ARPA increased the eligibility for, and amount of, premium tax credits to purchase health coverage through Patient Protection and Affordable Care Act, as amended by the Health and Education Reconciliation Act (collectively, the “Legislation”). Further, ARPA set the Medicaid program’s federal medical assistance percentage (“FMAP”) at 100 percent for amounts expended for COVID-19 vaccines and vaccine administration. ARPA also increases the FMAP by 5 percent for eight calendar quarters to incentivize states to expand their Medicaid programs. Finally, ARPA provides subsidies to cover 100 percent of health insurance premiums under the Consolidated Omnibus Budget Reconciliation Act through September 30, 2021. There is a high degree of uncertainty surrounding the implementation of the CARES Act, the PPPHCE Act, the CAA and ARPA, and the federal government may consider additional stimulus and relief efforts, but we are unable to predict whether additional stimulus measures will be enacted or their impact. There can be no assurance as to the total amount of financial and other types of assistance we will receive under the CARES Act, the PPPHCE Act, the CAA and the ARPA, and it is difficult to predict the impact of such legislation on our operations or how they will affect operations of our competitors. Moreover, we are unable to assess the extent to which anticipated negative impacts on us arising from the COVID-19 pandemic will be offset by amounts or benefits received or to be received under the CARES Act, the PPPHCE Act, the CAA and the ARPA; |
| | • | an increasing number of legislative initiatives have been passed into law that may result in major changes in the health care delivery system on a national or state level. For example, Congress has reduced to $0 the penalty for failing to maintain health coverage that was part of the original Legislation as part of the Tax Cuts and Jobs Act. President Biden has undertaken and is expected to undertake additional executive actions that will strengthen the Legislation and reverse the policies of the prior administration. To date, the Biden administration has issued executive orders implementing a special enrollment period permitting individuals to enroll in health plans outside of the annual open enrollment period and reexamining policies that may undermine the Legislation or the Medicaid program. The ARPA’s expansion of subsidies to purchase coverage through a Legislation exchange is anticipated to increase exchange enrollment. The Trump Administration had directed the issuance of final rules (i) enabling the formation of association health plans that would be exempt from certain Legislation requirements such as the provision of essential health benefits, (ii) expanding the availability of short-term, limited duration health insurance, (iii) eliminating cost-sharing reduction payments to insurers that would otherwise offset deductibles and other out-of-pocket expenses for health plan enrollees at or below 250 percent of the federal poverty level, (iv) relaxing requirements for state innovation waivers that could reduce enrollment in the individual and small group markets and lead to additional enrollment in short-term, limited duration insurance and association health plans and (v) incentivizing the use of health reimbursement arrangements by employers to permit employees to purchase health insurance in the individual market. The uncertainty resulting from these Executive Branch policies may have led to reduced Exchange enrollment in 2018, 2019 and 2020. It is also anticipated that these policies, to the extent that they remain as implemented, may create additional cost and reimbursement pressures on hospitals, including ours. In addition, there have been numerous political and legal efforts to expand, repeal, replace or modify the Legislation since its enactment, some of which have been successful, in part, in modifying the Legislation, as well as court challenges to the constitutionality of the Legislation. The U.S. Supreme Court rejected the latest such case on June 17, 2021, when the Court held in *California v. Texas* that the plaintiffs lacked standing to challenge the Legislation’s requirement to obtain minimum essential health insurance coverage, or the individual mandate. The Court dismissed the case without specifically ruling on the constitutionality of the Legislation. As a result, the Legislation will continue to remain law, in its entirety, likely for the foreseeable future. Any future efforts to challenge, replace or replace the Legislation or expand or substantially amend its provision is unknown. See below in *Sources of Revenue and Health Care Reform* for additional disclosure; |
| | • | as part of the CAA, Congress passed legislation aimed at preventing or limiting patient balance billing in certain circumstances. The CAA addresses surprise medical bills stemming from emergency services, out-of-network ancillary providers at in-network facilities, and air ambulance carriers. The legislation prohibits surprise billing when out-of-network emergency services or out-of-network services at an in-network facility are provided, unless informed consent is received. In these circumstances providers are prohibited from billing the patient for any amounts that exceed in-network cost-sharing requirements. On July 13, 2021, HHS, the Department of Labor and the Department of the Treasury issued an interim final rule, which begins to implement the legislation. The rule would limit our ability to receive payment for services at usually higher out-of-network rates in certain circumstances and prohibit out-of-network payments in other circumstances; |
| | • | the unfavorable impact on our business of the deterioration in national, regional and local economic and business conditions, including a worsening of unfavorable credit market conditions; |
| | • | there is a heightened risk of future cybersecurity threats, including ransomware attacks targeting healthcare providers. If successful, future cyberattacks could have a material adverse effect on our business. Any costs that we incur as a result of a data security incident or breach, including costs to update our security protocols to mitigate such an incident or breach could be significant. Any breach or failure in our operational security systems can result in loss of data or an unauthorized disclosure of or access to sensitive or confidential member or protected personal or health information and could result in significant penalties or fines, litigation, loss of customers, significant damage to our reputation and business, and other losses. Previously, we had experienced a cyberattack in September, 2020 that had an adverse effect on our operating results during the fourth quarter of 2020, before giving effect to partial recovery of the loss through receipt, during 2021, of commercial insurance proceeds and collection of previously reserved patient accounts, as discussed herein; |
| | • | as discussed below in *Sources of Revenue,* we receive revenues from various state and county-based programs, including Medicaid in all the states in which we operate. We receive annual Medicaid revenues of approximately $100 million, or greater, from each of Texas, California, Nevada, Illinois, Pennsylvania, Washington, D.C., Kentucky, Florida and Massachusetts. We also receive Medicaid disproportionate share hospital payments in certain states including Texas and South Carolina. We are therefore particularly sensitive to potential reductions in Medicaid and other state-based revenue programs as well as regulatory, economic, environmental and competitive changes in those states. We can provide no assurance that reductions to revenues earned pursuant to these programs, and the effect of the COVID-19 pandemic on state budgets, particularly in the above-mentioned states, will not have a material adverse effect on our future results of operations; |
| | • | the Budget Control Act of 2011 (the “2011 Act”) imposed annual spending limits for most federal agencies and programs aimed at reducing budget deficits by $917 billion between 2012 and 2021, according to a report released by the Congressional Budget Office. Among its other provisions, the law established a bipartisan Congressional committee, known as the Joint Select Committee on Deficit Reduction (the “Joint Committee”), which was tasked with making recommendations aimed at reducing future federal budget deficits by an additional $1.5 trillion over 10 years. The Joint Committee was unable to reach an agreement by the November 23, 2011 deadline and, as a result, across-the-board cuts to discretionary, national defense and Medicare spending were implemented on March 1, 2013 resulting in Medicare payment reductions of up to 2% per fiscal year with a uniform percentage reduction across all Medicare programs. The Bipartisan Budget Act of 2015, enacted on November 2, 2015, continued the 2% reductions to Medicare reimbursement imposed under the 2011 Act. Recent legislation has suspended payment reductions through December 31, 2021 in exchange for extended cuts through 2030. Subsequent legislation extended the payment reduction suspension through March 31, 2022, with a 1% payment reduction from then until June 30, 2022 and the full 2% payment reduction thereafter. We cannot predict whether Congress will restructure the implemented Medicare payment reductions or what other federal budget deficit reduction initiatives may be proposed by Congress going forward. See below in *2019 Novel Coronavirus Disease Medicare and Medicaid Payment Related Legislation – Medicare Sequestration Relief*, for additional disclosure related to the favorable effect the legislative extensions have had/are expected to have on our results of operations during 2020 and 2021; |
| | • | in June, 2016, the United Kingdom affirmatively voted in a non-binding referendum in favor of the exit of the United Kingdom (“U.K.”) from the European Union (the “Brexit”) and it was approved by vote of the British legislature. On March 29, 2017, the United Kingdom triggered Article 50 of the Lisbon Treaty, formally starting negotiations regarding its exit from the European Union. On January 31, 2020, the U.K. formally exited the European Union. On December 24, 2020, the United Kingdom and the European Union reached a post-Brexit trade and cooperation agreement that created new business and security requirements and preserved the United Kingdom’s tariff- and quota-free access to the European Union member states. The trade and cooperation agreement was provisionally applied as of January 1, 2021 and entered into force on May 1, 2021, following ratification by the European Union. We do not know to what extent Brexit will ultimately impact the business and regulatory environment in the U.K., the European Union, or other countries. Any of these effects of Brexit, and others we cannot anticipate, could harm our business, financial condition and results of operations, and; |
| --- | --- | --- | --- | --- | --- | --- | --- | --- | --- | --- | --- | --- | --- | --- | --- | --- | --- |
| | | 2021 | | | | 2020 | | |
There were also no goodwill impairments during 2020 or 2019.
CARES Act and Other Governmental Grants and Medicare Accelerated Payments:
During 2021, we received approximately $189 million of additional funds from the federal government in connection with the CARES Act, substantially all of which were received during the first quarter of 2021.
During the second quarter of 2021, we returned the $189 million to the appropriate government agencies utilizing a portion of our cash and cash equivalents held on deposit.
Also, in March of 2021 we made an early repayment of $695 million of funds received during 2020 pursuant to the Medicare Accelerated and Advance Payment Program.
These funds were returned to the government utilizing a portion of our cash and cash equivalents held on deposit.
2020:
As of December 31, 2020, we had received an aggregate of $1.112 billion as follows:
| | o | Approximately $417 million of funds received from various governmental stimulus programs, most notably the CARES Act. Included in our net income attributable to UHS for the year ended December 31, 2020, was the favorable impact of approximately $309 million (after-tax) resulting from the recording of approximately $413 million of CARES Act and other grant income revenues. Approximately $316 million of the grant income revenues were attributable to our acute care services and approximately $97 million were attributable to our behavioral health care services. |
| | o | Approximately $695 million of Medicare accelerated payments received pursuant to the Medicare Accelerated and Advance Payment Program. There was no impact on our earnings during 2020 in connection with receipt of these funds. As mentioned above, in March of 2021, we made an early, full repayment of these funds to the government. |
Net revenues increased by 9.4%, or $1.08 billion, to $12.64 billion during 2021 as compared to $11.56 billion during 2020.
As discussed above, included in our net revenues during 2020 was approximately $413 million of net revenues recorded in connection with various governmental stimulus programs, most notably the CARES Act.
The $41 million increase in our income before income taxes during 2021, as compared to 2020, was due to the following:
| | • | an increase of $41 million at our acute care facilities, as discussed below in *Acute Care Hospital Services*, which includes the favorable impact recorded during 2020, from $316 million of net revenues recorded in connection with various governmental stimulus programs, most notably the CARES Act ($306 million pre-tax favorable impact in 2020, net of amounts attributable noncontrolling interests); |
| | • | an increase of $2 million at our behavioral health care facilities, as discussed below in *Behavioral Health Services,* which includes the favorable impact recorded during 2020, from $97 million of net revenues recorded in connection with various governmental stimulus programs, most notably the CARES Act; |
| | | | 2021 | | | | 2020 | | | | 2021 | | | | 2020 | | |
| Patient days | | | | 1,564,828 | | | | 1,458,321 | | | | 1,568,639 | | | | 1,458,321 | |
| Admissions | | | | 304,955 | | | | 286,535 | | | | 305,296 | | | | 286,535 | |
| Net revenues | | $ | 6,963,627 | | | | 100.0 | % | | $ | 6,238,236 | | | | 100.0 | % |
| Salaries, wages and benefits | | | 2,947,853 | | | | 42.3 | % | | | 2,611,143 | | | | 41.9 | % |
| Other operating expenses | | | 1,656,848 | | | | 23.8 | % | | | 1,462,627 | | | | 23.4 | % |
| Supplies expense | | | 1,218,969 | | | | 17.5 | % | | | 1,081,154 | | | | 17.3 | % |
| Depreciation and amortization | | | 327,774 | | | | 4.7 | % | | | 318,077 | | | | 5.1 | % |
An excerpt. Shown here: 40 of 446 rewritten, 40 of 445 added and 40 of 204 removed. The counts are complete. For every sentence, read Item 7. Management’s Discussion and Analysis of Financial Condition and Results of Operations in the FY2022 filing and the FY2021 filing.
Item 7A. Quantitative and Qualitative Disclosures About Market Risk
10 rewritten, 3 added, 5 removed, 23 unchanged
During the years ended December 31, [added: 2022,] 2021 and 2020, we had no cash flow hedges outstanding.
The table below presents information about our long-term financial instruments that are sensitive to changes in interest rates as of December 31, [removed: 2021.][added: 2022.]
[removed: Maturity] [added: Maturity] Date, Fiscal Year Ending December [removed: 31][added: 31]
[removed: (dollar] [added: (dollar] amounts in [removed: thousands)][added: thousands)]
| | | [removed: 2022] [added: 2023] | | | | [removed: 2023] [added: 2024] | | | | [removed: 2024] [added: 2025] | | | | [removed: 2025] [added: 2026] | | | | [removed: 2026] [added: 2027] | | | | [removed: Thereafter] [added: Thereafter] | | | | [removed: Total] [added: Total] | | |
| [removed: Long-term debt:] [added: Long-term debt:] | | | | | | | | | | | | | | | | | | | | | | | | | | | | |
| Average interest rates | | | 2.4 | % | | | 2.4 | % | | | 2.4 | % | | | 2.4 | % | | | [removed: 2.4] [added: 2.8] | % | | | 3.2 | % | | | 2.6 | % |
| Average interest rates | | | [removed: 1.4] [added: 5.9] | % | | | [removed: 1.4] [added: 5.9] | % | | | [removed: 1.4] [added: 5.9] | % | | | [removed: 1.4] [added: 5.9] | % | | | [removed: 1.4] [added: 0.0] | % | | | 0.0 | % | | | [removed: 1.4] [added: 5.9] | % |
| [removed: Interest] [added: Interest] rate [removed: swaps:] [added: swaps:] | | | | | | | | | | | | | | | | | | | | | | | | | | | | |
As calculated based upon our variable rate debt outstanding as of December 31, [removed: 2021] [added: 2022] that is subject to interest rate fluctuations, each 1% change in interest rates would impact our pre-tax income by approximately [removed: $20] [added: $26] million.
| | | | | | | | | | | | | | | | | | | | | | | | | | | | | |
| Debt | | $ | 6,447 | | | $ | 7,008 | | | $ | 6,255 | | | $ | 701,345 | | | $ | 7,136 | | | $ | 1,437,502 | | | $ | 2,165,693 | |
| Debt | | $ | 75,000 | | | $ | 120,000 | | | | 120,000 | | | | 2,327,287 | | | | 0 | | | | 0 | | | $ | 2,642,287 | |
| --- | --- |
During 2019, we had nine interest rate swaps outstanding, all of which expired on April 15, 2019, whereby we paid a fixed rate on a total notional amount of $1.0 billion and received one-month LIBOR.
The average fixed rate payable on these swaps was 1.31%.
| Debt | | $ | 5,909 | | | $ | 6,523 | | | $ | 7,012 | | | $ | 6,274 | | | $ | 700,168 | | | $ | 1,437,551 | | | $ | 2,163,437 | |
| Debt | | $ | 42,500 | | | $ | 53,125 | | | | 85,000 | | | | 85,000 | | | | 1,761,226 | | | | 0 | | | $ | 2,026,851 | |
Item 1. Business
135 rewritten, 45 added, 44 removed, 258 unchanged
As of February [removed: 24, 2022,] [added: 27, 2023,] we owned and/or operated [removed: 363] [added: 359] inpatient facilities and [removed: 40] [added: 39] outpatient and other facilities including the following located in 39 states, Washington, D.C., the United Kingdom and Puerto Rico:
[removed: Acute] [added: Acute] care facilities located in the [removed: U.S.:][added: U.S.:]
[removed: | | • | 19] [added: 21] free-standing emergency departments, and; [removed: |]
[removed: | | • | 6] [added: 7] outpatient centers & 1 surgical hospital. [removed: |]
[removed: Behavioral] [added: Behavioral] health care facilities [removed: (335] [added: (331] inpatient facilities and [removed: 14] [added: 10] outpatient [removed: facilities):][added: facilities):]
[removed: Located] [added: Located] in the [removed: U.S.:][added: U.S.:]
[removed: | | • | 187] [added: 185] inpatient behavioral health care facilities, and; [removed: |]
[removed: | | • | 12] [added: 8] outpatient behavioral health care facilities. [removed: |]
[removed: Located] [added: Located] in the [removed: U.K.:][added: U.K.:]
[removed: | | • | 145] [added: 143] inpatient behavioral health care facilities, and; [removed: |]
[removed: | | • |] 2 outpatient behavioral health care facilities. [removed: |]
[removed: Located] [added: Located] in Puerto [removed: Rico:][added: Rico:]
[removed: | | • |] 3 inpatient behavioral health care facilities. [removed: |]
Net revenues from our acute care hospitals, outpatient facilities and commercial health insurer accounted for [removed: 56%] [added: 57%] of our consolidated net revenues during [removed: 2021] [added: 2022] and [removed: 55%] [added: 56%] during [removed: 2020.][added: 2021.]
Net revenues from our behavioral health care facilities and commercial health insurer accounted for [removed: 44%] [added: 43%] of our consolidated net revenues during [removed: 2021] [added: 2022] and [removed: 45%] [added: 44%] during [removed: 2020.][added: 2021.]
Our behavioral health care facilities located in the U.K. generated net revenues of approximately [removed: $688] [added: $685] million in [removed: 2021] [added: 2022] and [removed: $584] [added: $688] million in [removed: 2020.][added: 2021.]
Total assets at our U.K. behavioral health care facilities were approximately [removed: $1.351] [added: $1.235] billion as of December 31, [removed: 2021] [added: 2022] and [removed: $1.334] [added: $1.351] billion as of December 31, [removed: 2020.][added: 2021.]
[removed: Available Information][added: Available Information]
Our website is located at [removed: http://www.uhsinc.com.][added: www.uhs.com.]
In accordance with Section 303A.12(a) of the New York Stock Exchange Listed Company Manual, we submitted our CEO’s certification to the New York Stock Exchange in [removed: 2021.][added: 2022.]
[added: Additionally, contained in Exhibits 31.1 and 31.2 of this Annual Report on] Form 10-K, are our CEO’s and CFO’s certifications regarding the quality of our public disclosures under Section 302 of the Sarbanes-Oxley Act of 2002.
[removed: Our Mission][added: Our Mission]
[removed: | | • |] service excellence [removed: |]
[removed: | | • |] continuous improvement in measurable ways [removed: |]
[removed: | | • |] employee development [removed: |]
[removed: | | • |] ethical and fair treatment of all [removed: |]
[removed: | | • |] teamwork [removed: |]
[removed: | | • |] compassion [removed: |]
[removed: | | • |] innovation in service delivery [removed: |]
[removed: Business Strategy][added: Business Strategy]
[added: Acquisition of Additional Hospitals.] We selectively seek opportunities to expand our base of operations by acquiring, constructing or leasing additional hospital facilities.
[added: Improvement of Operations of Existing Hospitals and Services.] We also seek to increase the operating revenues and profitability of owned hospitals by the introduction of new services, improvement of existing services, physician recruitment and the application of financial and operational controls.
[added: Quality and Efficiency of Services.] Pressures to contain healthcare costs and technological developments allowing more procedures to be performed on an outpatient basis have led payers to demand a shift to ambulatory or outpatient care wherever possible.
[removed: Hospital Utilization][added: Hospital Utilization]
Other factors that affect utilization include general and local economic conditions, market penetration of managed care programs, the degree of outpatient use, the availability of [removed: reimbursement programs such as Medicare and Medicaid, and demographic changes such as the growth in local populations.]
[removed: Sources] [added: Sources] of [removed: Revenue][added: Revenue]
[removed: Regulation] [added: Regulation] and Other [removed: Factors][added: Factors]
[removed: Overview:] [added: Overview:] The healthcare industry is subject to numerous laws, regulations and rules including, among others, those related to government healthcare participation requirements, various licensure and accreditations, reimbursement for patient services, health information privacy and security rules, and Medicare and Medicaid fraud and abuse provisions (including, but not limited to, federal statutes and regulations prohibiting kickbacks and other illegal inducements to potential referral sources, false claims submitted to federal or state health care programs and self-referrals by physicians).
[removed: Licensing,] [added: Licensing,] Certification and [removed: Accreditation:] [added: Accreditation:] All of our U.S. hospitals are subject to compliance with various federal, state and local statutes and regulations in the U.S. and receive periodic inspection by state licensing agencies to review standards of medical care, equipment and cleanliness.
[removed: Certificates] [added: Certificates] of [removed: Need:] [added: Need:] Many of the states in which we operate hospitals have enacted certificates of need (“CON”) laws as a condition prior to hospital capital expenditures, construction, expansion, modernization or initiation of major new services.
28 inpatient acute care hospitals;
reimbursement programs such as Medicare and Medicaid, and demographic changes such as the growth in local populations.
The privacy and security regulations address the use and disclosure of
CMS
During orientation, newly hired employees learn our mission, vision, principles and values, key policies and procedures, a summary of the various benefits and resources available, and perhaps most notably, an overview of our founding principle, Service Excellence.
Learning key attributes of our Service Excellence standards, which include continuous improvement, employee development, ethical and fair treatment of all, teamwork, compassion and innovation in service delivery, provides newly hired employees a thorough understanding of our company culture.
Other components of our Service Excellence standards, which include treating everyone as a guest, demonstrating professionalism and excellence and practicing teamwork, are shared to help guide the desired approach to day-to-day activities.
Service Excellence Facilitator Certification Workshops are available for facility employees identified by their leadership for consistently upholding and demonstrating our Service Excellence standards.
Certified facilitators foster the Service Excellence culture and deliver training at their facilities.
During 2022, we strengthened our recruitment efforts, improved the overall hiring and onboarding experience, expanded the training resources employees need to do their jobs effectively and safely, facilitated more teamwork and collaboration, addressed burnout, expanded mentorship and increased employee engagement.
Each member of our Board of Directors and senior management is committed to healthcare operations that are ethical and in compliance with all applicable laws and regulations.
We prohibit retaliation for the good faith reporting of compliance concerns and offer the ability for individuals to anonymously elevate any concerns.
Leading into 2022, we launched a new employee assistance program which has provided a superior level of service to all our employees and members of their households.
They also provided support on site at any of our hospitals.
We have continuous training on workplace safety and launched a “We Care” program guide to ensure our hospitals support employees in a detailed way in the event of an employee injury.
In keeping with our culture of continuous improvement, training opportunities are available for all employees, regardless of level or status.
These include formal instructor-led, in-person or virtual training, informal mentoring or networking opportunities or self-administered online courses.
Training programs are designed to assist with personal and skill development, career advancement and succession planning.
In addition to mandatory training that focus on keeping employees mindful and informed of key policies and skill sets, many are voluntary.
All training is tailored to include potential Americans with Disabilities Act accommodations.
Across the company, we offer educational and work opportunities, including internships, externships and clinical field placement opportunities.
We also offer financial assistance programs, such as tuition reimbursement, to support employees participating in degree or certification programs.
As an EEO Employer, we support and are fully committed to recruitment, selection, placement, promotion and compensation of all individuals without regard to race, color, religion, age, sex (including pregnancy, gender identity, and sexual orientation), genetic information, national origin, disability status, protected veteran status or any other characteristic protected by federal, state or local laws.
Our commitment to diversity, equality and inclusion includes regularly monitoring employment practices to ensure equity, regardless of an employee’s gender, race or ethnicity and championing for inclusive behaviors through leadership example, policies and procedures, training and special events.
We continue to support the overall health and financial well-being of our employees across the extensive programs and benefit plans that we offer.
In 2022, the UHS Foundation continued to support employees and their families who suffered losses due to natural disasters across the country, including fires in Boulder, Colorado, Hurricane Ida, Hurricane Ian, and the storms that impacted Kentucky.
This transaction generated a gain of approximately $68.4 million for the Trust, our share of which (approximately $4.0 million) is included in our consolidated statement of income for the year ended December 31, 2021.
The total aggregate rental for leases on the four wholly-owned hospital facilities with the Trust (excluding Clive Behavioral Health Hospital which is discussed below) was approximately $20.2 million during 2022.
| | | | | | | | | | | | | |
(a)
(b)
We have one 5-year renewal option at fair market value lease rates (through 2031).
Effective January 1, 2022, the annual fair market value lease rate for this hospital is $6.3 million (there is no longer a bonus rental component of the lease payment).
On each January 1st through 2026, the annual rent will increase by 2.50% on a cumulative and compounded basis.
(c)
On each January 1st through 2033, the annual rent will increase by 2.25% on a cumulative and compounded basis.
(d)
The joint venture has three, 10-year renewal options at computed lease rates as stipulated in the
lease (2041 through 2070) and two additional, 10-year renewal options at fair market values lease rates (2071 through 2090).
| | | |
| --- | --- |
| | • | 28 inpatient acute care hospitals (including a newly constructed, 170-bed hospital located in Reno, Nevada, that is scheduled to be completed and opened during the first quarter of 2022); |
| --- | --- | --- |
Additionally, contained in Exhibits 31.1 and 31.2 of this Annual Report on
Acquisition of Additional Hospitals.
Improvement of Operations of Existing Hospitals and Services.
Quality and Efficiency of Services.
In the past, we have
These activities, which must meet certain requirements, include (but are not limited to) the following: investment interests,
fraud and abuse in Medicare.
direct result of another hospital’s violation of the law can bring a civil suit against the hospital unrelated to the rights granted under that statute.
At the Psychiatric Institute of Washington, clinical, clerical, support and maintenance employees are represented by the Communication Workers of America (AFL-CIO).
Our commitment to “Service Excellence” serves as the foundation of our culture and is defined as providing world-class service that is professional, timely, effective and efficient to all of our customer groups at all times.
Serving as the foundation of our company mission, vision, and principles, Service Excellence is the way we approach every human interaction at our company, all the time, every day.
All new employees participate in a Service Excellence training session.
Employees learn what Service Excellence means at our company and develop an action plan on how to apply this to their everyday work.
The individual action plan is mutually shared and maintained with employees and their managers.
To recruit and retain a diverse and talented workforce, we continuously monitor and update our competitive compensation and benefit packages.
We regularly survey our employees to obtain their views and assess employee satisfaction.
We use the views expressed in the surveys to assess and update our people strategy and policies.
We set high ethical standards for ourselves because caring for our patients is a sacred trust.
We provide protected ways for them to do that.
We know that the quality of the patient experience is driven by the personal compassion, competence and commitment our team members deliver every day.
A collaborative approach among our staff is encouraged because we all share the goal of providing superior quality patient care and support to families and loved ones.
During 2020, our increased attention to workplace safety has enabled us to continue our commitment to keeping our employees and facilities safe during the COVID-19 pandemic.
We have a number of employee and leadership development programs in place to strengthen our company, help further our employees’ personal career goals and assist with succession planning.
We encourage employees to take charge of their career development and set objectives in partnership with their managers.
We train managers to partner with employees and support them in their efforts.
We utilize various methods for personal and technical development: on-demand videos, webinars, classroom trainings, coaching, and more.
We also offer tuition reimbursement as a part of our benefits program.
It is our policy to ensure that both current and prospective employees receive equal employment opportunity without consideration of race, religion, color, national origin, nationality, ancestry, age, sex, marital status, sexual orientation, or disability in accordance with local, state and federal laws.
During 2021, the UHS Foundation, which was previously established to assist our employees that are significantly impacted by various events such as FEMA-qualified natural disasters and presidential-declared natural disasters, continued to provide financial support for UHS employees and their families who were significantly impacted by the COVID-19 pandemic.
During 2020, in response to the COVID 19 pandemic, the base salaries of all of our executive and non-executive officers, as well as certain other members of our senior management team, were reduced by various percentages.
In turn, we contributed the funds generated from these base salary reductions to the UHS Foundation.
In addition, the UHS Foundation also received voluntary contributions from other employees and various other parties, including members of our Board of Directors.
Utilizing funds from the UHS Foundation, we worked with impacted employees to cover the employee cost-share for benefits throughout COVID-19.
In addition, we also expanded resources through our employee assistance program, with a particular focus on emotional wellness and COVID-19 support for our front-line healthcare workers.
Most of the leases were entered into at the time the Trust commenced operations and provided for initial terms of 13 to 15 years with up to six additional 5-year renewal terms.
Each lease, at that time, also provided for additional or bonus rental, as discussed below.
| --- | --- | --- | --- |
An excerpt. Shown here: 40 of 135 rewritten, 40 of 45 added and 40 of 44 removed. The counts are complete. For every sentence, read Item 1. Business in the FY2022 filing and the FY2021 filing.
Item 3. Legal Proceedings
0 rewritten, 0 added, 1 removed, 1 unchanged
| --- | --- |
Cover and table of contents
49 rewritten, 6 added, 1 removed, 52 unchanged
[removed: UNITED STATES][added: UNITED STATES]
[removed: SECURITIES] [added: SECURITIES] AND EXCHANGE [removed: COMMISSION][added: COMMISSION]
[removed: Washington,] [added: Washington,] D.C. [removed: 20549][added: 20549]
[removed: FORM 10-K][added: FORM 10-K]
[removed: (MARK ONE)][added: (MARK ONE)]
| [removed: ☒] [added: ☒] | | [removed: ANNUAL] [added: ANNUAL] REPORT PURSUANT TO SECTION 13 OR 15(d) OF THE SECURITIES EXCHANGE ACT OF [removed: 1934] [added: 1934] |
[removed: For] [added: For] the fiscal year [removed: ended December 31, 2021][added: ended December 31, 2022]
| [removed: ☐] [added: ☐] | | [removed: TRANSITION] [added: TRANSITION] REPORT PURSUANT TO SECTION 13 OR 15(d) OF THE SECURITIES EXCHANGE ACT OF [removed: 1934] [added: 1934] |
[removed: For] [added: For] the transition period [removed: from to][added: from to]
[removed: Commission] [added: Commission] File [removed: No. 1-10765][added: No. 1-10765]
[removed: UNIVERSAL] [added: UNIVERSAL] HEALTH SERVICES, [removed: INC.][added: INC.]
[removed: (Exact] [added: (Exact] name of registrant as specified in its [removed: charter)][added: charter)]
| [removed: Delaware] [added: Delaware] | | [removed: 23-2077891] [added: 23-2077891] |
| [removed: (State] [added: (State] or other jurisdiction [removed: of incorporation] [added: of incorporation] or [removed: organization)] [added: organization)] | | [removed: (I.R.S. Employer Identification Number)] [added: (I.R.S. Employer Identification Number)] |
| [removed: UNIVERSAL] [added: UNIVERSAL] CORPORATE [removed: CENTER] [added: CENTER] | | |
| [removed: 367] [added: 367] South Gulph [removed: Road P.O.] [added: Road P.O.] Box [removed: 61558 King] [added: 61558 King] of [removed: Prussia, Pennsylvania] [added: Prussia, Pennsylvania] | | [removed: 19406-0958] [added: 19406-0958] |
| [removed: (Address] [added: (Address] of principal executive [removed: offices)] [added: offices)] | | [removed: (Zip Code)] [added: (Zip Code)] |
[removed: Registrant’s] [added: Registrant’s] telephone number, including area code: [removed: (610) 768-3300][added: (610) 768-3300]
[removed: Securities] [added: Securities] registered pursuant to Section 12(b) of the [removed: Act:][added: Act:]
[removed: Securities] [added: Securities] registered pursuant to Section 12(g) of the [removed: Act:][added: Act:]
[removed: Class] [added: Class] D Common Stock, $.01 par [removed: value][added: value]
[removed: (Title] [added: (Title] of each [removed: Class)][added: Class)]
The aggregate market value of voting stock held by non-affiliates at June 30, [removed: 2021] [added: 2022] was [removed: $10.8] [added: $6.4] billion.
The number of shares of the registrant’s Class A Common Stock, $.01 par value, Class B Common Stock, $.01 par value, Class C Common Stock, $.01 par value, and Class D Common Stock, $.01 par value, outstanding as of January 31, [removed: 2022,] [added: 2023,] were 6,577,100; [removed: 67,552,047;] [added: 63,417,294;] 661,688 and [removed: 14,625,] [added: 14,170,] respectively.
[removed: DOCUMENTS] [added: DOCUMENTS] INCORPORATED BY [removed: REFERENCE:][added: REFERENCE:]
Portions of the registrant’s definitive proxy statement for our 2022 Annual Meeting of Stockholders, which will be filed with the Securities and Exchange Commission within 120 days after December 31, [removed: 2021] [added: 2022] (incorporated by reference under Part III).
[removed: 2021] [added: 2022] FORM 10-K ANNUAL [removed: REPORT][added: REPORT]
[removed: TABLE] [added: TABLE] OF [removed: CONTENTS][added: CONTENTS]
| Item 3 | | [Legal [removed: Proceedings](#ITEM_3_LEGAL_PROCEEDINGS)] [added: Proceedings](#item_3_legal_proceedings)] | [removed: 36] [added: 35] |
| Item 4 | | [Mine Safety [removed: Disclosure](#ITEM_4_MINE_SAFETY_DISCLOSURES)] [added: Disclosure](#item_4_mine_safety_disclosures)] | [removed: 36] [added: 35] |
| Item 5 | | [Market for Registrant’s Common Equity, Related Stockholder Matters and Issuer Purchases of Equity [removed: Securities](#ITEM_5_MARKET_FOR_REGISTRANTS_COMMON_EQU)] [added: Securities](#item_5_market)] | [removed: 37] [added: 36] |
| Item 6 | | [removed: [\[RESERVED\]](#ITEM_6_RESERVED)] [added: [\[RESERVED\]](#item_6_reserved)] | [removed: 38] [added: 37] |
| Item 7 | | [Management’s Discussion and Analysis of Financial Condition and Results of [removed: Operations](#ITEM_7_MANAGEMENTS_DISCUSSION_ANALYSIS_F)] [added: Operations](#item_7_managements_discussion_analysis_f)] | [removed: 39] [added: 38] |
| Item 7A | | [Quantitative and Qualitative Disclosures About Market [removed: Risk](#ITEM_7A_QUANTITATIVE_QUALITATIVE_DISCLOS)] [added: Risk](#item_7a_quantitative_qualitative_disclos)] | [removed: 74] [added: 75] |
| Item 8 | | [Financial Statements and Supplementary [removed: Data](#ITEM_8_FINANCIAL_STATEMENTS_SUPPLEMENTAR)] [added: Data](#item_8_financial_statements_supplementar)] | [removed: 75] [added: 76] |
| Item 9 | | [Changes in and Disagreements with Accountants on Accounting and Financial [removed: Disclosure](#ITEM_9_CHANGES_IN_DISAGREEMENTS_WITH_ACC)] [added: Disclosure](#item_9_changes_in_disagreements_with_acc)] | [removed: 75] [added: 76] |
| Item 9A | | [Controls and [removed: Procedures](#ITEM_9A_CONTROLS_PROCEDURES)] [added: Procedures](#item_9a_controls_procedures)] | [removed: 75] [added: 76] |
| Item 9B | | [Other [removed: Information](#ITEM_9B_OR_INFORMATION)] [added: Information](#item_9b_or_information)] | [removed: 76] [added: 77] |
| Item 9C | | [Disclosure Regarding Foreign Jurisdictions that Prevent [removed: Inspections](#ITEM_9C_DISCLOSURE_REGARDING_FOREIGN)] [added: Inspections](#item_9c_disclosure_regarding_foreign)] | [removed: 76] [added: 77] |
| Item 10 | | [Directors, Executive Officers and Corporate [removed: Governance](#ITEM_10_DIRECTORS_EXECUTIVE_FICERS_CORPO)] [added: Governance](#item_10_directors_executive_ficers_corpo)] | [removed: 77] [added: 78] |
OR
| | | |
| | | |
If securities are registered pursuant to Section 12(b) of the Act, indicate by check mark whether the financial statements of the registrant included in the filing reflect the correction of an error to previously issued financial statements.
Indicate by check mark whether any of those error corrections are restatements that required a recovery analysis of incentive-based compensation received by any of the registrant’s executive officers during the relevant recovery period pursuant to §240.10D-1(b).
| | | | |
OR
An excerpt. Shown here: 40 of 49 rewritten, all 6 added and all 1 removed. The counts are complete. For every sentence, read Cover and table of contents in the FY2022 filing and the FY2021 filing.
Item 1B. Unresolved Staff Comments
0 rewritten, 0 added, 1 removed, 1 unchanged
| --- | --- |
Item 2. Properties
76 rewritten, 62 added, 13 removed, 382 unchanged
[removed: Executive] [added: Executive] and Administrative Offices and Commercial Health [removed: Insurer][added: Insurer]
[removed: Acute] [added: Acute] Care [removed: Hospitals][added: Hospitals]
| [removed: Name] [added: Name] of [removed: Facility] [added: Facility] | [removed: Location] [added: Location] | [removed: Number] [added: Number] of [removed: Beds] [added: Beds] | [removed: Real] [added: Real] Property Ownership [removed: Interest] [added: Interest] |
| Aiken Regional Medical Centers [removed: (2)] [added: (1)] | Aiken, South Carolina | 211 | Leased |
| Aurora Pavilion Behavioral Health Services [removed: (2)] [added: (1)] | Aiken, South Carolina | 62 | Leased |
| ER at Valley Vista | [added: North] Las Vegas, Nevada | — | Owned |
| Doctors Hospital of Laredo [removed: (7)] [added: (6)] | Laredo, Texas | 183 | Owned |
| The George Washington University Hospital [removed: (1)] [added: (19)] | Washington, D.C. | 395 | Leased |
| Henderson Hospital | Henderson, Nevada | [removed: 239] [added: 303] | Owned |
| Lakewood Ranch Medical Center | [removed: Bradenton,] [added: Lakewood Ranch,] Florida | 120 | Owned |
| Northern Nevada Sierra Medical Center [removed: (15)] | Reno, Nevada | [removed: 170] [added: 158] | Owned |
| South Texas Health System [removed: (3)] [added: (2)] | | | |
| Edinburg Regional Medical Center/Children’s Hospital [removed: (3)] [added: (2)] | Edinburg, Texas | [removed: 235] [added: 251] | Owned |
| South Texas Health System Behavioral [removed: (3)] [added: (2)] | McAllen, Texas | 134 | Owned |
| South Texas Health System Heart [removed: (3)] [added: (2)] | McAllen, Texas | 60 | Owned |
| South Texas Health System McAllen [added: (1)] (2) [removed: (3)] | McAllen, Texas | 431 | Leased |
| South Texas Health System ER Alamo [removed: (3)] [added: (2)] | Alamo, Texas | — | Owned |
| South Texas Health System ER McColl [removed: (3)] [added: (2)] | Edinburg, Texas | — | Owned |
| South Texas Health System ER Mission [added: (1)] (2) [removed: (3)] | Mission, Texas | — | Leased |
| South Texas Health System ER Monte Cristo [removed: (3)] [added: (2)] | Edinburg, Texas | — | Owned |
| South Texas Health System ER Ware Road [removed: (3)] [added: (2)] | McAllen, Texas | — | Owned |
| South Texas Health System ER Weslaco [added: (1)] (2) [removed: (3)] | Weslaco, Texas | — | Leased |
| Elite Medical Center [added: (ER)] | Las Vegas, Nevada | — | Owned |
| Wellington Regional Medical Center [removed: (2)] [added: (1)] | [removed: West Palm Beach,] [added: Wellington,] Florida | 235 | Leased |
| ER at Westlake | [removed: West Palm Beach,] [added: Westlake,] Florida | — | Leased |
[removed: Inpatient] [added: Inpatient] Behavioral Health Care [removed: Facilities][added: Facilities]
| [removed: United States:] [added: United States:] | | | |
| Arbour Hospital | [removed: Boston,] [added: Jamaica Plain,] Massachusetts | 136 | Owned |
| Arrowhead Behavioral Health [added: (16)] | Maumee, Ohio | 48 | Owned |
| Beaumont Behavioral Health [removed: (13)] [added: (18)] | Dearborn, Michigan | [removed: 32] [added: 87] | Leased |
| Black Bear Lodge | [removed: Sautee,] [added: Sautee Nacoochee,] Georgia | 115 | Owned |
| Canyon Creek Behavioral Health [removed: (2)] | Temple, Texas | 102 | Leased |
| Cedar Grove Residential Treatment Center | Murfreesboro, Tennessee | [removed: 40] [added: 45] | Owned |
| Cedar Hills Hospital [removed: (8)] [added: (7)] | [removed: Beaverton,] [added: Portland,] Oregon | 98 | Owned |
| Clive Behavioral Health [removed: (2) (12)] [added: (11)] | Clive, Iowa | 100 | Leased |
| Cumberland Hospital for Children and Adolescents | New Kent, Virginia | [removed: 110] [added: 108] | Owned |
| Friends Hospital [added: (15)] | Philadelphia, Pennsylvania | 219 | Owned |
| Fuller Hospital | [removed: South] Attleboro, Massachusetts | [removed: 102] [added: 109] | Owned |
| Inland Northwest Behavioral Health [removed: (10)] [added: (9)] | Spokane, Washington | 100 | Owned |
| Lancaster Behavioral Health Hospital [removed: (9)] [added: (8)] | Lancaster, Pennsylvania | 126 | Owned |
| ER at Sweetwater | North Augusta, South Carolina | — | Owned |
| ER at Sun City | Wimauma, Florida | −− | |
| Name of Facility | Location | Number of Beds | Real Property Ownership Interest |
| Name of Facility | Location | Number of Beds | Real Property Ownership Interest |
| Name of Facility | Location | Number of Beds | Real Property Ownership Interest |
| United States: | | | |
| Name of Facility | Location | Number of Beds | Real Property Ownership Interest |
| United States: | | | |
| Name of Facility | Location | Number of Beds | Real Property Ownership Interest |
| Via Linda BHS (14) | Scottsdale, Arizona | 120 | Leased |
| United States: | | | |
| Name of Facility | Location | Number of Beds | Real Property Ownership Interest |
| Name of Facility | Location | Number of Beds | Real Property Ownership Interest |
| Name of Facility | Location | Number of Beds | Real Property Ownership Interest |
| United Kingdom: | | | |
| Name of Facility | Location | Number of Beds | Real Property Ownership Interest |
| Name of Facility | Location | Number of Beds | Real Property Ownership Interest |
| United States: | | |
| United Kingdom: | | |
| Name of Facility | Location | Real Property Ownership Interest |
| | | |
| Name of Facility | Location | Real Property Ownership Interest |
| Riverside Medical Clinic Surgery Center | Riverside, California | Leased |
(1)
(2)
(3)
(4)
(5)
(6)
The remaining 7% ownership interest is held by unaffiliated third parties.
(7)
(8)
We manage and own a noncontrolling interest of 50% in this facility.
The remaining 50% ownership interest is held by an unaffiliated third party.
(9)
We manage and hold an 80% ownership interest in this facility.
(10)
We hold a 51% ownership interest in this facility.
(11)
We manage and hold a 52% ownership interest in this facility.
| --- | --- |
| | | | |
| Austin Lakes Hospital | Austin, Texas | 58 | Leased |
| Boulder Creek Academy | Bonners Ferry, Idaho | 105 | Owned |
| Schick Shadel Hospital | Burien, Washington | 60 | Owned |
| 45 Portland Road | Birmingham, UK | 4 | Leased |
| Whorlton Hall | County Durham, UK | 17 | Owned |
| Arbour Senior Care | Rockland, Massachusetts | Owned |
| Behavioral Educational Services | Riverdale, Florida | Leased |
| First Home Care (VA) | Portsmouth, Virginia | Leased |
| Foundations Atlanta at Midtown | Atlanta, Georgia | Leased |
| (1) | We hold an 80% ownership interest in this facility through a general partnership interest in a limited partnership. The remaining 20% ownership interest is held by an unaffiliated third party which leases the property to the partnership for nominal rent. The term of the partnership is scheduled to expire in July, 2047, and we have five, five-year extension options. The term of the lease is coterminous with the partnership term with a fair market value rental of the property during the extension term. |
| (15) | Hospital is scheduled to be completed and opened during the first quarter of 2022. |
An excerpt. Shown here: 40 of 76 rewritten, 40 of 62 added and all 13 removed. The counts are complete. For every sentence, read Item 2. Properties in the FY2022 filing and the FY2021 filing.
Item 4. Mine Safety Disclosures
1 rewritten, 0 added, 1 removed, 1 unchanged
[removed: PART II][added: PART II]
| --- | --- |
Item 5. . Market for Registrant’s Common Equity, Related Stockholder Matters and Issuer Purchases of Equity Securities
19 rewritten, 18 added, 10 removed, 16 unchanged
The number of stockholders of record as of January 31, [removed: 2022,] [added: 2023,] were as follows:
| Class [removed: B] [added: D] Common | | | [removed: 814] [added: 85] | |
| Class [removed: D] [added: B] Common | | | [removed: 90] [added: 729] | |
[removed: Stock] [added: Stock] Repurchase [removed: Programs][added: Programs]
[removed: On February 24,] [added: In February,] 2022, our Board of Directors authorized a $1.4 billion increase to [removed: our stock repurchase] [added: the] program.
As reflected below, during the fourth quarter of [removed: 2021, pursuant to previous share repurchase authorizations, including a $1.0 billion increase to the program approved by our Board of Directors in July, 2021,] [added: 2022,] we have repurchased approximately [removed: 3.43 million] [added: 812,141] shares at an aggregate cost of approximately [removed: $432.3 million.][added: $107.23 million (approximately $132.03 per share) pursuant to the terms of our stock repurchase program.]
For the year ended December 31, [removed: 2021,] [added: 2022,] we have repurchased approximately [removed: 8.41] [added: 6.67] million shares at an aggregate cost of approximately [removed: $1.201 billion.][added: $810.86 million (approximately $121.63 per share).]
As of December 31, 2021, [removed: prior to the above-mentioned increased authorization approved in February, 2022,] we had an aggregate available [removed: repurchase] [added: purchase] authorization of $358.2 million.
During the period of October 1, [removed: 2021] [added: 2022] through December 31, [removed: 2021,] [added: 2022,] we repurchased the following shares:
| | | [removed: Additional] [added: Additional] Dollars Authorized For Repurchase (in [removed: thousands)] [added: thousands)] | | | | [removed: Total] [added: Total] number of shares purchased [removed: (1)] [added: (1)] | | | | [removed: Total] [added: Total] number of shares [removed: cancelled] [added: cancelled] | | | | [removed: Average] [added: Average] price paid per share for forfeited restricted [removed: shares] [added: shares] | | | | [removed: Total] [added: Total] Number of shares purchased as part of publicly announced programs [removed: (2)] [added: (2)] | | | | [removed: Average] [added: Average] price paid per share for shares purchased as part of publicly announced [removed: program] [added: program] | | | | [removed: Aggregate] [added: Aggregate] purchase price paid (in [removed: thousands)] [added: thousands)] | | | | [removed: Maximum] [added: Maximum] number of dollars that may yet be purchased under the program (in [removed: thousands)] [added: thousands)] | | |
[removed: | | (1) | During the three-month period ended December 31, 2021, 588] [added: Includes] shares [added: that] were repurchased in connection with income tax withholding obligations resulting from the exercise of stock options and the vesting of restricted stock grants. [removed: |]
[removed: | | (2) | The only publicly announced program pursuant to which the shares were repurchased was the share repurchase program described above. There is no other plan or program that has expired during this time period.] Also, there is no other plan or program that we have determined to terminate prior to expiration, or under which we do not intend to make further purchases. [removed: |]
[removed: Dividends][added: Dividends]
During the year ended December 31, [removed: 2021] [added: 2022] we paid dividends of $0.80 per share.
[removed: Stock] [added: Stock] Price Performance [removed: Graph][added: Graph]
The following graph compares the cumulative total stockholder return on our common stock with the cumulative total return on the stock included in the Standard & Poor’s 500 Index and a Peer Group Index during the five-year period ended December 31, [removed: 2021.][added: 2022.]
The graph assumes an investment of $100 made in our common stock and each Index as of January 1, [removed: 2017] [added: 2018] and has been weighted based on market capitalization.
[removed: 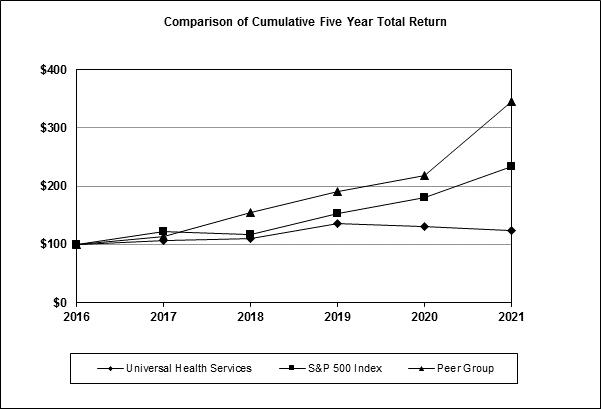][added: 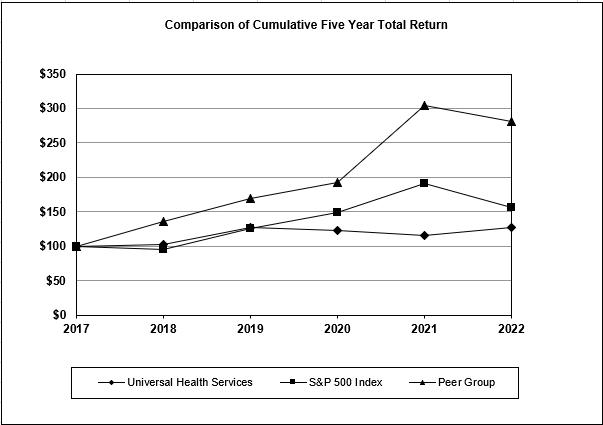]
| Company Name / Index | | [removed: 2016 Base] [added: 2017 Base] | | | | [removed: 2017] [added: 2018] | | | | [removed: 2018] [added: 2019] | | | | [removed: 2019] [added: 2020] | | | | [removed: 2020] [added: 2021] | | | | [removed: 2021] [added: 2022] | | |
| | | | | |
As of December 31, 2022, we had an aggregate available repurchase authorization of $947.37 million.
In addition, during the three-month period ended December 31, 2022, 17,727 shares were repurchased in connection with income tax withholding obligations resulting from stock-based compensation programs.
In addition, for the year ended December 31, 2022, 153,305 shares were repurchased in connection with income tax withholding obligations resulting from stock-based compensation programs.
| | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | |
| October, 2022 | | | — | | | | 1,730 | | | | 745 | | | $ | 0.01 | | | | — | | | $ | — | | | $ | — | | | $ | 1,054,597 | |
| November, 2022 | | | — | | | | 191,955 | | | | 286 | | | $ | 0.01 | | | | 182,141 | | | $ | 129.64 | | | $ | 23,612 | | | $ | 1,030,985 | |
| December, 2022 | | | — | | | | 637,764 | | | | 550 | | | $ | 0.01 | | | | 630,000 | | | $ | 132.73 | | | $ | 83,617 | | | $ | 947,368 | |
| Total October through December | | $ | \- | | | | 831,449 | | | | 1,581 | | | $ | 0.01 | | | | 812,141 | | | $ | 132.03 | | | $ | 107,229 | | | | | |
(1)
Also includes 745, 286 and 550 restricted shares that were forfeited and canceled by former employees pursuant to the terms of our restricted stock purchase plan during October, November and December, 2022, respectively.
(2)
The only publicly announced program pursuant to which the shares were repurchased was the share repurchase program described above.
There is no other plan or program that has expired during this time period.
| | | | | | | | | | | | | | | | | | | | | | | | | |
| Universal Health Services, Inc. | | $ | 100.00 | | | $ | 103.16 | | | $ | 127.53 | | | $ | 122.42 | | | $ | 116.10 | | | $ | 126.98 | |
| S&P 500 Index | | $ | 100.00 | | | $ | 95.62 | | | $ | 125.72 | | | $ | 148.85 | | | $ | 191.58 | | | $ | 156.88 | |
| Peer Group | | $ | 100.00 | | | $ | 135.63 | | | $ | 168.65 | | | $ | 192.34 | | | $ | 304.63 | | | $ | 281.64 | |
| --- | --- |
| October, 2021 | | | — | | | | 29 | | | | 731 | | | $ | 0.01 | | | | — | | | $ | — | | | $ | — | | | $ | 790,495 | |
| November, 2021 | | | — | | | | 2,222,037 | | | | 1,206 | | | $ | 0.01 | | | | 2,221,796 | | | $ | 126.53 | | | $ | 281,125 | | | $ | 509,370 | |
| December, 2021 | | | — | | | | 1,203,913 | | | | 1,301 | | | $ | 0.01 | | | | 1,203,595 | | | $ | 125.57 | | | $ | 151,137 | | | $ | 358,233 | |
| Total October through December | | $ | \- | | | | 3,425,979 | | | | 3,238 | | | $ | 0.01 | | | | 3,425,391 | | | $ | 126.19 | | | $ | 432,262 | | | | | |
| --- | --- | --- |
Our Board of Directors approved the resumption of quarterly dividend payments of $0.20 per share beginning in the first quarter of 2021 (after being temporarily suspended during 2020 as part of various COVID-19 initiatives).
| Universal Health Services, Inc. | | $ | 100.00 | | | $ | 106.93 | | | $ | 110.31 | | | $ | 136.36 | | | $ | 130.90 | | | $ | 124.14 | |
| S&P 500 Index | | $ | 100.00 | | | $ | 121.83 | | | $ | 116.49 | | | $ | 153.17 | | | $ | 181.35 | | | $ | 233.41 | |
| Peer Group | | $ | 100.00 | | | $ | 113.54 | | | $ | 154.00 | | | $ | 191.48 | | | $ | 218.39 | | | $ | 345.88 | |
Item 6. [RESERVED]
0 rewritten, 0 added, 1 removed, 0 unchanged
| --- | --- |
Item 8. Financial Statements and Supplementary Data
0 rewritten, 0 added, 1 removed, 2 unchanged
| --- | --- |
Item 9. Changes in and Disagreements with Accountants on Accounting and Financial Disclosure
0 rewritten, 0 added, 1 removed, 1 unchanged
| --- | --- |
Item 9A. Controls and Procedures.
5 rewritten, 0 added, 1 removed, 7 unchanged
As of December 31, [removed: 2021,] [added: 2022,] under the supervision and with the participation of our management, including our Chief Executive Officer (“CEO”) and Chief Financial Officer (“CFO”), we performed an evaluation of the effectiveness of our disclosure controls and procedures as defined in Rule 13a-15(e) or Rule 15d-15(e) of the Securities Exchange Act of 1934, as amended.
There have been no changes in our internal control over financial reporting or in other factors during the fourth quarter of [removed: 2021] [added: 2022] that have materially affected, or are reasonably likely to materially affect, our internal control over financial reporting.
[removed: Management’s] [added: Management’s] Report on Internal Control Over Financial [removed: Reporting][added: Reporting]
Based on its assessment, management has concluded that we maintained effective internal control over financial reporting as of December 31, [removed: 2021,] [added: 2022,] based on criteria in *Internal Control—Integrated Framework (2013)*, issued by the COSO.
The effectiveness of the Company’s internal control over financial reporting as of December 31, [removed: 2021] [added: 2022] has been audited by PricewaterhouseCoopers LLP, an independent registered public accounting firm as stated in its report which appears herein.
| --- | --- |
Item 9B. Other Information
0 rewritten, 0 added, 1 removed, 1 unchanged
| --- | --- |
Item 9C. Disclosure Regarding Foreign Jurisdictions that Prevent Inspections. Other Information
1 rewritten, 0 added, 1 removed, 1 unchanged
[removed: PART III][added: PART III]
| --- | --- |
Item 10. Directors, Executive Officers and Corporate Governance
1 rewritten, 0 added, 1 removed, 1 unchanged
There is hereby incorporated by reference the information to appear under the captions “Election of Directors”, “Section 16(a) Beneficial Ownership Reporting Compliance” and “Corporate Governance” in our Proxy Statement, to be filed with the Securities and Exchange Commission within 120 days after December 31, [removed: 2021.][added: 2022.]
| --- | --- |
Item 11. Executive Compensation
1 rewritten, 0 added, 1 removed, 0 unchanged
There is hereby incorporated by reference the information to appear under the caption “Executive Compensation” in our Proxy Statement to be filed with the Securities and Exchange Commission within 120 days after December 31, [removed: 2021.][added: 2022.]
| --- | --- |
Item 12. Security Ownership of Certain Beneficial Owners and Management and Related Stockholder Matters
1 rewritten, 0 added, 1 removed, 0 unchanged
There is hereby incorporated by reference the information to appear under the caption “Security Ownership of Certain Beneficial Owners and Management” and “Executive Compensation” in our Proxy Statement, to be filed with the Securities and Exchange Commission within 120 days after December 31, [removed: 2021.][added: 2022.]
| --- | --- |
Item 13. Certain Relationships and Related Transactions, and Director Independence
1 rewritten, 0 added, 1 removed, 0 unchanged
There is hereby incorporated by reference the information to appear under the captions “Certain Relationships and Related Transactions” and “Corporate Governance” in our Proxy Statement, to be filed with the Securities and Exchange Commission within 120 days after December 31, [removed: 2021.][added: 2022.]
| --- | --- |
Item 14. Principal Accountant Fees and Services.
2 rewritten, 0 added, 1 removed, 0 unchanged
There is hereby incorporated by reference the information to appear under the caption “Relationship with Independent Auditors” in our Proxy Statement, to be filed with the Securities and Exchange Commission within 120 days after December 31, [removed: 2021.][added: 2022.]
[removed: PART IV][added: PART IV]
| --- | --- |
Item 15. Exhibits and Financial Statement Schedules
70 rewritten, 58 added, 4 removed, 94 unchanged
[removed: (a)] [added: (a)] Documents filed as part of this [removed: report:][added: report:]
[removed: (1)] [added: (1)] Financial [removed: Statements:][added: Statements:]
[removed: (2)] [added: (2)] Financial Statement [removed: Schedules:][added: Schedules:]
[removed: (3) Exhibits:][added: (3) Exhibits:]
| [removed: No.] [added: No.] | | [removed: Description] [added: Description] |
| [removed: 3.2] [added: 4.1] | | [removed: Bylaws] [added: [Description] of [removed: Registrant, as amended,] [added: Securities of the Registrant] previously filed as Exhibit [removed: 3.2] [added: 4.5] to the Company’s Annual Report on Form 10-K for the year ended December 31, [removed: 1987,] [added: 2019,] is incorporated herein by [removed: reference (P).] [added: reference.](https://www.sec.gov/Archives/edgar/data/0000352915/000156459020006793/uhs-ex45_148.htm)] |
| 3.3 | | [Amendment to the Registrant’s Restated Certificate of Incorporation previously filed as Exhibit 3.1 to the Company’s Current Report on Form 8-K dated July 3, 2001 is incorporated herein by [removed: reference.](http://www.sec.gov/Archives/edgar/data/352915/000095013001502858/dex31.txt)] [added: reference.](https://www.sec.gov/Archives/edgar/data/352915/000095013001502858/dex31.txt)] |
| [removed: 4.1] [added: 10.5] | | [removed: [Description of Securities of the Registrant] [added: [Universal Health Services, Inc. Executive Retirement Income Plan dated January 1, 1993,] previously filed as Exhibit [removed: 4.5] [added: 10.7] to the Company’s Annual Report on Form 10-K for the year ended December 31, [removed: 2019,] [added: 2002,] is incorporated herein by [removed: reference.](http://www.sec.gov/Archives/edgar/data/0000352915/000156459020006793/uhs-ex45_148.htm)] [added: reference.](https://www.sec.gov/Archives/edgar/data/0000352915/000093176303000570/dex107.txt)] |
| 4.2 | | [Indenture, dated as of September 21, 2020, by and among the Company, the Subsidiary Guarantors party thereto, MUFG Union Bank, N.A., as trustee, and JPMorgan Chase Bank, N.A., as collateral agent., previously filed as Exhibit 4.1 to the Company’s Current Report on Form 8-K dated September 21, 2020, is incorporated herein by [removed: reference.](http://www.sec.gov/Archives/edgar/data/352915/000156459020044127/uhs-ex41_36.htm)] [added: reference.](https://www.sec.gov/Archives/edgar/data/352915/000156459020044127/uhs-ex41_36.htm)] |
| 4.3 | | [Additional Authorized Representative Joinder Agreement, dated as of September 21, 2020, among the Company, the Subsidiary Guarantors party thereto, JPMorgan Chase Bank, N.A., as collateral agent, the Authorized Representatives specified therein and MUFG Union Bank, N.A., as trustee, as an Additional Authorized Representative, previously filed as Exhibit 4.2 to the Company’s Current Report on Form 8-K dated September 21, 2020, is incorporated herein by [removed: reference](http://www.sec.gov/Archives/edgar/data/0000352915/000156459020044127/uhs-ex42_7.htm).] [added: reference](https://www.sec.gov/Archives/edgar/data/0000352915/000156459020044127/uhs-ex42_7.htm).] |
| 4.4 | | [Registration Rights Agreement, dated as of September 21, 2020, by and among the Company, the Subsidiary Guarantors party thereto, and J.P. Morgan Securities LLC, BofA Securities, Inc. and Goldman Sachs & Co. LLC, as representatives of the several Initial Purchasers, previously filed as Exhibit 10.1 to the Company’s Current Report on Form 8-K dated September 21, 2020, is incorporated herein by [removed: reference.](https://www.sec.gov/Archives/edgar/data/352915/000156459022006717/uhs-ex101_10.htm)] [added: reference.](https://www.sec.gov/Archives/edgar/data/352915/000156459020044127/uhs-ex101_8.htm)] |
| 4.5 | | [Indenture, dated as of August 24, 2021, by and among the Company, the Subsidiary Guarantors party thereto, U.S. Bank National Association, as Trustee, and JPMorgan Chase Bank, N.A., as collateral agent, previously filed as Exhibit 4.1 to the Company’s Current Report on Form 8-K dated August 24, 2021, is incorporated herein by [removed: reference.](http://www.sec.gov/Archives/edgar/data/0000352915/000156459021045588/uhs-ex41_13.htm)] [added: reference.](https://www.sec.gov/Archives/edgar/data/0000352915/000156459021045588/uhs-ex41_13.htm)] |
| 4.6 | | [Additional Authorized Representative Joinder Agreement, dated as of August 24, 2021, among U.S. Bank National Association, as Trustee and Additional Authorized Representative, the Company, the Subsidiary Guarantors party thereto, and JPMorgan Chase Bank, N.A., as collateral agent and administrative agent, previously filed as Exhibit 4.2 to the Company’s Current Report on Form 8-K dated August 24, 2021, is incorporated herein by [removed: reference.](http://www.sec.gov/Archives/edgar/data/0000352915/000156459021045588/uhs-ex42_11.htm)] [added: reference.](https://www.sec.gov/Archives/edgar/data/0000352915/000156459021045588/uhs-ex42_11.htm)] |
| 4.7 | | [Supplemental Indenture, dated as of August 24, 2021, among the Company, the Subsidiary Guarantors party thereto, U.S. Bank National Association (as successor to MUFG Union Bank, N.A.), as trustee, and JPMorgan Chase Bank, N.A., as collateral agent, to the indenture, dated as of September 21, 2020, governing the Existing 2030 Notes, previously filed as Exhibit 4.3 to the Company’s Current Report on Form 8-K dated August 24, 2021, is incorporated herein by [removed: reference.](http://www.sec.gov/Archives/edgar/data/0000352915/000156459021045588/uhs-ex43_9.htm)] [added: reference.](https://www.sec.gov/Archives/edgar/data/0000352915/000156459021045588/uhs-ex43_9.htm)] |
| 4.8 | | [Registration Rights Agreement, dated as of August 24, 2021, by and among the Company, the Subsidiary Guarantors party thereto, and J.P. Morgan Securities LLC, BofA Securities, Inc., Goldman Sachs & Co. LLC and Truist [removed: Securities, Inc., as representatives of the several Initial Purchasers, previously filed as Exhibit 10.1 to the Company’s Current Report on Form 8-K dated August 24, 2021, is incorporated herein by reference.](http://www.sec.gov/Archives/edgar/data/0000352915/000156459021045588/uhs-ex101_12.htm)] [added: Securities,](https://www.sec.gov/Archives/edgar/data/0000352915/000156459021045588/uhs-ex101_12.htm)] |
| 10.1 | | [Agreement, dated [removed: December 1, 2021,] [added: November 30, 2022,] to renew Advisory Agreement dated as of December 24, 1986, and amended and restated effective as of January 1, 2019 between Universal Health Realty Income Trust and UHS of Delaware, [removed: Inc.](https://www.sec.gov/Archives/edgar/data/352915/000156459022006717/uhs-ex103_8.htm)] [added: Inc.](https://www.sec.gov/Archives/edgar/data/352915/000095017023004656/uhs-ex10_1.htm)] |
| 10.2 | | [Agreement, dated as of December 4, 2019, to renew Advisory Agreement, dated as of December 24, 1986, and amended and restated effective as of January 1, 2019 between Universal Health Realty Income Trust and UHS of Delaware, Inc., previously filed as Exhibit 10.3 to the Company’s Annual Report on Form 10-K for the year ended December 31, 2018, is incorporated herein by [removed: reference.](http://www.sec.gov/Archives/edgar/data/0000352915/000156459019004919/uhs-ex103_37.htm)] [added: reference.](https://www.sec.gov/Archives/edgar/data/0000352915/000156459019004919/uhs-ex103_37.htm)] |
| [removed: 10.5] [added: 10.8*] | | [removed: [Universal] [added: [Amended and Restated Universal] Health Services, Inc. [removed: Executive Retirement Income] [added: Supplemental Deferred Compensation] Plan dated [added: as of] January 1, [removed: 1993,] [added: 2002,] previously filed as Exhibit [removed: 10.7] [added: 10.29] to the Company’s Annual Report on Form 10-K for the year ended December 31, 2002, is incorporated herein by [removed: reference.](http://www.sec.gov/Archives/edgar/data/0000352915/000093176303000570/dex107.txt)] [added: reference.](https://www.sec.gov/Archives/edgar/data/0000352915/000093176303000570/dex1029.txt)] |
| 10.6 | | [Universal Health Services, Inc. Supplemental Executive Retirement Income Plan effective as of June 1, 2018, dated as of June 18, 2018, previously filed as Exhibit 10.1 to the Company’s Quarterly Report on Form 10-Q for the quarterly period ended March 31, 2019, is incorporated herein by [removed: reference.](http://www.sec.gov/Archives/edgar/data/0000352915/000156459019017239/uhs-ex101_23.htm)] [added: reference.](https://www.sec.gov/Archives/edgar/data/0000352915/000156459019017239/uhs-ex101_23.htm)] |
| [removed: 10.10*] [added: 10.13] | | [removed: [Amended and Restated] [added: [Amendment No. 1 to the Master Lease Document, between certain subsidiaries of] Universal Health Services, Inc. [removed: Supplemental Deferred Compensation Plan] [added: and Universal Health Realty Income Trust,] dated [removed: as of January 1, 2002,] [added: April 24, 2006,] previously filed as Exhibit 10.29 to the Company’s Annual Report on Form 10-K for the year ended December 31, [removed: 2002,] [added: 2006,] is incorporated herein by [removed: reference.](http://www.sec.gov/Archives/edgar/data/0000352915/000093176303000570/dex1029.txt)] [added: reference.](https://www.sec.gov/Archives/edgar/data/0000352915/000119312507042808/dex1029.htm)] |
| [removed: 10.11*] [added: 10.9*] | | [Universal Health Services, Inc. Employee Stock Purchase Plan, previously filed as Exhibit 4.1 to the Company’s Registration Statement on Form S-8 (File No. 333-122188), dated January 21, 2005 is incorporated herein by [removed: reference.](http://www.sec.gov/Archives/edgar/data/0000352915/000119312505009505/dex41.htm)] [added: reference.](https://www.sec.gov/Archives/edgar/data/0000352915/000119312505009505/dex41.htm)] |
| [removed: 10.12*] [added: 10.10*] | | [Universal Health Services, Inc. Third Amended and Restated 2005 Stock Incentive Plan as Amended, previously filed as Exhibit 99.1 to the Company’s Registration Statement on Form S-8 (File No.333-218359), dated May 31, 2017, is incorporated herein by [removed: reference.](http://www.sec.gov/Archives/edgar/data/0000352915/000119312517188941/d514264dex991.htm)] [added: reference.](https://www.sec.gov/Archives/edgar/data/0000352915/000119312517188941/d514264dex991.htm)] |
| [removed: 10.13*] [added: 10.11*] | | [Form of Stock Option Agreement, previously filed as Exhibit 10.4 to the Company’s Current Report on Form 8-K, dated June 8, 2005, is incorporated herein by [removed: reference.](http://www.sec.gov/Archives/edgar/data/0000352915/000119312505121907/dex104.htm)] [added: reference.](https://www.sec.gov/Archives/edgar/data/0000352915/000119312505121907/dex104.htm)] |
| [removed: 10.14*] [added: 10.12*] | | [Form of Stock Option Agreement for Non-Employee Directors, previously filed as Exhibit 10.2 to the Company’s Current Report on Form 8-K, dated October 3, 2005, is incorporated herein by [removed: reference.](http://www.sec.gov/Archives/edgar/data/0000352915/000119312505195725/dex102.htm)] [added: reference.](https://www.sec.gov/Archives/edgar/data/0000352915/000119312505195725/dex102.htm)] |
| [removed: 10.15] [added: 10.58] | | [removed: [Amendment No. 1 to the Master] [added: [Master] Lease [removed: Document,] [added: Document] between certain subsidiaries of Universal Health Services, Inc. and Universal Health Realty Income Trust, dated [removed: April 24, 2006,] [added: December 31, 2021] previously filed as Exhibit [removed: 10.29] [added: 10.54] to the Company’s Annual Report on Form 10-K [removed: for the year ended December 31, 2006,] [added: dated February 24, 2022,] is incorporated herein by [removed: reference.](http://www.sec.gov/Archives/edgar/data/0000352915/000119312507042808/dex1029.htm)] [added: reference.](https://www.sec.gov/Archives/edgar/data/352915/000156459022006717/uhs-ex1054_42.htm)] |
| [removed: 10.16*] [added: 10.14*] | | [Amended and Restated Universal Health Services, Inc. 2010 Employees’ Restricted Stock Purchase Plan, previously filed as Exhibit 10.2 to the Company’s Quarterly Report on Form 10-Q filed on August 7, 2015, is incorporated herein by [removed: reference.](http://www.sec.gov/Archives/edgar/data/0000352915/000119312515281740/d941004dex102.htm)] [added: reference.](https://www.sec.gov/Archives/edgar/data/0000352915/000119312515281740/d941004dex102.htm)] |
| [removed: 10.17*] [added: 10.15*] | | [Universal Health Services, Inc. 2010 Executive Incentive Plan, previously filed as Exhibit 10.3 to the Company’s Quarterly Report on Form 10-Q filed on August 7, 2015, is incorporated herein by [removed: reference.](http://www.sec.gov/Archives/edgar/data/0000352915/000119312515281740/d941004dex103.htm)] [added: reference.](https://www.sec.gov/Archives/edgar/data/0000352915/000119312515281740/d941004dex103.htm)] |
| [removed: 10.18] [added: 10.16] | | [Omnibus Amendment to Receivables Sale Agreements, dated as of October 27, 2010, previously filed as Exhibit 10.1 to the Company’s Current Report on Form 8-K dated November 2, 2010, is incorporated herein by [removed: reference.](http://www.sec.gov/Archives/edgar/data/0000352915/000119312510243987/dex101.htm)] [added: reference.](https://www.sec.gov/Archives/edgar/data/0000352915/000119312510243987/dex101.htm)] |
| [removed: 10.19] [added: 10.17] | | [Amended and Restated Credit and Security Agreement, dated as of October 27, 2010, previously filed as Exhibit 10.2 to the Company’s Current Report on Form 8-K dated November 2, 2010, is incorporated herein by [removed: reference.](http://www.sec.gov/Archives/edgar/data/0000352915/000119312510243987/dex102.htm)] [added: reference.](https://www.sec.gov/Archives/edgar/data/0000352915/000119312510243987/dex102.htm)] |
| [removed: 10.20] [added: 10.18] | | [Second Amendment to Amended and Restated Credit and Security Agreement, dated as of October 25, 2013, previously filed as Exhibit 10.1 to the Company’s Current Report on Form 8-K dated October 30, 2013, is incorporated herein by [removed: reference.](http://www.sec.gov/Archives/edgar/data/0000352915/000119312513417091/d619136dex101.htm)] [added: reference.](https://www.sec.gov/Archives/edgar/data/0000352915/000119312513417091/d619136dex101.htm)] |
| [removed: 10.21] [added: 10.19] | | [Third Amendment to Amended and Restated Credit and Security Agreement, dated as of August 1, 2014, previously filed as Exhibit 10.1 to the Company’s Current Report on Form 8-K dated August 4, 2014, is incorporated herein by [removed: reference.](http://www.sec.gov/Archives/edgar/data/0000352915/000119312514293450/d768656dex101.htm)] [added: reference.](https://www.sec.gov/Archives/edgar/data/0000352915/000119312514293450/d768656dex101.htm)] |
| [removed: 10.22] [added: 10.20] | | [Fourth Amendment to Amended and Restated Credit and Security Agreement, dated as of December 22, 2015, previously filed as Exhibit 10.1 to the Company’s Current Report on Form 8-K dated December 22, 2015, is incorporated herein by [removed: reference](http://www.sec.gov/Archives/edgar/data/0000352915/000119312515416088/d106645dex101.htm).] [added: reference](https://www.sec.gov/Archives/edgar/data/0000352915/000119312515416088/d106645dex101.htm).] |
| [removed: 10.23] [added: 10.21] | | [Fifth Amendment to Amended and Restated Credit and Security Agreement, dated as of July 7, 2017, previously filed as Exhibit 10.1 to the Company’s Quarterly Report on Form 10-Q filed on August 7, 2017, is incorporated herein by [removed: reference.](http://www.sec.gov/Archives/edgar/data/0000352915/000156459017016003/uhs-ex101_20.htm)] [added: reference.](https://www.sec.gov/Archives/edgar/data/0000352915/000156459017016003/uhs-ex101_20.htm)] |
| [removed: 10.24] [added: 10.22] | | [Sixth Amendment to Amended and Restated Credit and Security Agreement, dated as of April 26, 2018, previously filed as Exhibit 10.1 to the Company’s Current Report on Form 8-K dated April 27, 2018, is incorporated herein by [removed: reference.](http://www.sec.gov/Archives/edgar/data/0000352915/000156459018009467/uhs-ex101_6.htm)] [added: reference.](https://www.sec.gov/Archives/edgar/data/0000352915/000156459018009467/uhs-ex101_6.htm)] |
| [removed: 10.25] [added: 10.23] | | [removed: [Seventh] [added: [Eighth] Amendment to Amended and Restated Credit and Security Agreement, dated as of April 26, 2021, previously filed as Exhibit 10.1 to the Company’s Quarterly Report on Form 10-Q dated May 7, 2021, is incorporated herein by [removed: reference.](http://www.sec.gov/Archives/edgar/data/0000352915/000156459021025562/uhs-ex101_23.htm)] [added: reference.](https://www.sec.gov/Archives/edgar/data/352915/000156459021025562/uhs-ex101_23.htm)] |
| [removed: 10.26] [added: 10.27] | | [Assignment and Assumption Agreement, dated as of October 27, 2010, previously filed as Exhibit 10.3 to the Company’s Current Report on Form 8-K dated November 2, 2010, is incorporated herein by [removed: reference.](http://www.sec.gov/Archives/edgar/data/0000352915/000119312510243987/dex103.htm)] [added: reference.](https://www.sec.gov/Archives/edgar/data/0000352915/000119312510243987/dex103.htm)] |
| [removed: 10.27] [added: 10.28] | | [Credit Agreement, dated as of November 15, 2010, by and among Universal Health Services, Inc., JPMorgan Chase Bank, N.A. and the various financial institutions as are or may become parties thereto, as Lenders, SunTrust Bank, The Royal Bank of Scotland, Plc, Bank of Tokyo-Mitsubishi UFJ Trust Company and Credit Agricole Corporate and Investment Bank, as co-documentation agents, Deutsche Bank Securities Inc. and Bank of America N.A. as co-syndication agents, and JPMorgan Chase Bank, N.A., as administrative agent for the Lenders and as collateral agent for the secured parties, previously filed as Exhibit 10.1 to the Company’s Current Report on Form 8-K dated November 17, 2010, is incorporated herein by [removed: reference.](http://www.sec.gov/Archives/edgar/data/0000352915/000095015710002042/ex10-1.htm)] [added: reference.](https://www.sec.gov/Archives/edgar/data/0000352915/000095015710002042/ex10-1.htm)] |
| [removed: 10.28] [added: 10.29] | | [First Amendment, dated as of March 15, 2011, to the Credit Agreement, dated as of November 15, 2010, by and among Universal Health Services, Inc., JPMorgan Chase Bank, N.A. and the various financial institutions as are or may become parties thereto, as Lenders, certain banks as co-documentation agents, and as co-syndication agents, and JPMorgan Chase Bank, N.A., as administrative agent for the Lenders and as collateral agent for the secured parties, previously filed as Exhibit 10.1 to the Company’s Current Report on Form 8-K dated March 15, 2011, is incorporated herein by [removed: reference.](http://www.sec.gov/Archives/edgar/data/0000352915/000119312511067583/dex101.htm)] [added: reference.](https://www.sec.gov/Archives/edgar/data/0000352915/000119312511067583/dex101.htm)] |
| [removed: 10.29] [added: 10.30] | | [Credit Agreement, dated as of November 15, 2010 and amended and restated as of September 21, 2012, by and among Universal Health Services, Inc. (the borrower), the several lenders from time to time parties thereto, Credit Agricole Corporate and Investment Bank, Mizuho Corporate Bank LTD., Royal Bank of Canada and The Royal Bank of Scotland PLC (as co-documentation agents), Bank of Tokyo-Mitsubishi UFJ Trust Company, Bank of America N.A. and SunTrust Bank (as co-syndication agents), and JPMorgan Chase Bank, N.A. (as administrative agent), previously filed as Exhibit 10.1 to the Company’s Current Report on Form 8-K dated September 26, 2012, is incorporated herein by [removed: reference.](http://www.sec.gov/Archives/edgar/data/0000352915/000119312512404549/d415922dex101.htm)] [added: reference.](https://www.sec.gov/Archives/edgar/data/0000352915/000119312512404549/d415922dex101.htm)] |
| [removed: 10.30] [added: 10.31] | | [Second Amendment, dated as of September 21, 2012, to the Credit Agreement, dated as of November 15, 2010 (as amended from time to time), among Universal Health Services, Inc., a Delaware corporation, the several banks and other financial institutions from time to time parties thereto, JPMorgan Chase Bank, N.A., as administrative agent and the other agents party thereto, previously filed as Exhibit 10.2 to the Company’s Current Report on Form 8-K dated September 26, 2012, is incorporated herein by [removed: reference.](http://www.sec.gov/Archives/edgar/data/0000352915/000119312512404549/d415922dex102.htm)] [added: reference.](https://www.sec.gov/Archives/edgar/data/0000352915/000119312512404549/d415922dex102.htm)] |
| 3.2 | | [Amended and Restated Bylaws of Registrant, previously filed as Exhibit 3.1 to the Company’s Current Report on Form 8-K dated September 21, 2022, is incorporated herein by reference.](https://www.sec.gov/Archives/edgar/data/352915/000156459022032142/uhs-ex31_9.htm) |
| No. | | Description |
| | | [Inc., as representatives of the several Initial Purchasers, previously filed as Exhibit 10.1 to the Company’s Current Report on Form 8-K dated August 24, 2021, is incorporated herein by reference.](https://www.sec.gov/Archives/edgar/data/0000352915/000156459021045588/uhs-ex101_12.htm) |
| 4.9 | | [Second Supplemental Indenture, dated as of June 23, 2022, among the Company, the Subsidiary Guarantors party thereto, U.S. Bank Trust Company, National Association (as successor to U.S. Bank National Association), as trustee, and JPMorgan Chase Bank, N.A., as collateral agent, to the indenture, dated as of September 21, 2020, previously filed as Exhibit 4.1 to the Company’s Current Report on Form 8-K dated June 27, 2022, is incorporated herein by reference.](https://www.sec.gov/Archives/edgar/data/352915/000156459022024223/uhs-ex41_9.htm) |
| 4.10 | | [First Supplemental Indenture, dated as of June 23, 2022, among the Company, the Subsidiary Guarantors party thereto, U.S. Bank Trust Company, National Association (as successor to U.S. Bank National Association), as trustee, and JPMorgan Chase Bank, N.A., as collateral agent, to the indenture, dated as of August 24, 2021, previously filed as Exhibit 4.2 to the Company’s Current Report on Form 8-K dated June 27, 2022, is incorporated herein by reference.](https://www.sec.gov/Archives/edgar/data/352915/000156459022024223/uhs-ex42_7.htm) |
| 4.11 | | [Third Supplemental Indenture, dated as of November 4, 2022, among the Company, the Subsidiary Guarantors party thereto, U.S. Bank Trust Company, National Association (as successor to U.S. Bank National Association), as trustee, and JPMorgan Chase Bank, N.A., as collateral agent, to the indenture, dated as of September 21, 2020, previously filed as Exhibit 4.1 to the Company’s Quarterly Report on Form 10-Q dated November 8, 2022, is incorporated herein by reference.](https://www.sec.gov/Archives/edgar/data/352915/000156459022037046/uhs-ex41_48.htm) |
| 4.12 | | [Second Supplemental Indenture, dated as of November 4, 2022, among the Company, the Subsidiary Guarantors party thereto, U.S. Bank Trust Company, National Association (as successor to U.S. Bank National Association), as trustee, and JPMorgan Chase Bank, N.A., as collateral agent, to the indenture, dated as of August 24, 2021, previously filed as Exhibit 4.2 to the Company’s Quarterly Report on Form 10-Q dated November 8, 2022, is incorporated herein by reference.](https://www.sec.gov/Archives/edgar/data/352915/000156459022037046/uhs-ex42_47.htm) |
| No. | | Description |
| 10.24 | | [Ninth Amendment to Amended and Restated Credit and Security Agreement, dated as of April 22, 2022. previously filed as Exhibit 10.1 to the Company’s Quarterly Report on Form 10-Q for the Quarter dated May 6, 2022, is incorporated herein by reference.](https://www.sec.gov/Archives/edgar/data/352915/000156459022018570/uhs-ex101_24.htm) |
| No. | | Description |
| 10.25 | | [Tenth Amendment to Amended and Restated Credit and Security Agreement, dated as of July 22, 2022, previously filed as Exhibit 10.5 to the Company’s Quarterly Report on Form 10-Q dated August 8, 2022, is incorporated herein by reference.](https://www.sec.gov/Archives/edgar/data/352915/000156459022028437/uhs-ex105_27.htm) |
| 10.26 | | [Eleventh Amendment to Amended and Restated Credit and Security Agreement, dated as of September 20, 2022, previously filed as Exhibit 10.2 to the Company’s Quarterly Report on Form 10-Q dated November 8, 2022, is incorporated herein by reference.](https://www.sec.gov/Archives/edgar/data/352915/000156459022037046/uhs-ex102_25.htm) |
| 10.35 | | [Fifth Amendment to the Credit Agreement, dated as of November 15, 2010, as amended on March 15, 2011, September 21, 2012, May 16, 2013 and August 7, 2014, among the Company, as borrower, the several banks and other financial](https://www.sec.gov/Archives/edgar/data/0000352915/000119312516616699/d200774dex101.htm) |
| No. | | Description |
| | | [institutions from time to time parties thereto, as lenders, JPMorgan Chase Bank, N.A., as administrative agent, and the other agents party thereto, previously filed as Exhibit 10.1 to the Company’s Current Report on Form 8-K dated June 8, 2016, is incorporated herein by reference.](https://www.sec.gov/Archives/edgar/data/0000352915/000119312516616699/d200774dex101.htm) |
| No. | | Description |
| | | [Trustee, and JPMorgan Chase Bank, N.A., as collateral agent, previously filed as Exhibit 10.4 to the Company’s Current Report on Form 8-K dated August 12, 2014, is incorporated herein by reference.](https://www.sec.gov/Archives/edgar/data/0000352915/000119312514306618/d773872dex104.htm) |
| 10.55* | | [Amendment, dated as of March 23, 2022, to Employment Agreement, dated as of December 23, 2020, between Universal Health Services, Inc. and Marc D. Miller, previously filed as Exhibit 10.2 to the Company’s Current Report on Form 8-K dated March 23, 2022, is incorporated herein by reference.](https://www.sec.gov/Archives/edgar/data/352915/000156459022011986/uhs-ex102_7.htm) |
| --- | --- | --- |
| No. | | Description |
| | | |
| 10.57* | | [Amendment, dated as of March 23, 2022, to Employment Agreement, dated as of December 23, 2020, between Universal Health Services, Inc. and Alan B. Miller, previously filed as Exhibit 10.3 to the Company’s Current Report on Form 8-K dated March 23, 2022, is incorporated herein by reference.](https://www.sec.gov/Archives/edgar/data/352915/000156459022011986/uhs-ex103_8.htm) |
| | | |
| | | |
| 10.59* | | [Universal Health Services, Inc. 2022 Executive Incentive Plan, previously filed as Exhibit 10.1 to the Company’s Current Report on Form 8-K dated March 23, 2022, is incorporated herein by reference.](https://www.sec.gov/Archives/edgar/data/352915/000156459022011986/uhs-ex101_6.htm) |
| | | |
| 10.60 | | [Universal Health Services, Inc. Amended and Restated 2020 Omnibus Stock and Incentive Plan, previously filed as Exhibit 99.1 to the Company’s Registration Statement on Form S-8 (File No. 333-265495) dated June 9, 2022, is incorporated herein by reference.](https://www.sec.gov/Archives/edgar/data/352915/000156459022022864/uhs-ex991_6.htm) |
| | | |
| 10.61 | | [Form of Restricted Stock Unit Award Agreement under the Universal Health Services, Inc. 2020 Omnibus Stock and Incentive Plan, previously filed as Exhibit 10.4 to the Company’s Quarterly Report on Form 10-Q filed on August 8, 2022, is incorporated herein by reference.](https://www.sec.gov/Archives/edgar/data/352915/000156459022028437/uhs-ex104_238.htm) |
| | | |
| 10.62* | | [Form of Restricted Stock Units Award Agreement for Named Executive Officers with Employment Agreements, , previously filed as Exhibit 10.5 to the Company’s Quarterly Report on Form 10-Q filed on May 6, 2022, is incorporated herein by reference.](https://www.sec.gov/Archives/edgar/data/352915/000156459022018570/uhs-ex105_113.htm) |
| | | |
| 10.63* | | [Form of Restricted Stock Units Award Agreement for Named Executive Officers without Employment Agreements, previously filed as Exhibit 10.6 to the Company’s Quarterly Report on Form 10-Q filed on May 6, 2022, is incorporated herein by reference.](https://www.sec.gov/Archives/edgar/data/352915/000156459022018570/uhs-ex106_115.htm) |
| | | |
| 10.64* | | [Form of Restricted Stock Units Award Agreement for Directors, previously filed as Exhibit 10.7 to the Company’s Quarterly Report on Form 10-Q filed on May 6, 2022, is incorporated herein by reference.](https://www.sec.gov/Archives/edgar/data/352915/000156459022018570/uhs-ex107_114.htm) |
| | | |
| 10.65* | | [Separation Agreement and General Release by and between UHS of Delaware, Inc. and Marvin Pember effective as of December 31, 2022, previously filed as Exhibit 99.1 to the Company’s Current Report on Form 8-K/A dated December 7, 2022, is incorporated herein by reference.](https://www.sec.gov/Archives/edgar/data/352915/000156459022039115/uhs-ex991_6.htm) |
| | | |
| 10.66* | | [Employment Agreement between Universal Health Services, Inc. and Edward Sim dated October 18, 2022.](https://www.sec.gov/Archives/edgar/data/0000352915/000156459020058584/uhs-ex101_6.htm) |
| | | |
| --- | --- |
| 10.8 | | Agreement of Limited Partnership of District Hospital Partners, L.P. (a District of Columbia limited partnership) by and among UHS of D.C., Inc. and The George Washington University, previously filed as Exhibit 10.1 to the Company’s Quarterly Report on Form 10-Q for the quarters ended March 30, 1997, and June 30, 1997, is incorporated herein by reference (P). |
| 10.9 | | Contribution Agreement between The George Washington University (a congressionally chartered institution in the District of Columbia) and District Hospital Partners, L.P. (a District of Columbia limited partnership), previously filed as Exhibit 10.3 to the Company’s Quarterly Report on Form 10-Q for the quarter ended June 30, 1997, is incorporated herein by reference (P). |
| 10.54 | | [Master Lease Document between certain subsidiaries of Universal Health Services, Inc. and Universal Health Realty Income Trust, dated December 31, 2021.](https://www.sec.gov/Archives/edgar/data/352915/000156459022006717/uhs-ex1054_42.htm) |
An excerpt. Shown here: 40 of 70 rewritten, 40 of 58 added and all 4 removed. The counts are complete. For every sentence, read Item 15. Exhibits and Financial Statement Schedules in the FY2022 filing and the FY2021 filing.
Item 16. Form 10-K Summary
676 rewritten, 253 added, 192 removed, 582 unchanged
[removed: Pursuant] [added: Pursuant] to the requirements of Section 13 or 15(d) of the Securities Exchange Act of 1934, the Registrant has duly caused this report to be signed on its behalf by the undersigned, thereunto duly [removed: authorized.][added: authorized.]
| | | [removed: Marc] [added: Marc] D. [removed: Miller Chief] [added: Miller Chief] Executive [removed: Officer] [added: Officer February 27, 2023] |
[removed: Pursuant] [added: Pursuant] to the requirements of the Securities Exchange Act of 1934, this report has been signed below by the following persons on behalf of the Registrant and in the capacities and on the dates [removed: indicated.][added: indicated.]
| | [removed: Signatures |] [added: Signatures] | | | [removed: Title] | [added: Title] | | | [removed: Date] | [added: Date] | |
| /s/ ALAN B. MILLER [removed: Alan] [added: Alan] B. [removed: Miller] [added: Miller] | | | | Executive Chairman of the Board | | | | February [removed: 24, 2022 |] [added: 27, 2023] | | |
| /s/ MARC D. MILLER [removed: Marc] [added: Marc] D. [removed: Miller] [added: Miller] | | | | Director, President and Chief Executive Officer (Principal Executive Officer) | | | | February [removed: 24, 2022 |] [added: 27, 2023] | | |
| /s/ LAWRENCE S. GIBBS [removed: Lawrence S. Gibbs] | | | | Director | | | | February [removed: 24, 2022 |] [added: 27, 2023] | | |
| /s/ EILEEN C. MCDONNELL [removed: Eileen] [added: Eileen] C. [removed: McDonnell] [added: McDonnell] | | | | Director | | | | February [removed: 24, 2022 |] [added: 27, 2023] | | |
| /s/ WARREN J. NIMETZ [removed: Warren] [added: Warren] J. [removed: Nimetz] [added: Nimetz] | | | | Director | | | | February [removed: 24, 2022 |] [added: 27, 2023] | | |
| /s/ MARIA SINGER [removed: Maria Singer] [added: Maria Singer] | | | | Director | | | | February [removed: 24, 2022 |] [added: 27, 2023] | | |
| /s/ ELLIOTT J. SUSSMAN M.D. [removed: Elliot] [added: Elliot] J. Sussman [removed: M.D.] [added: M.D.] | | | | Director | | | | February [removed: 24, 2022 |] [added: 27, 2023] | | |
| /s/ STEVE FILTON [removed: Steve Filton] [added: Steve Filton] | | | | Executive Vice President, Chief Financial Officer and Secretary (Principal Financial and Accounting Officer) | | | | February [removed: 24, 2022 |] [added: 27, 2023] | | |
[removed: INDEX] [added: INDEX] TO FINANCIAL [removed: STATEMENTS][added: STATEMENTS]
[removed: AND] [added: AND] FINANCIAL STATEMENT [removed: SCHEDULE][added: SCHEDULE]
| [Report of Independent Registered Public Accounting [removed: Firm](#ReportofIndependentRegisteredPublic)] [added: Firm](#reportofindependentregisteredpublic)] (PCAOB ID: 238) | [removed: 2] [added: 89] |
| [Consolidated Statements of Income for December 31, [added: 2022,] 2021, [removed: 2020,] and [removed: 2019](#CONSOLIDATED_STATEMENTS_INCOME)] [added: 2020](#consolidated_statements_income)] | [removed: 2] [added: 91] |
| [Consolidated Statements of Comprehensive Income for December 31, [added: 2022,] 2021, [removed: 2020,] and [removed: 2019](#CONSOLIDATED_STATEMENTS_COMPREHENSIVE_IN)] [added: 2020](#consolidated_statements_comprehensive_in)] | [removed: 2] [added: 92] |
| [Consolidated Balance Sheets as of December 31, [removed: 2021] [added: 2022] and [removed: 2020](#CONSOLIDATED_BALANCE_SHEETS)] [added: 2021](#consolidated_balance_sheets)] | [removed: 2] [added: 93] |
| [Consolidated Statements of Changes in Equity for December 31, [removed: 2021, 2010] [added: 2022, 2021] and [removed: 2019](#CONSOLIDATED_STATEMENTS_CHANGES_IN_EQUIT)] [added: 2020](#consolidated_statements_changes_in_equit)] | [removed: 2] [added: 94] |
| [Consolidated Statements of Cash Flows for December 31, [removed: 2021, 2020] [added: 2022, 2021] and [removed: 2019](#CONSOLIDATED_STATEMENTS_CASH_FLOWS)] [added: 2020](#consolidated_statements_cash_flows)] | [removed: 2] [added: 97] |
| [Notes to Consolidated Financial [removed: Statements](#NOTES_TO_CONSOLIDATED_FINANCIAL_STATEMEN)] [added: Statements](#notes_to_consolidated_financial_statemen)] | [removed: 2] [added: 98] |
| [Supplemental Financial Statement Schedule II: Valuation and Qualifying Accounts as of and for December 31, [added: 2022,] 2021, [removed: 2020,] and [removed: 2019](#SCHEDULEII_VALUATION)] [added: 2020](#scheduleii_valuation)] | [removed: 2] [added: 128] |
[removed: Report] [added: Report] of Independent Registered Public Accounting [removed: Firm][added: Firm]
[removed: Opinions] [added: Opinions] on the Financial Statements and Internal Control over Financial [removed: Reporting][added: Reporting]
We have audited the accompanying consolidated balance sheets of Universal Health Services, Inc. and its subsidiaries (the “Company”) as of December 31, [removed: 2021] [added: 2022] and [removed: 2020,] [added: 2021,] and the related consolidated statements of income, of comprehensive income, of changes in equity and of cash flows for each of the three years in the period ended December 31, [removed: 2021,] [added: 2022,] including the related notes and financial statement schedule listed in the accompanying index (collectively referred to as the “consolidated financial statements”).
We also have audited the Company's internal control over financial reporting as of December 31, [removed: 2021,] [added: 2022,] based on criteria established in [removed: *Internal] [added: Internal] Control - Integrated [removed: Framework*] [added: Framework] (2013) issued by the Committee of Sponsoring Organizations of the Treadway Commission (COSO).
In our opinion, the consolidated financial statements referred to above present fairly, in all material respects, the financial position of the Company as of December 31, [removed: 2021] [added: 2022] and [removed: 2020,] [added: 2021,] and the results of its operations and its cash flows for each of the three years in the period ended December 31, [removed: 2021] [added: 2022] in conformity with accounting principles generally accepted in the United States of America.
Also in our opinion, the Company maintained, in all material respects, effective internal control over financial reporting as of December 31, [removed: 2021,] [added: 2022,] based on criteria established in [removed: *Internal] [added: Internal] Control - Integrated [removed: Framework*] [added: Framework] (2013) issued by the COSO.
[removed: Basis] [added: Basis] for [removed: Opinions][added: Opinions]
[removed: Definition] [added: Definition] and Limitations of Internal Control over Financial [removed: Reporting][added: Reporting]
[removed: Critical] [added: Critical] Audit [removed: Matters][added: Matters]
The critical audit matter communicated below is a matter arising from the current period audit of the consolidated financial statements that was communicated or required to be communicated to the audit committee and that (i) relates to accounts or disclosures that are [removed: material to the consolidated financial statements and (ii) involved our especially challenging, subjective, or complex judgments.]
[added: The] communication of critical audit matters does not alter in any way our opinion on the consolidated financial statements, taken as a whole, and we are not, by communicating the critical audit matter below, providing a separate opinion on the critical audit matter or on the accounts or disclosures to which it relates.
[removed: Valuation] [added: *Valuation] of accounts [removed: receivable][added: receivable*]
As of December 31, [removed: 2021,] [added: 2022,] the net accounts receivable balance was [removed: $1.7] [added: $2.0] billion.
Developing an independent expectation involved calculating the percentage of cash collections as compared to the recorded net accounts receivable balance as of the end of the prior year, applying those calculated percentages to the recorded accounts receivable balance as of December 31, [removed: 2021,] [added: 2022,] and comparing the calculated balance to management’s estimate of the net accounts receivable balance.
[removed: UNIVERSAL] [added: UNIVERSAL] HEALTH SERVICES, INC. AND [removed: SUBSIDIARIES][added: SUBSIDIARIES]
[removed: CONSOLIDATED STATEMENTS OF INCOME][added: CONSOLIDATED STATEMENTS OF COMPREHENSIVE INCOME]
| | | [removed: Year] [added: Year] Ended December [removed: 31,] [added: 31,] | | | | | | | | | | |
| | | [removed: 2021] [added: 2022] | | | | [removed: 2020] [added: 2021] | | | | [removed: 2019] [added: 2020] | | |
SIGNATURES
| | | | | | | | | | | |
| --- | --- | --- | --- | --- | --- | --- | --- | --- | --- | --- |
| | | | | | | | | | | |
| | | | | | | | | | | |
| | | | | | | | | | | |
| | | | | | | | | | | |
| /s/ NINA CHEN\-LANGENMAYR | | | | Director | | | | February 27, 2023 | | |
| Nina Chen-Langenmayr | | | | | | | | | | |
| | | | | | | | | | | |
| Lawrence S. Gibbs | | | | | | | | | | |
| | | | | | | | | | | |
| | | | | | | | | | | |
| | | | | | | | | | | |
| | | | | | | | | | | |
| | | | | | | | | | | |
| | |
material to the consolidated financial statements and (ii) involved our especially challenging, subjective, or complex judgments.
February 27, 2023
CONSOLIDATED STATEMENTS OF INCOME
| | | | | | | | | | | | | |
| | | | | | | | | | | | | |
| | | | | | | | | |
| | | 2022 | | | | 2021 | | |
| | | | 10,523,027 | | | | 10,105,220 | |
| | | | 5,355,633 | | | | 5,208,793 | |
| | | | 5,918,458 | | | | 5,874,275 | |
| | | | 5,038,390 | | | | 4,955,712 | |
| | | | | | | | | |
| | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | |
UNIVERSAL HEALTH SERVICES, INC. AND SUBSIDIARIES
(in thousands)
| | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | |
| | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | Accumulated | | | | UHS | | | | | | | | | | |
| | | Redeemable | | | | | | | | | | | | | | | | | | | | | | | | | | | | Other | | | | Common | | | | | | | | | | |
| | | Noncontrolling | | | | Class A | | | | Class B | | | | Class C | | | | Class D | | | | Cumulative | | | | Retained | | | | Comprehensive | | | | Stockholders' | | | | Noncontrolling | | | | | | |
| | | Interest | | | | Common | | | | Common | | | | Common | | | | Common | | | | Dividends | | | | Earnings | | | | Income (Loss) | | | | Equity | | | | Interest | | | | Total | | |
UNIVERSAL HEALTH SERVICES, INC. AND SUBSIDIARIES
CONSOLIDATED STATEMENTS OF CHANGES IN EQUITY—(Continued)
(in thousands)
| --- | --- |
SIGNATURES
| --- | --- | --- |
February 24, 2022
| | | | | | | | | | | | |
| --- | --- | --- | --- | --- | --- | --- | --- | --- | --- | --- | --- |
The
| | | | 10,105,220 | | | | 9,378,486 | |
| | | | 5,208,793 | | | | 4,865,722 | |
| | | | 5,874,275 | | | | 5,373,124 | |
| | | | 4,955,712 | | | | 4,821,886 | |
| Balance, January 1, 2019 | | $ | 4,292 | | | $ | 66 | | | $ | 841 | | | $ | 7 | | | $ | 0 | | | $ | (409,156 | ) | | $ | 5,793,262 | | | $ | 4,242 | | | $ | 5,389,262 | | | $ | 76,531 | | | $ | 5,465,793 | |
| Repurchased | | | — | | | | — | | | | (57 | ) | | | — | | | | — | | | | — | | | | (753,870 | ) | | | — | | | | (753,927 | ) | | | — | | | | (753,927 | ) |
| Comprehensive income: | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | | |
| Net income to UHS / noncontrolling interests | | | 541 | | | | — | | | | — | | | | — | | | | — | | | | — | | | | 814,854 | | | | — | | | | 814,854 | | | | 12,148 | | | | 827,002 | |
| Unrealized derivative gains on cash flow hedges (net of income tax effect of $928) | | | — | | | | — | | | | — | | | | — | | | | — | | | | — | | | | — | | | | (2,997 | ) | | | (2,997 | ) | | | — | | | | (2,997 | ) |
| Subtotal - comprehensive income | | | 541 | | | | — | | | | — | | | | — | | | | — | | | | — | | | | 814,854 | | | | 27,651 | | | | 842,505 | | | | 12,148 | | | | 854,653 | |
| Medicare accelerated payments and deferred CARES Act and other grants | | | (698,762 | ) | | | 698,768 | | | | 0 | |
See *Provision for Asset Impairment-Foundations Recovery Network,* in *Other Assets and Intangible Assets* below, for additional disclosure related to a provision for asset impairment recorded during 2019 to reduce the carrying value of real property assets of certain Foundations Recovery Network, L.L.C. facilities.
| Balance, January 1, 2020 | | $ | 448,415 | | | $ | 3,421,345 | | | $ | 3,869,760 | |
| Adjustments to goodwill (a) | | | (1,521 | ) | | | 14,349 | | | | 12,828 | |
There was no impairment recorded during 2020.
During 2019 we recorded provisions for asset impairments related to Foundations Recovery Network, L.L.C., as discussed below.
Provision for Asset Impairment-Foundations Recovery Network:
Our financial results for the year ended December 31, 2019 include a pre-tax provisions for asset impairment of approximately $98 million recorded in connection with Foundations Recovery Network, L.L.C. (“Foundations”), which was acquired by us in 2015.
This provision for asset impairment includes: (i) a $75 million impairment provision to write-off the carrying value of the Foundations’ tradename intangible asset, and; (ii) a $23 million impairment provision to reduce the carrying value of real property assets of certain Foundations’ facilities.
The provision for asset impairment recorded during 2019, which is included in other operating expenses in the accompanying consolidated statements of income, was recorded after evaluation of the estimated fair value of the Foundations’ tradename as well as certain related real property assets.
The provision for asset impairment was impacted by the following: (i) decisions made by management during 2019 to cancel the opening of future planned de novo facilities; (ii) reductions in projected future patient volumes, revenues and cash flows resulting from continued operating trends and financial results experienced by existing facilities that significantly lagged expectations, and; (iii) competitive pressures experienced in certain markets that were deemed to be permanent.
| Balance, January 1, 2020, net of income tax | | $ | (17 | ) | | $ | 39,568 | | | $ | (7,658 | ) | | $ | 31,893 | |
| 2020 activity: | | | | | | | | | | | | | | | | |
| Pretax amount | | | 0 | | | | 13,619 | | | | 4,428 | | | | 18,047 | |
| Income tax effect | | | 0 | | | | (749 | ) | | | (1,071 | ) | | | (1,820 | ) |
Cash flow hedges are accounted for by recording the fair value
As of December 31, 2020, $372 million of the MAAPP funds were included in the current liabilities in our consolidated balance sheet and $323 million were included noncurrent liabilities.
Recent Accounting Standards: In March 2020, the FASB issued ASU 2020-04, “Facilitation of the Effects of Reference Rate Reform on Financial Reporting.” The ASU is intended to provide temporary optional expedients and exceptions to the US GAAP guidance on contract modifications and hedge accounting to ease the financial reporting burdens related to the expected market transition from LIBOR and other interbank offered rates to alternative reference rates.
This guidance was effective beginning on March 12, 2020, and the Company may elect to apply the amendments prospectively through December 31, 2022.
The Company is currently evaluating the impact this guidance may have on our consolidated financial statements.
Cash Flow Hedges:
During 2019, we had nine interest rate swaps outstanding, all of which expired on April 15, 2019, whereby we paid a fixed rate on a total notional amount of $1.0 billion and received one-month LIBOR.
The average fixed rate payable on these swaps was 1.31%.
An excerpt. Shown here: 40 of 676 rewritten, 40 of 253 added and 40 of 192 removed. The counts are complete. For every sentence, read Item 16. Form 10-K Summary in the FY2022 filing and the FY2021 filing.